Skeletal Tissues and Bone Fractures: Anatomy, Mechanics, and Pathology
An in-depth exploration of the human skeletal system, covering bone tissue types (cortical and cancellous), connective tissues, the mechanics of bone fractures, factors influencing fracture resistance, and classifications of fractures. It also discusses bone health conditions like osteopenia and osteoporosis.
The human skeletal system is far more than a static framework; it is a dynamic, living organ system that responds constantly to the mechanical demands placed upon it. By balancing structural rigidity with the ability to absorb energy, bones allow for movement, protect vital organs, and serve as a reservoir for essential minerals. Understanding how these tissues are organized and how they fail under stress is fundamental to the study of biomechanics and clinical orthopedics.
The Architecture of Bone
Bone is a complex, anisotropic structure, meaning its mechanical properties—such as strength and stiffness—change depending on the direction of the applied force. This anisotropy is a result of how the bone is organized into two distinct types of tissue: cortical and cancellous bone.
Cortical vs. Cancellous Bone
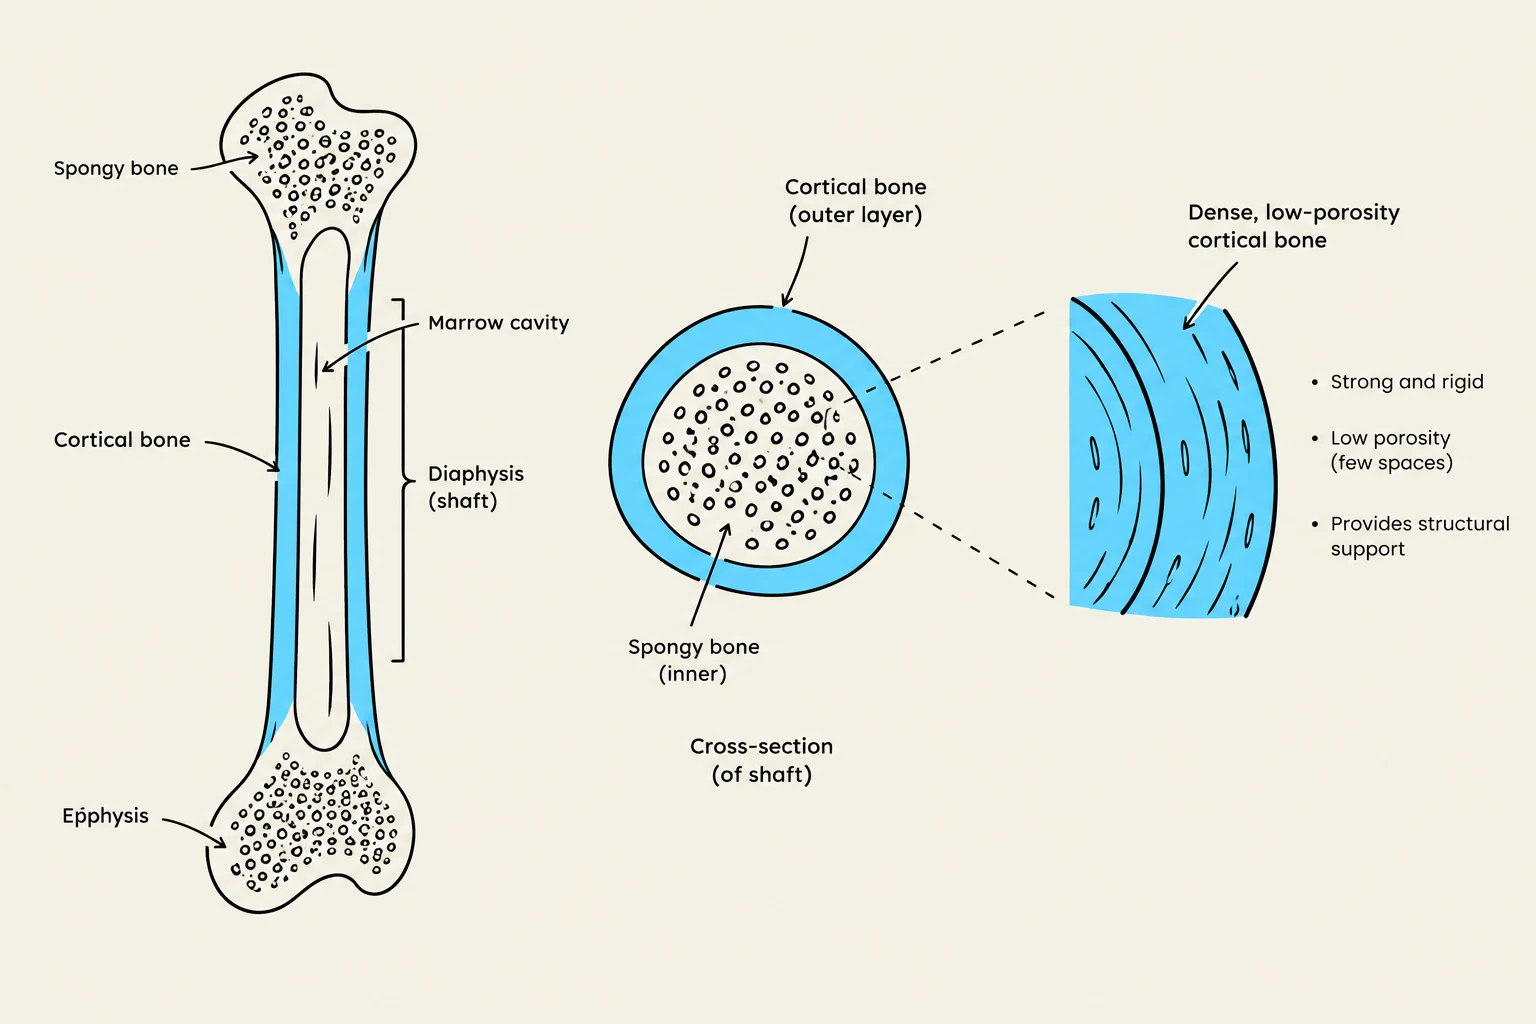
Cortical bone (also known as compact bone) is the dense, outer layer of the bone. It has low bone porosity (typically 5–30%), making it very stiff and highly resistant to high-magnitude stresses. You will find cortical bone primarily in the shafts of long bones and the outer coverings of flat or irregular bones.
In contrast, cancellous bone (also known as trabecular or spongy bone) is located in the interior and at the ends (epiphyses) of long bones. It is highly porous, with a non-mineral content ranging from 30% to 90%. While it is less stiff than cortical bone, its porous structure allows it to be highly responsive to strain, making it excellent at absorbing and distributing forces.
Diagram illustrating the structure of a long bone, including spongy bone, cortical bone, marrow cavity, diaphysis, and epiphysis, along with a cross-section of the shaft and details on dense cortical bone.
The Role of Connective Tissue
Bones do not function in isolation. They are held in place by connective tissues that act as "bone-y" connections. These passive stabilizers include:
Ligaments: Connect bone to bone, resisting excessive movement and preventing dislocation.
Tendons: Connect muscle to bone, facilitating movement.
Cartilage: Provides protective lubrication and spreads loads over wide areas to reduce stress.
Mechanics of Fracture: Why Bones Break
A fracture occurs when an applied load exceeds the bone's physiological capacity to withstand force. The likelihood of a fracture is not determined by the force alone, but by a complex interplay of several factors.
Factors Influencing Fracture Resistance
Magnitude, Duration, and Rate: The amount of force, how long it is applied, and how quickly it is delivered all dictate whether the bone will fail.
Bone Geometry: The cross-sectional shape of the bone influences its ability to resist bending or compression.
Bone Porosity and Health: Higher porosity generally leads to lower strength.
Anisotropic Effects: Because bone is anisotropic, it is strongest when resisting compression (along the longitudinal axis) and weakest when resisting shear (forces acting parallel to the surface).
Exam Tip: Stress vs. Strain
Remember that Stress is the manner in which force is distributed over a surface area, whereas Strain is the resulting deformation (change in shape).
Stress=AreaForceStiffness=StrainStress
Loading Types: Acute vs. Chronic
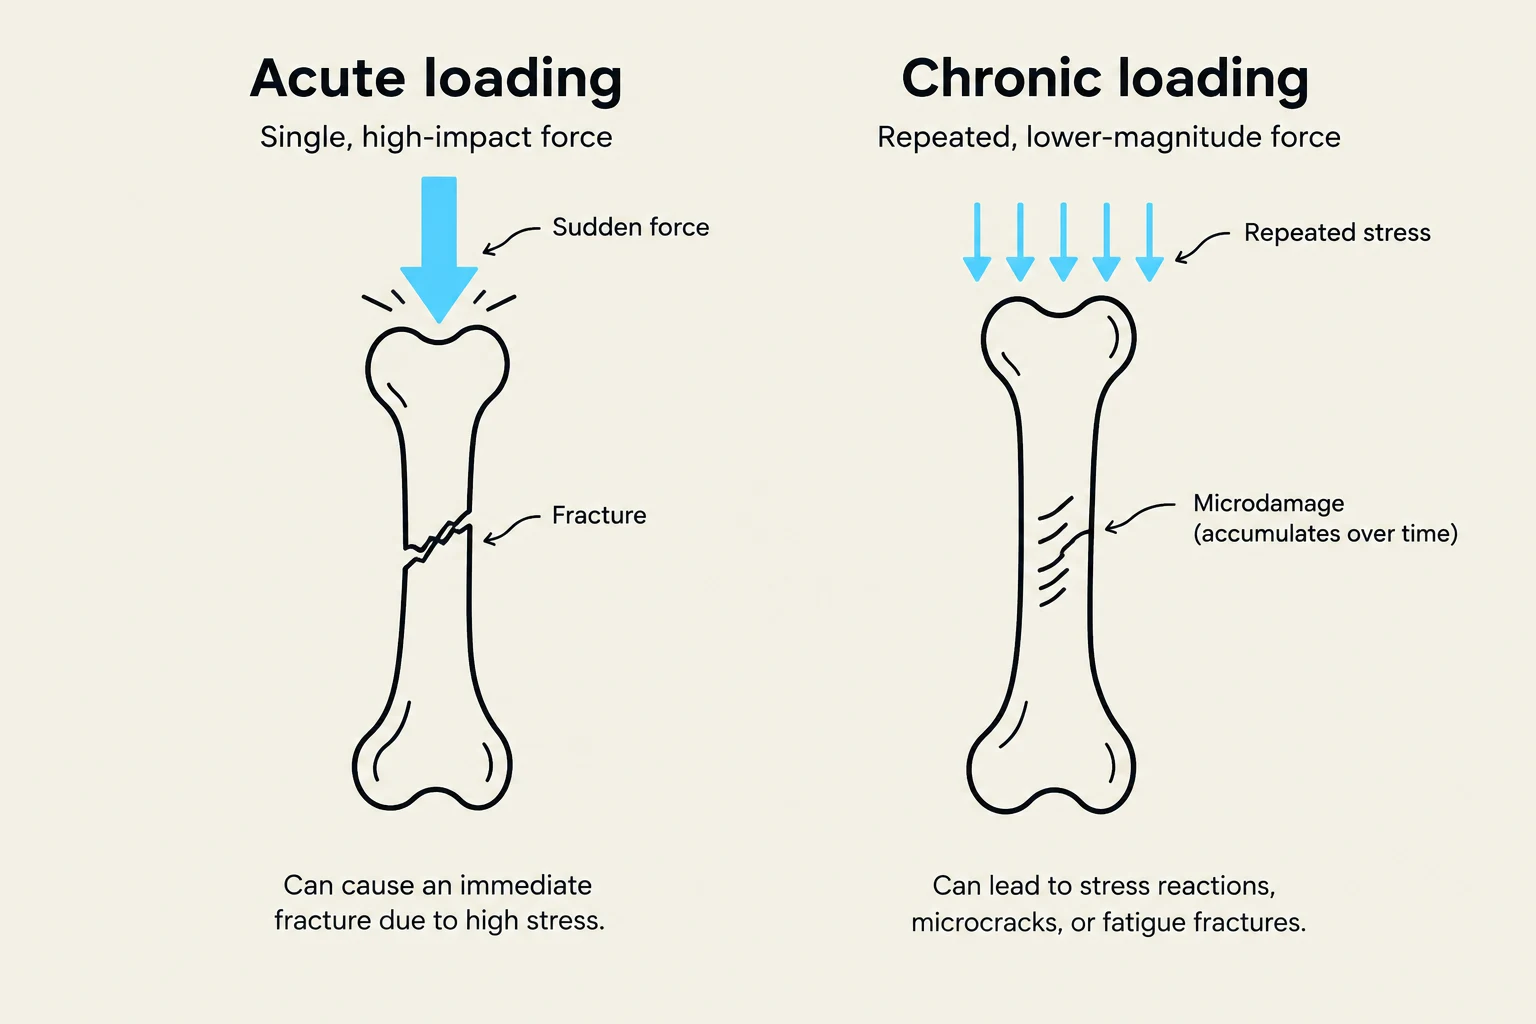
Loading can be categorized by its temporal pattern. Acute loading involves a single, high-magnitude force (e.g., a fall or a collision). Chronic loading involves the repeated application of lower-magnitude forces over time.
This illustration compares acute loading, which causes immediate fractures from high-impact force, with chronic loading, which leads to microdamage and fatigue fractures from repeated stress.
Classifying Fractures
Fractures are classified by the type of force that caused them and their relationship to the surrounding soft tissue.
By Force Type
Avulsions: Caused by tensile loading (pulling forces), often where a ligament or tendon pulls a piece of bone away.
Spiral Fractures: Result from a combination of bending and torsion (twisting).
Compression Fractures: Occur when bone is "squished," often seen in the vertebrae.
Greenstick Fractures: An incomplete break that occurs in more flexible, younger individuals.
Stress Fractures: Small cracks caused by chronic loading (repeated, low-magnitude stress).
Epiphyseal Fractures: Fractures that specifically involve the growth plate (physis).
By Soft Tissue Relationship
Simple Fractures: The bone breaks, but the ends remain contained within the soft tissue.
Compound Fractures: The broken bone ends protrude through the skin, creating a high risk of infection.
Bone Health: Osteopenia and Osteoporosis
Bone is a dynamic tissue that undergoes constant remodelling via osteoblasts (bone-forming cells) and osteoclasts (bone-resorbing cells). When this balance is disrupted, bone health declines.
The progression of bone loss typically follows a specific path:
Osteopenia: A condition characterized by decreased bone mineral density.
Osteoporosis: A more advanced state of bone atrophy where the bone becomes significantly more porous and brittle.
As bone mineral density drops, the risk of fractures increases dramatically. In individuals with osteoporosis, fractures can occur even during Activities of Daily Living (ADL), such as walking or standing up. This is particularly problematic in elderly populations and post-menopausal women due to hormonal changes that accelerate bone resorption.
Comparison of a healthy bone with high mineral density and thick cortical walls to an osteoporotic bone with lower mineral density and thinner cortical walls, illustrating differences in trabecular and cortical bone structure.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.