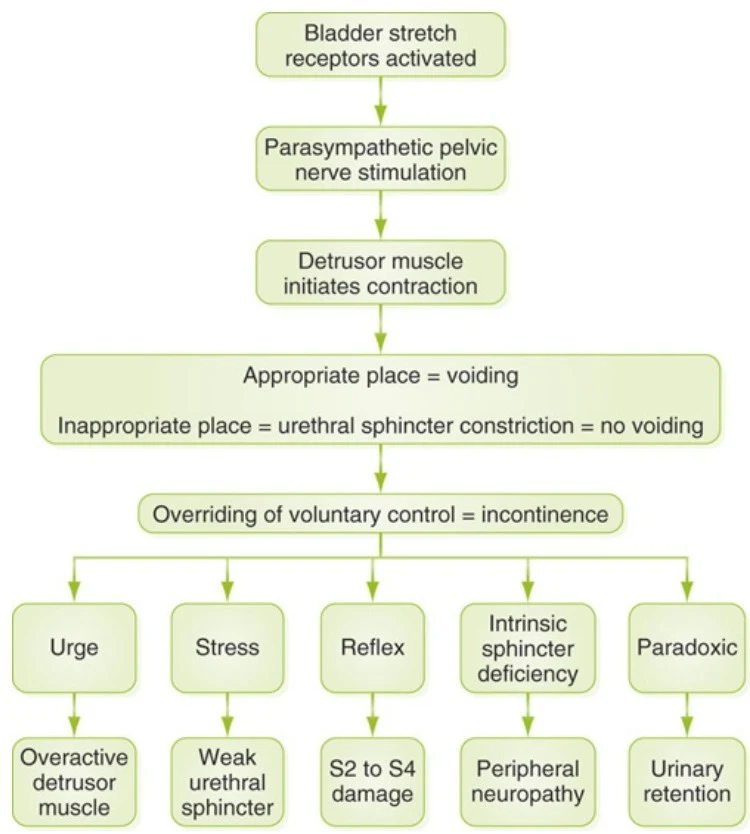
2. Urge Incontinence
Characterized by a sudden, intense urge to urinate followed by involuntary leakage, this type is often associated with Overactive Bladder (OAB). It can be caused by urinary tract infections (UTIs), bladder irritants, or neurological conditions such as Parkinson’s disease, Multiple Sclerosis (MS), or stroke.
3. Overflow Incontinence
This type involves the inability to empty the bladder completely (retention), leading to constant dribbling or a weak stream. Common causes include urethral blockages, prostate disease, or nerve damage from Diabetes Mellitus.
4. Reflex Incontinence
Resulting from nerve trauma (specifically S2-S4 injury), this type involves detrusor hyperreflexia. In this state, the bladder contracts without the individual experiencing a prior sensation of urgency.
5. Other Specialized Types
- Enuresis: Involuntary urination in children older than 4–5 years, often manifesting as nocturnal enuresis (bed-wetting).
- Transient Incontinence: Temporary loss of control due to external factors like delirium, infection, constipation, or consumption of caffeine and alcohol.
- Functional Incontinence: Occurs when physical or mental impairments prevent a person from reaching a toilet in time.
- Gross Total Incontinence: Continuous or periodic uncontrollable leaking of large volumes, often due to anatomic defects or spinal cord injuries.
- Mixed Incontinence: When a patient experiences symptoms of more than one type simultaneously.
Risk Factors and Complications
Risk Factors
Several factors increase the likelihood of developing incontinence:
- Gender: Females are at higher risk due to pregnancy, childbirth, and menopause.
- Age: While not "normal," incontinence is an inevitable occurrence for many as they age.
- Lifestyle: Obesity increases pressure on the bladder, while smoking can lead to chronic coughing, contributing to stress incontinence.
- Medical Conditions: Prostate disease in males, renal disease, and Diabetes Mellitus (which affects nerve innervation) are significant contributors.
Complications
The impact of incontinence extends beyond physical discomfort:
- Physical: Skin moisture can lead to rashes, infections, and ulcers. Incomplete emptying can also lead to recurrent UTIs.
- Psychological: Patients often experience embarrassment, anxiety, depression, and a loss of self-image.
- Quality of Life: Incontinence can lead to sexual dysfunction and may force individuals to limit work or social activities.
Diagnostic Testing
To determine the cause and type of incontinence, clinicians utilize several diagnostic tools:
- History and Physical: Reviewing past medical history and performing a physical exam.
- Bladder Diary: Tracking fluid intake and voiding patterns.
- Laboratory Tests: Urinalysis and urine cultures to check for infection.
- Imaging: Cystourethrogram (X-ray of the bladder/urethra), pelvic ultrasound, or cystoscopy (using a small lighted instrument to visualize the bladder).
- Urodynamic Testing: Specifically used to measure pressures within the bladder.
Management Strategies
Management is typically approached in a tiered fashion, moving from least invasive to most invasive.
First-Line: Behavioral and Lifestyle Modifications
The initial goal is to manage symptoms through habit changes:
- Bladder Training: Implementing scheduled toileting and coping strategies.
- Pelvic Floor Exercises: Performing Kegel exercises to strengthen the muscles that support the bladder.
- Dietary Changes: Reducing intake of bladder irritants like caffeine, alcohol, and acidic foods.
- Lifestyle: Weight loss and increased physical activity to reduce intra-abdominal pressure.
Second-Line: Pharmacological Treatments
If behavioral changes are insufficient, medications may be prescribed:
- Muscarinic Antagonists (Anticholinergics): Used to manage urge incontinence.
- Estrogen Replacement: Often used for postmenopausal women.
- Botulinum Toxin A: Injected directly into the bladder.
- Bulking Agents: Collagen or other materials used to reinforce urethral tissue.
Third-Line: Surgical and Advanced Procedures
For severe or refractory cases, more intensive interventions are required:
- Mechanical Supports: Use of a pessary (a stiff vaginal ring) or an artificial urinary sphincter.
- Neuromodulation: Sacral nerve stimulation.
- Surgical Repair: Bladder neck suspension or radiofrequency therapy to firm the lower urinary tract.
Exam Tip: When differentiating between Stress and Urge incontinence, remember the trigger. Stress is triggered by increased pressure (coughing/lifting), whereas Urge is triggered by involuntary bladder contractions (often associated with OAB).