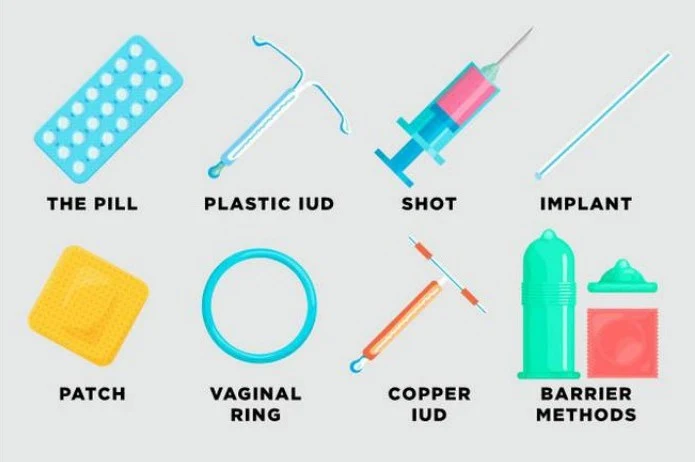
Dosing Regimens and Schedules
COCs are typically organized into different regimens to suit patient needs:
- Monophasic: The dose of estrogen and progestin remains constant throughout the entire pack.
- Biphasic, Triphasic, or Quadriphasic: These regimens use varying doses of hormones throughout the cycle to more closely simulate the body's natural hormonal fluctuations.
- Extended-Cycle and Continuous Schedules: Instead of taking a 7-day placebo (inert) period, patients take active pills continuously or for longer stretches (e.g., 84 days). This can reduce withdrawal bleeding, pain, and premenstrual symptoms.
Missed Dose Protocols
Missing a pill can compromise contraceptive efficacy. The protocol depends on when the dose was missed:
- ≥1 pill missed in the 1st week: Take the missed pill ASAP and continue the pack, but use a backup method (like condoms) for the next 7 days.
- 1–2 pills missed in the 2nd or 3rd week: Take the missed pill ASAP, continue the pack, and use backup for 7 days.
- ≥3 pills missed in the 2nd or 3rd week: Follow the same protocol as missing 1 pill in weeks 2-3, but ensure backup protection is used.
Progestin-Only Contraceptives
Often referred to as the "mini-pill," progestin-only contraceptives are a vital alternative for patients who cannot take estrogen.
Mechanism and Advantages
The primary mechanism of progestin-only methods is the alteration of cervical secretions to create a barrier against sperm. They also have a weak effect on modifying the endometrium to make it less favorable for implantation.
Key Advantages:
- Safety Profile: Because they lack estrogen, they do not carry the same risks of thrombosis, hypertension, or nausea associated with COCs.
- Lactation: They are safer for patients who are breastfeeding.
Disadvantages:
- Side Effects: Patients often experience irregular bleeding, such as breakthrough spotting or amenorrhea (absence of menstruation).
- Efficacy: They are considered "weak inhibitors" of ovulation compared to COCs, making them slightly less effective.
Missed Dose Alert: For progestin-only pills, if a patient misses one or more pills, they must take it ASAP and use backup protection for at least 2 days.
Clinical Considerations: Balancing Hormones
When prescribing hormonal therapy, clinicians must balance the levels of estrogen and progestin to minimize adverse effects.
The Balancing Act
An imbalance in hormone levels can lead to various clinical manifestations:
| Hormone Status | Potential Side Effects |
|---|
| Estrogen Excess | Nausea, breast tenderness, edema, bloating, hypertension, migraine |
| Estrogen Deficiency | Early/midcycle breakthrough bleeding, increased spotting |
| Progestin Excess | Weight gain, depression, fatigue, acne, hirsutism |
| Progestin Deficiency | Late breakthrough bleeding, amenorrhea, hypermenorrhea |
Contraindications and Risks
Certain patients should avoid COCs entirely due to the risk of serious cardiovascular events.
- Absolute Contraindications: History of thrombosis (blood clots), cerebral vascular disease, coronary occlusion, unexplained vaginal bleeding, or known pregnancy.
- High-Risk Groups: Smokers over the age of 55 are at significantly increased risk for cardiovascular complications.
- Hypertension: COCs can increase angiotensin and aldosterone levels, potentially worsening hypertension.
Drug Interactions
Pharmacotherapy requires careful monitoring of drug-drug interactions, particularly involving the liver's metabolic pathways.
-
Reduced Efficacy of Contraceptives: CYP-450 inducers speed up the metabolism of the contraceptive hormones, making them less effective. Examples include:
- Rifampin
- Antiseizure medications (carbamazepine, phenytoin, phenobarbital)
- St. John's wort
- Clinical Action: If a patient experiences breakthrough bleeding while on an inducer, consider switching to a different form of birth control.
-
Altered Effects of Other Drugs:
- Decreased drug effects: COCs may decrease the efficacy of hypoglycemic agents (insulin/diabetes meds) and warfarin.
- Increased drug effects: COCs may increase the effects of theophylline, TCAs, and benzodiazepines (like diazepam), potentially leading to toxicity.
Exam Tip: If a question asks which patient is at the highest risk for a venous thromboembolism (VTE) while taking COCs, look for the patient who smokes heavily or has a significant family history of stroke/thrombosis.