A comprehensive guide to pediatric health promotion, covering nutrition across the lifespan, obesity prevention, sleep, physical activity, safety, and child maltreatment prevention.
Health promotion in pediatrics is defined as a proactive process of enabling children to increase control over, and improve, their own health. Because the health of children has a profound impact on both individual lifelong outcomes and the health of entire communities, healthcare providers must focus on anticipatory guidance—providing families with information about what to expect in upcoming developmental stages. This article explores the critical pillars of pediatric wellness: nutrition, physical activity, safety, and the protection of children from maltreatment.
Nutrition Across the Lifespan
Nutritional requirements are dynamic, shifting significantly as a child moves through different developmental stages.
Infancy: The Foundation
For the first six months of life, breastfeeding is recommended, and can continue up to two years. A critical clinical note for nurses is that infants who are exclusively breastfed require Vitamin D supplementation of 400 IU/day. As the child enters the second six months, solid foods should be introduced one at a time, starting with meats, meat alternatives, and iron-fortified foods. It is important to avoid honey and corn syrup during this period.
Toddlers and Preschoolers
As children transition into toddlerhood, parents may encounter "physiological anorexia," a phenomenon where a child's food intake varies greatly from day to day. This is often a normal developmental occurrence rather than a sign of malnutrition. Preschoolers may also develop "strong tastes" or food fads. To support healthy habits, caregivers should encourage variety, establish mealtime routines, and involve children in food preparation to increase their interest in new foods.
School-Age and Adolescents
School-age children often face "junk-food" concerns and have high energy requirements. During adolescence, nutritional needs spike again due to rapid and extensive growth. Nurses should be particularly vigilant regarding iron deficiency in adolescent females.
Dietary Patterns and Vegetarianism
Families may choose various plant-based diets, which can be adequate for all ages if well-planned:
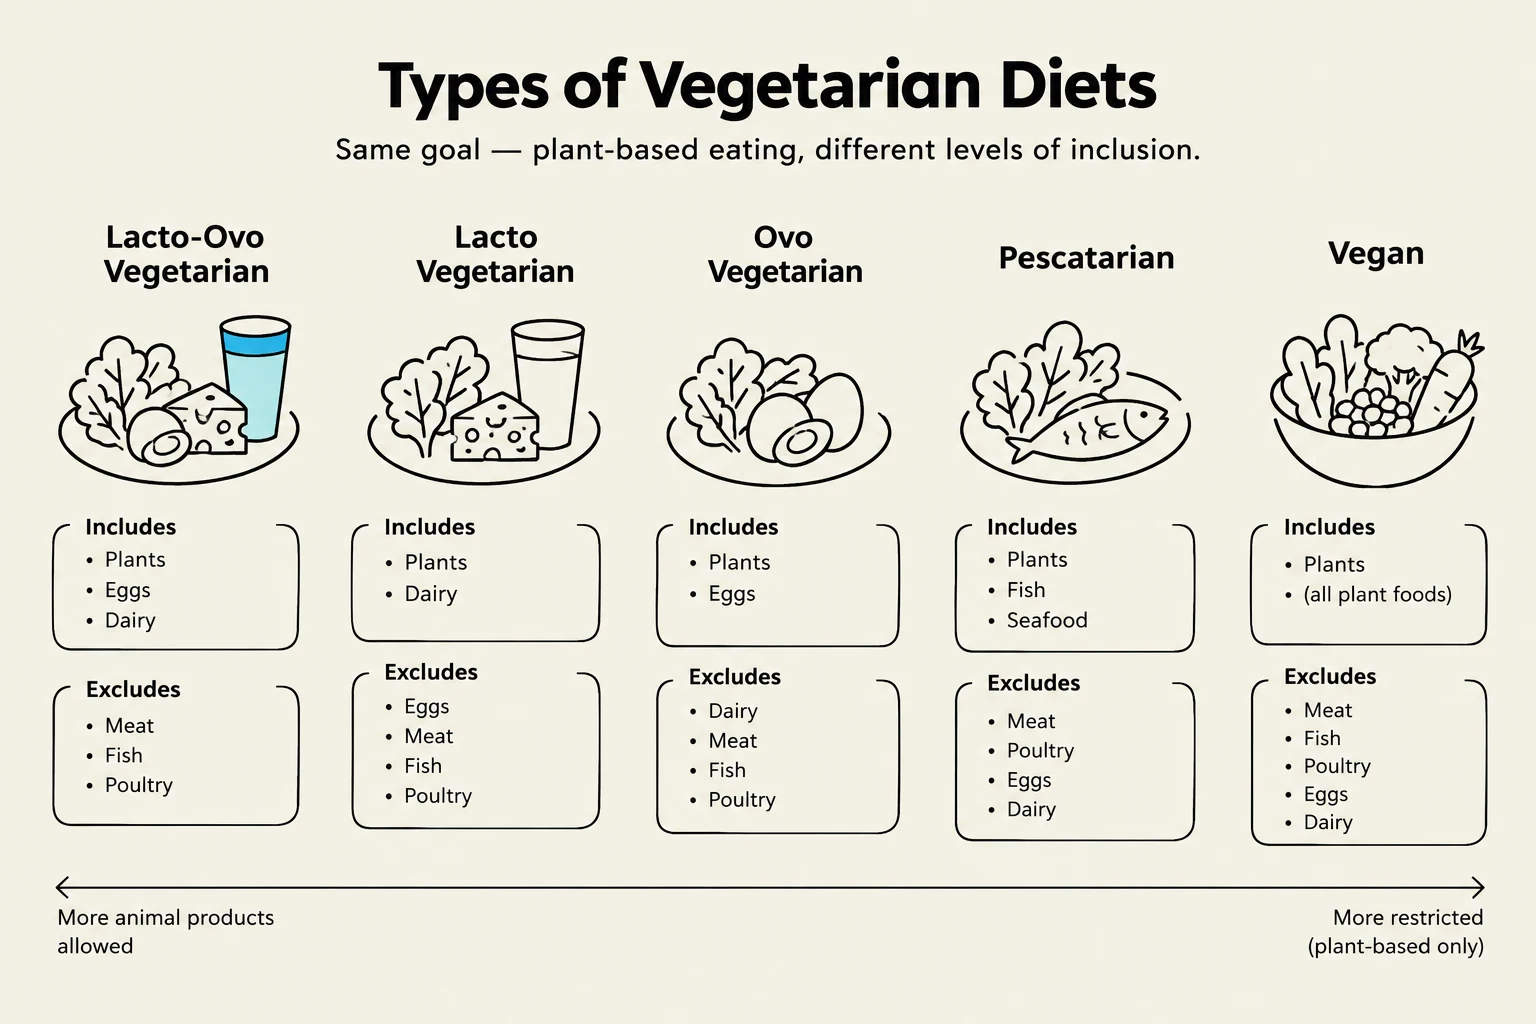
Lacto-ovo vegetarians: Consume dairy but exclude meat and eggs.
Lactovegetarians: Consume milk but exclude meat and eggs.
Vegans: Eliminate all animal-derived products, including honey and dairy.
Semivegetarians: Follow a lacto-ovo diet but include some fish or poultry.
Macrobiotics: A very strict diet limited to specific fruits, vegetables, and legumes.
This chart outlines different types of vegetarian diets, including Lacto-Ovo, Lacto, Ovo, Pescatarian, and Vegan, detailing the foods typically included and excluded in each.
Dietary Guidelines and Micronutrient Needs
In Canada, nutritional guidance is centered around Canada’s Food Guide, which emphasizes eating protein foods, plenty of vegetables and fruits, whole grains, and making water the drink of choice. For nurses, the guide provides a framework for teaching food skills and creating supportive eating environments.
A vital component of pediatric nutrition is ensuring adequate intake of Calcium and Vitamin D for bone development. The following table outlines the Dietary Reference Intakes (DRIs):
Age Group
Calcium RDA (mg/day)
Vitamin D RDA (IU/day)
0–6 months
200
400
7–12 months
260
400
1–3 years
700
600
4–8 years
1000
600
9–18 years
1300
600
Exam Tip: When assessing an infant, remember that while breastfeeding is the gold standard, exclusive breastfeeding necessitates Vitamin D supplementation (400 IU/day) to prevent deficiency.
Obesity Prevention and Management
Obesity is a multifactorial issue resulting from a caloric intake that consistently exceeds expenditure. It is categorized by Body Mass Index (BMI): overweight is a BMI > 25 (85th to 97th percentile), while obesity is a BMI > 30 (95th to 99.9th percentile).
The etiology of obesity is complex, involving:
Biological factors: Genetics and the protective effects of breastfeeding.
Behavioral factors: Sedentary lifestyles (increased screen time) and lack of physical activity.
Social/Economic factors: Marketing of high-fat/sugar foods and unequal access to nutritious options.
Psychological factors: Emotional eating as a coping mechanism for anxiety or depression.
Management requires a holistic approach involving diet, exercise, behavioral therapy, and family involvement.
Sleep, Rest, and Physical Activity
Physical activity is essential for developing muscle strength, cardiovascular capacity, and bone density while helping to control body fat.
Activity Recommendations
Infants (<1 year): Focus on interactive floor-based play and "tummy time"; screen time is not recommended.
Toddlers (1–2 years): At least 180 minutes of varied physical activity daily.
Children/Adolescents (5–17 years): At least 60 minutes of moderate to vigorous aerobic activity daily, with muscle/bone-strengthening activities at least 3 days per week.
Sleep Needs
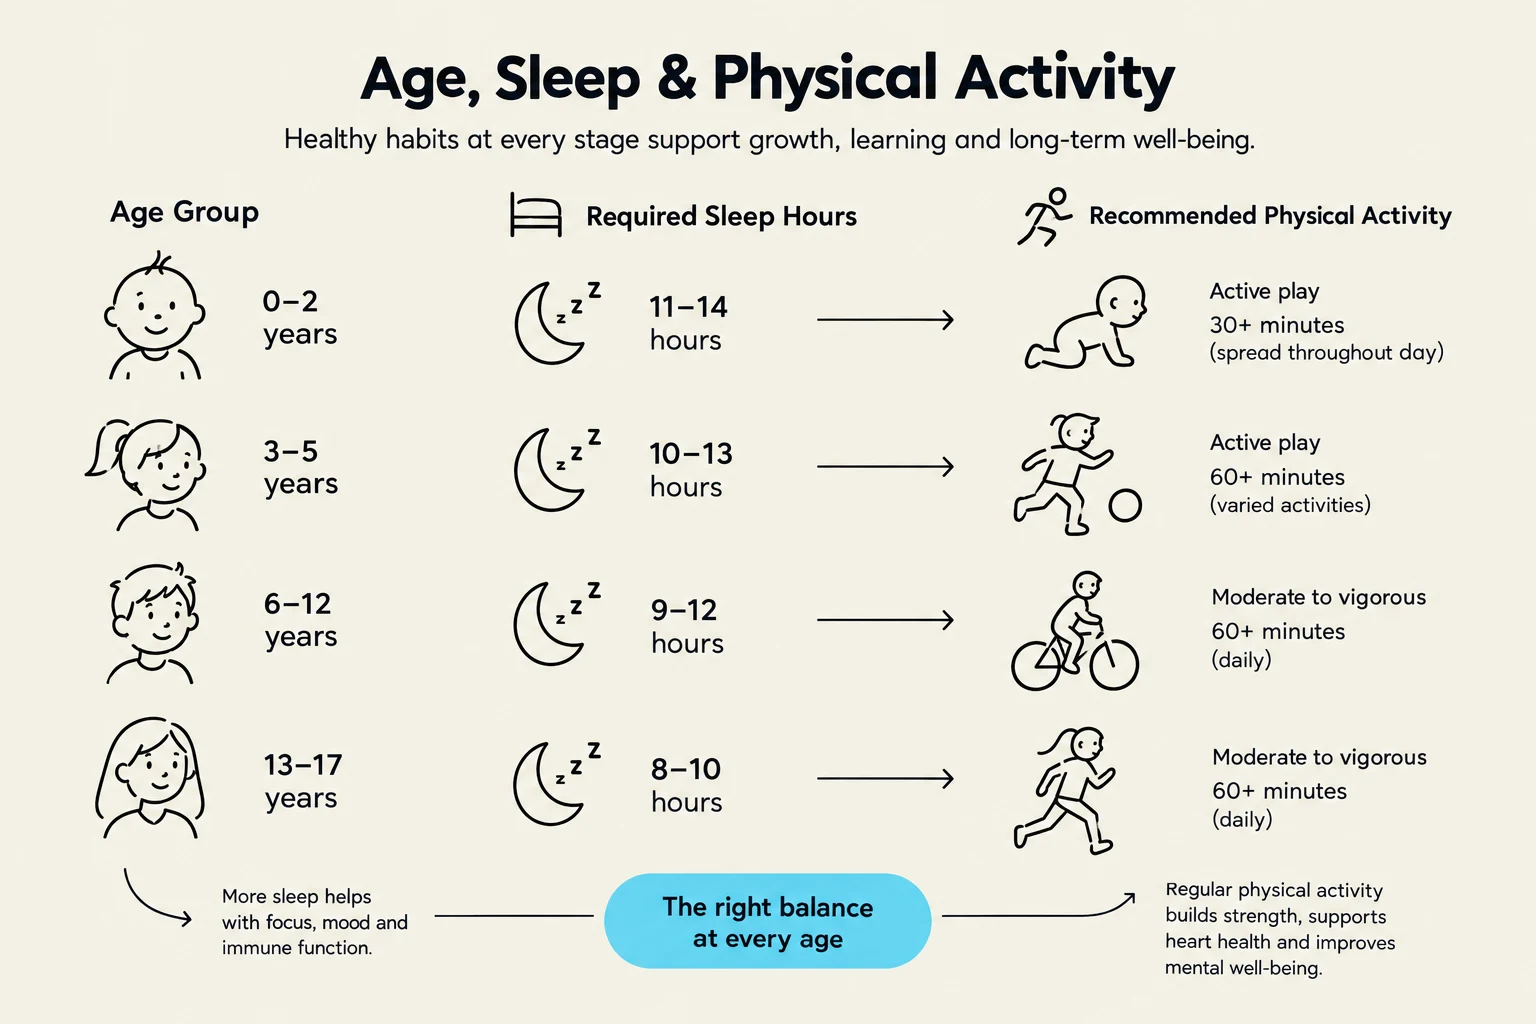
Sleep requirements decrease as children age:
Infants (4–12 months): 12–16 hours.
Toddlers (1–2 years): 11–14 hours.
School-age (6–12 years): 9–12 hours.
Teenagers (13–18 years): 8–10 hours.
This chart outlines recommended sleep hours and physical activity for different age groups, emphasizing their importance for growth, learning, and well-being.
Safety Promotion and Injury Prevention
In pediatrics, the term "injury" is preferred over "accident" because "accident" implies a random, unavoidable event, whereas "injury" suggests that many events are preventable through responsibility and control. Unintentional injuries are the leading cause of death and disability for Canadian children over age 1.
Developmental Safety Risks
Infants: Most injuries occur at home. Use the SAFE PAD acronym to remember risks: Suffocation, Asphyxia/Animal bites, Falls, Electrical/Burns, Poisoning, Automobile safety, and Drowning.
Toddlers/Preschoolers: High curiosity and developing motor skills lead to risks from falls and poisoning.
School-age: Pedestrian accidents are a leading cause of death.
Adolescents: Motor vehicle accidents are the leading cause of injury and death, often exacerbated by a sense of invincibility.
Nurses can use passive approaches (e.g., smoke detectors, car seats) or active approaches (e.g., wearing a bike helmet, driving carefully) to promote safety.
Child Maltreatment
Child maltreatment is the intentional physical, emotional, or sexual abuse or neglect of a child by a caregiver.
Types of Maltreatment
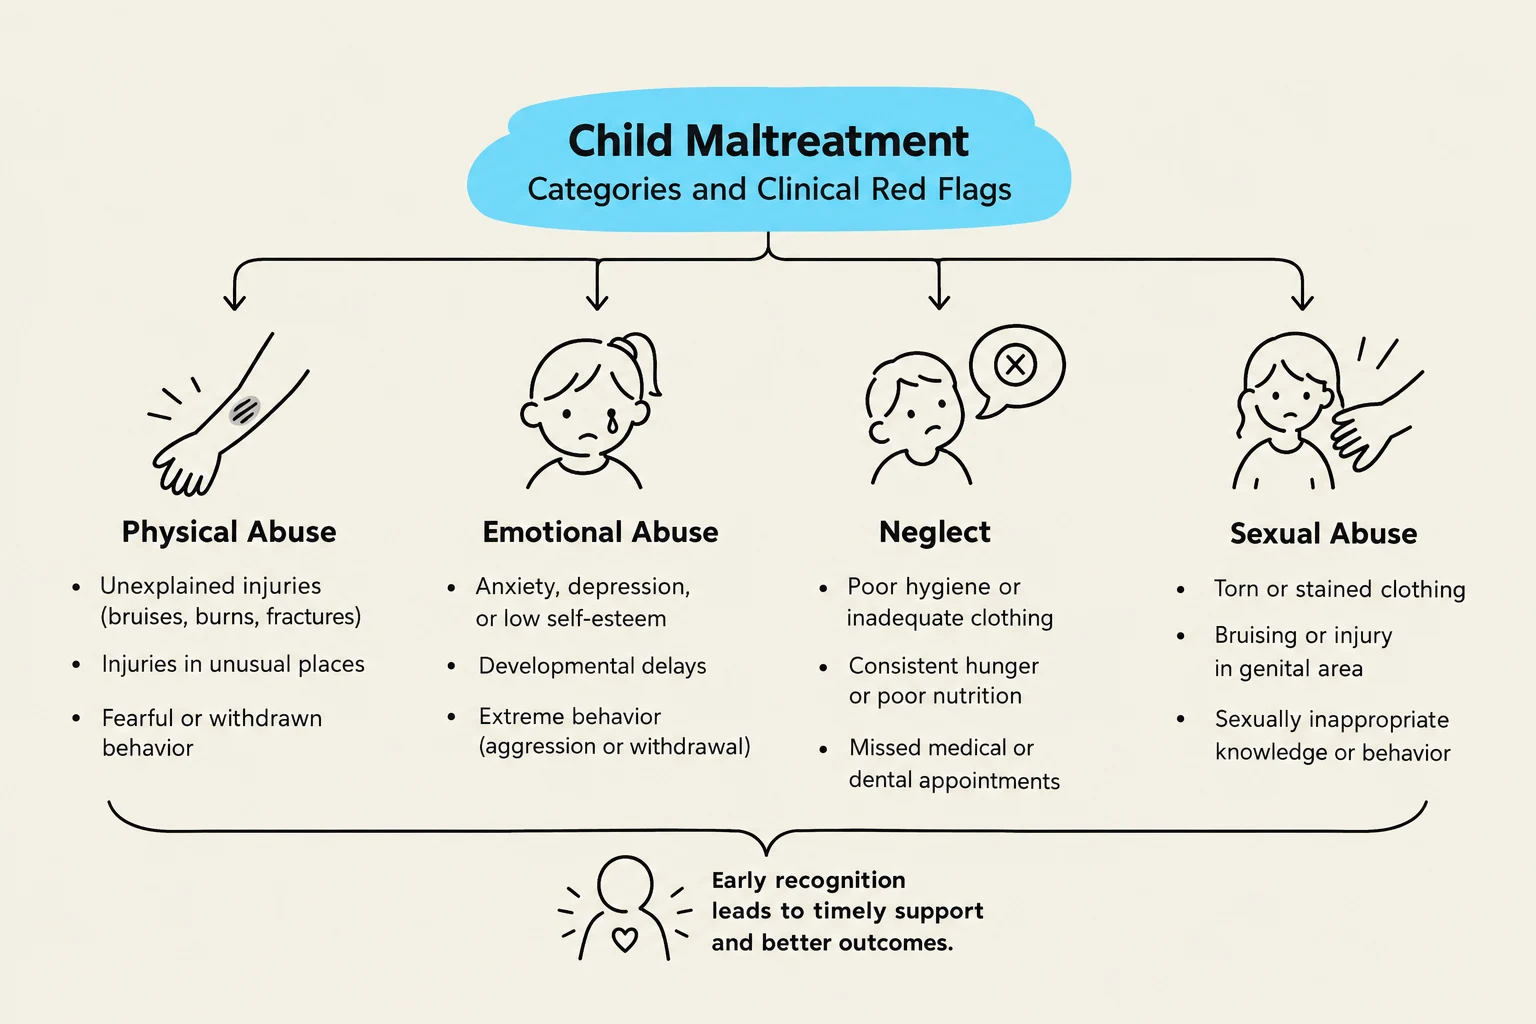
Physical Abuse: May present as fractures, burns (often without splash patterns), or bruises in "red flag" areas like the ears, neck, or torso.
Emotional Abuse: Deliberate attempts to destroy a child's self-esteem, which can manifest as failure to thrive, sleep disorders, or social withdrawal.
Sexual Abuse: Characterized by age-inappropriate sexual play, STIs, or sudden changes in personality.
Neglect: Failure to provide necessary care (physical or emotional).
Munchausen Syndrome by Proxy (Medical Child Abuse): A caregiver induces or exaggerates symptoms in a child for personal gratification.
This diagram outlines the categories and clinical red flags associated with child maltreatment, including physical abuse, emotional abuse, neglect, and sexual abuse. It also emphasizes the importance of early recognition for timely support and better outcomes.
The Nurse's Role
Nurses have a legal, ethical, and moral responsibility to report any suspected abuse immediately to local authorities. Proof is not required to make a report; the nurse's duty is to report suspicion. When talking to a child who reveals abuse, provide a private setting, use their vocabulary, and reassure them that the abuse is not their fault.
Critical Note: Patient confidentiality requirements do not apply when a nurse is reporting suspected child abuse.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.