A comprehensive guide to understanding the menstrual cycle, common menstrual disorders such as amenorrhea and dysmenorrhea, premenstrual syndromes, and various methods of contraception, including combined oral contraceptives and progestin-only pills.
Understanding the menstrual cycle is fundamental to reproductive health. While every individual's cycle may vary slightly in duration and volume, a "normal" menstrual period typically lasts between 4 to 6 days, with a total blood loss of approximately 30 mL. When these patterns deviate significantly from the norm, it can indicate underlying physiological issues, hormonal imbalances, or pathological conditions that require clinical attention.
Normal vs. Abnormal Menstruation
A standard menstrual pattern is characterized by regularity. However, many women experience variations that can range from harmless discomfort to indicators of serious medical problems.
Amenorrhea
Amenorrhea refers to the absence of menstruation. It is categorized into two main types:
Primary Amenorrhea: This occurs when a person has never had a menstrual period by age 16. This may be caused by genetic disorders, such as Turner's syndrome, or congenital defects like uterine agenesis.
Secondary Amenorrhea: This is the cessation of previously established periods. Common causes include pregnancy, lactation, and menopause. Other triggers include hypothalamic tumors, sudden weight loss, extreme stress, eating disorders, or intensive athletic training.
Dysmenorrhea
Dysmenorrhea is painful menstruation that can significantly impact a person's quality of life. The pain is driven by an increase in prostaglandins (PGs), which trigger strong uterine contractions and cause blood vessel constriction. This constriction leads to uterine ischemia (reduced blood flow to the tissue), resulting in intense, intermittent abdominal pain that often radiates to the back, legs, or perineum.
Primary Dysmenorrhea: Often appears with the very first cycle and has no known specific cause.
Secondary Dysmenorrhea: Develops later in life and may be linked to conditions like endometriosis or reproductive cancers.
Clinical Tip: Management for dysmenorrhea often involves NSAIDs to inhibit prostaglandin production or oral contraceptives to suppress ovulation.
Abnormal Bleeding Patterns
Abnormal bleeding is frequently associated with hormone imbalances or pathological diagnoses, including reproductive cancers. These patterns are classified as follows:
Vaginal bleeding that occurs between regular menstrual periods.
Polymenorrhea
Frequent menstrual cycles lasting shorter than 21 days.
Oligomenorrhea
Infrequent menstrual cycles lasting longer than 42 days.
Premenstrual Syndromes
Symptoms of premenstrual syndromes typically emerge 5 to 11 days prior to the onset of menstruation. These conditions most commonly affect women in their late 20s to late 40s, particularly those who have had at least one childbirth or have a family history of mood disorders.
Premenstrual Syndrome (PMS): A collection of physical and emotional symptoms, including irritability, depression, fatigue, headaches, abdominal bloating, breast tenderness, and sleep disturbances.
Premenstrual Dysphoric Syndrome (PMDD): A more severe clinical manifestation characterized by intense depression, tension, and irritability.
Management of Premenstrual Symptoms
Treatment strategies range from lifestyle modifications to pharmacological interventions:
Lifestyle Modifications (TLC): Reducing the consumption of caffeine, soda, chocolate, fat, processed sugars, and alcohol. It is recommended to increase fluid intake and consume small, frequent meals high in whole grains, vegetables, and fruit.
Nutritional Supplementation: Increasing intake of Vitamin B6, Calcium (Ca), and Magnesium (Mg).
Pharmacotherapy: Use of SSRIs (antidepressants), NSAIDs (analgesics), diuretics, or Hormone Replacement Therapy (HRT).
Contraception and Hormonal Control
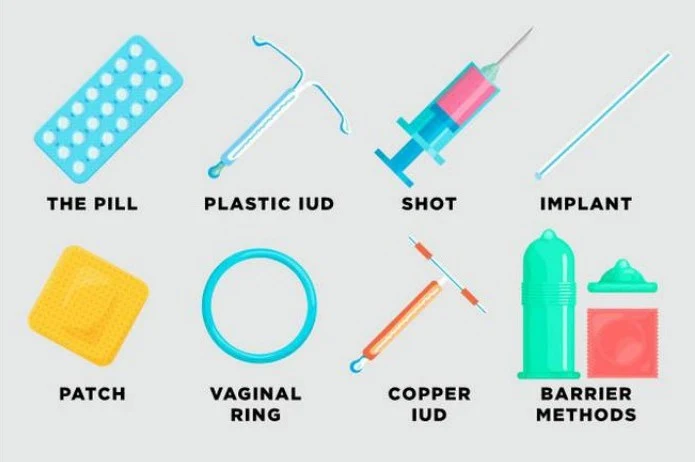
This illustration displays various methods of contraception, including pills, IUDs, injections, implants, patches, vaginal rings, and barrier methods.
Contraception can be categorized into nonpharmacologic methods (such as surgical sterilization, mechanical devices like condoms, or fertility awareness) and pharmacologic methods.
Combined Oral Contraceptives (COCs)
COCs contain both estrogen and progestin. They work by inhibiting ovulation through two primary mechanisms:
Estrogen: Suppresses the release of Follicle-Stimulating Hormone (FSH) from the pituitary, which inhibits follicular maturation.
Progestin: Acts on the hypothalamus and pituitary to suppress the midcycle Luteinizing Hormone (LH) surge and thickens cervical mucus to act as a barrier to sperm.
Different generations of progestins offer different side effect profiles. For example, 1st generation progestins (norethindrone) may be more androgenic (causing acne or hirsutism), while 3rd and 4th generation progestins are generally less androgenic but may carry a higher risk of thrombosis.
Safety Warning: COCs are absolutely contraindicated in patients with a history of thrombosis, cerebral vascular disease, known/suspected breast cancer, or smokers over the age of 55.
Progestin-Only Contraceptives (The "Mini-Pill")
Unlike COCs, progestin-only methods are not cyclic and must be taken continuously. Their primary mechanism is the alteration of cervical secretions to create a barrier against sperm. While they avoid the estrogen-related risks of thrombosis and nausea, they are generally less effective at inhibiting ovulation and may cause irregular bleeding.
Managing Side Effects and Interactions
Hormonal balance is delicate. An excess or deficiency in these hormones can lead to various side effects:
Hormone State
Potential Side Effects
Estrogen Excess
Nausea, breast tenderness, edema, hypertension, migraines.
Weight gain, depression, fatigue, acne, hirsutism.
Progestin Deficiency
Late breakthrough bleeding, amenorrhea, hypermenorrhea.
Drug Interactions: Certain substances can reduce the effectiveness of oral contraceptives by inducing the CYP-450 enzyme system. These include Rifampin, certain antiseizure medications (e.g., carbamazepine, phenytoin), and St. John's wort. Conversely, oral contraceptives may increase the effects of drugs like Warfarin or certain hypoglycemic agents.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.