An overview of white blood cells (leukocytes), their production in the bone marrow, maturation into specialized types like neutrophils and lymphocytes, and their roles in the immune system. Covers hematopoietic pathways, neutrophil function including phagocytosis, and lymphocyte roles in adaptive immunity.
White blood cells (WBCs), or leukocytes, are the primary effectors of the immune system. They are responsible for identifying, ingesting, and destroying invading microorganisms, as well as managing the body's response to inflammation and abnormal cells. Understanding how these cells are produced in the bone marrow and how they mature into specialized types—such as neutrophils and lymphocytes—is fundamental to clinical hematology.
The Hematopoietic Pathway: From Stem Cell to Mature Cell
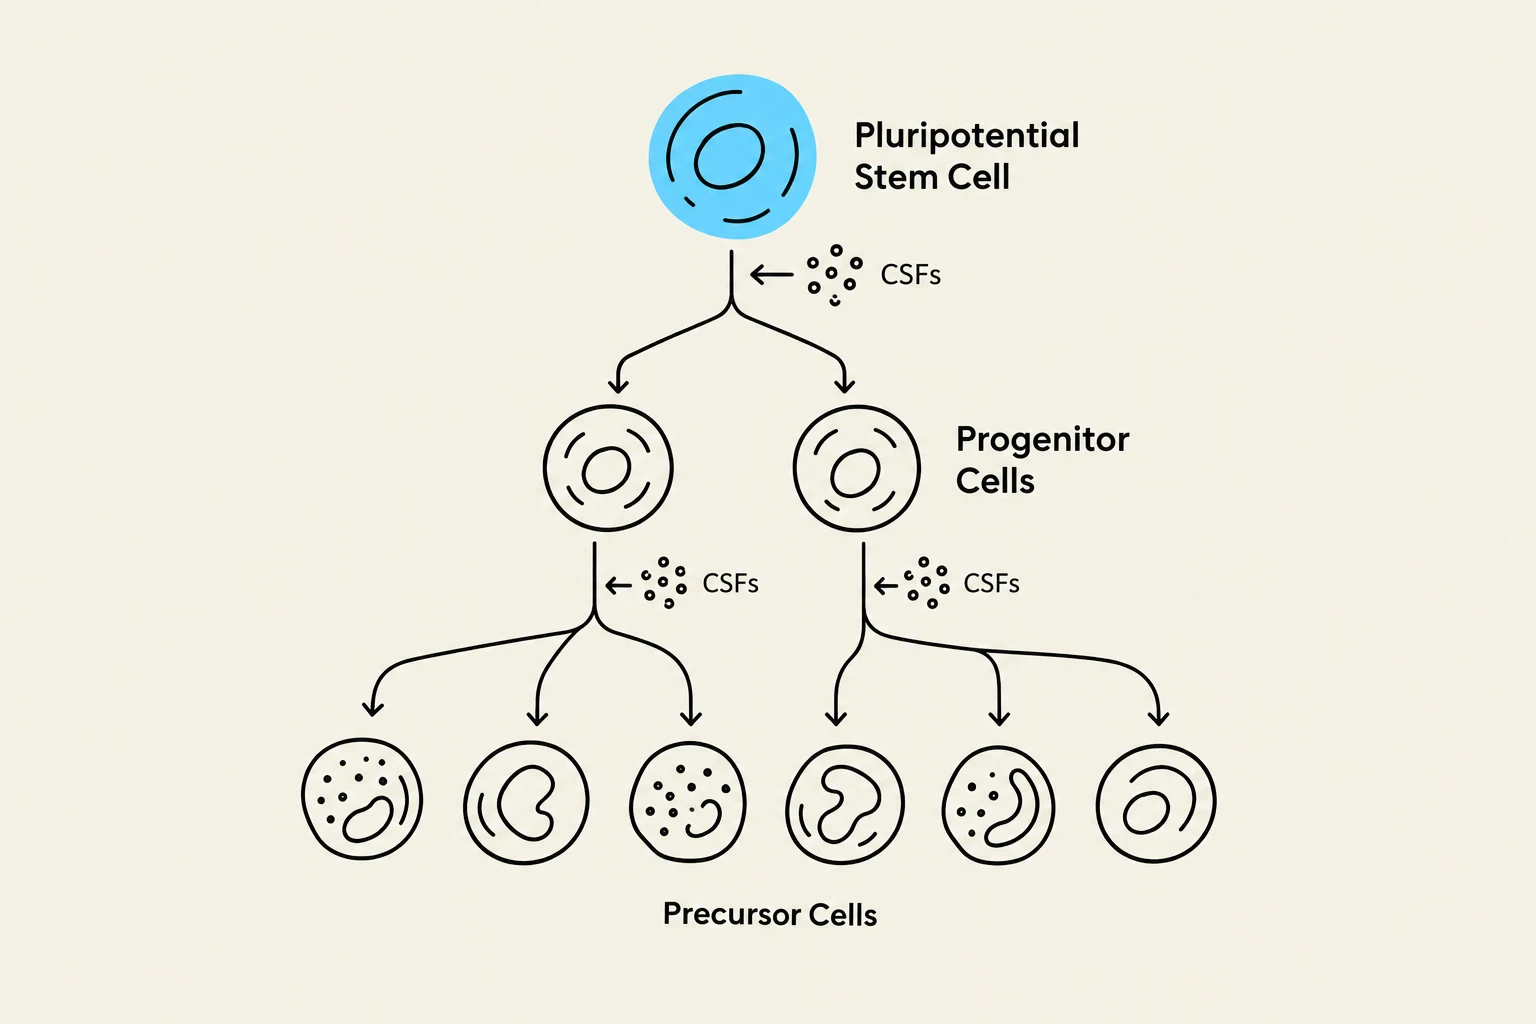
Diagram illustrating the differentiation of pluripotent stem cells into progenitor cells and then into precursor cells, influenced by CSFs.
The production of white blood cells is a highly regulated process that begins in the bone marrow. This journey from a single undifferentiated cell to a specialized functional unit involves several distinct stages of proliferation and differentiation.
The Hierarchy of Production
The developmental pathway follows a specific progression:
Pluripotential Cells: These are the ultimate stem cells capable of giving rise to all blood cell types.
Progenitor Cells: These cells are more committed to a specific lineage.
Precursor Cells: These are the cells that undergo visible morphological changes as they mature.
This entire process is driven by Colony Stimulating Factors (CSFs), which are chemical signals released by cells like macrophages to instruct the bone marrow to produce specific types of white cells.
Myeloid Proliferation and Neutrophil Maturation
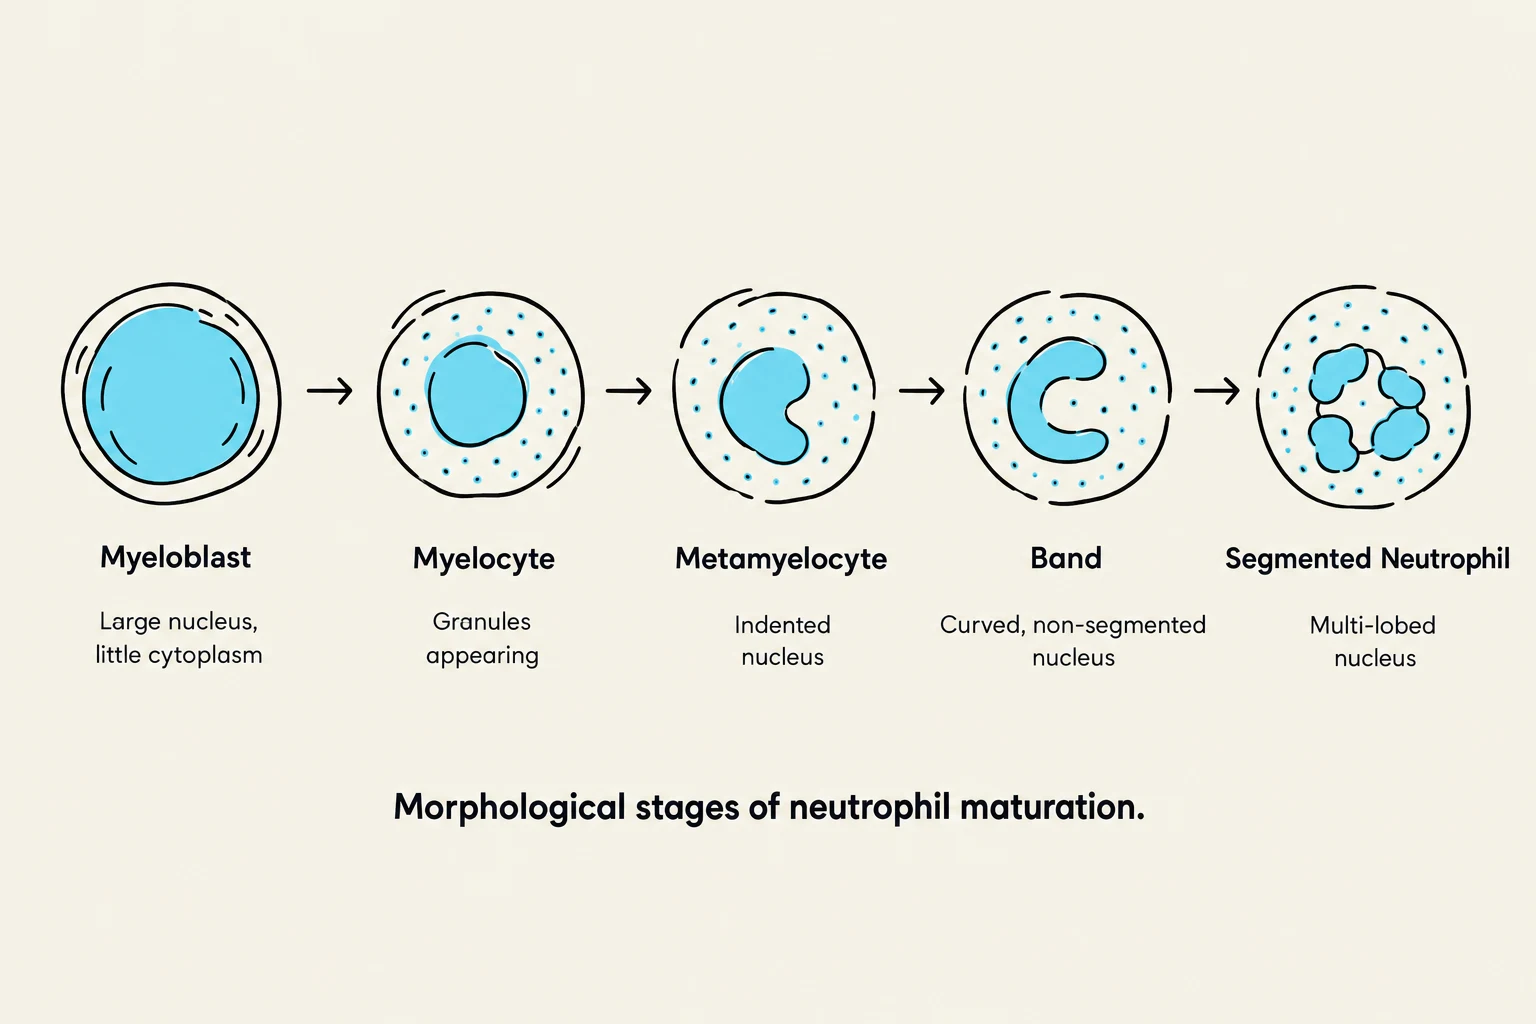
Morphological stages of neutrophil maturation.
The myeloid lineage produces granulocytes, the most prominent of which are neutrophils. Neutrophils are the "first responders" of the innate immune system, specialized in the ingestion and destruction of bacteria.
The Maturation Sequence
In the bone marrow, cells undergo a series of morphological changes. As they mature, they move through the following stages:
Myeloblast: The earliest recognizable precursor.
Myelocyte: The stage where specific granules begin to appear.
Metamyelocyte: A stage showing nuclear indentation.
Band: A cell with a curved, non-segmented nucleus.
Segmented Neutrophil: The fully mature cell with a lobulated nucleus.
A cell typically remains in the bone marrow for 5–7 days before being released into the blood. Once in the peripheral blood, they circulate for several hours before moving into the tissues, where they may spend 1–2 days.
Neutrophil Pools in Peripheral Blood
When examining a blood smear, neutrophils exist in two distinct functional groups:
Circulating Neutrophils (50%): These are free-floating in the bloodstream, ready to be deployed to sites of infection.
Marginating Neutrophils (50%): These are located adjacent to the endothelial lining of the blood vessels. They can be mobilized into the circulating pool by stimuli such as epinephrine.
Clinical Note: The "Left Shift"
During an infection, the bone marrow is stimulated to release cells more rapidly. This often results in the release of younger cells (like bands and metamyelocytes) into the blood, a phenomenon known as a "left shift".
The Mechanics of Neutrophil Function
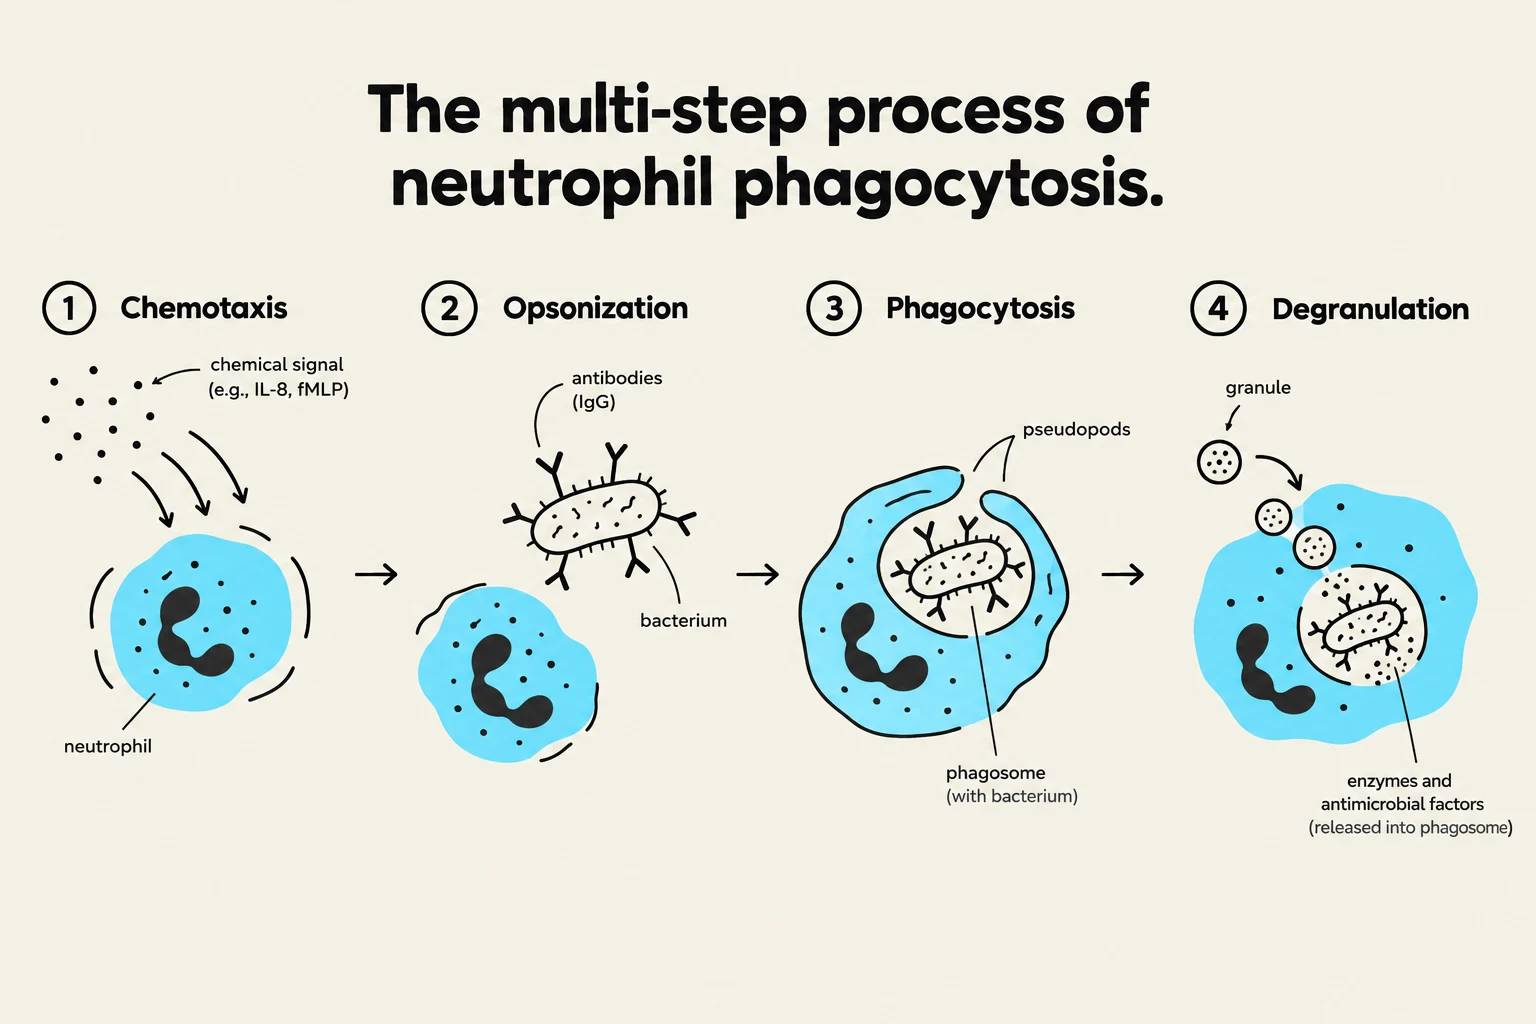
The diagram illustrates the four-step process of neutrophil phagocytosis: chemotaxis, opsonization, phagocytosis, and degranulation.
The primary role of the neutrophil is phagocytosis—the ingestion and destruction of microorganisms. This is a multi-step process:
Chemotaxis: Neutrophils are attracted to the infection site by chemical signals like C5a or antigen-antibody complexes.
Opsonization: The neutrophil "recognizes" the organism, often because the bacteria has been coated in antibodies or complement proteins.
Phagocytosis: The cell uses pseudopods to surround the organism, fusing them into a vesicle called a phagosome.
Degranulation and Killing: Granules within the neutrophil fuse with the phagosome to release enzymes. The cell also undergoes an "oxidative burst," reducing oxygen to create hydrogen peroxide, which reacts with myeloperoxidase to form hypochlorous acid (a bleach-like component) to kill the microbe.
Inflammation: As metabolites leak into surrounding tissue, they cause swelling and fever.
The Importance of Granules
Neutrophils contain three types of granules that are vital for survival:
Primary (Azurophilic) Granules: These appear first and contain myeloperoxidase to activate proteinases.
Secondary (Specific) Granules: These appear during the myelocyte stage and contain lysozymes that hydrolyze bacterial cell walls.
Tertiary Granules: The last to appear.
Exam Tip: If a patient has a deficiency in these granules, they will suffer from increased or recurrent infections because the cells lack the "weapons" necessary to kill bacteria.
Lymphocyte Production and Immunity
While neutrophils handle innate immunity, lymphocytes are the stars of adaptive immunity, facilitating both humoral (antibody-mediated) and cellular (cell-mediated) responses.
Maturation Sites
Lymphocyte development is divided into two phases:
Primary Maturation (Antigen-Independent): This occurs in the bone marrow and thymus. B cells stay in the bone marrow until they develop unique immunoglobulin antigen receptors, while T cells migrate to the thymus to complete their maturation.
Secondary Maturation (Antigen-Dependent): Once mature, lymphocytes move to the spleen and lymph nodes. Here, they only proliferate and "condition" themselves if they encounter a specific antigen.
Functional Types of Lymphocytes
T Cells: Central to cellular immunity. They can act as helper cells (stimulating antibody production) or suppressor cells (inhibiting it). They are also responsible for tumor immunity and graft-versus-host reactivity.
B Cells: These cells remain in a "resting stage" until they encounter an antigen. Once stimulated, they differentiate into plasma cells, which produce immunoglobulins (antibodies).
Natural Killer (NK) Cells: These are non-T and non-B cells that lyse tumor cells and virus-infected cells.
Clinical Correlations: Counts and Abnormalities
In the laboratory, we distinguish between relative counts (the percentage of a specific cell type out of 100 total WBCs) and absolute counts (the actual number of cells per microliter).
Neutrophil Disorders
Neutrophilia: An increased number of neutrophils, often seen in infection, stress, or inflammation.
Neutropenia: A decrease in mature neutrophils (<1500 cells/µL), which can lead to recurrent bacterial infections.
Lymphocyte Disorders
Lymphocytosis: A true increase is defined as an absolute count >4,000/μL. This is often seen in viral infections like Infectious Mononucleosis.
Reactive (Atypical) Lymphocytes: These are lymphocytes that have changed their appearance (becoming larger with stretched nuclei) because they are actively responding to a stimulus, such as the Epstein-Barr virus.
Lymphopenia: A decreased number of lymphocytes, which can be caused by HIV (which destroys helper T cells), chemotherapy, or aplastic anemia.
Calculating Absolute Counts
To find the absolute count, use the following formula:
Absolute Count=Relative %×Total WBC Count
Example:
If a patient has a total WBC of 8,000/μL and the differential shows $30%$ lymphocytes: