This guide explains the essential vocabulary used in clinical examinations to describe the morphology of oral lesions, including color, texture, borders, bases, and palpation findings. It categorizes lesions into flat, solid elevations, fluid-filled, and tissue loss types, providing clear definitions and examples for a
When performing a clinical examination of the oral cavity, the ability to accurately describe what you see is fundamental to reaching a correct diagnosis. A photograph can capture the appearance of a lesion, but it cannot convey the texture, depth, or mobility that a physical examination provides. To communicate effectively with other healthcare professionals, clinicians must use a standardized vocabulary of morphology to describe mucosal color, texture, borders, and the specific nature of the lesion.
Mucosal Color and Texture
Comparison of common mucosal surface textures: Smooth, Rough, Papillary, and Reticular.
The first step in any examination is assessing the color and surface of the mucosa. While we often refer to "normal" gingiva as pink, it is more accurate to describe a lesion's color in relation to the surrounding tissue. A "normal" finding is one where the tissue color blends seamlessly with the adjacent healthy tissue.
Color alone is rarely sufficient to establish a definitive diagnosis. For example, terms like "leukoplakia" are often used as descriptive placeholders when a lesion is white but cannot yet be categorized as a specific condition like lichen planus. Similarly, "erythroleukoplakia" describes a lesion that presents with both red and white components.
Beyond color, you must describe the texture of the mucosal surface. Common descriptors include:
Smooth: A regular, even surface.
Rough: An uneven or coarse texture.
Papillary: A surface with small, finger-like projections.
Reticular: A lacy or net-like pattern.
Crusted: A surface covered with dried exudate or debris.
Clinical Tip: Preparing the Site
If saliva is obscuring your view, do not rub the tissue with gauze, as this can alter the morphology or cause irritation. Instead, gently pat or blot the area with a 2x2 gauze to dry it.
Borders, Bases, and Palpation
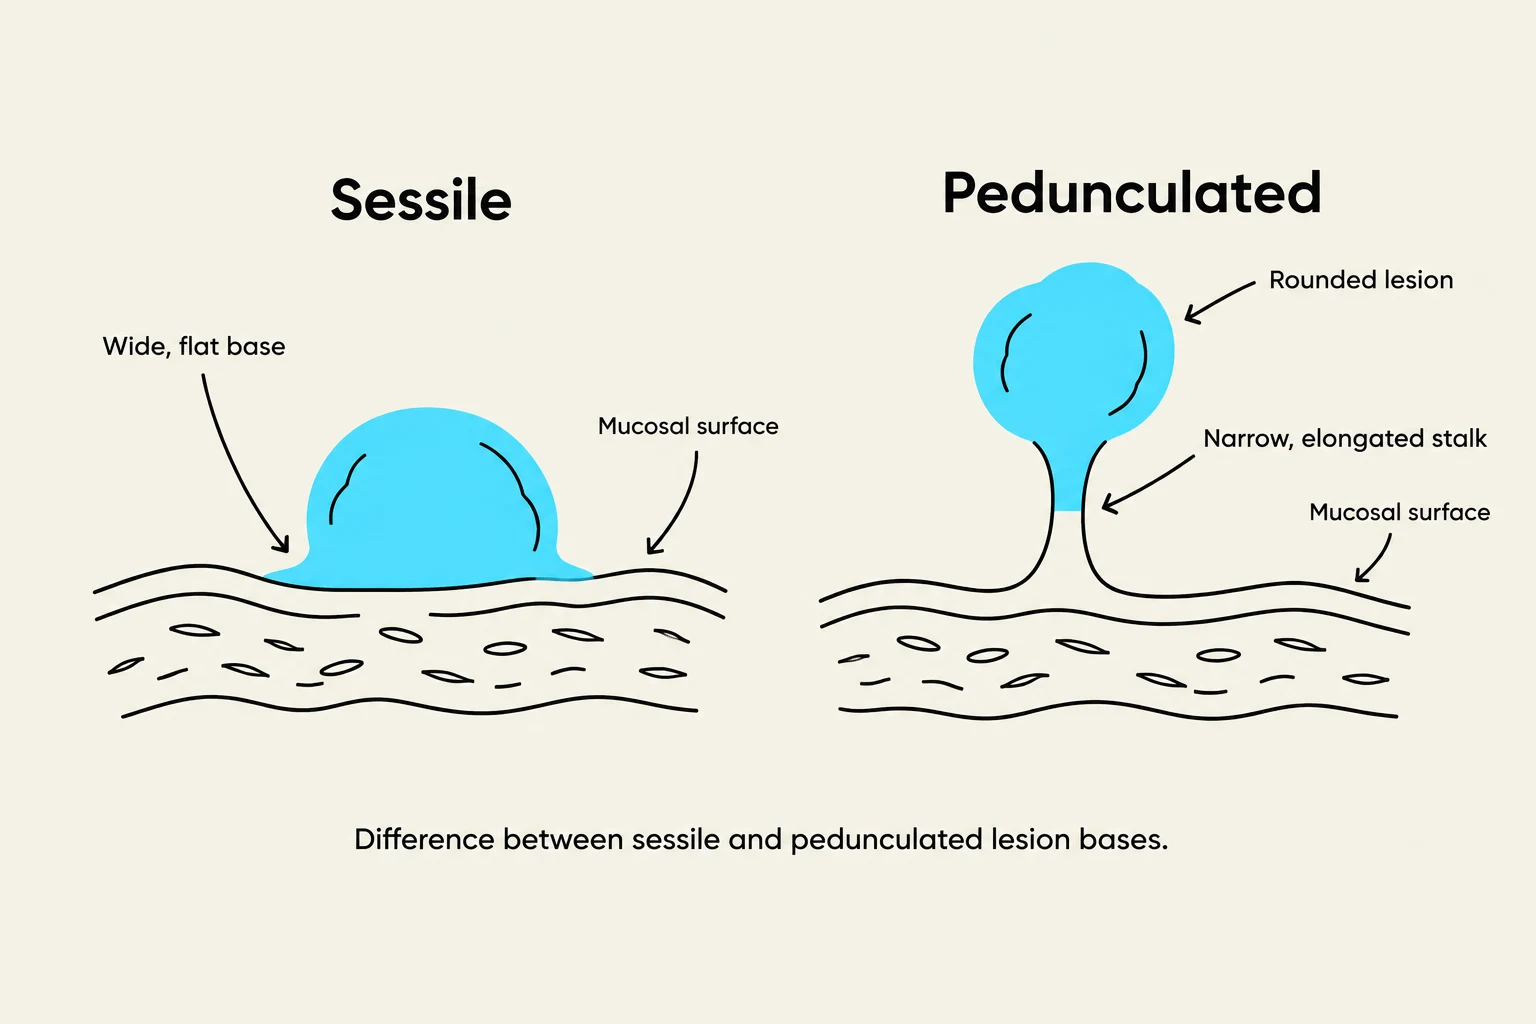
Diagram illustrating the difference between sessile and pedunculated lesions, highlighting their bases and structures.
Once the surface is visible, you must define the boundaries and the way the lesion attaches to the tissue.
Borders and Margins
A lesion may have well-defined margins, where there is a clear demarcation between the lesion and the healthy tissue, or poorly defined margins, where the lesion gradually blends into the surrounding mucosa. You should also note if the edges are rolled, irregular, or if the lesion is flat or elevated.
Sessile vs. Pedunculated
The "base" refers to how the lesion attaches to the underlying tissue:
Sessile: The lesion has a broad base of attachment.
Pedunculated: The lesion is attached to the tissue by a small stalk.
Palpation Findings
Palpation is essential because a photo cannot tell you how a lesion feels. During palpation, assess the following:
Tenderness: Does the patient experience pain upon touch?
Consistency: Is the tissue soft, firm, hard, or indurated (hardened)?
Fluctuance: Does the lesion feel like it contains fluid?
Mobility: Does the lesion roll around in the tissue, or is it "fixed" to deeper structures? (Fixation is particularly important to note when examining lymph nodes).
Classification of Lesion Types
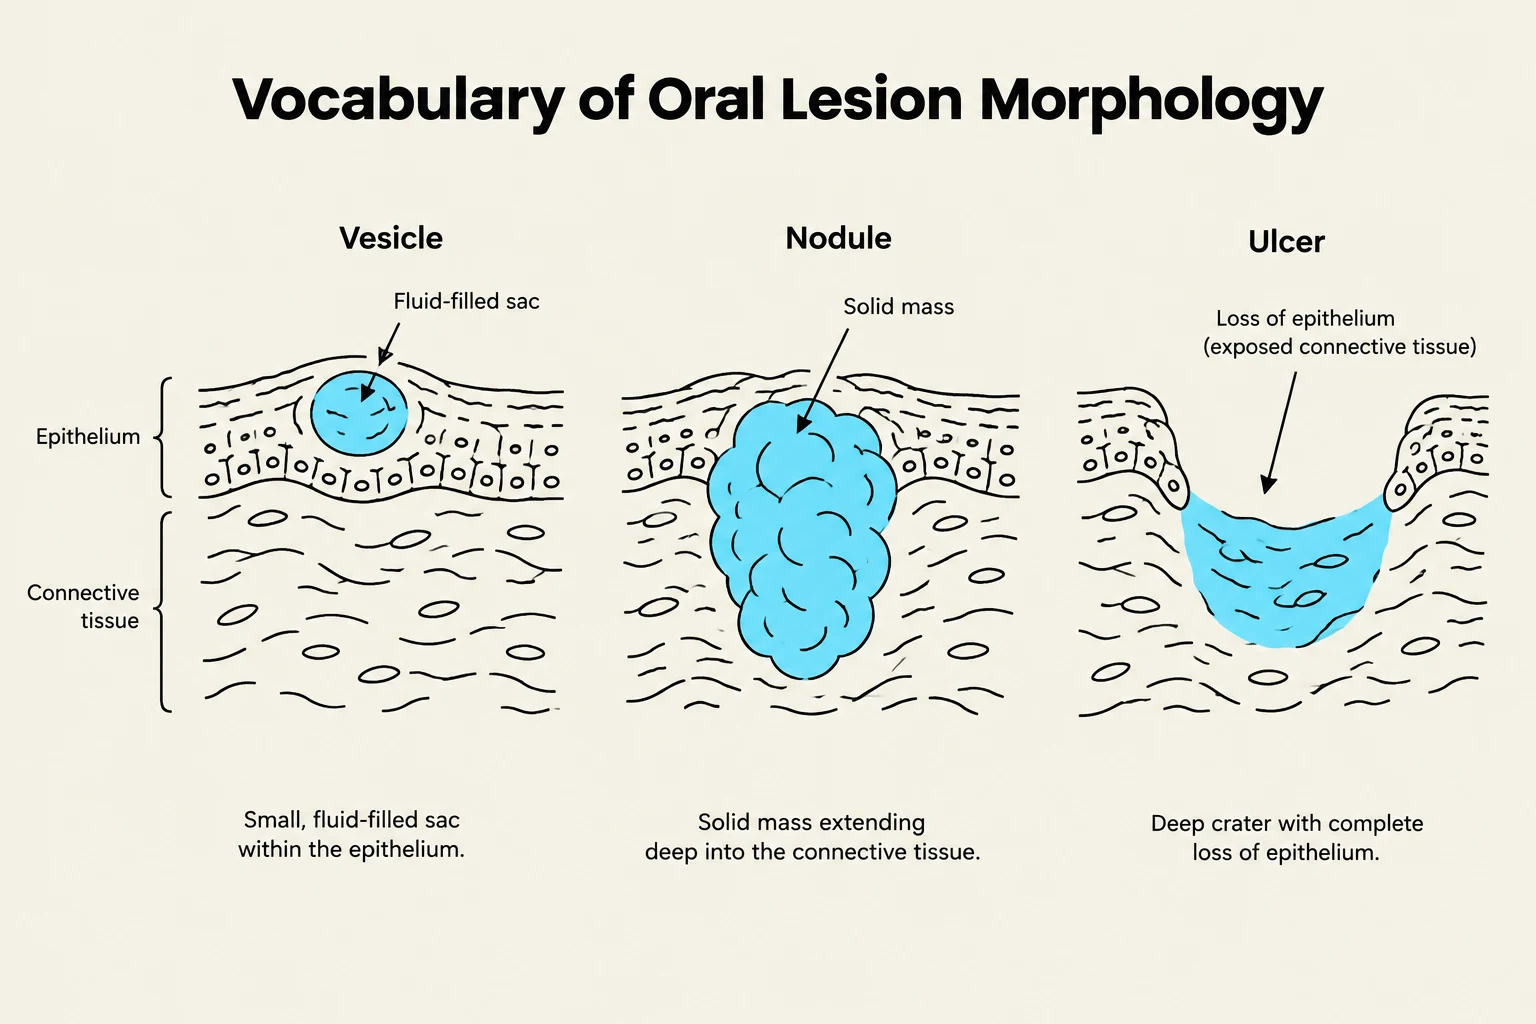
This diagram illustrates and defines three types of oral lesions: vesicle, nodule, and ulcer, based on their morphology and location within the epithelium and connective tissue.
Morphological terms are often categorized by whether the lesion is flat, solid, or fluid-filled.
Flat Lesions: Macules and Patches
Both macules and patches represent a change in color without any change in the elevation of the tissue. They are flush with the surrounding mucosa.
Macule: A small, flat area of color change.
Patch: A larger area of color change.
Solid Elevations: Papules, Nodules, and Plaques
These terms describe elevations that are solid rather than fluid-filled.
Papule: A small, solid elevation or "bump".
Nodule: A solid elevation that extends deeper into the connective tissue rather than just sitting on the surface.
Plaque: A broad, relatively flat, elevated surface.
Clinical Tip: Precise Measurement
Avoid relying solely on descriptive terms like "small" or "large." Always record the actual dimensions in millimeters (e.g., "4 mm papule"). If taking a photo for documentation, place a periodontal probe next to the lesion to provide a scale for measurement.
Fluid-Filled Lesions: Vesicles and Bullae
These lesions are characterized by a fluid-filled sac beneath a thin "roof" of tissue.
Vesicle: A small, fluid-filled sac.
Bulla: A larger fluid-filled sac.
Note that oral roofs are very thin and fragile; therefore, vesicles and bullae can rupture easily.
Loss of Tissue: Erosions and Ulcers
When the epithelial layer is lost, the lesion is classified based on the depth of that loss:
Erosion: A superficial loss of the epithelial layer that does not extend deep into the connective tissue.
Ulcer: A deeper loss of tissue that extends through the epithelium and may expose the underlying connective tissue.
Clinical Tip: The "Ruptured Blister" Phenomenon
Many patients will describe having "blisters" (vesicles or bullae), but when they arrive at the clinic, you may only see erosions or ulcers. This is because the fragile fluid-filled sacs often rupture before the examination. In such cases, always ask the patient if they have had similar lesions on their skin, eyes, or genital area, as certain syndromes present with a triad of oral, ocular, and genital involvement.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.