Understanding the hemodynamics of the arterial system and the technology used to visualize them is a cornerstone of vascular ultrasound. By combining the physics of the Doppler effect with a deep knowledge of human anatomy, clinicians can assess blood flow velocity, direction, and the presence of pathology such as stenosis or occlusion. This article explores the different Doppler modalities, the characteristics of arterial waveforms, and the complex anatomy of the carotid and cerebral circulation.
This diagram compares Continuous Wave (CW), Pulsed Wave (PW), and Power Doppler ultrasound modalities, illustrating their distinct operational principles and signal representations.
Doppler Modalities
In vascular ultrasound, we use different modes to capture specific types of information regarding blood movement. The choice of modality depends on whether the clinician needs to measure velocity, determine the location of flow, or simply confirm its presence.
Continuous Wave (CW) Doppler
Continuous Wave Doppler utilizes a minimum of two crystals to transmit and receive sound simultaneously. Because it is constantly transmitting and receiving, it has no limit on the maximum velocity it can measure and is entirely free of aliasing. However, the trade-off for this unlimited speed capability is "range ambiguity," meaning the device cannot tell exactly where along the beam the flow is occurring.
Pulsed Wave (PW) Doppler
Pulsed Wave Doppler uses a minimum of one crystal to send short pulses of sound. This allows for excellent range resolution, meaning the sonographer can place a "sample volume" at a specific depth to measure flow at a precise location. The primary limitation of PW Doppler is that it is subject to aliasing; if the blood velocity exceeds the limit set by the Pulse Repetition Frequency (PRF), the waveform will appear distorted.
Power Doppler (Angio Doppler)
Power Doppler is an energy-based mode that focuses on the amplitude of the Doppler signal rather than the frequency shift. This makes it highly sensitive to slow, deep, or extremely tiny vessels. It is not angle-dependent and is free of aliasing. While it is excellent for visualizing the presence or absence of flow, it provides no data regarding the direction or the speed of that flow.
Exam Tip: If you need to see if a tiny vessel is patent (open) but don't care about how fast the blood is moving, use Power Doppler. If you need to measure a high-velocity jet in a stenosis, use Continuous Wave Doppler.
Waveform Components and Resistance Profiles
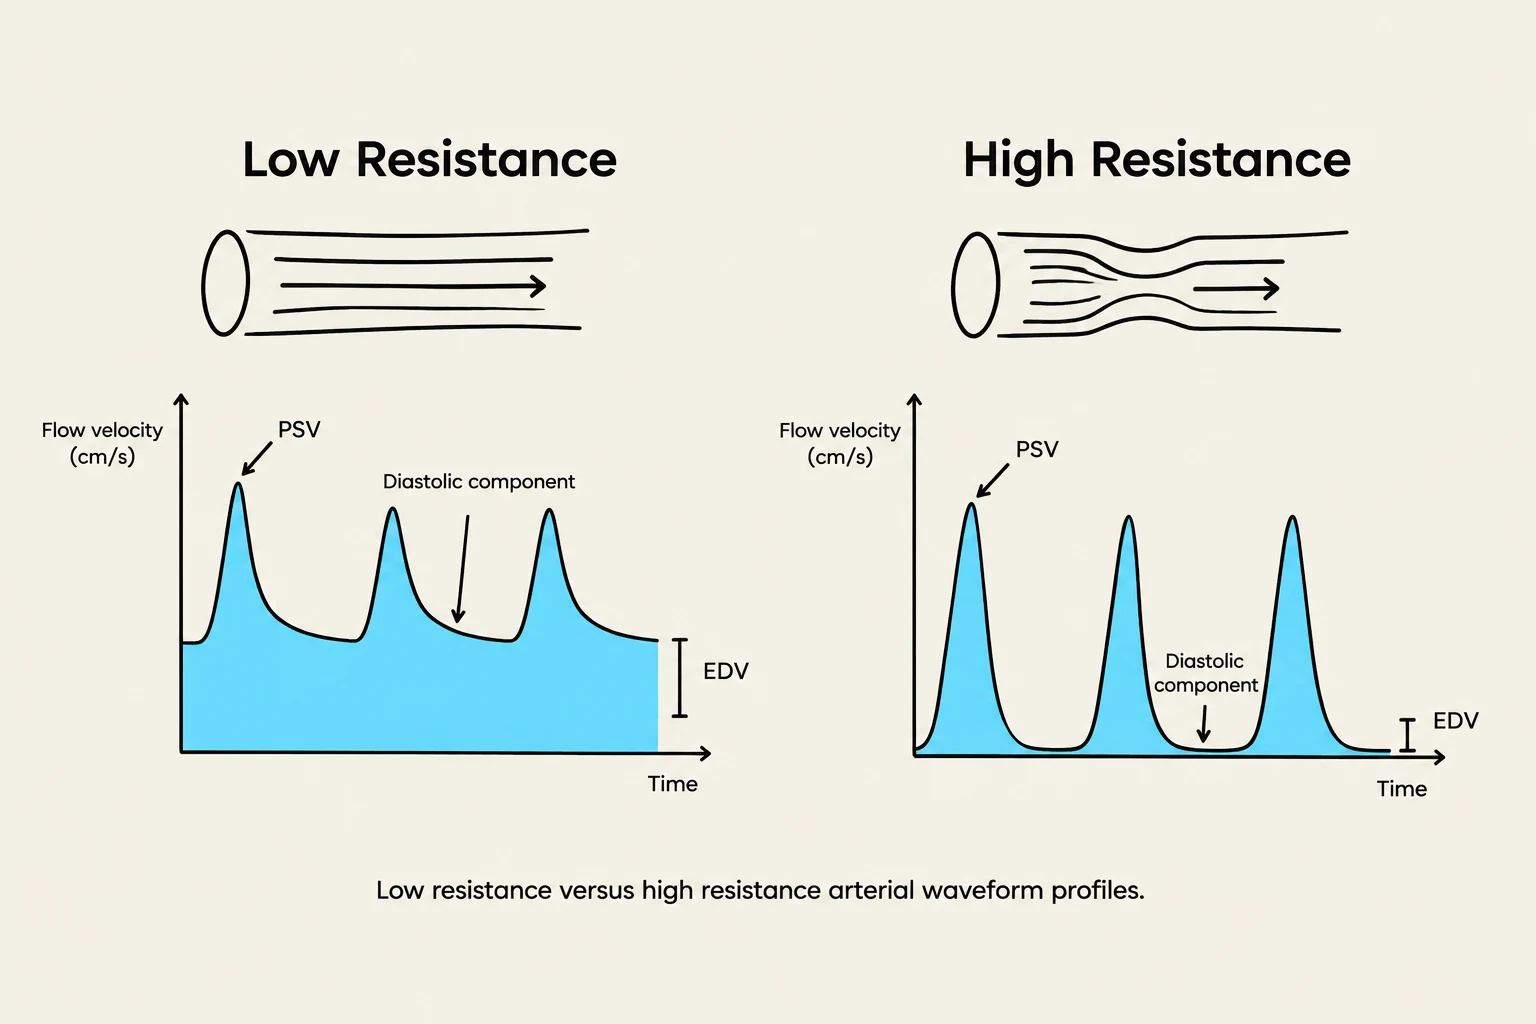
Comparison of arterial waveform profiles in low resistance versus high resistance conditions, illustrating flow velocity over time.
When viewing a spectral Doppler waveform, several components are analyzed to determine the health of the vessel. These include the Peak Systolic Velocity (PSV), the End Diastolic Velocity (EDV), the spectral envelope, the spectral window, and the dicrotic notch.
The shape of these waveforms is determined by the resistance of the distal vascular bed. Arteries are categorized into three main profiles:
Low Resistance Flow: These vessels exhibit continuous, steady flow throughout both systole and diastole. A high diastolic component indicates that the vessel supplies a highly vascular organ that requires constant blood supply. Examples include the Internal Carotid Artery (ICA), renal, vertebral, and hepatic arteries.
High Resistance Flow: These vessels show pulsatile flow (often triphasic or biphasic) with a significantly decreased or absent diastolic component. This indicates the vessel supplies a peripheral bed where constant flow is not necessary. Examples include the External Carotid Artery (ECA), aorta, and extremity arteries.
Mixed Resistance: Some vessels act as a transition. The Common Carotid Artery (CCA) displays a combination of both high and low resistance characteristics.
Carotid Artery Anatomy
The carotid system is the primary pathway for blood traveling from the heart to the brain. The CCA ascends the neck and eventually bifurcates into two distinct vessels: the ICA and the ECA.
The Carotid Bulb
The carotid bulb is located at the junction of the distal CCA and the proximal ICA. This anatomical landmark is clinically significant because it is one of the most common sites for plaque formation.
Internal Carotid Artery (ICA)
The ICA is the larger of the two branches and is characterized by low-resistance flow. Anatomically, it is positioned posterior-lateral to the ECA. A key diagnostic feature is that the ICA has no branches in the cervical (neck) region.
The ICA is divided into four major sections:
Extracranial (Cervical): The longest portion, which is the primary area for clinical scanning.
Intracranial (Petrous Cavernous/Carotid Siphon): An S-shaped section.
Ophthalmic Section: This section gives rise to the ophthalmic artery, which supplies the eyes, forehead, and nose.
Supraclinoid: The distal portion where the ICA terminates into the ACA and MCA.
External Carotid Artery (ECA)
The ECA is smaller than the ICA and exhibits high-resistance flow. It is positioned anterior-medial to the ICA. Unlike the ICA, the ECA has eight distinct branches that supply the face, scalp, neck, and jaw. These include the superior thyroid, ascending pharyngeal, lingual, facial, occipital, posterior auricular, maxillary, and superficial temporal arteries.
Cerebral Circulation and the Circle of Willis
The brain's blood supply is divided into two main circuits: the Anterior Circulation and the Posterior Circulation.
Anterior Circulation: Includes the extracranial CCA/ICA and the intracranial Anterior Cerebral Artery (ACA) and Middle Cerebral Artery (MCA).
Posterior Circulation: Includes the extracranial Vertebral Arteries and the intracranial Posterior Cerebral Artery (PCA) and Basilar Artery.
The Circle of Willis and Collateralization
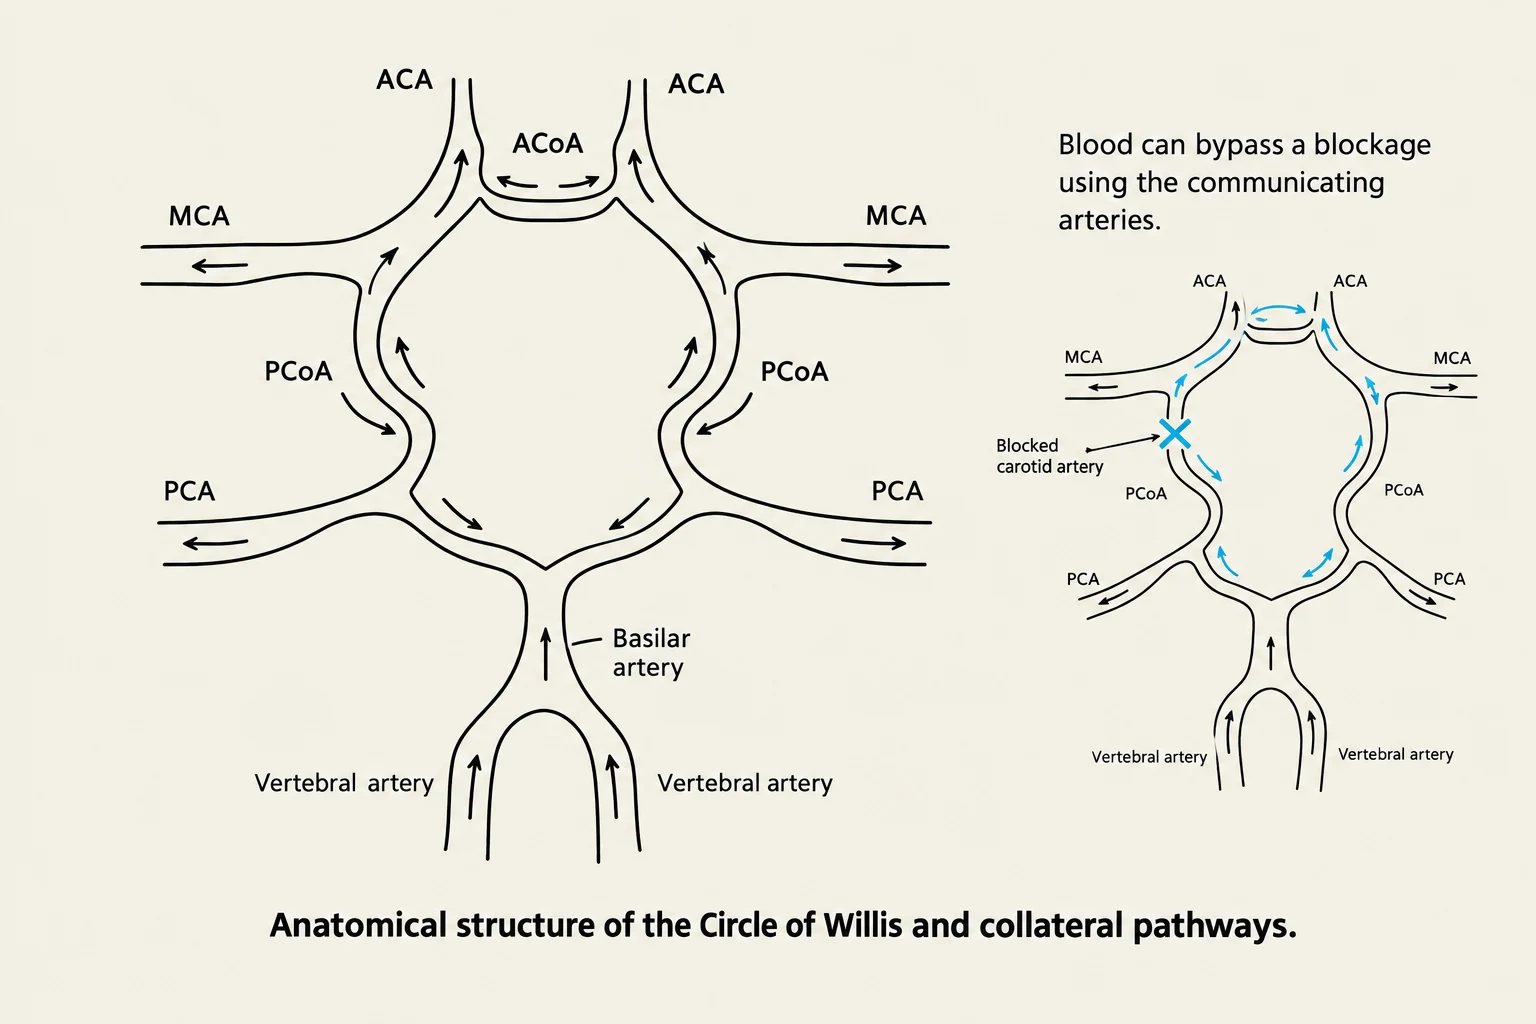
Anatomical structure of the Circle of Willis and collateral pathways.
The Circle of Willis is a vital anastomotic network located at the base of the brain. It is formed by the connection of the ICA and the vertebral/basilar arteries. The primary purpose of this network is collateralization—providing alternative pathways for blood to reach brain tissue in the event of a stenosis or total occlusion in one of the main feeder arteries.
The network is composed of several key vessels:
ACA (Anterior Cerebral Artery): Carries 20% to 30% of cerebral blood.
MCA (Middle Cerebral Artery): The largest contributor, carrying 70% to 80% of cerebral blood.
PCA (Posterior Cerebral Artery): Feeds the posterior structures of the brain.
ACoA (Anterior Communicating Artery): Connects the left and right anterior circulations.
PCoA (Posterior Communicating Artery): Connects the anterior circulation to the posterior circulation.
By understanding these anatomical connections, clinicians can better predict how a patient's brain might compensate for vascular disease.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.