Diabetes Mellitus is a metabolic disorder characterized by abnormally high levels of glucose in the bloodstream. While the condition is categorized into several subtypes—including Type 1, Type 2, and Gestational diabetes—the underlying physiological mechanisms and management strategies vary significantly between them. Understanding the role of the pancreas and the specific nuances of Type 1 Diabetes Mellitus (T1DM) is essential for effective clinical management and patient education.
The Pancreas and Endocrine Function
The cellular structure of the Islets of Langerhans, showing alpha, beta, delta, and epsilon cells and their respective hormones (glucagon, insulin, somatostatin, and ghrelin) and their interaction with a capillary.
The pancreas is a unique organ that serves both exocrine and endocrine functions. While its exocrine function involves producing digestive enzymes and bicarbonate to neutralize stomach acid, its endocrine function is critical for glucose homeostasis.
The endocrine portion of the pancreas consists of clusters of cells known as the Islets of Langerhans. Within these islets, specialized cells secrete hormones directly into the bloodstream to regulate metabolism:
Alpha cells: Produce glucagon, a hormone that raises blood sugar levels.
Beta cells: Produce insulin and amylin, which work to lower blood sugar levels.
Delta cells: Secrete somatostatin, which helps regulate the secretion of other hormones.
Epsilon cells: Produce ghrelin, often referred to as the "hunger hormone".
In a healthy individual, the body maintains a balance between these hormones. For example, insulin levels spike when carbohydrates are consumed to manage the influx of glucose, while basal levels of insulin are produced continuously throughout the day.
Pathophysiology: Type 1 vs. Type 2 Diabetes
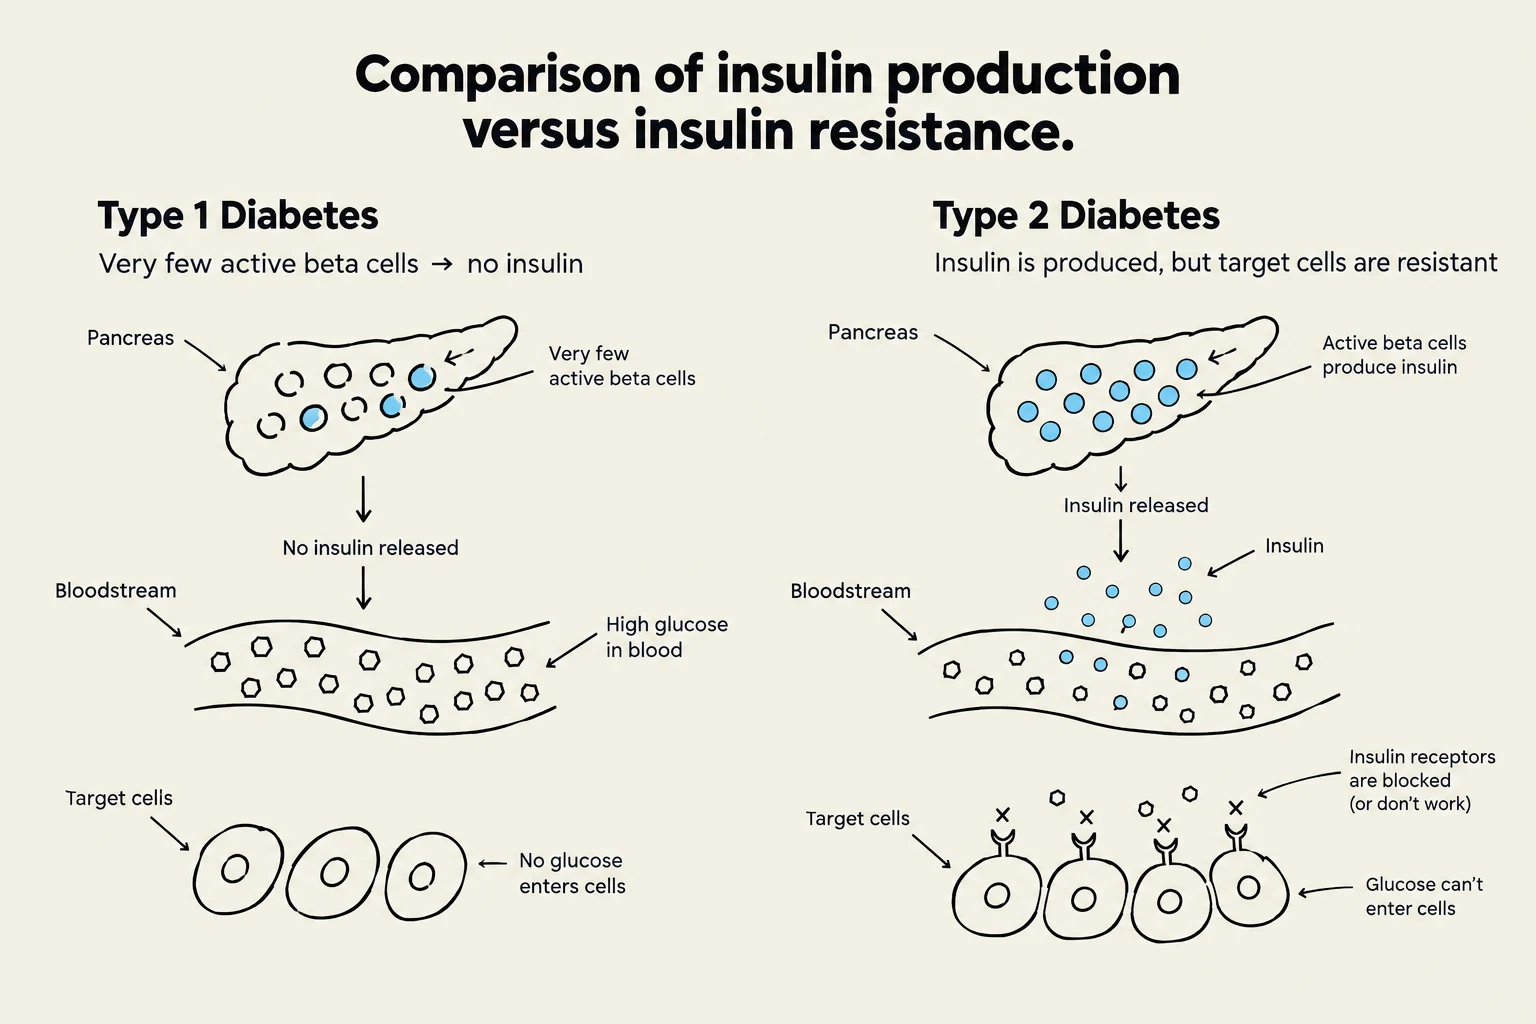
This diagram compares insulin production and function in Type 1 Diabetes, where there is little to no insulin production, and Type 2 Diabetes, where insulin is produced but target cells are resistant.
The primary distinction between the major types of diabetes lies in the mechanism of insulin deficiency or dysfunction.
Type 1 Diabetes Mellitus (T1DM)
T1DM occurs when the pancreas is unable to produce sufficient insulin. This is often an autoimmune process that typically develops at a young age and cannot be prevented. Because the body lacks endogenous insulin, patients with T1DM require lifelong insulin therapy to survive.
Type 2 Diabetes Mellitus (T2DM)
In contrast, T2DM is primarily driven by insulin resistance, a state where the body's cells do not respond effectively to the insulin being produced. T2DM tends to develop later in life and can often be prevented or managed through lifestyle modifications, such as diet and physical activity.
Despite these differences, both types share common symptoms, including:
Polyuria (frequent urination)
Polydipsia (increased thirst)
Polyphagia (extreme hunger)
Fatigue and blurred vision
Exam Tip: When distinguishing between the two, remember that Type 1 is a problem of production (absolute deficiency), whereas Type 2 is a problem of response (resistance).
Clinical Diagnosis and Monitoring
To diagnose diabetes, clinicians look for specific thresholds in blood glucose measurements:
Hemoglobin A1C (HbA1C): A measure of the average blood sugar levels over the past three months. A level ≥6.5% is indicative of diabetes.
Fasting Plasma Glucose: Measured after at least 8 hours of no caloric intake. A level ≥7.0 mmol/L indicates diabetes.
Random Plasma Glucose: A measurement taken at any time. A level ≥11.1 mmol/L indicates diabetes.
Patients must also monitor for acute complications: hypoglycemia (low blood sugar, typically <4 mmol/L) and hyperglycemia (high blood sugar). Hypoglycemia is often considered the immediate priority in clinical settings because severe episodes can be life-threatening.
Management of Type 1 Diabetes
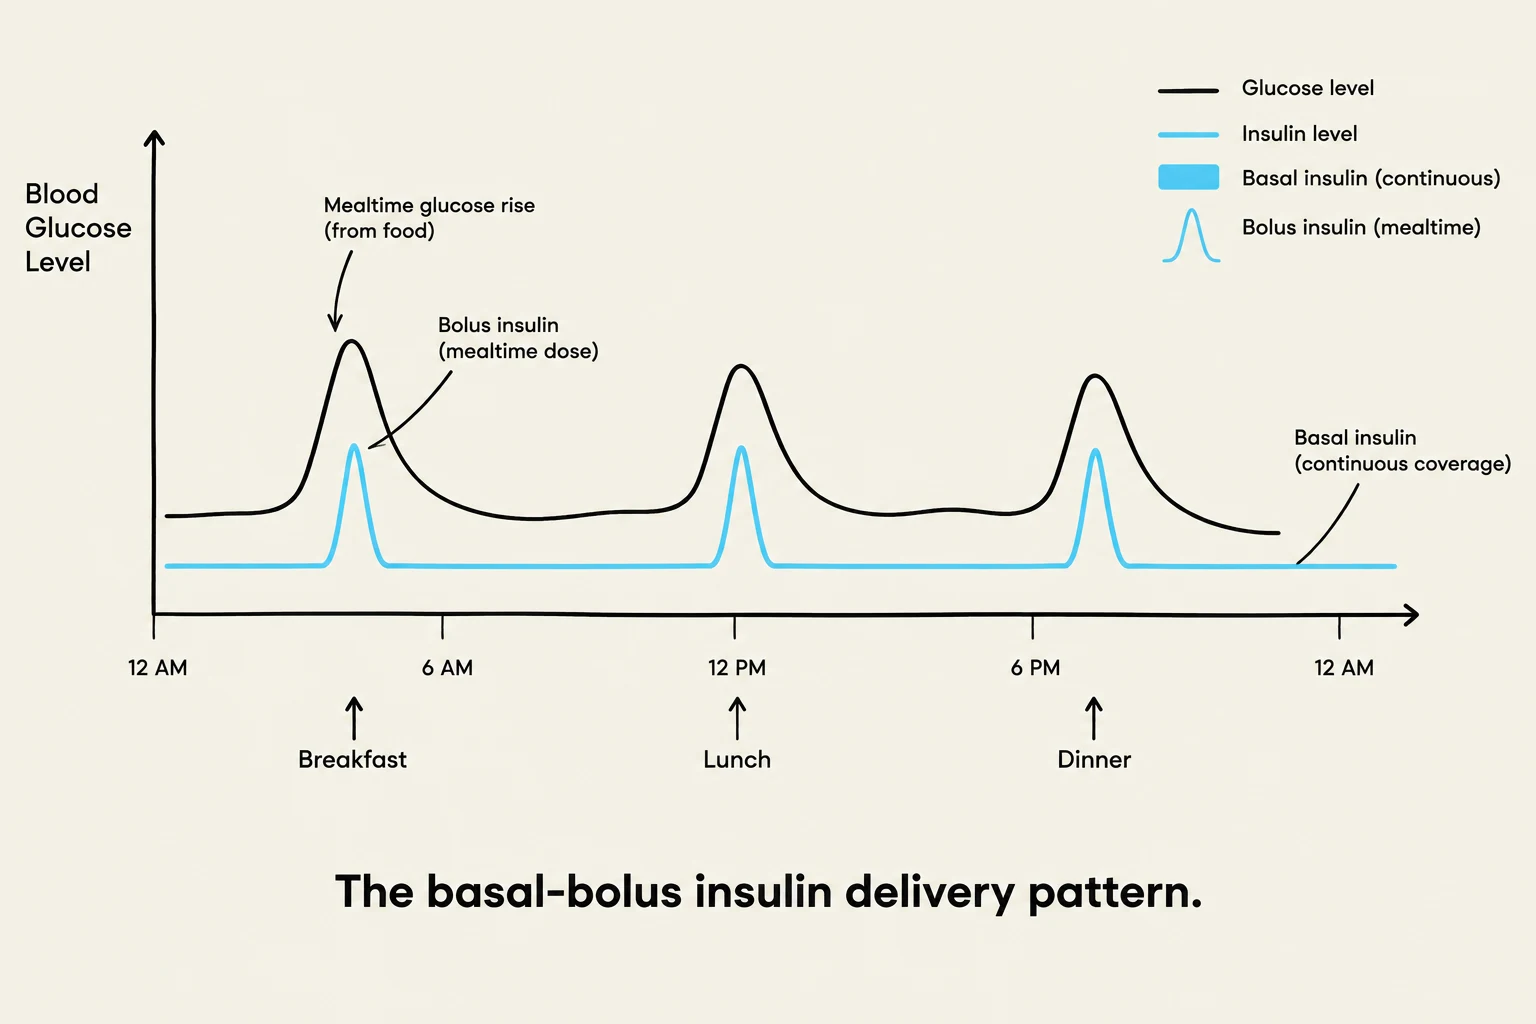
This graph illustrates the basal-bolus insulin delivery pattern, showing how blood glucose levels fluctuate throughout the day in response to meals and insulin administration.
Management of T1DM focuses on mimicking the natural "basal-bolus" pattern of insulin secretion.
Insulin Regimens
Treatment involves using different types of insulin to provide both continuous coverage and mealtime spikes:
Basal Insulin: Provides a steady background level of insulin.
Long-acting: Such as Insulin Glargine (Lantus, Toujeo) or Insulin Degludec (Tresiba).
Intermediate-acting: Such as NPH, which is "cloudy" and usually requires twice-daily dosing.
Ultra-long-acting: Such as Insulin Icodec, which can be dosed once weekly.
Bolus Insulin: Used to manage glucose spikes after eating.
Rapid-acting: Such as Insulin Aspart (NovoRapid, Trurapi) or Insulin Lispro (Humalog).
Short-acting: Such as Regular Insulin (Humulin R), which has a slower onset than rapid-acting analogues.
Advanced Delivery and Monitoring
Patients may use insulin pumps to deliver fast-acting insulin at pre-programmed basal rates and mealtime boluses. To monitor their progress, patients use various technologies:
Glucometers: Traditional finger-prick testing.
Flash Glucose Monitoring (FGM): Such as the Freestyle Libre, which requires periodic scanning.
Continuous Glucose Monitoring (CGM): Such as Dexcom, which provides real-time, continuous data without the need for manual scanning.
Complications of Diabetes
Failure to maintain glycemic control can lead to severe long-term complications, categorized into two groups:
Microvascular Complications (damage to small blood vessels):
Retinopathy (eyes)
Nephropathy (kidneys)
Neuropathy (nerves)
Macrovascular Complications (damage to large blood vessels):
Coronary Artery Disease
Peripheral Artery Disease
Cerebrovascular Accidents (stroke)
Clinical Note: Managing insulin demands requires balancing several factors, including diet, physical activity, stress, sleep, and weight.
Worked Example: Dosing Calculation
Scenario: A patient requires insulin therapy. Their Total Daily Dose (TDD) is calculated to be 24 units. Following a standard basal-bolus split of 50/50, how should this be distributed?
Solution:
To find the basal and bolus amounts, we divide the TDD by 2:
Basal Dose=224 units=12 unitsBolus Dose=224 units=12 units
The patient would then administer 12 units of long-acting (basal) insulin daily and divide the remaining 12 units of short-acting (bolus) insulin among their meals (e.g., 4 units at breakfast, 4 at lunch, and 4 at dinner).
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.