This guide explains the distinctions between crisis and trauma, the anatomy of traumatic experiences, and the role of Polyvagal Theory and the Window of Tolerance in understanding stress responses. It also covers clinical tools like grounding and psychological safety, and the importance of self-care for practitioners.
In the field of social services, understanding the nuances of human distress is fundamental to providing effective care. Practitioners must navigate a complex landscape of immediate emergencies and long-term psychological injuries. To do this effectively, one must adopt a trauma-informed lens, which prioritizes psychological safety and recognizes the profound impact of traumatic stress on the human nervous system.
Distinguishing Crisis from Trauma
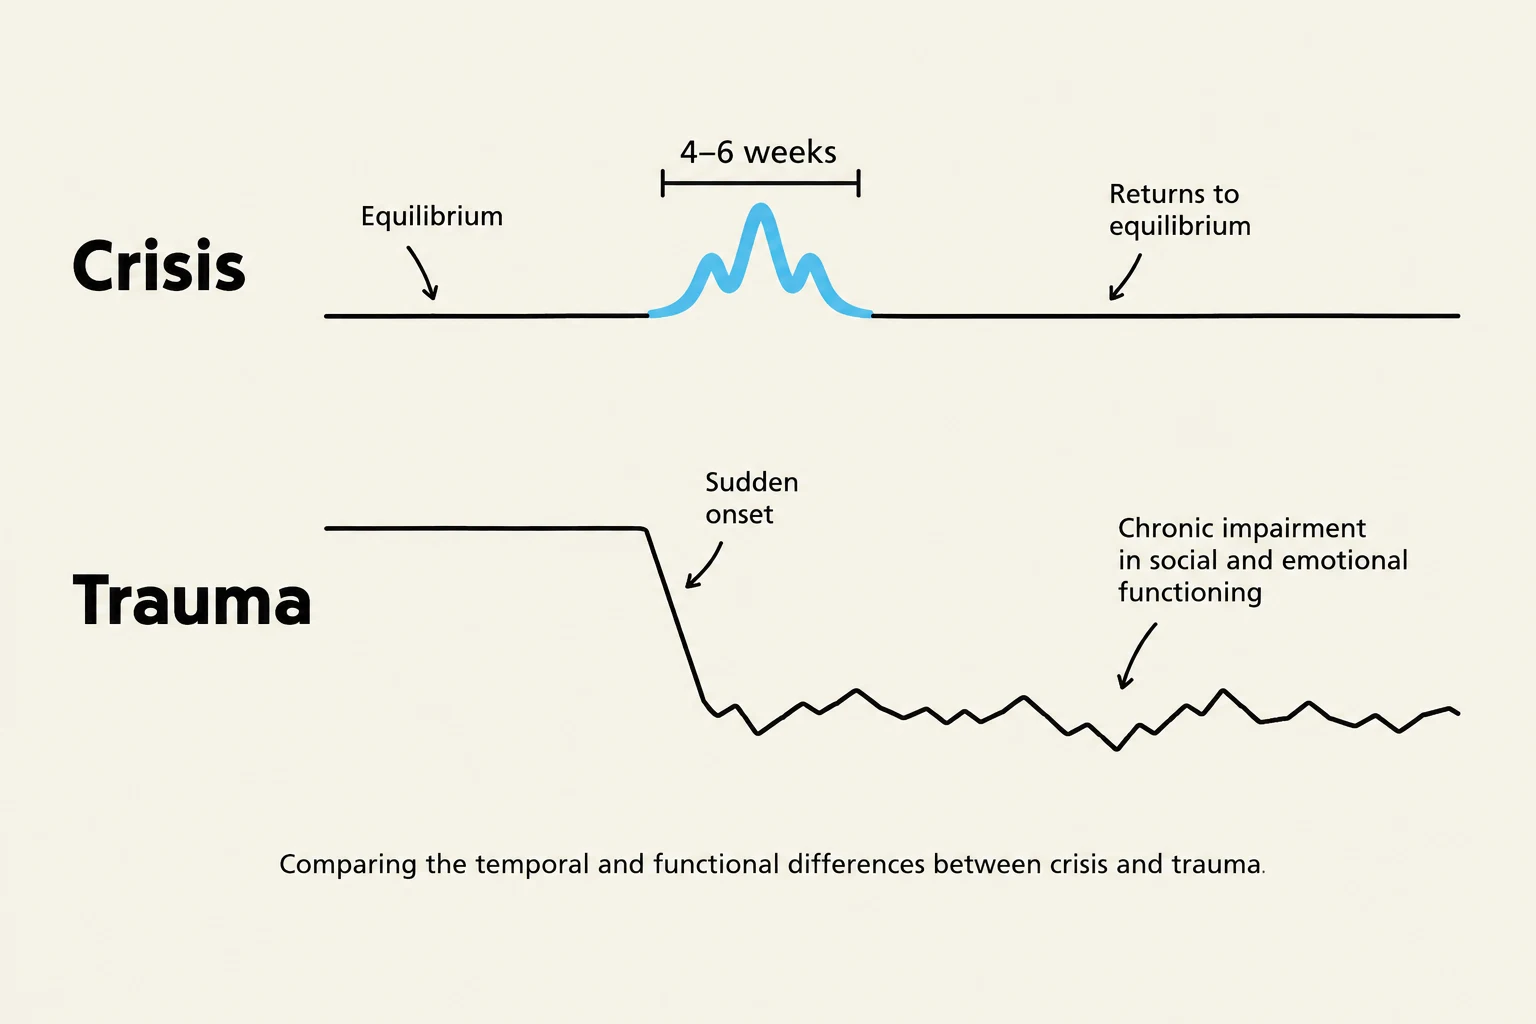
This diagram illustrates the differing temporal and functional impacts of crisis and trauma, showing a temporary disruption for crisis and a more prolonged impairment for trauma.
A common challenge for new practitioners is distinguishing between a crisis and trauma. While these terms are often used interchangeably in casual conversation, they represent different temporal and psychological states.
Crisis Intervention
A crisis is defined as a period of unusual stress that temporarily renders an individual unable to direct their life effectively. By nature, a crisis is time-limited, typically lasting approximately 4 to 6 weeks. This is because the human psyche generally cannot tolerate extreme tension and psychological disequilibrium for longer periods without seeking a new state of equilibrium.
TraumaTrauma occurs when an experience is so extreme, unexpected, and overwhelming that it exceeds an individual's capacity to cope, causing a disconnection from safety, resourcefulness, or love. While every trauma begins as a crisis, not every crisis results in trauma. Unlike a crisis, trauma can lead to chronic responses that impair long-term social, emotional, and occupational functioning.
Exam Tip: Remember that the primary distinction lies in duration and impact. A crisis is a temporary state of disequilibrium (4–6 weeks), whereas trauma involves a lasting disruption to the individual's sense of safety and ability to function.
The Anatomy of a Traumatic Experience
What transforms a stressful event into a traumatic one? According to the Trauma Toolkit, there are three common elements that define a traumatic experience:
The event was unexpected.
The individual was unprepared.
The individual felt unable to stop the event.
Furthermore, the nature of the event—often involving feared or actual death or serious injury—plays a role, but the individual's subjective meaning of the event is equally critical. The same event may be traumatic for one person but not for another based on individual differences.
Polyvagal Theory and the Window of Tolerance
To understand why traumatized individuals react the way they do, we must look at the nervous system through the lens of Polyvagal Theory. This theory explains how our autonomic nervous system regulates our responses to perceived threats.
The Window of Tolerance
The Window of Tolerance and autonomic nervous system states.
The Window of Tolerance (or the Optimal Zone of Arousal) is the state in which an individual can effectively manage emotions and process information. Within this window, the Ventral Vagal Nerve is stimulated, allowing for:
Social engagement: The ability to connect with others.
Emotional regulation: The ability to experience a full range of emotions with a sense of control.
Effective learning: Full activation of the pre-frontal cortex, allowing for intuition, insight, and new learning.
Moving Out of the Window
When a person encounters traumatic stress, they are pushed out of this optimal zone into one of two survival states:
1. Hyperarousal (The Sympathetic System)
This is the "Fight or Flight" response. The body accelerates its autonomic response, leading to increased heart rate and blood pressure.
Symptoms: Hyper-vigilance, anxiety, racing thoughts, and disorganized cognitive processing.
Impact: In this state, the individual perceives constant danger, and no new learning can take place.
2. Hypoarousal (The Dorsal Vagal Nerve)
This is the "Freeze" response. The body undergoes extreme deceleration.
Symptoms: Numbness, dissociation (a disconnection from awareness), depression, hopelessness, and a "shut-down" response.
Impact: Like hyperarousal, this state prevents the individual from integrating new information or learning.
Clinical Tools: Grounding and Psychological Safety
When working with clients experiencing flashbacks (re-experiencing trauma) or dissociation, practitioners must utilize grounding skills. Grounding is a specific type of coping strategy designed to immediately connect an individual to the present moment, helping to manage intense anxiety or overwhelming sensations.
In a professional setting, creating psychological safety—the ability for a client or student to speak up without fear—is a cornerstone of trauma-informed practice.
The Practitioner's Responsibility: Self-Care and Self-Compassion
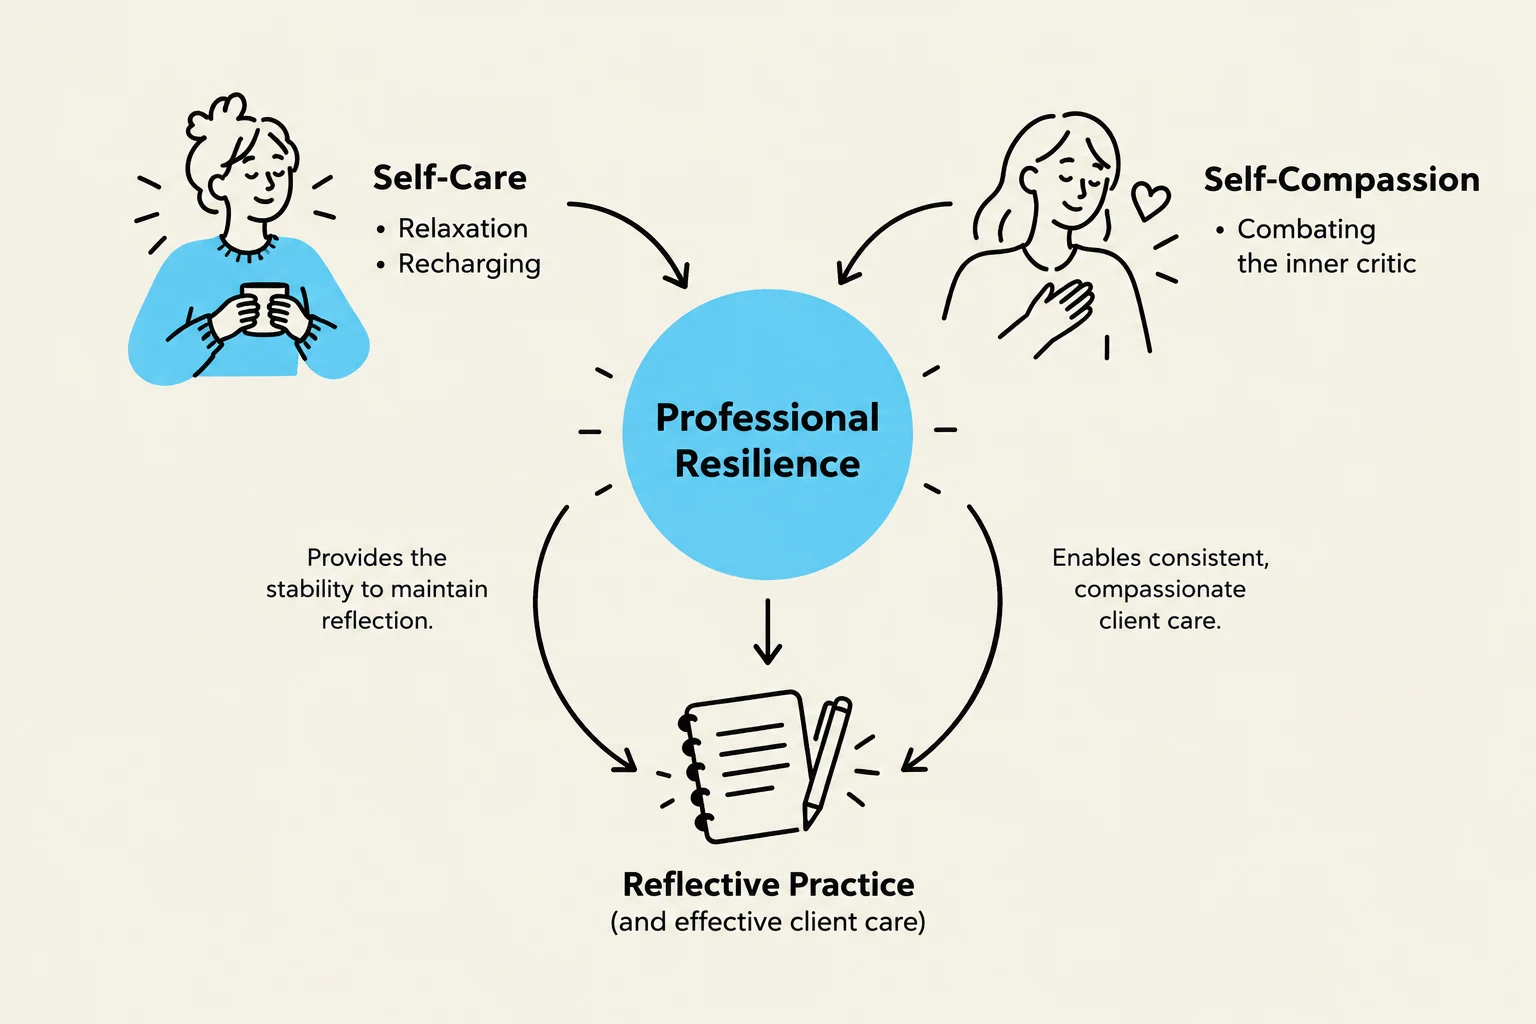
A diagram illustrating the components of professional resilience, including self-care, self-compassion, and reflective practice, and their interrelationships.
Working with sensitive content, including violence and harm, can be taxing for social service workers. To maintain professional resilience, practitioners must prioritize two internal practices:
Self-care: Engaging in regular activities to reduce stress and enhance long-term well-being. This includes knowing how to relax, recharge, and self-soothe.
Self-compassion: Treating oneself with the same kindness one would offer a friend. This is a vital tool for combating the "inner critic" that often arises in high-stress professions.
Reflective Practice: As you move forward in your training, always check in with yourself. Recognize your own triggers and develop a personal plan for coping to ensure you can remain present for those you serve.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.