Understanding Thyroid Dysfunction and Its Pharmacological Management
This guide explains the endocrine system, focusing on the hypothalamic-pituitary-thyroid axis, and details the causes, manifestations, and pharmacological treatments for hypothyroidism and hyperthyroidism. It covers key medications, drug interactions, and clinical monitoring strategies.
The endocrine system is a sophisticated network of ductless glands that release chemical messengers, known as hormones, directly into the bloodstream. These hormones regulate vital body functions, including metabolism, temperature, and growth, by interacting with specific receptor sites on or within target cells. One of the most critical regulatory systems in the body is the thyroid axis, which maintains metabolic homeostasis through a precise communication loop between the brain and the thyroid gland.
The Hypothalamic-Pituitary-Thyroid Axis
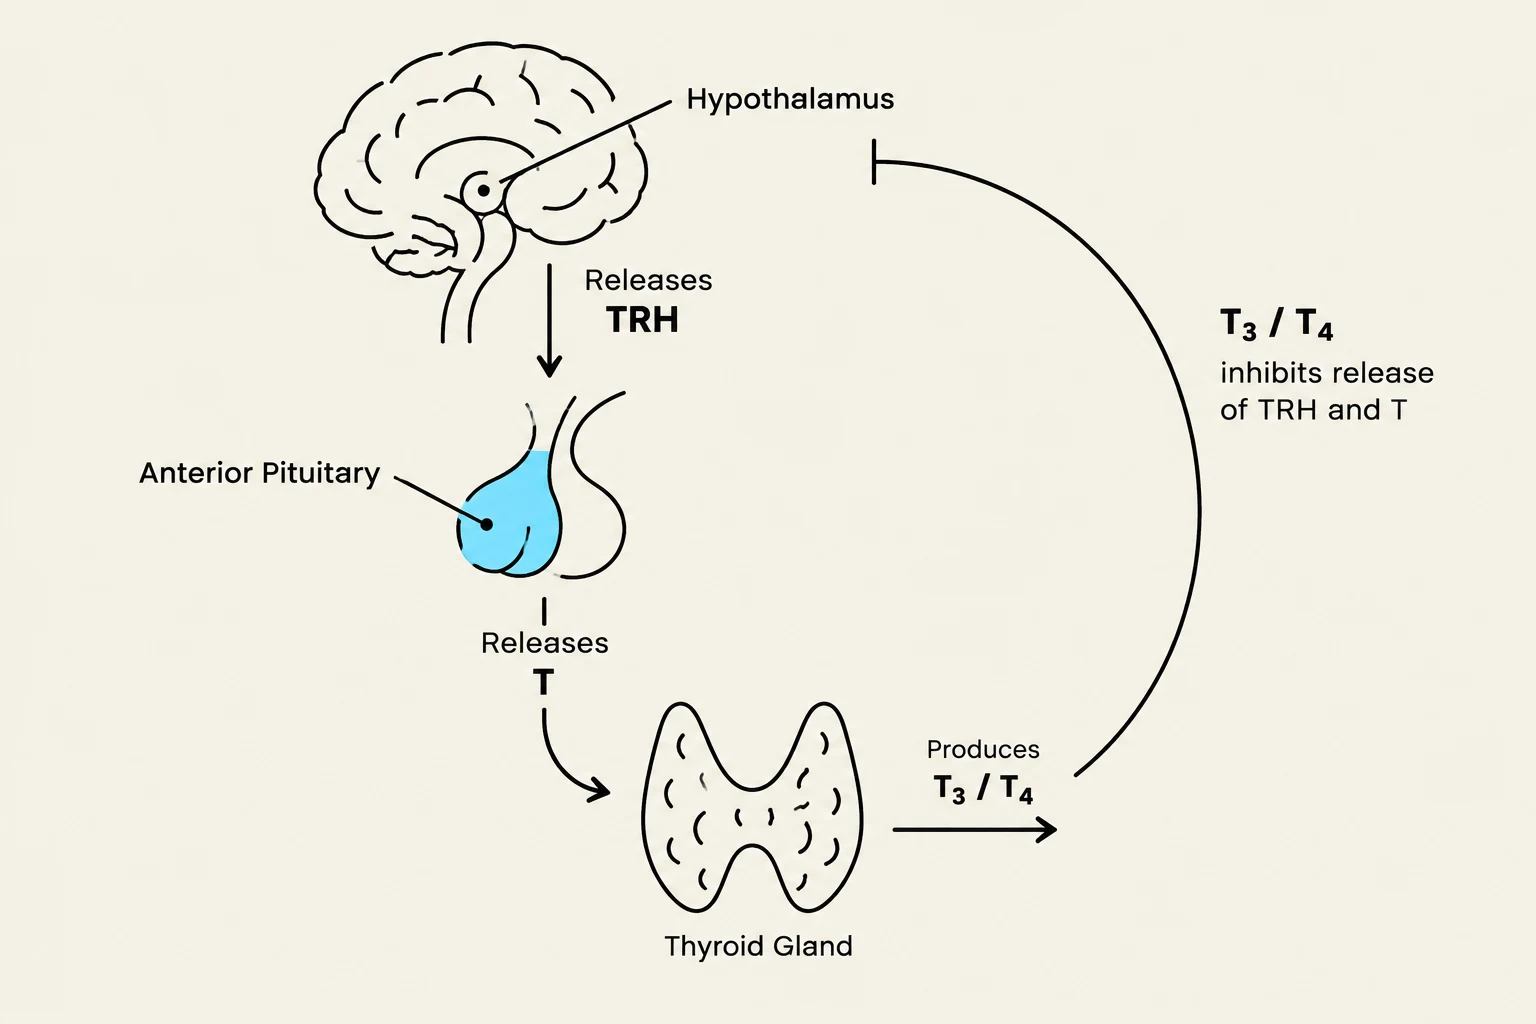
Thyroid hormone production is not autonomous; it is governed by a negative feedback loop involving the hypothalamus, the anterior pituitary, and the thyroid gland.
The Hypothalamus: Acts as the sensor. When it detects low levels of thyroid hormone, it secretes Thyrotropin-Releasing Hormone (TRH).
The Anterior Pituitary: Responds to TRH by releasing Thyroid-Stimulating Hormone (TSH).
The Thyroid Gland: Stimulated by TSH, the thyroid produces and releases two primary hormones: Triiodothyronine (T3) and Tetraiodothyronine (T4).
As T3 and T4 levels rise in the blood, they signal the hypothalamus and pituitary to decrease the production of TRH and TSH, effectively "shutting off" the stimulus to prevent hormone excess.
This diagram illustrates the negative feedback loop of thyroid hormone regulation, involving the hypothalamus, anterior pituitary, and thyroid gland.
Hypothyroidism: Underactive Thyroid
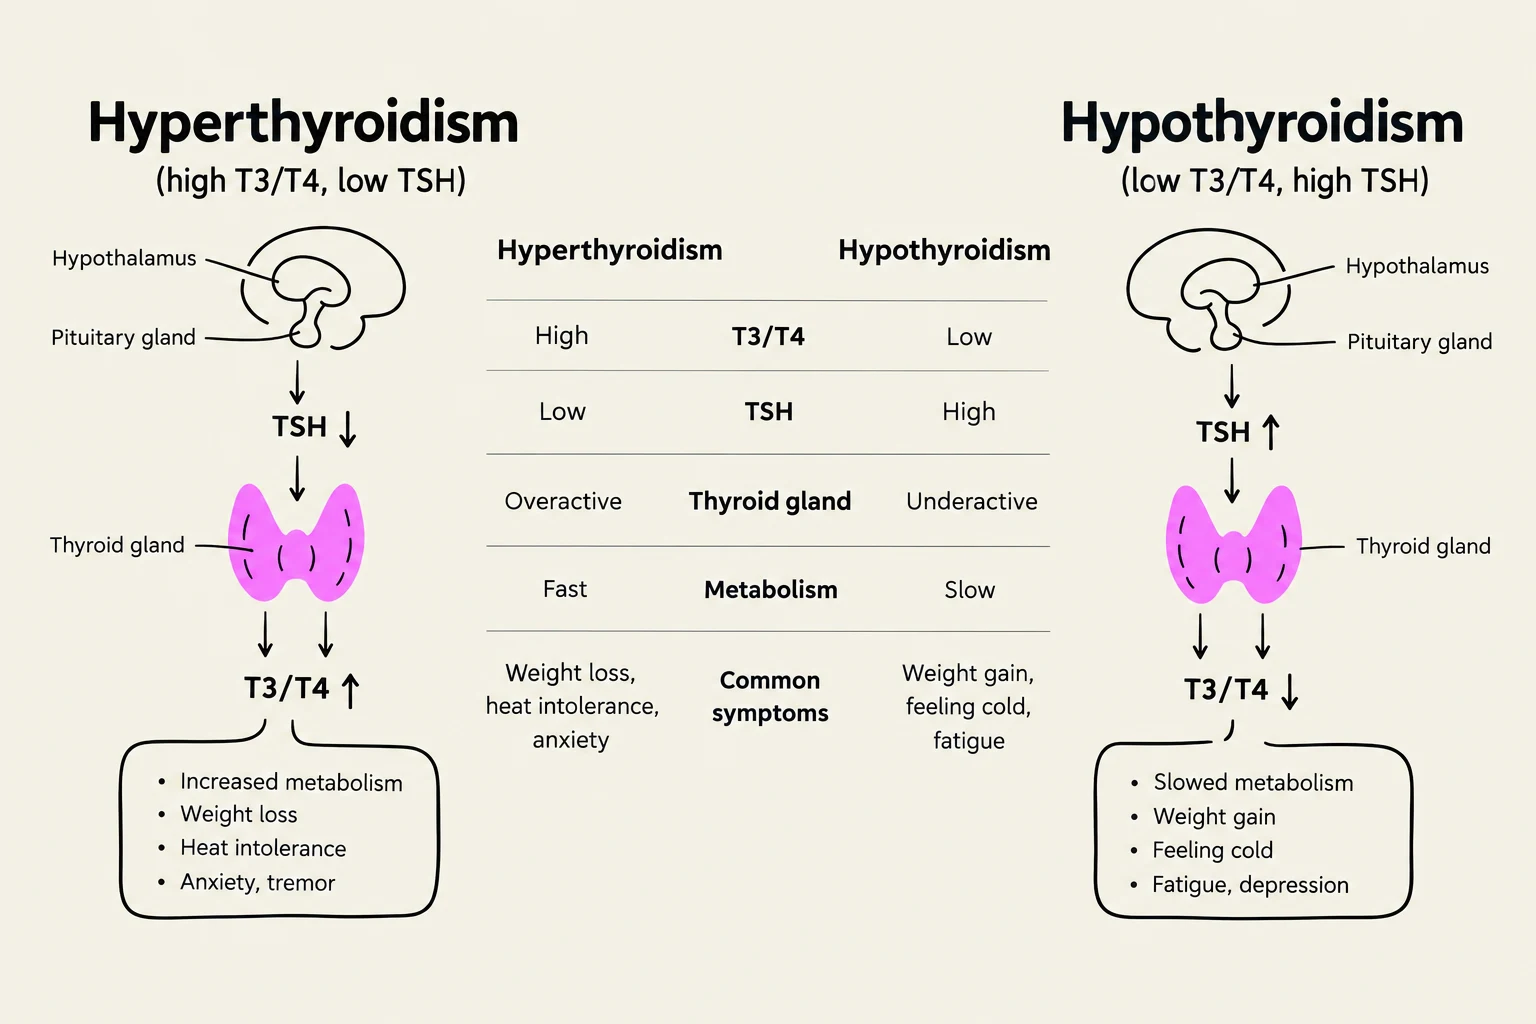
Hypothyroidism occurs when the thyroid gland fails to produce sufficient hormones. This can result from an absolute absence of the gland, iodine deficiency, autoimmune disorders, tumors, or issues within the hypothalamus itself. Because thyroid hormones influence almost every cell in the body, a deficit leads to a generalized "slowing down" of physiological processes.
Clinical Manifestations:
Depressed Central Nervous System (CNS)
Decreased metabolic rate
Slowed cardiovascular function (bradycardia)
Pharmacological Management of Hypothyroidism
The primary goal of treatment is replacement therapy to restore normal metabolic function.
Levothyroxine (Synthroid): This is the synthetic form of T4 and is the drug of choice for long-term replacement, especially in children.
Administration: It must be taken in the morning on an empty stomach.
Onset: It may take 1–3 weeks to feel effects, but it typically takes 6–8 weeks to reach full therapeutic levels.
Liothyronine (Cytomel): A synthetic version of T3. Because T3 is more potent and acts faster, this medication should be avoided in patients with cardiac or anxiety problems.
Liotrix (Thyrolar): A synthetic combination of T4 and T3 in a standard 4:1 ratio. Like Liothyronine, it is generally avoided in patients with cardiac dysfunction.
Thyroid Desiccated (Armour Thyroid): A preparation derived from dried animal thyroid glands containing both T3 and T4. Note that its effects can be unpredictable.
Clinical Alert: Drug-Drug Interactions
Levothyroxine is highly protein-bound. Be cautious of the following:
Cholestyramine: Decreases the absorption of thyroid hormones.
Oral Anticoagulants: May have their effects increased.
Antidiabetics: May have their effects decreased.
Hyperthyroidism: Overactive Thyroid
Hyperthyroidism, such as Graves’ disease, involves the excessive production and release of thyroid hormones into the circulation. This creates a "stimulated" state where the body's metabolic processes are running too fast.
Clinical Manifestations:
Tachycardia (rapid heart rate) and palpitations
Weight loss despite increased appetite
Heat intolerance and increased body temperature
Hypertension and flushing
Goiter (enlarged thyroid gland)
Antithyroid Agents and Treatments
To manage hyperthyroidism, clinicians use drugs to block hormone production or physical interventions to reduce gland activity.
Thioamides (Propylthiouracil and Methimazole): These drugs prevent the formation of thyroid hormones within the cells and partially inhibit the conversion of T4 to the more active T3.
Iodine Solutions (Potassium Iodide): When administered in high doses, these can block thyroid function.
Radioactive Iodine (I131): This treatment works by destroying thyroid cells. Because the cells are destroyed, patients will require lifelong thyroid hormone replacement therapy.
This diagram illustrates the differences between hyperthyroidism and hypothyroidism, detailing hormone levels, thyroid gland activity, metabolism, and common symptoms.
Infiltrative Ophthalmopathy
Some patients with hyperthyroidism develop exophthalmos (bulging eyes), an autoimmune-mediated inflammatory process of the orbital tissues.
Teprotumumab (Tepezza): An IGF-1 receptor inhibitor used to treat this condition.
Side Effects: Patients should be monitored for hyperglycemia, hearing loss, alopecia (hair loss), and muscle spasms.
Clinical Monitoring and Nursing Considerations
Effective management of thyroid dysfunction requires vigilant monitoring of both laboratory values and physical symptoms.
Laboratory Monitoring:
Regularly assess serum levels of T3, T4, and TSH to ensure the patient is within the therapeutic range.
Physical Assessment:
Vital Signs: Monitor heart rate (for tachycardia or arrhythmias), temperature, and blood pressure.
Weight: Monitor for unexpected weight loss (hyperthyroidism) or weight gain (hypothyroidism).
Medication Management:
Tachycardia: Propranolol may be prescribed to manage a rapid heart rate in hyperthyroid patients.
Adverse Effects: When using Thioamides, monitor for agranulocytosis (a dangerous drop in white blood cell count). When using replacement therapy, monitor for signs of over-replacement, such as arrhythmias and hypertension.
Student Exam Tip: The "Speed" of Hormones
Remember that thyroid hormones influence the function of every cell in the body. When assessing a patient on thyroid medication, always look at the "whole picture"—not just the thyroid, but the heart rate, temperature, and mental status.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.