Understanding the Motor System: Lower Motor Neurons and Muscle Synergies
This content explains the role of lower motor neurons as the final common pathway in motor control, detailing their structure, function, and the signs of LMN lesions. It also explores upper motor neurons, descending pathways, and the coordination of movement through muscle synergies and spinal reflexes.
The human motor system is a sophisticated hierarchy designed to transform a mental intention into fluid, purposeful movement. This process requires seamless communication between the high-level decision-making centers of the brain and the individual muscle fibers that execute the work. To understand how we move, we must distinguish between the "commanders" (Upper Motor Neurons) and the "executors" (Lower Motor Neurons), while also exploring the complex interneuronal networks that coordinate these components into functional muscle synergies.
The Lower Motor Neuron: The Final Common Pathway
At the very bottom of the motor hierarchy lies the lower motor neuron (LMN). Specifically, the alpha motor neuron serves as the final common pathway for all motor control. These neurons have their cell bodies located in the ventral horn (specifically lamina 9) of the spinal cord.
The LMN is the terminal link in the chain; its axon extends out of the central nervous system to form a motor unit. A motor unit consists of a single alpha motor neuron and all the specific muscle fibers it innervates. The size of these units—known as the innervation ratio—varies based on the muscle's function. For example, muscles requiring fine, dexterous control (like those in the hand) have small motor units with fewer fibers per neuron, whereas large muscles used for power (like those in the leg) have much larger motor units.
Diagram illustrating a single alpha motor neuron branching to innervate multiple muscle fibers, forming a motor unit.
Because the LMN is the last stop before the muscle, any injury to this pathway results in denervation—the muscle is no longer receiving signals to contract. This leads to a distinct clinical presentation known as LMN signs:
Muscle Weakness/Paralysis: An inability to generate force due to lost input.
Denervation Atrophy: Wasting and thinning of muscle tissue because the muscle lacks the trophic support of the neuron.
Hypotonia/Flaccidity: A significant decrease in muscle tone or "floppiness".
Hyporeflexia/Areflexia: Diminished or absent deep tendon reflexes because the reflex arc is broken at the efferent limb.
Exam Tip: If a clinical case describes a patient with "flaccid paralysis" and "muscle wasting" on the ipsilateral (same) side of a lesion, think Lower Motor Neuron.
Upper Motor Neurons and Cortical Organization
While the LMN executes the movement, the Upper Motor Neurons (UMNs) initiate the motor plan. UMNs originate in the cerebral cortex or the brainstem and descend through the spinal cord to synapse with the LMNs. The system follows a hierarchical control structure where the cortex selects the goal, the basal ganglia and cerebellum refine the plan, and the LMNs produce the output.
The descending pathways are broadly categorized into two groups:
1. Pyramidal Pathways (Corticospinal)
These pathways are responsible for voluntary, highly skilled movements.
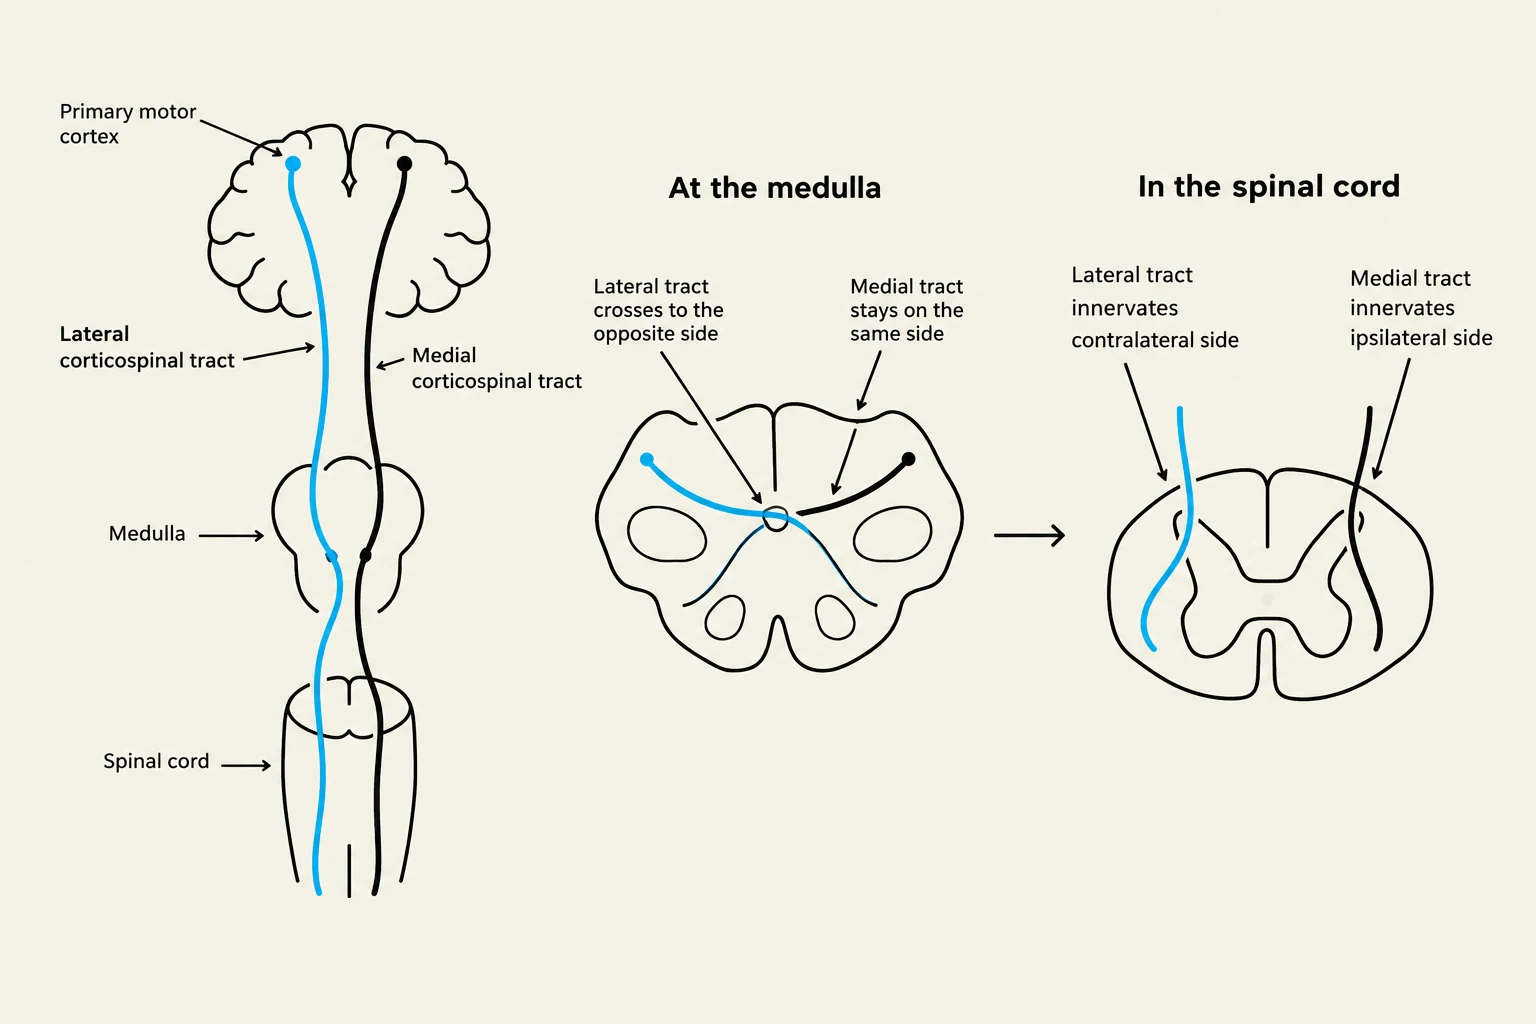
Lateral Corticospinal Tract: Originates in the motor cortex and decussates (crosses) in the medulla. It synapses laterally in the spinal cord to control distal muscles (arms and legs), allowing for "fractionated" movements—the ability to move individual muscles independently.
Medial (Anterior) Corticospinal Tract: Controls axial and proximal muscles (trunk, neck, shoulders, and hips) to maintain posture. Unlike the lateral tract, these fibers often project bilaterally.
Corticobulbar Tract: Connects the motor cortex to the brainstem to control the muscles of the face and neck.
2. Extrapyramidal Pathways
These pathways primarily manage unconscious, automatic functions like posture and gross movement.
Vestibulospinal Tracts: The lateral tract (from the medulla) maintains center of gravity, while the medial tract orients the head and neck.
Reticulospinal Tract: Originates in the pons and is involved in postural, antigravity, and gross limb movements. Notably, it is the only medial tract that can influence distal extremity muscles, often contributing to abnormal movement patterns (synergies) in UMN lesions.
Modulatory Pathways: The Ceruleospinal and Raphespinal pathways enhance the activity of spinal interneurons and motor neurons, often modulated by emotional or limbic activity.
Diagram illustrating the pathways of the lateral and medial corticospinal tracts from the primary motor cortex through the medulla and into the spinal cord, showing decussation at the medulla and innervation patterns in the spinal cord.
Muscle Synergies and Interneuron Networks
Movement is rarely the result of a single muscle acting in isolation. Instead, the nervous system utilizes muscle synergies—groups of muscles activated together to produce fluid, functional movements. This coordination is managed by interneurons within the spinal cord that create complex inhibitory and excitatory circuits.
Inhibitory Circuits
To prevent muscles from fighting each other, the spinal cord employs two primary inhibitory mechanisms:
Reciprocal Inhibition: When an agonist muscle (the one contracting) is activated, an inhibitory interneuron is triggered to prevent the antagonist muscle from contracting. This is mediated by Ia afferents from muscle spindles.
Autogenic Inhibition (Recurrent Inhibition): This protects the muscle from excessive tension. When a muscle is under extreme load, Type Ib afferents from the Golgi Tendon Organ (GTO) signal an inhibitory interneuron to inhibit the alpha motor neuron of that same muscle, forcing it to relax.
Central Pattern Generators (CPGs)
For rhythmic, repetitive tasks like walking or breathing, the system uses Central Pattern Generators. These are neural networks in the spinal cord and brainstem that can produce rhythmic motor outputs even without continuous input from the cortex.
Spinal Reflexes: Rapid Protective Responses
Reflexes are involuntary, rapid responses to stimuli that occur through spinal circuitry.
Stretch Reflex (Deep Tendon Reflex): This is a monosynaptic reflex. When a muscle is stretched (e.g., tapping the patellar tendon), the muscle spindle sends a signal via Ia afferents directly to the alpha motor neuron, causing the muscle to contract. It also includes a disynaptic component of reciprocal inhibition to relax the antagonist.
Flexion Withdrawal Reflex: A protective response to a noxious (painful) stimulus. The signal travels via the spinothalamic tract, activating interneurons that excite the flexor muscles of the injured limb to pull it away.
Crossed Extensor Reflex: To prevent you from falling when you withdraw a limb, this reflex triggers extension in the contralateral (opposite) limb. Interneurons cross the midline of the spinal cord to activate the extensors of the opposite leg, providing a "support" stance.
Diagram illustrating the withdrawal reflex and the crossed extensor reflex in response to a painful stimulus.
Clinical Correlation: A patient with a C5 ventral nerve root transection (an LMN injury) would demonstrate hyporeflexia at the biceps tendon because the efferent limb of the reflex arc is physically severed.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.