Understanding SOAP Charting for Clinical Documentation
A comprehensive guide to SOAP charting, a standard framework in healthcare for documenting patient encounters. Learn the Subjective, Objective, Assessment, and Plan components with practical examples.
In the fast-paced environment of clinical practice, clear and concise communication is the lifeline of patient safety. Whether you are a medical student on your first rotation or a seasoned practitioner, the ability to document a patient encounter accurately is a core competency. The most widely recognized framework for this task is SOAP charting.
SOAP is an acronym for Subjective, Objective, Assessment, and Plan. This structured method ensures that healthcare providers capture a holistic view of the patient while maintaining a logical flow that allows other clinicians to follow the reasoning behind a diagnosis and treatment strategy.
The Subjective Component: The Patient's Story
The "S" in SOAP stands for Subjective. This section is dedicated to the patient's perspective of their health status. It is composed of information that cannot be independently measured or verified by the clinician, but rather must be reported by the patient, a family member, or a caregiver.
When documenting the subjective portion, you should focus on the Chief Complaint (CC) and the History of Present Illness (HPI). This includes:
Symptoms: Pain levels, nausea, dizziness, or fatigue.
Onset and Duration: When the issue started and how long it lasts.
Character and Severity: Is the pain sharp or dull? Is it a 3/10 or a 9/10?
Modifying Factors: What makes the symptom better or worse?
Exam Tip: Avoid using "objective" language in the subjective section. For example, do not write "Patient is coughing." Instead, write "Patient reports a persistent, dry cough for three days." The former is an observation; the latter is a report of a symptom.
The Objective Component: The Clinician's Findings
The "O" stands for Objective. This section is the bedrock of clinical evidence. Unlike the subjective section, the objective portion contains data that is observable, measurable, and reproducible by another clinician.
Physical Examination Findings: What you see (inspection), feel (palpation), hear (auscultation), and tap (percussion).
Laboratory and Diagnostic Results: Results from blood work, X-rays, EKGs, or urinalysis that are already available at the time of the encounter.
It is vital to remain neutral here. Instead of writing "Patient looks sick," write "Patient appears pale and diaphoretic".
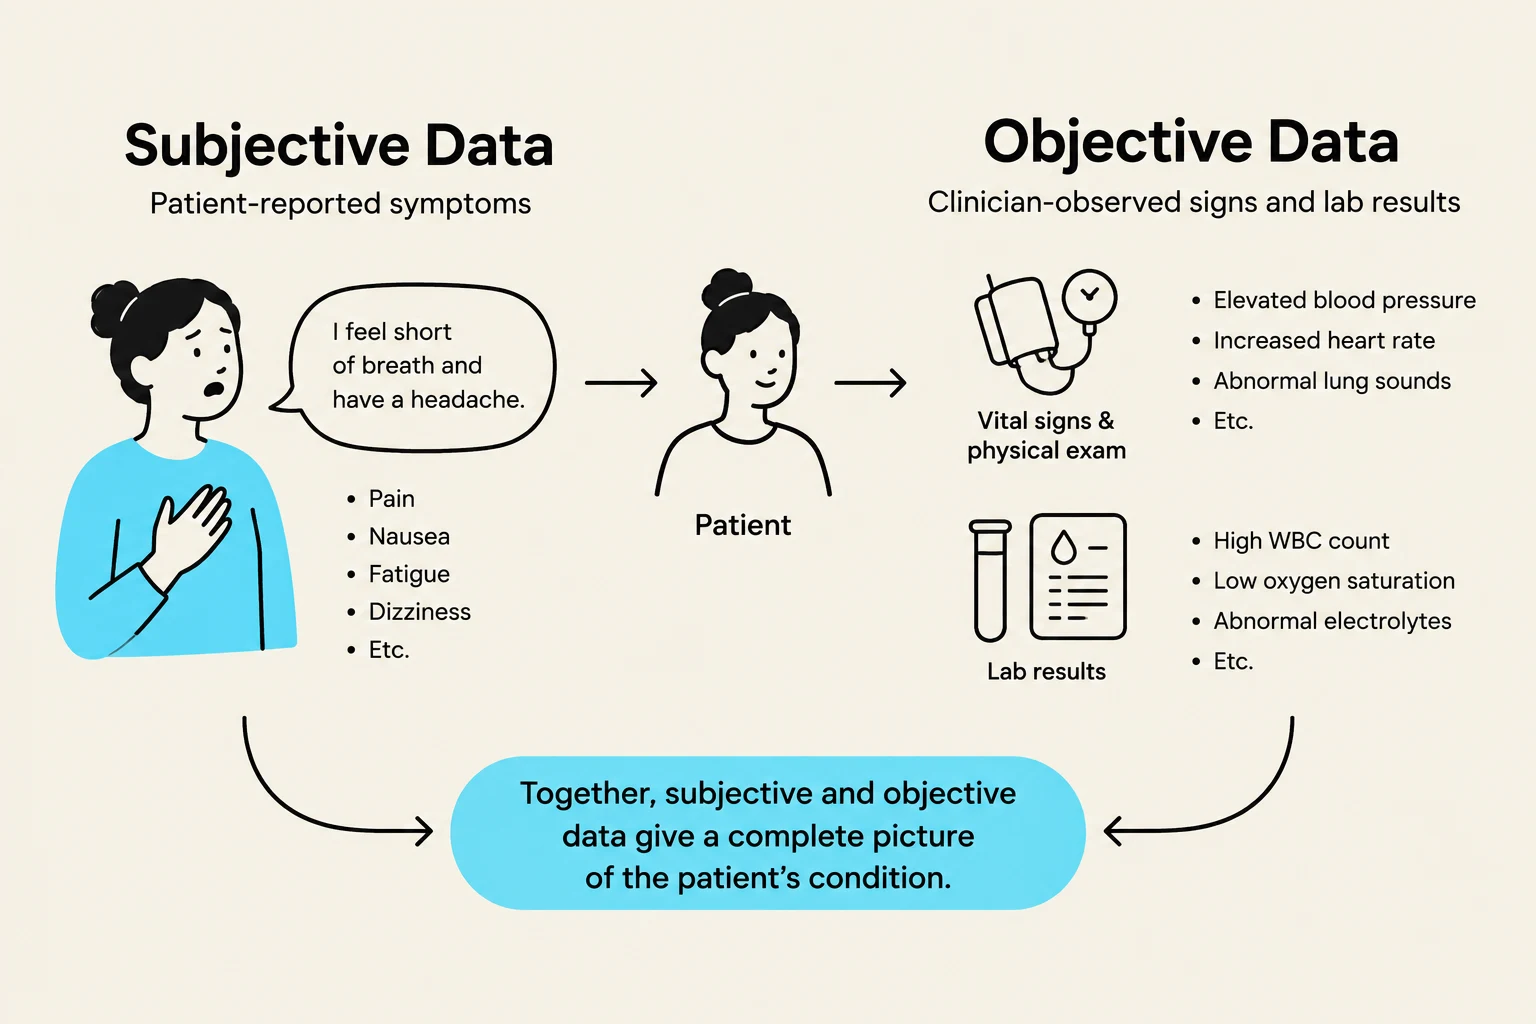
This diagram illustrates the distinction between subjective data (patient-reported symptoms) and objective data (clinician-observed signs and lab results) in assessing a patient's condition.
Assessment: The Clinical Synthesis
The "A" stands for Assessment. This is where the clinician synthesizes the Subjective and Objective data to form a clinical judgment. The assessment is not just a list of diagnoses; it is a professional interpretation of the patient's current state.
In this section, you may include:
Differential Diagnoses: A list of potential conditions that could explain the patient's presentation, ranked from most likely to least likely.
Final Diagnosis: If the cause is certain, state the definitive diagnosis.
Status Updates: For chronic conditions, note whether the condition is "improving," "stable," or "exacerbated".
The assessment bridges the gap between "what happened" (S and O) and "what we are going to do" (P).
The Plan: The Path Forward
The "P" stands for Plan. This section outlines the specific actions that will be taken to address the issues identified in the assessment. A well-structured plan should be actionable and clear to all members of the healthcare team.
A comprehensive plan often follows these categories:
Diagnostic Plan: Orders for further testing (e.g., "Order CBC and BMP," "Schedule chest X-ray").
Patient Education: Instructions given to the patient regarding their condition or treatment.
Follow-up: When the patient should return or when they should seek emergency care.
The SOAP note is a method of documentation used in healthcare to record patient information. It stands for Subjective, Objective, Assessment, and Plan.
Worked Example: Putting it All Together
To solidify your understanding, let's look at a brief example of a patient presenting with acute respiratory symptoms.
Subjective:
Patient reports a "sharp, stabbing" pain in the right chest when breathing deeply for the last 24 hours. Also reports a dry cough and mild fever. Denies leg swelling or recent travel.
Objective:
Temp: 38.2∘C (100.8∘F). HR: 105 bpm. RR: 22 breaths/min. SpO2: $93%$ on room air. Lung auscultation reveals decreased breath sounds in the right lower lobe. No calf tenderness noted on palpation.
Assessment:
Pleuritic chest pain, likely secondary to pneumonia.
Fever, etiology uncertain but consistent with infection.
Differential includes pulmonary embolism (less likely given lack of leg swelling) and pneumothorax.
Plan:
Order Chest X-ray (PA and Lateral).
Order CBC and inflammatory markers.
Start supplemental oxygen to maintain SpO2 >94%.
Follow up in 48 hours with lab results.
Final Thought: The goal of SOAP charting is not just to record data, but to tell the story of a patient's clinical journey in a way that is logical, evidence-based, and easy for any other clinician to pick up and understand immediately.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.