Explores the pathophysiology of silent myocardial infarctions (MIs), focusing on how conditions like diabetes mellitus and autonomic neuropathy can lead to a lack of typical chest pain symptoms during a cardiac event. Discusses the underlying mechanisms of atherosclerosis, ischemia, and impaired nerve signaling.
In clinical practice, the "classic" presentation of a myocardial infarction (MI)—crushing substernal chest pain, diaphoresis, and radiation to the left arm—is often the gold standard for diagnosis. However, a significant subset of patients experiences what is known as a silent myocardial infarction (MI). In these cases, the patient undergoes myocardial necrosis without the typical subjective experience of pain. Understanding why certain populations are predisposed to these "silent" events is critical for advanced pathophysiology students and clinicians, as these patients are at a much higher risk for sudden cardiac death and undetected progressive heart disease.
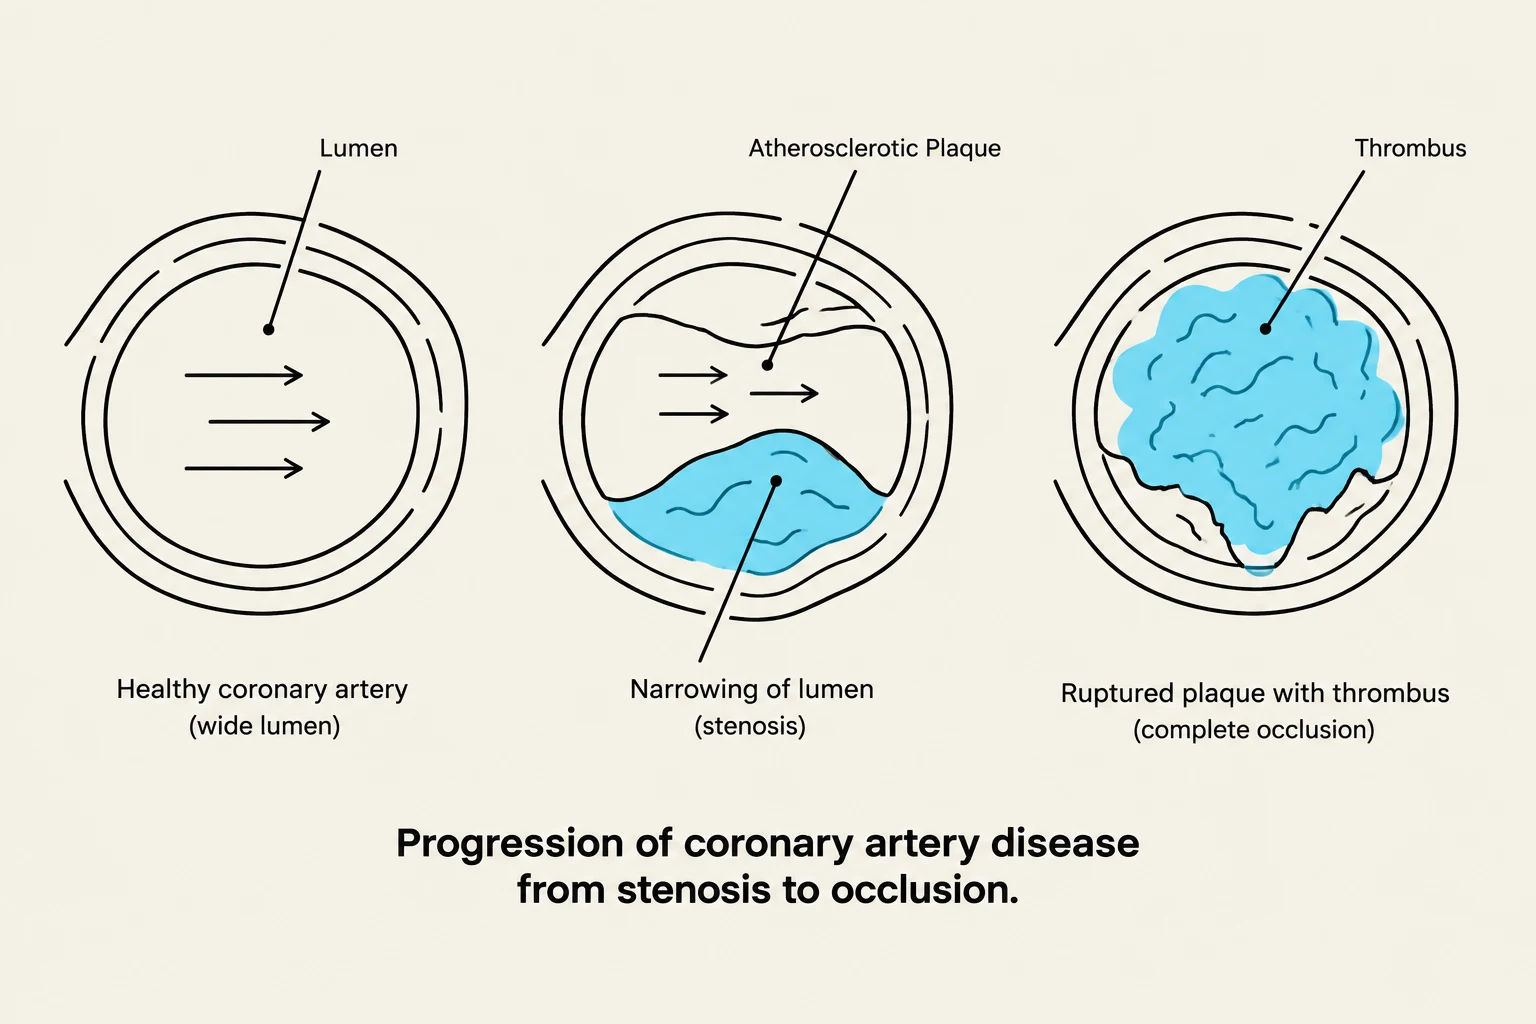
Progression of coronary artery disease from stenosis to occlusion.
The Foundation: Atherosclerosis and Ischemia
To understand a silent MI, one must first understand the progression of coronary artery disease. The underlying driver for most ischemic events is atherosclerosis, the buildup of fatty plaques within the arterial walls. This process is often accelerated by systemic factors such as hypertension, which increases mechanical stress on the endothelium, and diabetes mellitus, which promotes inflammatory changes and vessel wall damage.
As atherosclerosis progresses, the lumen of the coronary artery narrows. This leads to cardiac ischemia, a state where the oxygen demand of the myocardium exceeds the oxygen supply provided by the blood flow. When this imbalance is predictable and occurs during physical exertion (such as walking), it is often classified as stable angina. However, if a plaque ruptures or a thrombus forms, complete occlusion occurs, leading to an infarction. In a typical patient, this occlusion triggers nociceptors that send pain signals to the brain; in a silent MI, this communication pathway is compromised.
The Role of Diabetes Mellitus
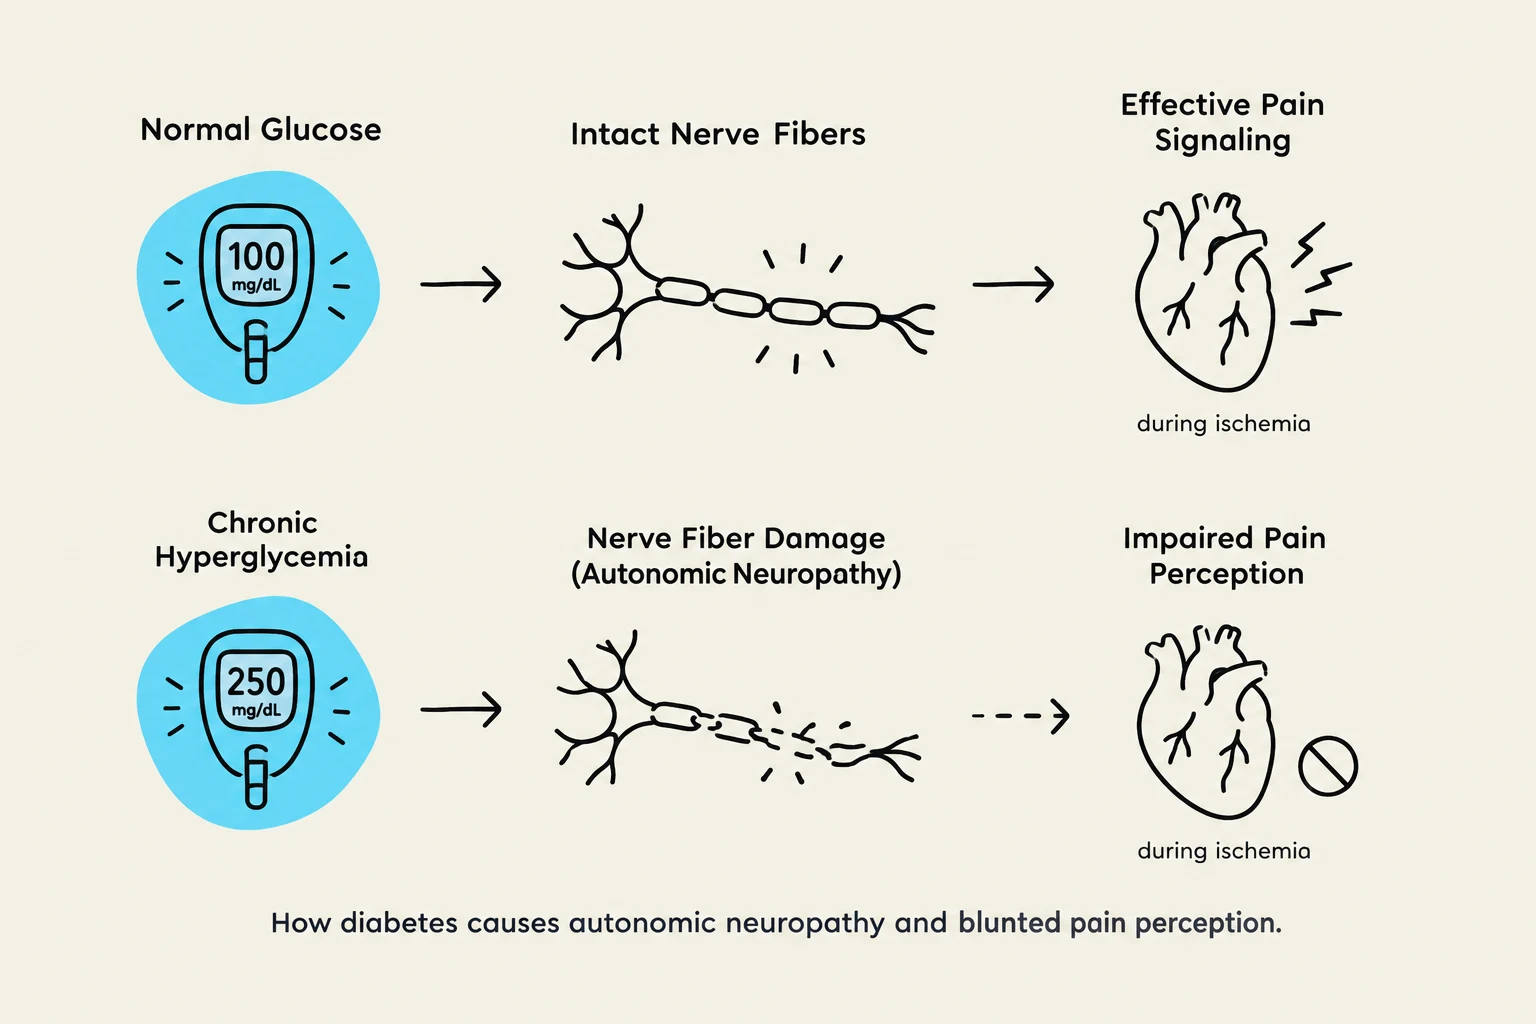
This diagram illustrates how chronic hyperglycemia, a condition associated with diabetes, can lead to autonomic neuropathy and impaired pain perception. In normal glucose levels, nerve fibers are intact, allowing for effective pain signaling during ischemia. However, with chronic hyperglycemia, nerve fiber damage occurs, resulting in blunted pain perception during ischemia.
Diabetes mellitus is perhaps the most significant risk factor for the "silencing" of an MI. While diabetes contributes to cardiovascular risk through accelerated atherosclerosis, its most unique contribution to silent ischemia is its effect on the nervous system.
Chronic fluctuations in blood glucose levels lead to metabolic derangements that cause structural and functional damage to various nerve fibers. This damage manifests as autonomic neuropathy. The autonomic nervous system is responsible for regulating involuntary bodily functions, including heart rate, blood pressure, and the perception of pain. When this system is damaged by long-standing diabetes, the body's ability to signal distress during an ischemic event is severely diminished.
Pathophysiology of Autonomic Neuropathy
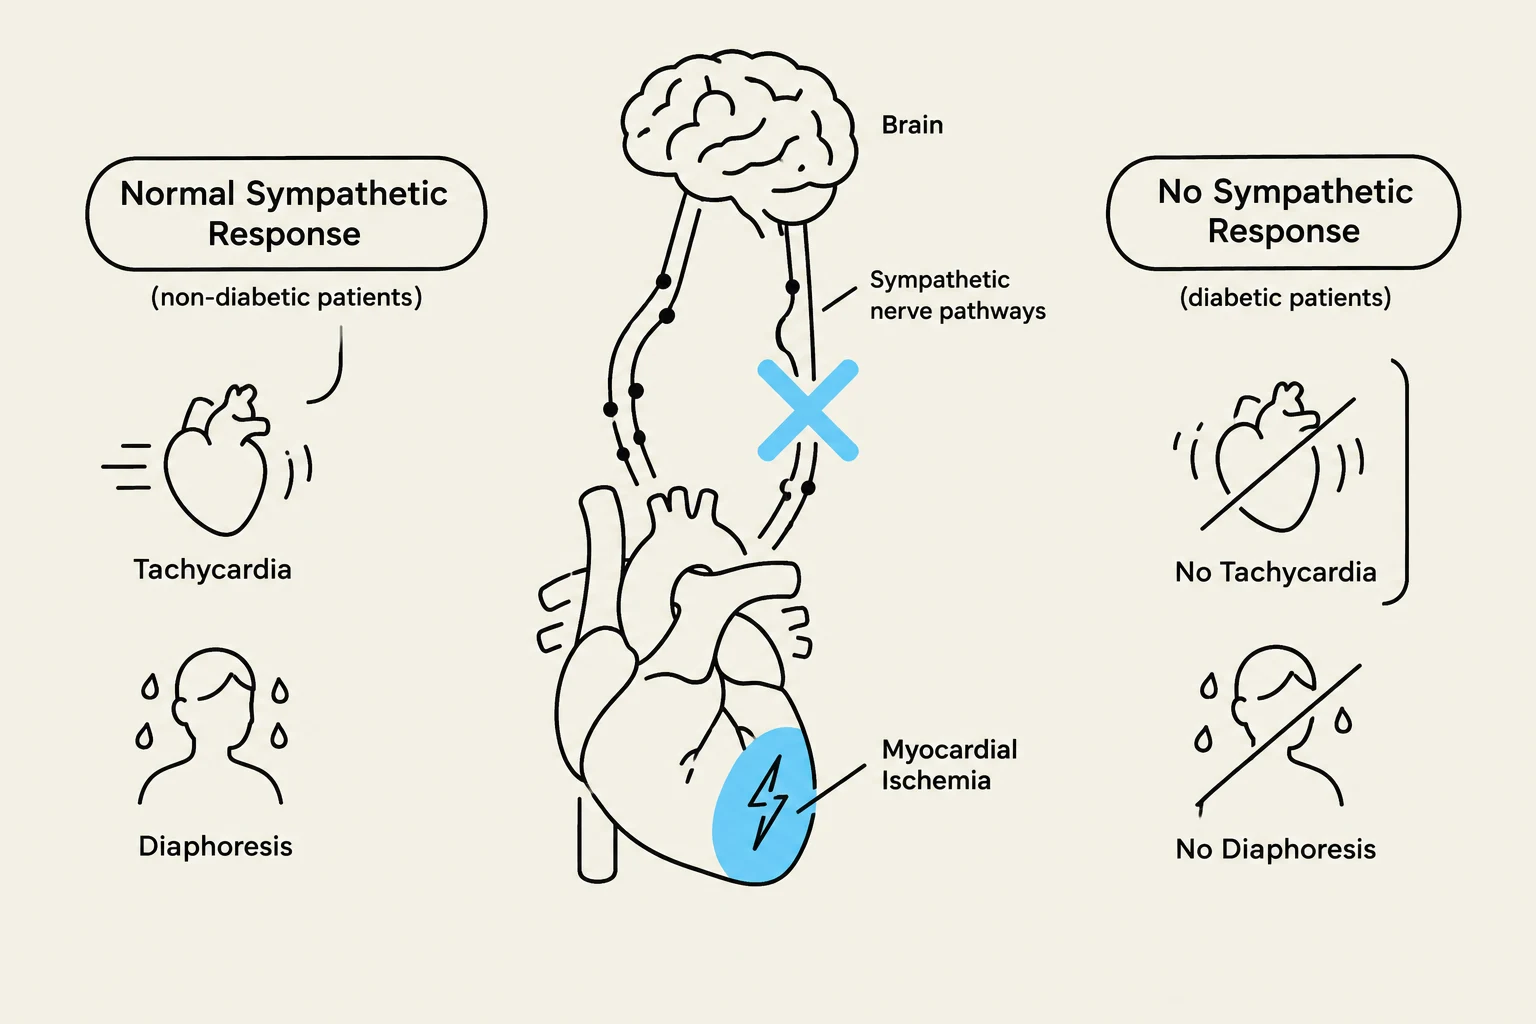
This diagram illustrates the difference in sympathetic nervous system response between non-diabetic and diabetic patients, highlighting tachycardia, diaphoresis, and myocardial ischemia.
Autonomic neuropathy affects the sympathetic and parasympathetic pathways. In the context of a myocardial infarction, the sympathetic nervous system is typically responsible for the "fight or flight" response, which includes the perception of acute pain and the physiological symptoms (like tachycardia) that alert a patient to a crisis.
When autonomic neuropathy is present:
Blunted Pain Perception: The sensory pathways that normally translate myocardial ischemia into the sensation of chest pain are impaired.
Loss of Warning Signs: The patient may not experience the typical sympathetic surge (increased heart rate or sweating) that often accompanies cardiac distress.
Consequently, a patient with diabetes may experience a full-scale myocardial infarction—complete with tissue death—without ever realizing they are in danger.
💡 Exam Tip: Identifying High-Risk Profiles
When evaluating multiple-choice questions regarding silent MIs, look for the intersection of Diabetes Mellitus and Autonomic Neuropathy. While hypertension increases the risk of atherosclerosis and stroke, it does not inherently cause the neurological "blunting" required for a silent MI. An obese male with diabetes is a much higher-risk candidate for a silent event than a middle-aged female with hypertension or a young smoker.
Clinical Correlation: Stable Angina vs. Acute Events
It is important for clinicians to distinguish between stable patterns and evolving threats. A patient with a history of stable angina may report that their attacks are becoming more frequent or occurring with less exertion (e.g., while walking). This change in pattern—known as unstable angina—is a red flag that the underlying atherosclerosis is progressing or that a plaque is becoming unstable, potentially leading to a full myocardial infarction.
Condition
Primary Mechanism
Typical Symptom
Stable Angina
Predictable ischemia due to fixed stenosis
Chest pain during exertion
Hypertension
Increased vascular workload/stress
Often asymptomatic (the "silent killer")
Silent MI
Myocardial necrosis with impaired nerve signaling
Asymptomatic (due to neuropathy)
Summary for Advanced Practice
The pathophysiology of a silent MI is a complex interplay between vascular disease and neurological dysfunction. While atherosclerosis provides the mechanism for the occlusion, autonomic neuropathy—driven by long-standing diabetes mellitus—provides the mechanism for the lack of symptoms. Clinicians must maintain a high index of suspicion for myocardial ischemia in diabetic patients, even in the absence of classic chest pain, as their neurological "alarm system" may be fundamentally broken.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.