Understanding Renal Health: Diagnostics, Nursing Care, and Replacement Therapies
This guide explains the diagnostic evaluation of kidney function, essential nursing priorities for patients with renal disorders, and the various types of renal replacement therapies including hemodialysis, peritoneal dialysis, and CRRT.
The kidneys serve as the body's primary filtration system, maintaining fluid, electrolyte, and acid-base balance while excreting metabolic waste. When renal function is compromised—whether through acute injury or chronic progression—the body experiences a buildup of nitrogenous wastes (azotemia) and dangerous electrolyte shifts. Understanding the diagnostic pathway, nursing priorities, and the various modalities of renal replacement therapy is essential for managing patients with renal and urinary disorders.
Diagnostic Evaluation
To accurately assess kidney health, clinicians utilize a combination of laboratory tests, imaging, and invasive procedures to determine the degree of impairment and the underlying cause.
Laboratory Testing
Blood and urine analysis provide the most immediate data regarding renal filtration capacity:
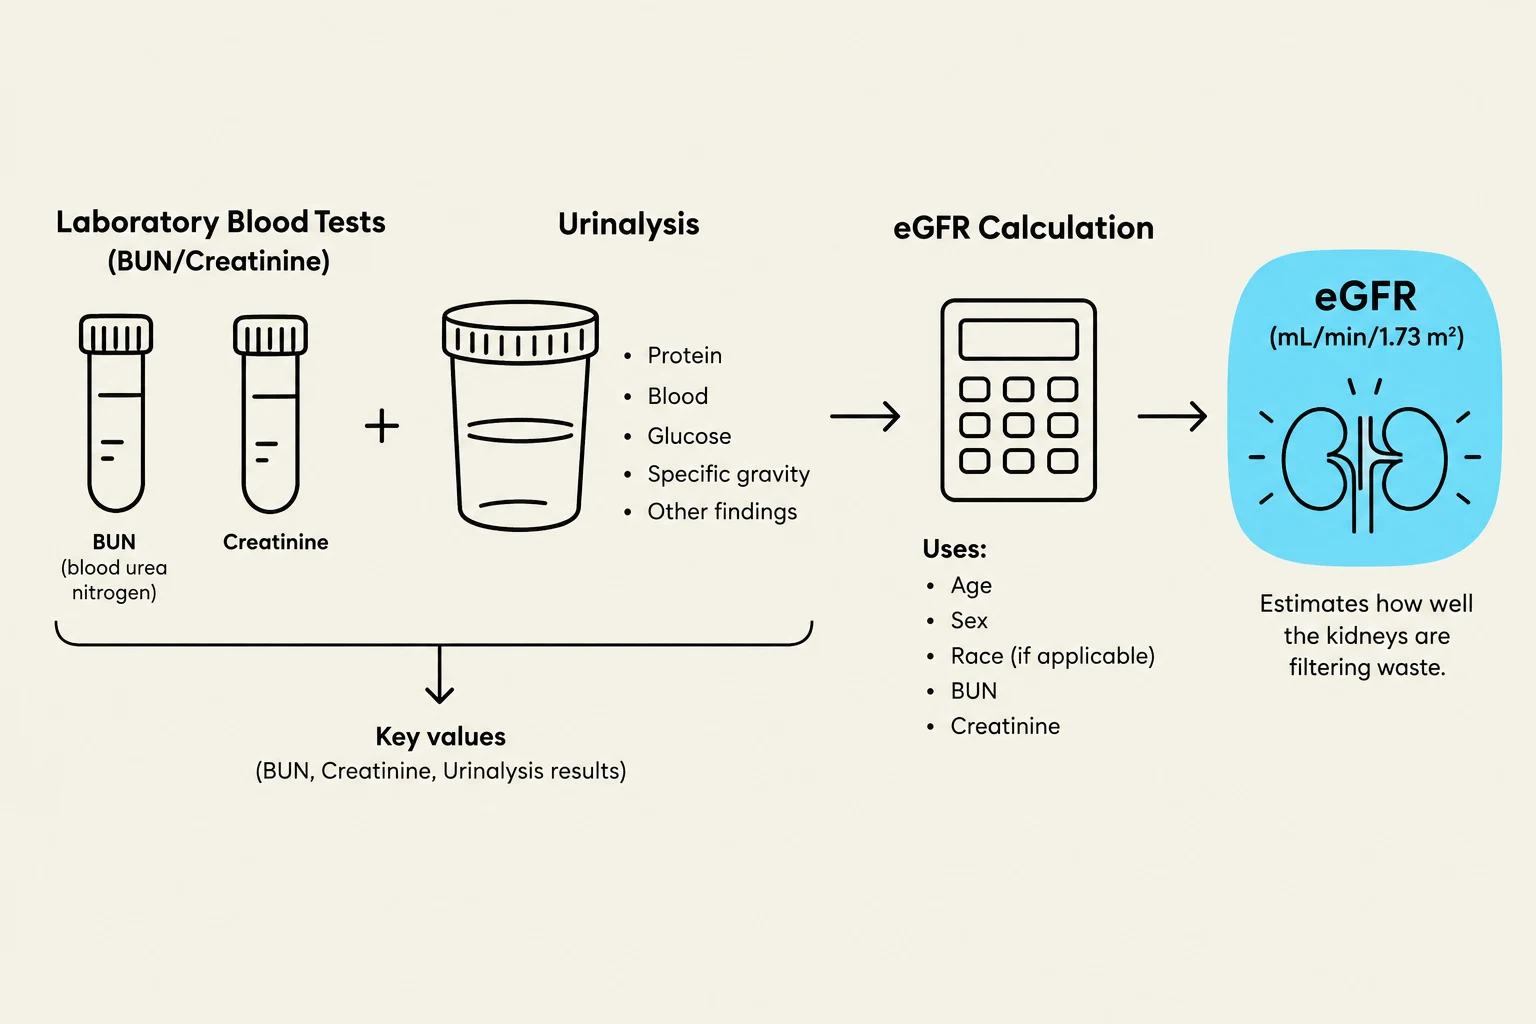
Laboratory Blood Tests: Monitoring BUN (Blood Urea Nitrogen) and Creatinine is fundamental; elevated levels indicate impaired filtration. Other tests include Complete Blood Count (CBC), serum albumin, and C3 complement tests.
Urinalysis: This is used to detect the presence of proteins (often seen in nephrotic syndrome) and blood (common in nephritic syndrome or kidney stones).
eGFR (estimated Glomerular Filtration Rate): This critical calculation is used for the staging of chronic kidney disease.
Imaging and Biopsy
When structural issues are suspected, imaging studies such as ultrasound or CT scans are employed. In certain cases, a kidney biopsy may be necessary to obtain tissue for definitive diagnosis.
This diagram illustrates the process of calculating estimated Glomerular Filtration Rate (eGFR) using laboratory blood tests (BUN and Creatinine) and urinalysis results. The eGFR is a measure of kidney function.
Nursing Priorities
Nursing care for renal patients focuses on preventing complications from fluid shifts and electrolyte imbalances.
Clinical Monitoring
Nurses must prioritize frequent vital sign monitoring, particularly blood pressure, as hypertension is both a cause and a symptom of renal disease. Because fluid overload can lead to pulmonary edema or heart failure, maintaining strict fluid balance through daily weights is a top priority.
Safety and Complications
Fall Precautions: Patients are at increased risk for falls due to potential fluid overload, dizziness, or neurological changes.
Infection Prevention: Patients with renal failure or those with vascular access are highly susceptible to infection.
Assessment: Nurses must monitor for mental status changes (indicating increased nitrogenous waste), numbness/tingling (electrolyte imbalance), and respiratory status.
Exam Tip: When a patient is experiencing fluid overload, the most reliable indicator of fluid status change is a sudden increase in daily weight, rather than just assessing for edema.
Medical and Nutritional Management
Management aims to control the underlying cause of renal dysfunction and mitigate the systemic effects of waste buildup.
Pharmacologic Management
Medications are used to manage the secondary effects of kidney failure:
Antihypertensives: To control high blood pressure.
Erythropoiesis-stimulating agents (ESAs): To treat anemia caused by decreased red cell production.
Phosphate and Potassium Binders: To prevent dangerous elevations in serum levels.
Diuretics: To manage fluid volume.
Nutritional Therapy
Dietary modification is a cornerstone of renal care. Patients must often adhere to restrictions of sodium, potassium, and phosphates. However, they must also ensure adequate intake of protein (depending on the stage of disease), calcium, Vitamin D, and iron to prevent malnutrition.
Renal Replacement Therapy (RRT)
When kidneys can no longer sustain life, RRT is required to perform the work of filtration.
Hemodialysis
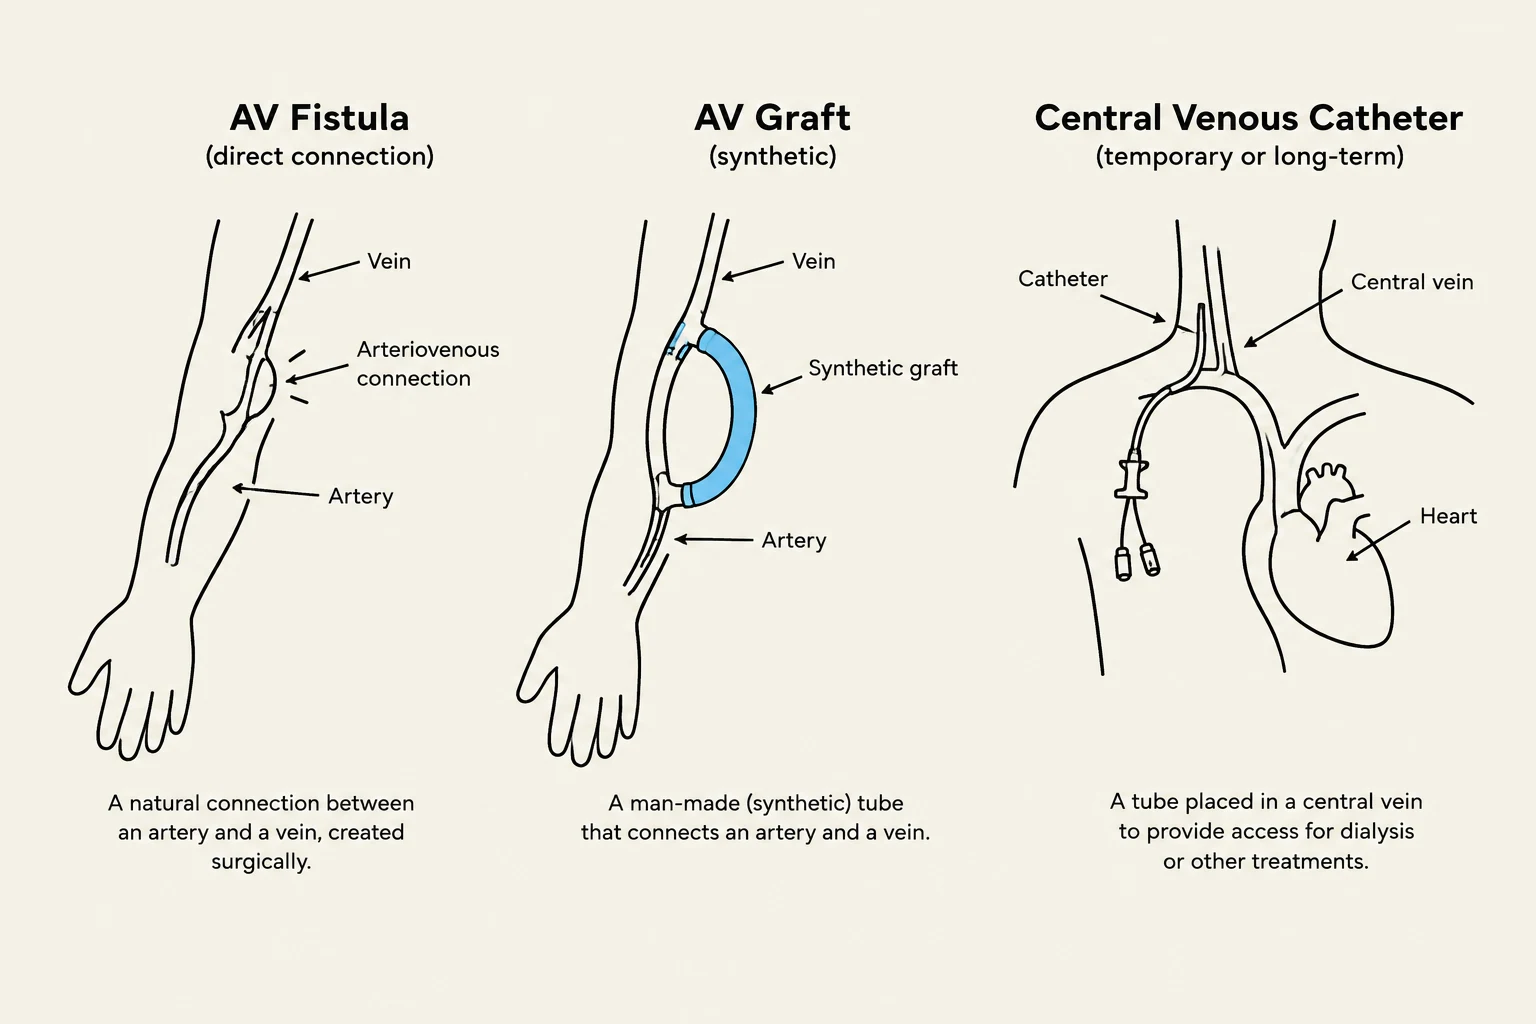
Hemodialysis is the most common method, typically performed three times weekly. It requires reliable vascular access:
Arteriovenous (AV) fistula: The preferred method due to a lower risk of infection.
Arteriovenous (AV) graft: A synthetic tube used when a fistula cannot be created.
Central Venous Catheter (CVC): Can be used immediately but carries a high risk of infection.
Common complications of hemodialysis include hypotension, muscle cramps, and disequilibrium syndrome, a neurological issue caused by rapid fluid and solute shifts.
Diagrams illustrating AV Fistula, AV Graft, and Central Venous Catheter procedures.
Peritoneal Dialysis
This method uses the patient's peritoneum as a filter to remove toxins and reestablish electrolyte balance. It offers greater independence and flexibility.
Types: Includes Continuous Ambulatory PD (CAPD) and Automated PD (APD).
Complications: The most significant risk is peritonitis (infection of the peritoneum) and catheter site infections.
Continuous Renal Replacement Therapy (CRRT)
CRRT is reserved for critically ill patients, such as those with Acute Kidney Injury (AKI), in an ICU setting. It provides a much slower, continuous removal of solutes and fluids to avoid the rapid shifts seen in standard dialysis. Common modalities include:
Continuous veno-venous hemodialysis (CVVHD)
Continuous veno-venous hemofiltration (CVVH)
Continuous veno-venous hemodiafiltration (CVVHDF)
Slow continuous ultrafiltration (SCUF)
Kidney Transplantation
Transplantation is the best long-term treatment for End-Stage Renal Disease (ESRD). It requires lifelong immunosuppressive therapy to prevent organ rejection.
Comparison of Hemodialysis, Peritoneal Dialysis, and Continuous Renal Replacement Therapy (CRRT) including patient acuity, method of filtration, and primary function.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.