Understanding NSAIDs and Corticosteroids: Mechanisms, Risks, and Nursing Care
This guide explains the distinct mechanisms of action, potential risks, and essential nursing assessments for Non-Steroidal Anti-Inflammatory Drugs (NSAIDs) and Corticosteroids. It covers gastrointestinal and renal function monitoring, the dangers of sudden corticosteroid cessation, and patient education on bleeding ri
In the management of inflammatory conditions—such as Rheumatoid Arthritis (RA), Lupus, or Multiple Sclerosis (MS)—pharmacological intervention often centers on two major classes of drugs: Non-Steroidal Anti-Inflammatory Drugs (NSAIDs) and Corticosteroids. While both are highly effective at reducing pain and inflammation, they operate through distinct biological pathways and carry significantly different risk profiles. For healthcare providers, understanding the nuance between these medications is critical for preventing life-threatening complications like gastrointestinal hemorrhage or adrenal crisis.
Mechanism of Action: How They Work
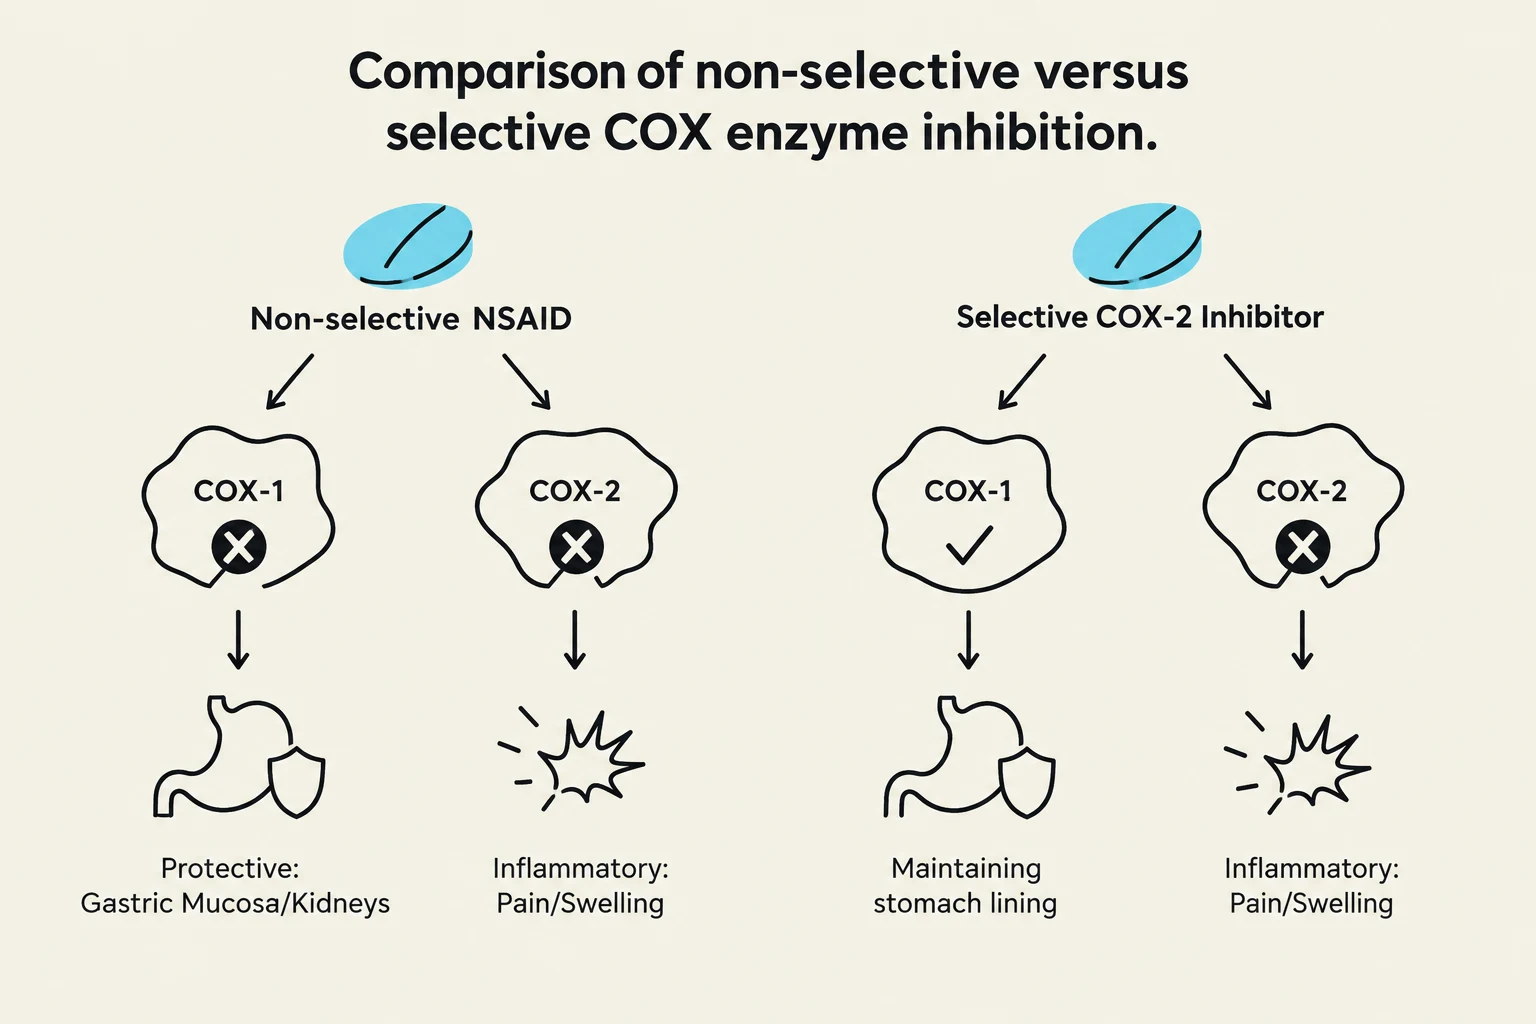
Comparison of non-selective versus selective COX enzyme inhibition, illustrating the effects of NSAIDs on COX-1 and COX-2 enzymes and their impact on the gastric mucosa, kidneys, and pain/swelling.
To understand why these drugs cause specific side effects, we must first look at how they interrupt the inflammatory process.
NSAIDs (Non-Steroidal Anti-Inflammatory Drugs)
NSAIDs, such as Ibuprofen and Celecoxib, work by inhibiting the enzyme cyclooxygenase (COX). This enzyme is responsible for the synthesis of prostaglandins, which are lipid compounds that signal pain, induce fever, and mediate inflammation.
There are two primary types of COX enzymes:
COX-1: Often referred to as the "housekeeping" enzyme. It helps maintain the protective lining of the stomach (gastric mucosa), supports kidney function, and aids platelet aggregation.
COX-2: Primarily induced during injury or inflammation. This is the target for reducing pain and swelling.
Traditional NSAIDs (like Ibuprofen) are non-selective, meaning they inhibit both COX-1 and COX-2. This provides pain relief but also strips away the stomach's protective lining. Selective COX-2 inhibitors (like Celecoxib) are designed to target inflammation while sparing the COX-1 enzyme, theoretically reducing GI irritation, though they may still carry cardiovascular risks.
Corticosteroids (Prednisone)
Corticosteroids, such as Prednisone, act much higher up in the physiological cascade. Rather than just blocking one enzyme, they mimic the effects of hormones produced by the adrenal cortex. They work by suppressing the immune response and inhibiting the production of various inflammatory mediators at the genetic level. Because they are systemic and potent, they are often used for acute flares of autoimmune diseases, but their "broad-spectrum" suppression makes them much more taxing on the body's natural regulatory systems.
Nursing Assessments: Monitoring for Toxicity
Because these medications impact vital organ systems, nurses must perform targeted assessments.
Gastrointestinal (GI) Function
Both drug classes pose a significant threat to the GI tract, but through different mechanisms.
NSAIDs: By inhibiting COX-1, these drugs reduce the production of protective mucus in the stomach, making the patient highly susceptible to peptic ulcers and GI bleeding.
Corticosteroids: While they don't directly inhibit the protective lining as aggressively as NSAIDs, they can increase the risk of ulceration, especially when used in combination with NSAIDs.
Nursing Action: Monitor for signs of occult or overt bleeding, such as:
Black, tarry stools (melena).
Hematemesis (vomiting blood or "coffee-ground" emesis).
Epigastric pain or tenderness.
Renal (Kidney) Function
Mechanism of NSAID-induced renal vasoconstriction.
NSAIDs can significantly impact renal perfusion. By inhibiting prostaglandins that help dilate the afferent arterioles in the kidney, NSAIDs can cause vasoconstriction, leading to decreased glomerular filtration rates (GFR) and potential acute kidney injury.
Nursing Action:
Monitor Intake and Output (I&O).
Track serum creatinine and Blood Urea Nitrogen (BUN) levels.
Assess for peripheral edema (a sign of fluid retention).
💡 Exam Tip: The "Double Whammy"
If a patient is prescribed both an NSAID and a Corticosteroid, their risk for GI bleeding increases exponentially. Always check the medication administration record (MAR) for concurrent use of these two classes.
Critical Patient Education
Patient education is the most effective way to prevent adverse events once the patient leaves the clinical setting.
The Danger of Sudden Cessation (Corticosteroids)
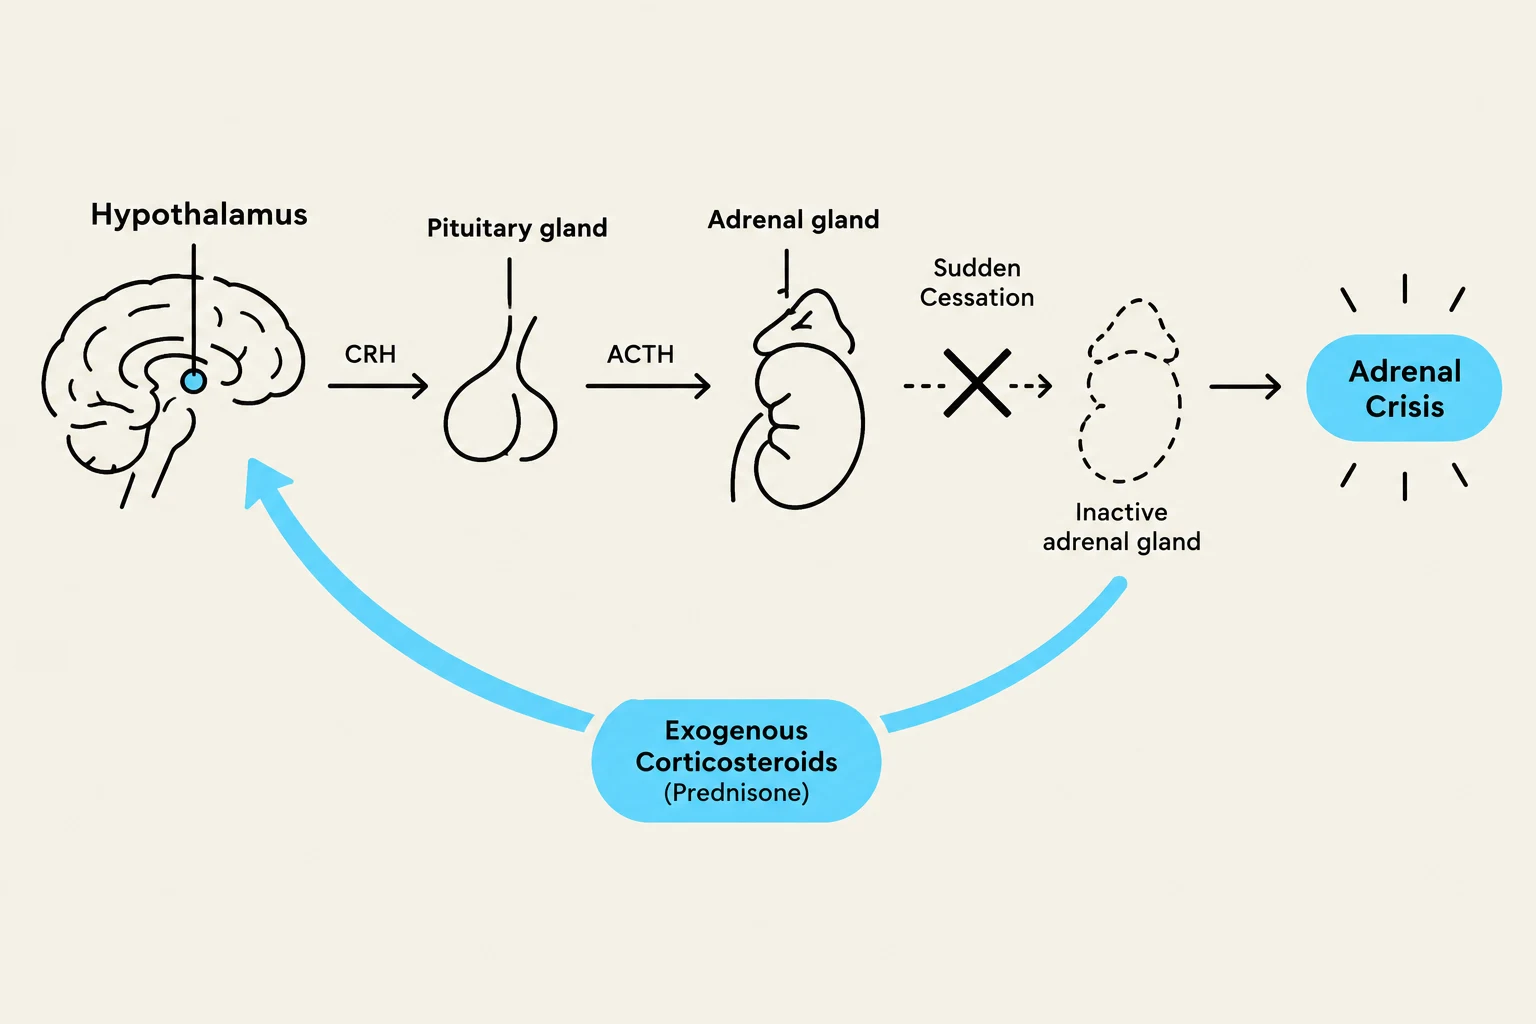
Diagram illustrating the HPA axis and the potential for adrenal crisis due to sudden cessation of exogenous corticosteroids like Prednisone.
One of the most dangerous mistakes a patient can make with Prednisone is stopping the medication abruptly. When a patient takes exogenous (external) corticosteroids for a prolonged period, the body's natural production of cortisol via the hypothalamic-pituitary-adrenal (HPA) axis is suppressed.
If the drug is stopped suddenly, the body cannot immediately resume its own hormone production, leading to acute adrenal insufficiency (Addisonian crisis), which can be fatal.
Education Point: "You must taper this medication. Never stop taking Prednisone without a doctor's specific tapering schedule."
Bleeding Risks and Lifestyle
Patients on NSAIDs must be educated on the signs of bleeding and how to mitigate risks.
Signs to Report: Instruct patients to report any change in stool color (black/tarry) or any unusual bruising immediately.
Mitigation: Suggest taking NSAIDs with food or milk to buffer the stomach, though this does not eliminate the underlying risk to the gastric mucosa.
Avoidance: Advise patients to avoid excessive alcohol consumption, which further irritates the gastric lining and increases bleeding risk.
Summary Table for Quick Review
Feature
NSAIDs (e.g., Ibuprofen)
Corticosteroids (e.g., Prednisone)
Primary Target
COX-1 and COX-2 enzymes
Immune system/HPA axis
Main Risk
GI ulcers, Renal impairment
Adrenal suppression, Hyperglycemia, Bone loss
Key Assessment
Creatinine, Stool color, Edema
Blood glucose, Weight, Tapering adherence
Cessation Risk
Low (Withdrawal not typical)
High (Risk of Adrenal Crisis)
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.