This content explains the principles of movement analysis, including sequencing, timing, and accuracy, and discusses theoretical frameworks of motor control such as Reflex Theory, Hierarchical Theory, Systems Theory, and Dynamic Systems Theory. It details the analysis of functional transitions like side-lying to sit an
In clinical practice, observing a patient move is more than just watching them walk or stand; it is a sophisticated process of evaluating how the nervous system coordinates muscles, joints, and environmental constraints to achieve a goal. This process, known as movement analysis, allows clinicians to break down complex actions into measurable components to identify specific deficits in strength, coordination, or neurological control. By understanding the underlying mechanics of transitions like sitting up or standing, therapists can design targeted interventions to improve functional independence.
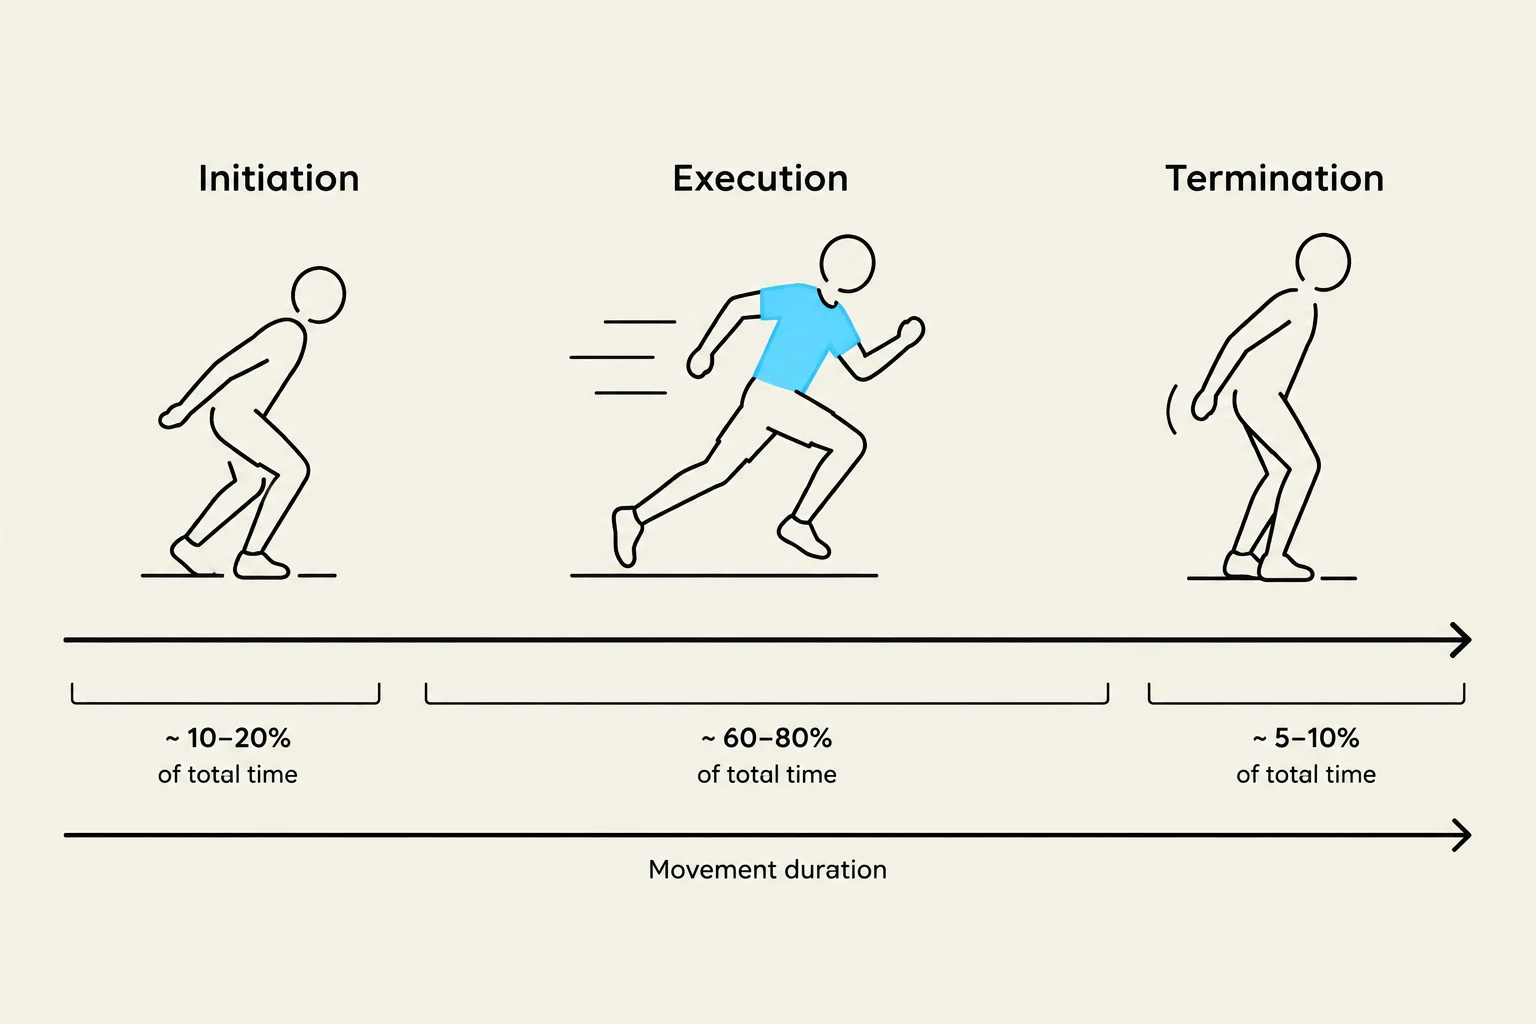
A diagram illustrating the three phases of movement: Initiation, Execution, and Termination, with their respective durations as percentages of total time.
The Dimensions of Movement Analysis
To analyze a movement effectively, we must look beyond the "what" and focus on the "how." Movement analysis is categorized into several key constructs that describe the quality and structure of motor output:
Sequencing: This refers to the specific order of motor output required to achieve the intended goal. For example, in a sit-to-stand task, the sequence of hip flexion before knee extension is vital for success.
Timing: This is the temporal structure of the movement. It includes the relative percentage of time devoted to different segments, specifically the initiation phase, the execution phase, and the termination phase.
Accuracy: This measures how closely a movement matches a standard or known value, essentially representing the "freedom from error" in the movement pattern.
Symptom Provocation: During analysis, clinicians must monitor for movements that evoke specific patient symptoms, such as pain or neurological sensations, which can guide diagnosis and treatment precautions.
Exam Tip: When analyzing a task, remember that "smoothness" is a component of coordination. A movement is perceived as smooth when it occurs in a continual fashion without interruptions in velocity or trajectory.
Analyzing Functional Transitions
Functional tasks are rarely single movements; they are sequences of phases. We can analyze these by breaking them down into the initiation, execution, and termination stages.
Side-Lying to Sit at the Edge of the Bed (EOB)
Phases of the side-lying to sit transition, illustrating hip and trunk movement, reach and weight-bearing, and the final stable sitting position.
Transitioning from a side-lying position to sitting at the edge of the bed is a complex task requiring significant trunk and upper extremity coordination.
Initiation Phase: The movement begins with hip flexion of both lower extremities to move the legs off the edge of the bed. This is followed by trunk lateral flexion to begin the shift in center of mass.
Execution Phase: The patient continues lateral trunk flexion while performing shoulder abduction to bring the elbow into a weight-bearing position. Simultaneously, elbow extension is required to transfer weight onto the hand.
Termination Phase: The movement concludes when the patient achieves a stable, upright sitting posture.
Potential Impairments: Clinicians should look for deficits in amplitude, speed, or smoothness. Specific difficulties may include an inability to perform sufficient shoulder abduction, poor elbow extension, or difficulty with hip flexion to clear the bed.
Sit-to-Stand (STS)
The sit-to-stand task is a fundamental mobility skill that relies heavily on momentum and postural control. Analysis begins by observing initial conditions, such as seat height, the presence of armrests, and the support surface of the feet.
Preparation: The patient must achieve a "ready position." The essential component here is the anterior pelvic tilt, which prepares the body for the upcoming movement.
Initiation Phase: This phase relies on flexion momentum. The patient uses hip flexion while the trunk is initially extended to create the necessary forward momentum.
Execution Phase: As the momentum is transferred, the patient performs triple extension (simultaneous extension of the hips, knees, and ankles) to rise.
Termination Phase: The task ends once the patient reaches a standing position and achieves stabilization.
Muscle Actions and Biomechanics in STS
The success of the sit-to-stand transition depends on the precise coordination of muscle contractions:
Muscle Group
Contraction Type
Role in Sit-to-Stand
Quadriceps & Glutes
Concentric
Provides the force to extend the joints and lift the body weight.
Erector Spinae
Eccentric
Controls the trunk movement and maintains stability.
Transverse Abdominis (TA)
Eccentric
Provides core stability and helps bring the knees forward for momentum.
Rectus Abdominis
Eccentric
Assists in controlling the trunk during the transition.
Potential Impairments: Common errors include a lack of anterior pelvic tilt during preparation, insufficient flexion momentum, or a "slumped" upper trunk (flexed posture) during the rise.
Clinical Note: If a patient exhibits inadequate TA eccentric activation, they may struggle to translate the knees forward, which is critical for generating the momentum needed for the execution phase.
Theoretical Frameworks of Motor Control
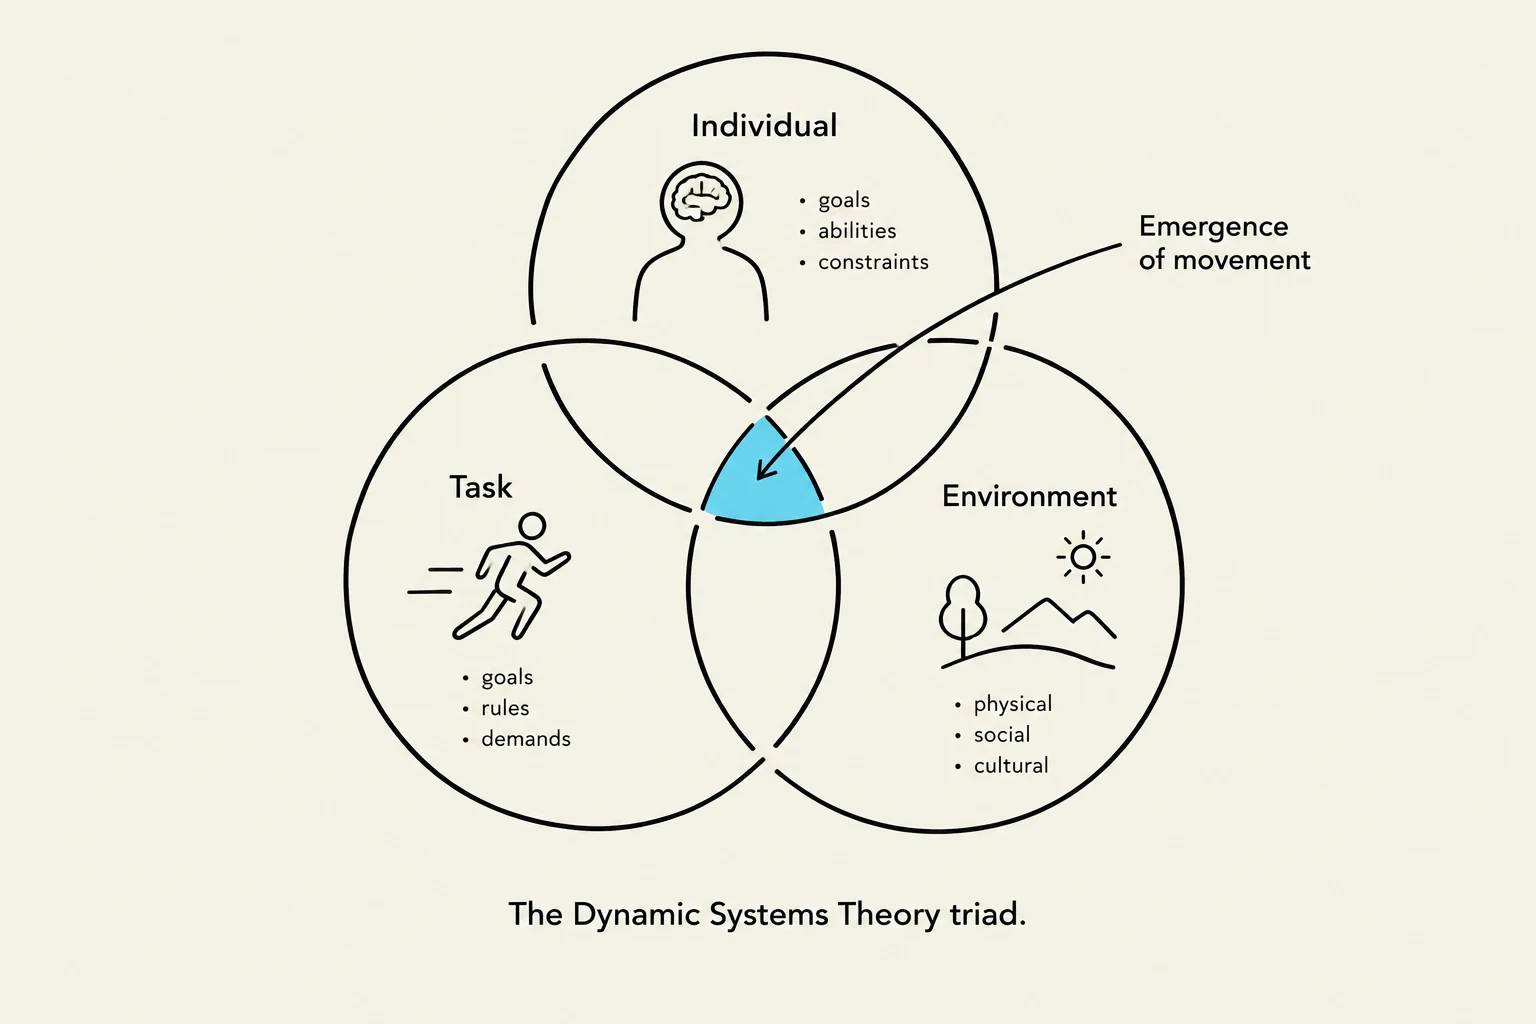
A diagram illustrating the Dynamic Systems Theory triad, showing the interaction of Individual, Task, and Environment factors in the emergence of movement.
Understanding why these movements occur requires looking at motor control theories. These theories explain how the central nervous system (CNS) manages the "degrees of freedom" (the many moving parts of the body):
Reflex Theory: Suggests that movement is a chain of individual reflexes. While it explains primitive developmental movements (like righting reactions), it is often considered too simplistic for complex adult tasks.
Hierarchical Theory: Views the nervous system as a top-down structure where higher centers exert inhibitory or excitatory control over lower-level reflexes.
Systems Theory: Moves away from a purely neural view, looking at the body as a mechanical system. It suggests that movement emerges from the interaction of many systems (muscular, skeletal, etc.).
Dynamic Systems Theory: Suggests that movement is not just controlled by the brain but emerges from the interaction between the individual, the task, and the environment.
By applying these analyses, clinicians can move from simply observing a patient's struggle to identifying whether the issue is a lack of strength (concentric deficit), a lack of stability (eccentric deficit), or a breakdown in the temporal sequencing of the movement.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.