This document explains the macrovascular and microvascular complications of diabetes mellitus, including cardiovascular disease, stroke, retinopathy, nephropathy, and neuropathy. It also covers metabolic syndrome and clinical management strategies.
Diabetes mellitus is a progressive metabolic disorder that, if not managed effectively, can lead to devastating systemic consequences. While acute complications like hypoglycemia or ketoacidosis require immediate attention, the long-term complications are often more common, cause significant disability, and can affect almost every organ system in the body. Understanding these complications is essential for healthcare providers to implement preventative strategies and manage patient outcomes effectively.
Macrovascular Complications and Cardiovascular Disease
The most significant long-term threat to patients with diabetes is cardiovascular disease, which serves as the primary cause of death in this population. Macrovascular complications involve damage to the large blood vessels, characterized by thickened vessel walls and occlusion (blockage).
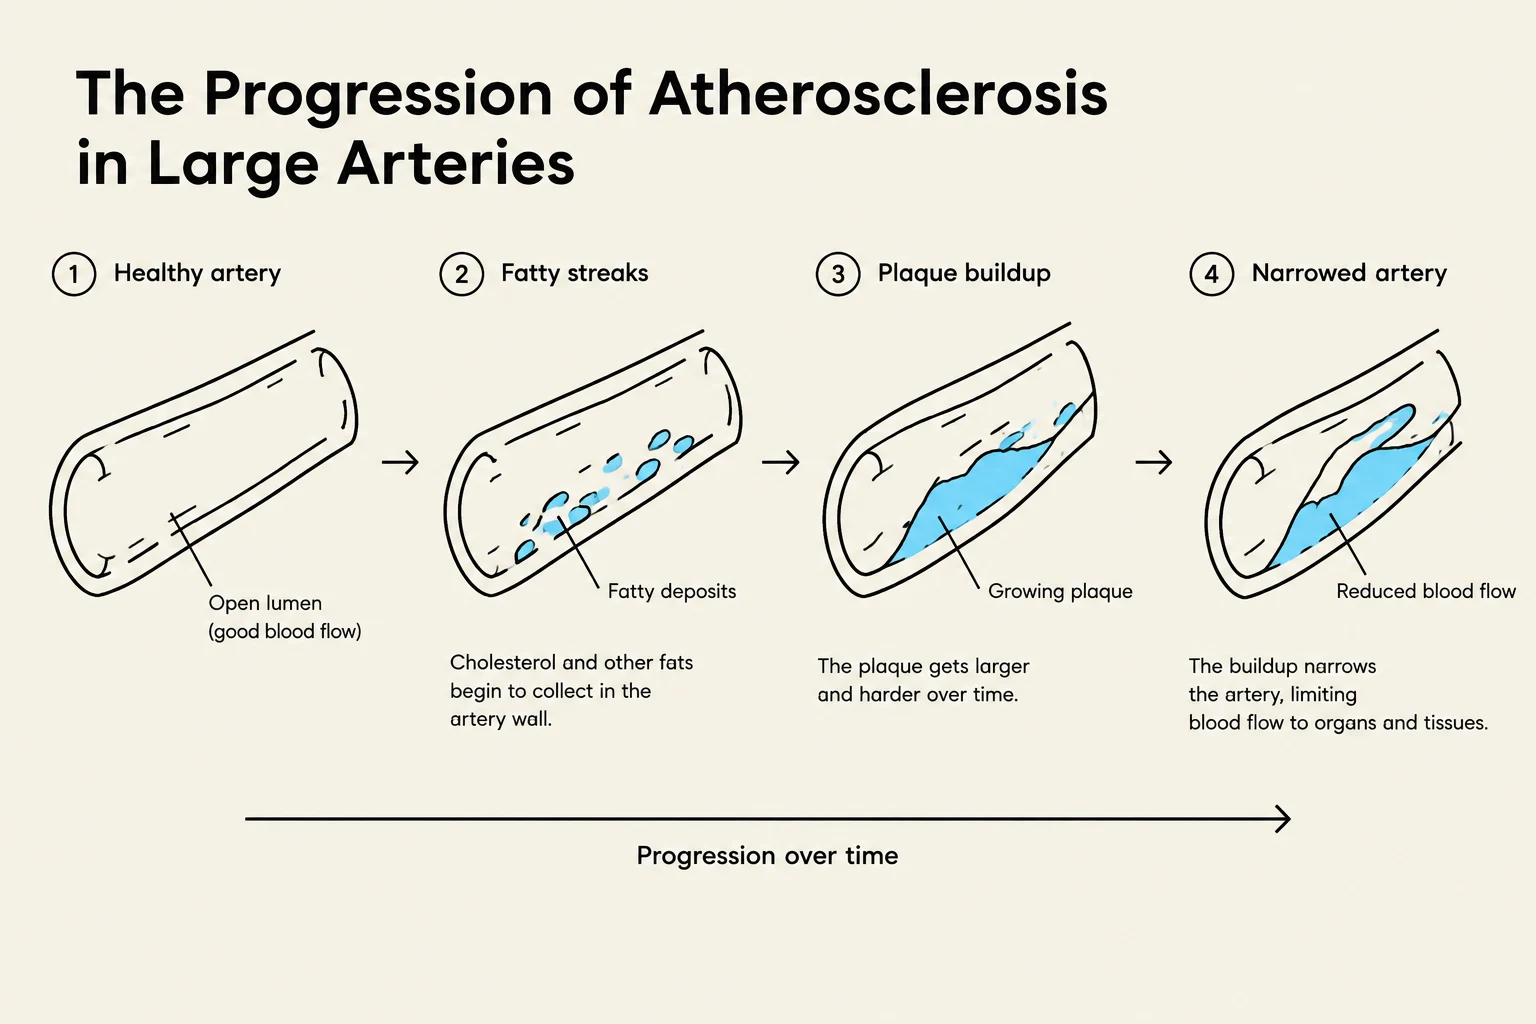
These complications are driven by several interrelated risk factors, including high blood sugar (BS), obesity, hypertension (HTN), and increased triglycerides. A major driver of this process is atherosclerosis, the buildup of plaque within the arterial walls, which impairs circulation.
The Spectrum of Macrovascular Disease
Macrovascular issues manifest in several critical areas:
Coronary Artery Disease (CAD): Occurs when atherosclerosis affects the vessels supplying the heart, leading to impaired blood flow to the cardiac muscle.
Cerebrovascular Disease (CVD): Affects the vessels supplying the brain, significantly increasing the risk of a stroke.
Peripheral Vascular Disease (PVD): Occurs when circulation is impaired to the extremities, such as the legs.
Diagram illustrating the progression of atherosclerosis in large arteries, showing the stages from a healthy artery to a narrowed artery due to plaque buildup.
Stroke: Ischemic vs. Hemorrhagic
Diabetic patients face twice the risk of stroke compared to the general population. High sugar levels damage epithelial tissue, causing vessel walls to stiffen and lose elasticity, which increases the risk of coagulation. Strokes are categorized into two main types:
Ischemic Stroke: Caused by blood clots or fatty deposits that break off and travel to the brain, blocking blood flow.
Hemorrhagic Stroke: Caused by the rupture of a blood vessel, leading to bleeding within the brain.
Metabolic Syndrome and Insulin Resistance
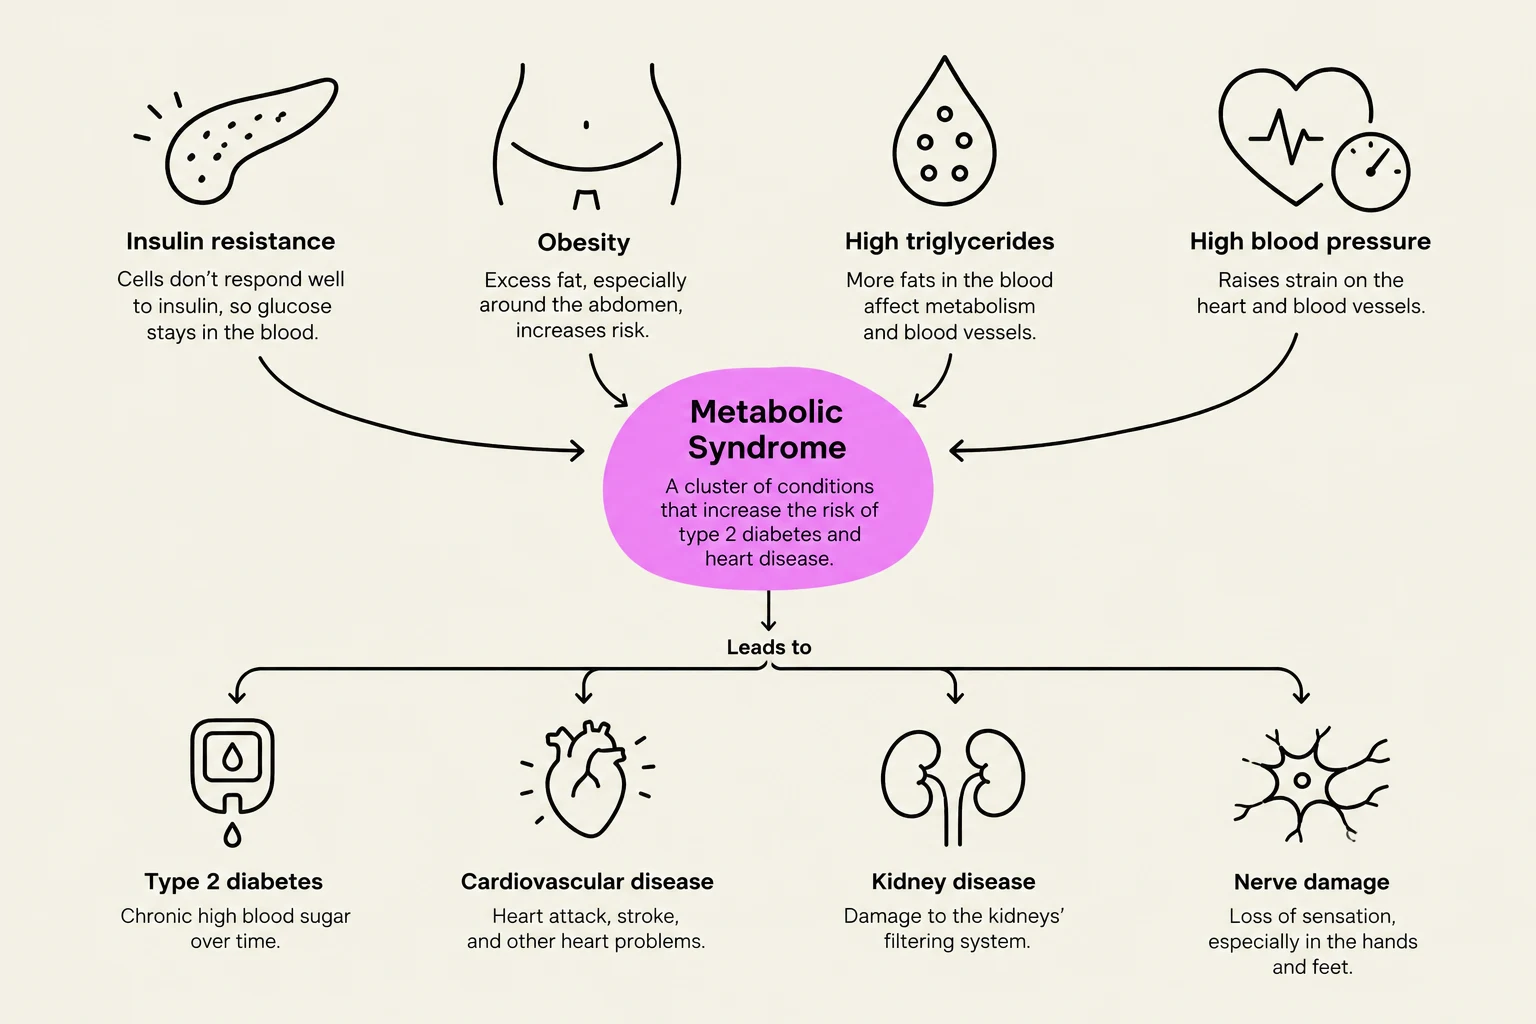
Many patients with diabetes also present with metabolic syndrome, a cluster of risk factors that significantly heightens the risk for heart disease. This syndrome is often characterized by insulin resistance, a state where the body's cells do not respond effectively to insulin, necessitating higher glucose levels.
The clinical hallmarks of metabolic syndrome include:
Abdominal Obesity: Often described as a "large waistline" or an "apple shape".
Dyslipidemia: Specifically, high triglyceride levels and low HDL (the "good") cholesterol levels.
Hypertension: High blood pressure.
Hyperglycemia: High fasting blood sugar levels.
Cardiomyopathy and Heart Health
Beyond the direct blockage of arteries, diabetes can lead to cardiomyopathy, a disease of the heart muscle itself. This can be driven by insulin resistance, physical inactivity, and dyslipidemia.
When a patient suffers from chronic hypertension, the heart must work harder to pump blood against increased resistance. Because the heart is a muscle, this constant overworking causes it to enlarge, a condition known as left ventricular hypertrophy. This enlargement can eventually lead to poor cardiac output and heart failure.
This diagram illustrates the components and consequences of metabolic syndrome, a cluster of conditions that increase the risk of type 2 diabetes and heart disease. It shows contributing factors like insulin resistance, obesity, high triglycerides, and high blood pressure, and resulting conditions such as type 2 diabetes, cardiovascular disease, kidney disease, and nerve damage.
Exam Tip: When studying cardiovascular complications, remember that macrovascular issues refer to large vessels (CAD, PVD, Stroke), whereas microvascular issues refer to small vessels (Retinopathy, Nephropathy, Neuropathy).
Microvascular Complications: The "-Pathies"
While macrovascular issues affect large vessels, diabetes also causes significant damage to the capillaries through a process called capillary basement membrane thickening. This leads to three primary microvascular "pathies":
1. Diabetic Retinopathy
This is a leading cause of blindness in adults aged 20–74. It progresses through four stages:
Mild Nonproliferative: Initial swelling and possible leaking of vessels.
Moderate Nonproliferative: Essential vessels become blocked, increasing swelling.
Severe Nonproliferative: The retina is no longer adequately perfused; the body begins signaling for new vessel growth.
Proliferative Retinopathy: The final stage where new, fragile, and abnormal blood vessels grow. These are prone to leaking, which can lead to diabetic macular edema (DME), neovascular glaucoma, or a medical emergency known as tractional retinal detachment.
2. Diabetic Nephropathy
Diabetes is a major driver of kidney disease; diabetic patients account for 50% of new diagnoses of End-Stage Kidney Disease (ESKD) each year. Key indicators include the presence of albumin in the urine and abnormal BUN/Creatinine levels.
3. Diabetic Neuropathy
Nerve damage from continuous uncontrolled sugar can affect up to 50% of clients with diabetes.
Peripheral Neuropathy: Usually starts in the feet and legs (distal symmetric) and can cause numbness, tingling, or burning. This loss of sensation increases the risk for undetected foot infections and amputations.
Autonomic Neuropathy: Affects the Autonomic Nervous System (ANS), leading to cardiac issues (tachycardia, silent MI), GI issues (delayed emptying), or renal issues (urinary retention).
Mononeuropathy: Damage to a specific nerve, such as causing Bell's palsy or double vision.
Proximal Neuropathy (Diabetic Amyotrophy): Affects the thighs, hips, or buttocks, often causing severe pain and muscle weakness.
Clinical Management and Patient Safety
Managing these complications requires a multi-faceted approach involving blood sugar control, blood pressure management, and lifestyle modifications.
For patients in a hospital setting, blood glucose targets are typically maintained between 140–180 mg/dL. During "sick days," patients must be educated to continue their medications, monitor blood sugar every 4 hours, and stay hydrated.
Clinical Alert: If a patient with diabetes is unable to keep liquids down for more than 4 hours, is experiencing severe vomiting/diarrhea for more than 6 hours, or is feeling sleepy/confused, they must seek immediate medical attention.
Summary Table: Complication Overview
Type
Key Complications
Primary Mechanism
Macrovascular
CAD, Stroke, PVD
Atherosclerosis & vessel occlusion
Microvascular
Retinopathy, Nephropathy, Neuropathy
Capillary basement membrane thickening
Metabolic
Metabolic Syndrome
Insulin resistance & dyslipidemia
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.