Understanding Iron Deficiency Anaemia: A Pathophysiological Analysis
This content examines iron deficiency anaemia (IDA) through a clinical case study, detailing its pathophysiology, diagnostic markers, and compensatory physiological responses. It covers red blood cell morphology, iron studies, and the impact of IDA on oxygen transport.
Anaemia is a condition characterized by a deficiency in the number of healthy red blood cells (RBCs) or the amount of haemoglobin within them, leading to a reduced capacity of the blood to transport oxygen. This case study examines Ms M, a 29-year-old professional squash player, who presented with light-headedness and syncope (fainting) during a tournament. Through an analysis of her clinical presentation and laboratory results, we will explore the complex relationship between iron availability, haemoglobin synthesis, and the body's physiological attempts to maintain homeostasis.
Clinical Presentation and Initial Findings
Ms M presented with several classic signs of anaemia. Upon admission, her vital signs revealed significant deviations from the norm: a heart rate of 140 bpm (tachycardia) and a respiratory rate of 28 breaths per minute (tachypnoea). Her blood pressure was also low at 100/40 mmHg. Physical examination noted pale skin and conjunctiva, spoon-shaped nails, and a smooth tongue.
Her initial laboratory results showed a haemoglobin (Hb) level of 80 g/L and a haematocrit (HCT) of 30%. These values indicate a significant reduction in the proportion of blood volume composed of red blood cells.
Microcytic Hypochromic Anaemia
The morphology of Ms M's red blood cells is a critical diagnostic clue. Laboratory analysis identified her cells as microcytic (small) and hypochromic (pale). To understand why this occurs, we must look at the indices used to describe red cell size and colour:
MCV (Mean Corpuscular Volume): Measures the average size of an RBC. Ms M's value was 70 fL (Ref: 80–100 fL), indicating microcytosis.
MCH (Mean Corpuscular Haemoglobin): The average amount of haemoglobin per RBC. Her value was 18 pg (Ref: 27–32 pg).
MCHC (Mean Corpuscular Haemoglobin Concentration): The average concentration of haemoglobin within a given volume of packed red cells. Her value was 270 g/L (Ref: 300–350 g/L).
Exam Tip: When you see low MCV, MCH, and MCHC together, think of a "production problem." The cell is small and pale because it lacks the "filling" (haemoglobin) that gives it volume and colour.
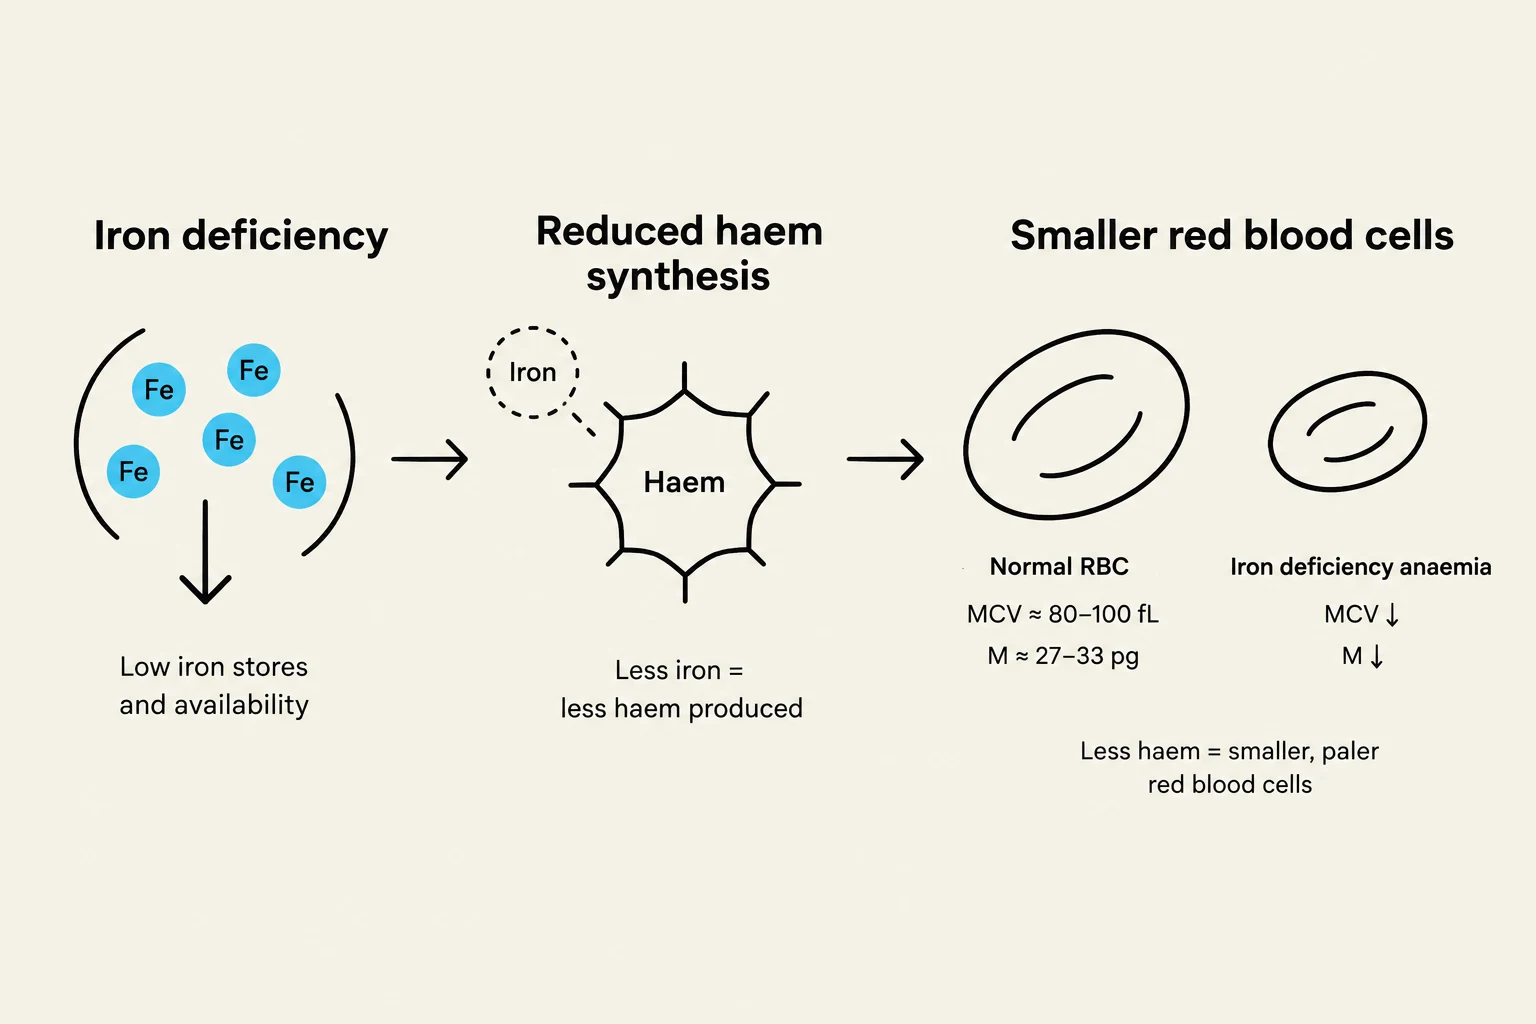
This diagram illustrates the process of iron deficiency leading to reduced haem synthesis, resulting in smaller and paler red blood cells characteristic of iron deficiency anaemia. It shows the impact on iron stores, haem production, and red blood cell indices like MCV and M.
The Mechanism: Haem and Haemoglobin Synthesis
The root cause of these morphological changes lies in the synthesis of haem. Haem is a component of haemoglobin that requires iron to be produced. Iron must be incorporated into protoporphyrin IX to form haem.
In Ms M's case, iron deficiency leads to a cascade of events:
↓ Iron availability→↓ Haem synthesis.
↓ Haemoglobin synthesis→ The developing erythroblasts cannot fill themselves with enough haemoglobin.
Cellular Division: To attempt to reach a functional concentration of haemoglobin, the cells undergo extra divisions, resulting in smaller cells (↓ MCV).
Reduced Density: Because there is less haemoglobin per cell, the cells appear pale (↓ MCH and MCHC).
Iron Studies and Diagnostic Differentiation
To confirm the diagnosis, clinicians look at specific iron markers. Ms M's results provided a classic pattern for iron deficiency anaemia (IDA):
Parameter
Ms M's Result
Interpretation
Ferritin
8 μg/L (Low)
Depleted iron stores
Serum Iron
30 μg/dL (Low)
Reduced circulating iron
TIBC
600 μg/dL (High)
Increased iron-binding capacity as the body seeks more iron
Transferrin Saturation
10% (Low)
Insufficient iron available for erythropoiesis
FEP (Free Erythrocyte Protoporphyrin)
110 μg/dL (High)
Protoporphyrin accumulates because there is no iron to convert it to haem
This diagram illustrates the profile of iron studies in Iron Deficiency Anaemia (IDA), showing low ferritin and serum iron, and high TIBC and FEP, with corresponding explanations for each.
Differential Diagnosis: Thalassaemia
Given Ms M's Greek ancestry and her pronounced microcytosis (MCV 70 fL), a clinician might initially consider thalassaemia. Thalassaemia is a genetic condition affecting globin chain synthesis that also presents with small, pale red cells. However, Ms M's iron studies—specifically the low ferritin and high TIBC—strongly point toward iron deficiency rather than a genetic haemoglobinopathy.
Physiological Compensatory Responses
When haemoglobin levels drop, the body's oxygen-carrying capacity is compromised. While the lungs can still oxygenate the blood, there is simply not enough haemoglobin to carry an adequate volume of oxygen to the tissues. This leads to a decrease in tissue oxygen delivery.
To compensate for this deficit, the body initiates several physiological responses:
Tachycardia: An increased heart rate (140 bpm) to increase cardiac output and move blood faster.
Tachypnoea: An increased respiratory rate (28/min) to maximize oxygen uptake in the lungs.
In Ms M's case, these compensations were insufficient during the high oxygen demands of a squash tournament. The mismatch between oxygen supply and demand led to cerebral hypoxia (low oxygen to the brain), resulting in her light-headedness and fainting.
The Erythropoietic Response
Normally, when the body senses low oxygen, the bone marrow increases its erythropoietic response by releasing more reticulocytes (immature red blood cells). However, Ms M's reticulocyte count was 1%, which is "inappropriately low" given the severity of her anaemia.
To find the true state of her marrow's production, we must calculate the corrected reticulocyte percentage:
Using Ms M's data:
Corrected Reticulocyte %=1%×(4530)=1%×0.667=0.67%
This low corrected value confirms that her bone marrow cannot effectively respond to the anaemia because it lacks the essential raw material: iron.
Conclusion and Management
Ms M's condition was likely caused by chronic menstrual blood loss, a known side effect of her copper IUD. Management must be two-fold: correcting the iron deficiency (via oral or IV iron) and addressing the underlying cause (managing her menstrual bleeding and reviewing contraceptive options).
This diagram illustrates the process of iron deficiency anemia, starting with blood loss leading to depleted ferritin (low iron stores), which results in impaired iron availability and ultimately iron deficiency anemia. The cycle can continue if the underlying cause of iron deficiency is not addressed.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.