Understanding High-Risk Pregnancies and Antepartum Alterations
This guide explains the various factors contributing to high-risk pregnancies, including biophysical, psychosocial, sociodemographic, and environmental domains. It details common antepartum alterations such as hyperemesis gravidarum, ectopic pregnancy, placenta previa, preeclampsia, and gestational diabetes, along with
Pregnancy is a complex physiological process that, while often progressing naturally, can be jeopardized by various threats to the well-being of the mother and the fetus. A "high-risk" pregnancy is defined as any pregnancy where the life or well-being of the pregnant woman or infant is at risk due to biophysical or psychosocial disorders. Modern clinical practice has moved beyond a purely medical view of risk, adopting a holistic approach that recognizes how multiple, overlapping factors contribute to pregnancy outcomes.
Categorizing Risk Factors
To provide safe and culturally competent care, clinicians must differentiate between various types of risk factors. These factors are often interrelated and cumulative, meaning one risk factor can exacerbate another.
The Four Domains of Risk
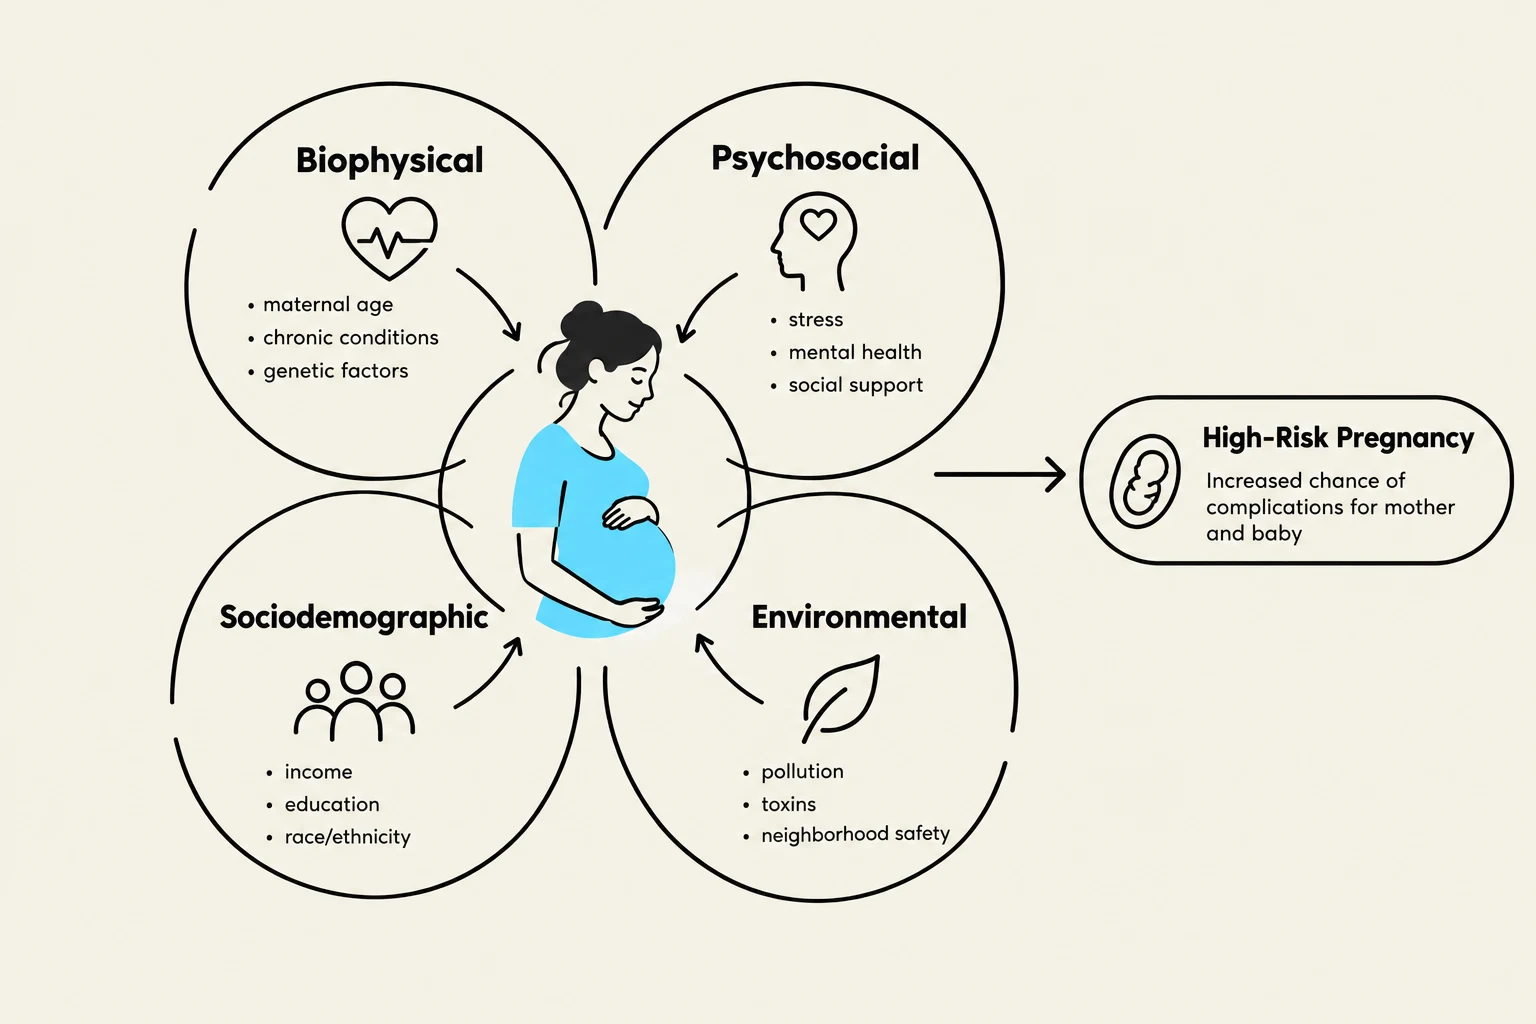
Modern nursing practice categorizes risk into four broad domains:
Biophysical: Physiological factors such as age, parity (number of births), blood type (e.g., Rh incompatibility), and pre-existing medical conditions.
Psychosocial: Mental health, stress, coping mechanisms, and support systems.
Sociodemographic: Factors like socioeconomic status, education, and ethnicity.
Environmental: External influences such as exposure to toxins, pollution, or unsafe living conditions.
Timing of Alterations
Risk factors are also categorized by when they appear in the clinical timeline:
Pre-existing Alterations: Conditions present before conception, such as chronic hypertension, diabetes, or advanced maternal age.
Potential Alterations: New complications that develop during the course of pregnancy, such as gestational diabetes or preeclampsia.
This diagram illustrates the various factors contributing to a high-risk pregnancy, categorized into biophysical, psychosocial, sociodemographic, and environmental aspects.
Common Antepartum Alterations
Understanding the pathophysiology and clinical manifestations of specific alterations is essential for effective nursing intervention.
Hyperemesis Gravidarum
Unlike typical "morning sickness," hyperemesis gravidarum involves excessive vomiting that often occurs after 12 weeks of gestation. The woman may retch even when not eating, leading to significant dehydration, electrolyte imbalances, and weight loss (typically >5%).
Clinical Manifestations: Increased pulse rate, decreased blood pressure, poor skin turgor, and the presence of ketones in the urine.
Nursing Care: Focus on hydration (IV Lactated Ringers), nutritional support (small, frequent meals), and managing environmental triggers like food odors.
Ectopic Pregnancy
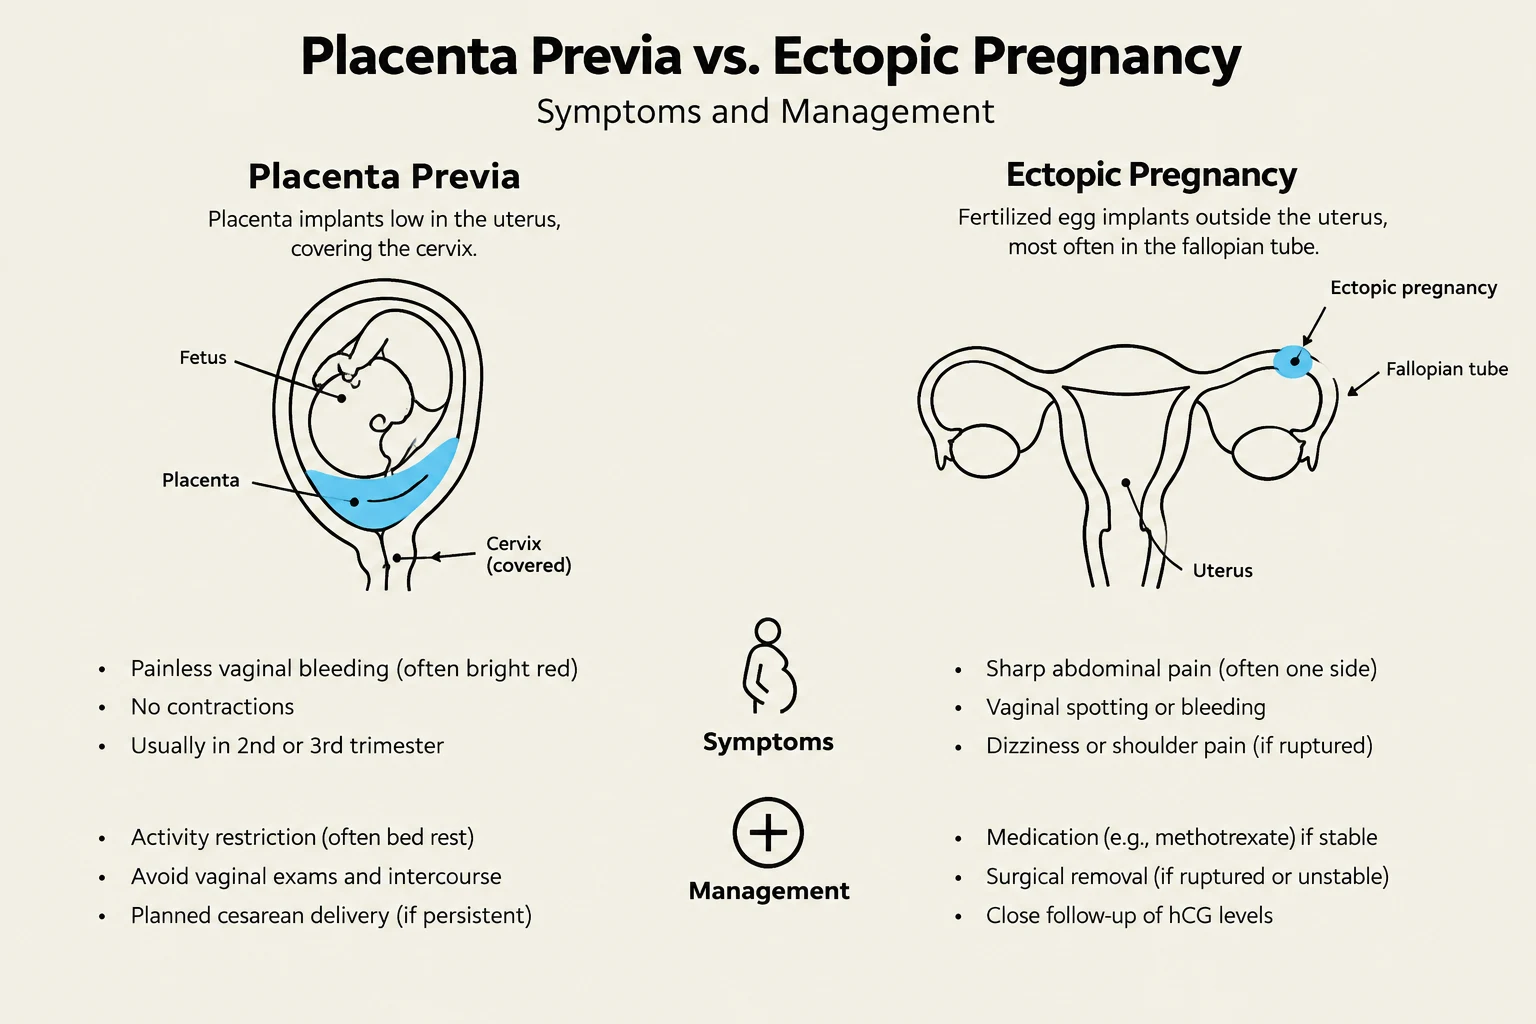
An ectopic pregnancy occurs when a fertilized ovum implants outside the endometrial lining of the uterus. This is a medical emergency due to the risk of rupture and hemorrhage.
Clinical Manifestations: Unilateral stabbing abdominal pain, delayed/light menses, dark red/brown spotting, and referred shoulder pain.
Management: Medical management may include methotrexate to inhibit cell division if rupture has not occurred.
Placenta Previa
Placenta previa occurs when the placenta implants in the lower segment of the uterus, covering or near the cervical os.
Clinical Manifestations:Bright red, painless bleeding during the third trimester, with a soft, non-tender uterus and a reassuring fetal heart rate.
Critical Nursing Alert:No vaginal examinations should be performed on a client with suspected placenta previa, as this can trigger massive hemorrhage.
This diagram illustrates and compares Placenta Previa and Ectopic Pregnancy, detailing their symptoms and management strategies.
Preeclampsia and Hypertensive Disorders
Hypertensive disorders range from gestational hypertension (new onset after 20 weeks) to preeclampsia, which includes signs of end-organ damage.
Preeclampsia Manifestations: Blood pressure ≥140/90 mmHg (or ≥160/110 mmHg in severe cases), proteinuria (≥2+ on dipstick), persistent headache, visual disturbances, and epigastric pain.
Management: Medications such as methyldopa or labetalol are used for blood pressure control, while magnesium sulfate is administered for seizure prophylaxis.
Exam Tip: Magnesium Sulfate Toxicity
When monitoring a patient on magnesium sulfate, watch for signs of toxicity:
Respiratory depression (respirations <12/min)
Decreased deep tendon reflexes (DTRs)
Decreased urinary output (<30 mL/hr)
Decreased level of consciousness
Gestational Diabetes Mellitus (GDM)
GDM is carbohydrate intolerance that is first recognized during pregnancy. It can be caused by the direct metabolic stress of pregnancy hormones.
Risks: Maternal risks include hydramnios and preeclampsia; fetal risks include macrosomia (large baby), birth trauma, and neonatal hypoglycemia.
Management: Focuses on diet therapy, regular exercise, and blood glucose monitoring.
Clinical Reasoning and Nursing Management
Effective care for high-risk patients requires the application of the nursing process through clinical reasoning and decision-making. Nurses must integrate interrelated concepts such as perfusion, metabolism, oxygenation, stress/coping, and comfort.
Medication Safety and Calculations
Precision in medication administration is vital, especially when managing high-risk infusions.
Example 1: Magnesium Sulfate Infusion Rate
An order is written for Magnesium Sulfate 4 g/hr via continuous infusion. The available medication is 20 g in 500 mL of Lactated Ringers. To find the rate in mL/hr:
Concentration=500 mL20 g=0.04 g/mLRate (mL/hr)=Concentration (g/mL)Desired Dose (g/hr)Rate=0.04 g/mL4 g/hr=100 mL/hr
Example 2: IV Pig (IVPB) Administration
A client is prescribed Zosyn 1.3 g in 100 mL D5W to infuse over 20 minutes. To calculate the mL/hr rate:
Rate (mL/hr)=Time (min)Volume (mL)×60 min/hrRate=20 min100 mL×60=300 mL/hr
The Nurse's Role
The nurse serves as an educator and a support person. This involves:
Assessment: Monitoring maternal vital signs, fetal heart rate, urinary output, and deep tendon reflexes.
Interdisciplinary Collaboration: Working with the healthcare team to implement evidence-based therapies, such as using corticosteroids for fetal lung maturity or Rho(D) immune globulin for Rh-negative mothers.
Psychosocial Support: Providing therapeutic communication, especially during pregnancy loss (spontaneous abortion), where the focus shifts to emotional support and preventing physical complications.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.