Understanding Endocrine Problems and Thyroid Dysfunction
An overview of endocrine system disorders, focusing on thyroid dysfunction including hyperthyroidism and hypothyroidism. Covers causes, clinical manifestations, diagnostic studies, and nursing management strategies for conditions like Graves' disease and myxedema coma.
The endocrine system serves as the body's internal communication network, utilizing hormones to regulate a vast array of physiological processes. Among the most critical players in this system is the thyroid gland, a butterfly-shaped organ located at the front of the neck. By secreting thyroxine (T4) and triiodothyronine (T3), the thyroid gland acts as a master regulator of metabolism, growth, development, heart rate, body temperature, and even bone health. When this delicate balance is disrupted, patients may experience life-threatening conditions ranging from hypermetabolic states to profound metabolic slowing.
Thyroid Gland Function and Goiter
The primary responsibility of the thyroid is to maintain metabolic homeostasis. T3 and T4 influence almost every cell in the body, affecting the nervous system, the menstrual cycle, and cardiovascular stability.
A common clinical finding in thyroid disorders is a goiter, which is an enlargement of the thyroid gland. A goiter does not necessarily indicate a specific disease but is a physical manifestation of an underlying issue. Causes include:
Hyperthyroidism (overactive thyroid)
Hypothyroidism (underactive thyroid)
Iodine deficiency
Thyroid nodules or genetic factors
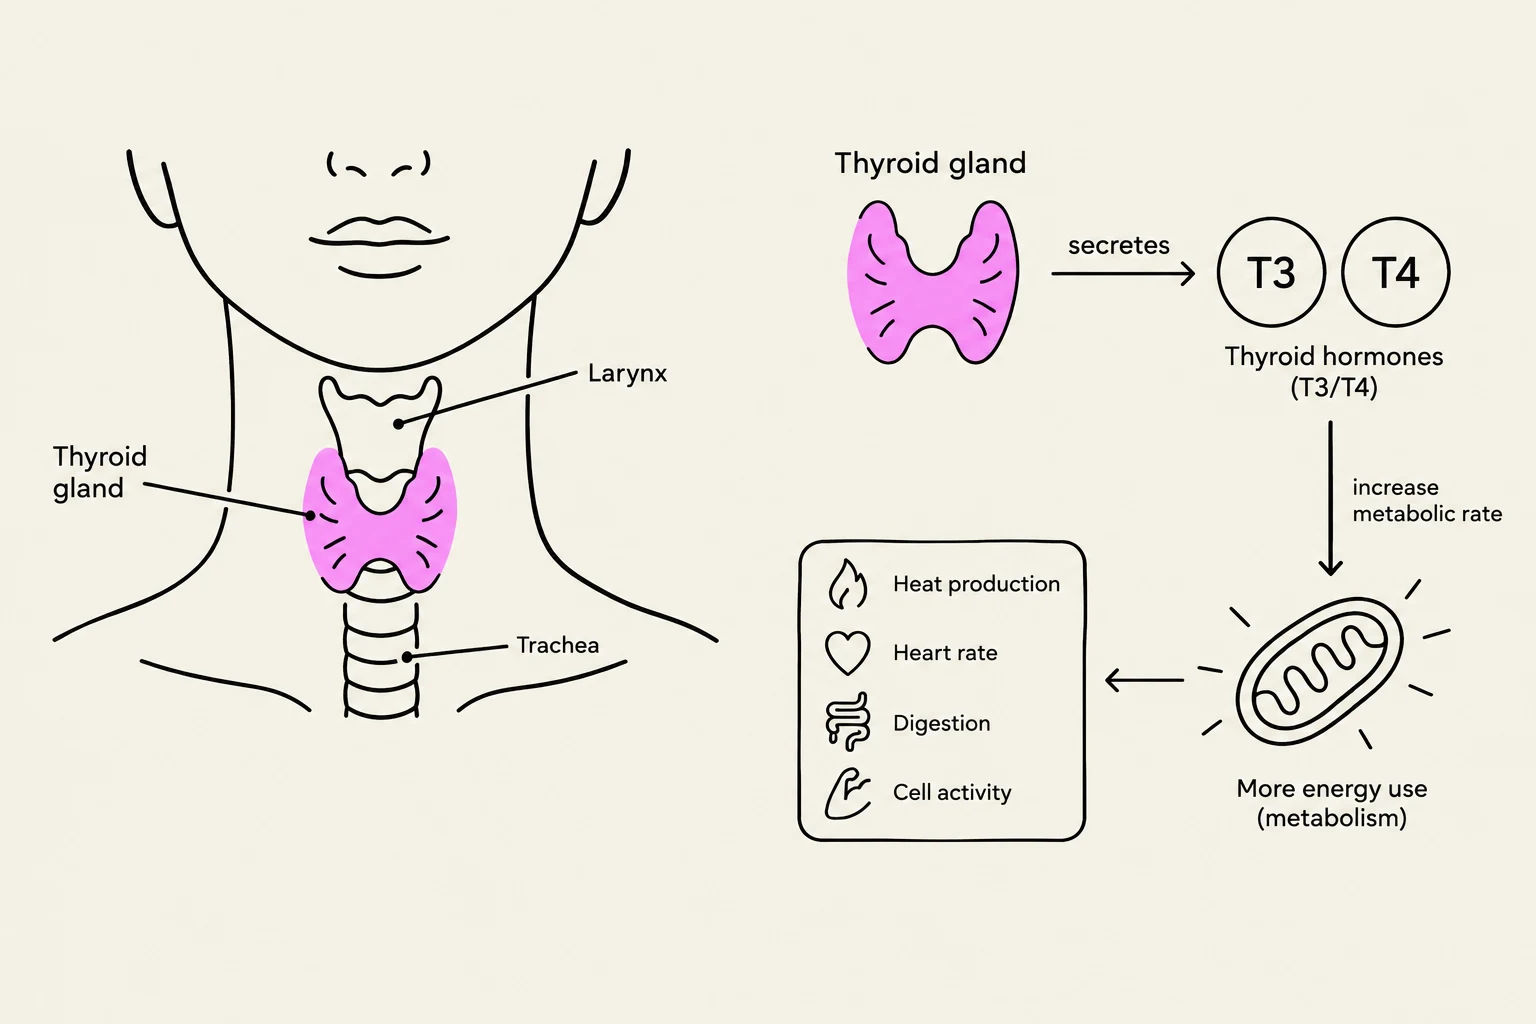
This diagram illustrates the location of the thyroid gland in the human neck and its role in producing thyroid hormones (T3/T4) that increase metabolic rate, affecting heat production, heart rate, digestion, and cell activity.
Hyperthyroidism and Graves’ Disease
Hyperthyroidism is characterized by a sustained increase in the synthesis and release of T3 and T4. This condition is most frequently observed in women between the ages of 20 and 40.
Graves’ Disease
The most common cause of hyperthyroidism is Graves’ disease, an autoimmune disorder where the body produces antibodies that cause diffuse thyroid enlargement and excessive hormone secretion. Women are five times more likely to develop this condition than men.
A hallmark clinical manifestation of Graves’ disease is exophthalmos—an abnormal eye appearance where the eyeballs are forced outward due to increased fat deposits and fluid behind the eyes.
Clinical Manifestations of Hyperthyroidism
Because the body is in a hypermetabolic state, patients often present with:
Cardiovascular: Tachycardia, hypertension, palpitations, and dysrhythmias.
Integumentary: Warm, moist skin, hair loss, and vitiligo.
Neurological: Insomnia, delirium, and difficulty focusing the eyes.
Other: Heat intolerance, rapid speech, and weight loss despite increased appetite.
Exam Tip: When assessing a patient with hyperthyroidism, always check for "bruits" via auscultation over the thyroid gland, which can indicate increased vascularity.
Acute Complications: Thyrotoxicosis
Acute thyrotoxicosis is a medical emergency characterized by severe tachycardia, heart failure, and hyperthermia (up to 106° F / 41.1° C). Patients may experience agitation, seizures, delirium, or coma.
Hypothyroidism
In contrast to hyperthyroidism, hypothyroidism is a deficiency of thyroid hormones that causes a general slowing of the metabolic rate. It is more common in women than in men.
Etiology and Manifestations
Common causes include iodine deficiency, Hashimoto's thyroiditis, or the side effects of treatments for hyperthyroidism. Clinical signs include:
Metabolic: Weight gain and increased cholesterol/triglycerides.
Neurological: Fatigue, lethargy, somnolence, and slowed speech.
Physical Appearance: Puffy face and hair loss.
Gastrointestinal: Constipation.
Myxedema Coma
The most severe complication of hypothyroidism is myxedema coma, often precipitated by infection, cold exposure, or trauma. This state is characterized by impaired consciousness, subnormal temperature, hypotension, and cardiovascular collapse.
This diagram illustrates the contrasting symptoms of hyperthyroidism (overactive thyroid) and hypothyroidism (underactive thyroid), focusing on metabolism, heart rate, and temperature regulation.
Diagnostics and Nursing Management
Diagnostic Studies
To differentiate between these states, clinicians utilize several tests:
TSH Levels: TSH increases in primary hypothyroidism and decreases in secondary hypothyroidism.
Free T4 and Total T3/T4: Used to measure circulating hormone levels.
Radioactive Iodine Uptake (RAIU): Helps identify the cause of hyperthyroidism.
Antibodies: Thyroid peroxidase (TPO) antibodies can indicate autoimmune origins.
Nursing Implementation: Hyperthyroidism
Nursing care for hyperthyroidism focuses on symptom relief and preventing complications.
Nutrition: A high-calorie diet (4000–5000 cal/day) with 6 meals and snacks is recommended. Avoid caffeine and highly seasoned foods.
Exophthalmos Care: Apply artificial tears, use dark glasses, and elevate the head of the bed.
Post-Thyroidectomy Care: Monitor for hemorrhage, laryngeal nerve damage (stridor), and hypocalcemia. Ensure oxygen and suction equipment are at the bedside.
Nursing Implementation: Hypothyroidism
Medication: Lifelong therapy with Levothyroxine (Synthroid) is standard. Start with a low dose and monitor for signs of excess (chest pain, nervousness).
Nutrition: A low-calorie diet is typically advised.
Myxedema Coma Care: Requires IV thyroid hormone replacement, cardiac monitoring, and potentially mechanical ventilation.
Summary of Clinical Differences
Feature
Hyperthyroidism
Hypothyroidism
Metabolic Rate
Increased
Decreased
Temperature
Heat intolerance / Hyperthermia
Cold intolerance
Weight Change
Weight loss
Weight gain
Heart Rate
Tachycardia
Bradycardia
Speech
Rapid
Slowed
Clinical Note: In the event of a thyroidectomy, the most critical assessment is maintaining a patent airway. Always have a tracheostomy tray available in the room for immediate use if laryngeal edema occurs.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.