Understanding Diabetic Ketoacidosis (DKA) and Hyperglycemic Hyperosmolar Nonketotic Syndrome (HHNS)
This content explains the distinct pathophysiologies, clinical presentations, and treatment protocols for Diabetic Ketoacidosis (DKA) and Hyperglycemic Hyperosmolar Nonketotic Syndrome (HHNS), two severe acute complications of diabetes mellitus. It differentiates between Type 1 and Type 2 diabetes and outlines critical
Diabetes mellitus is a complex metabolic disorder characterized by the body's inability to properly regulate blood glucose levels. While both Type 1 and Type 2 diabetes involve hyperglycemia, the underlying mechanisms, clinical presentations, and life-threatening complications differ significantly. Understanding these distinctions is critical for medical professionals, particularly when distinguishing between the two most severe acute complications: Diabetic Ketoacidosis (DKA) and Hyperglycemic Hyperosmolar Nonketotic Syndrome (HHNS).
Understanding the Foundations: Type 1 vs. Type 2 Diabetes
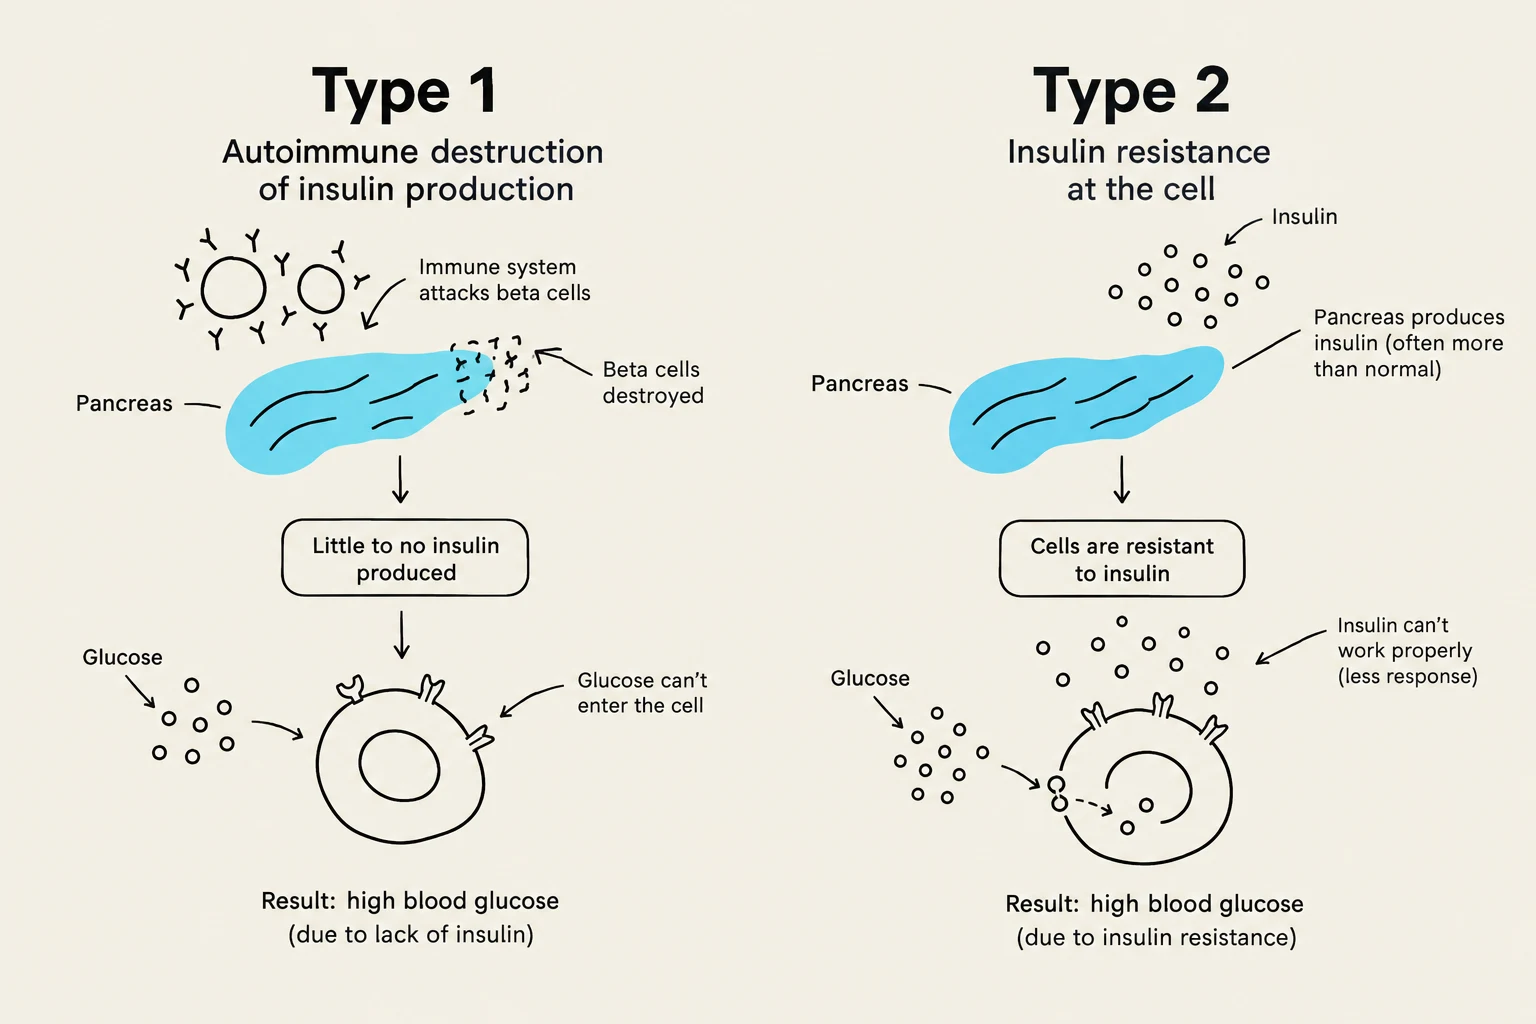
The primary difference between the two types of diabetes lies in the presence or function of insulin. Insulin acts as the "key" that puts glucose and potassium into the cells.
Type 1 Diabetes Pathophysiology
Type 1 diabetes is an autoimmune condition where the body attacks its own insulin-producing cells. Because the body produces no insulin, it is often described as "faster and younger" in onset. Without insulin, glucose remains in the bloodstream, leading to high sugar levels and the production of ketones.
Type 2 Diabetes Pathophysiology
Type 2 diabetes is characterized by "insulin resistance," where the body's insulin receptors do not work effectively. This is often associated with lifestyle factors such as a sedentary lifestyle and high simple sugar intake. Type 2 is generally a "slower and older" onset condition.
Diagrams illustrating the mechanisms of Type 1 and Type 2 diabetes, showing autoimmune destruction of insulin production in Type 1 and insulin resistance at the cell in Type 2, both resulting in high blood glucose.
Diabetic Ketoacidosis (DKA)
DKA is a medical emergency most commonly associated with Type 1 diabetes. It is often triggered by "the 4 S's": Sepsis (infection), Sickness (stomach virus/flu), Stress (surgery), or Skipping insulin.
Clinical Presentation
DKA follows a specific pattern that can be remembered using the mnemonic DKA:
D - Dry & High Sugar: Significant hyperglycemia.
K - Ketones & Kussmaul Respirations: The presence of ketones leads to "fruity breath" and Kussmaul respirations, which are deep, rapid, and regular breaths used by the body to compensate for acidity.
A - Abdominal Pain & Acidosis: Patients often experience abdominal pain and metabolic acidosis, where the blood pH drops below the normal range of 7.35–7.45.
Electrolyte Imbalances: The Potassium Paradox
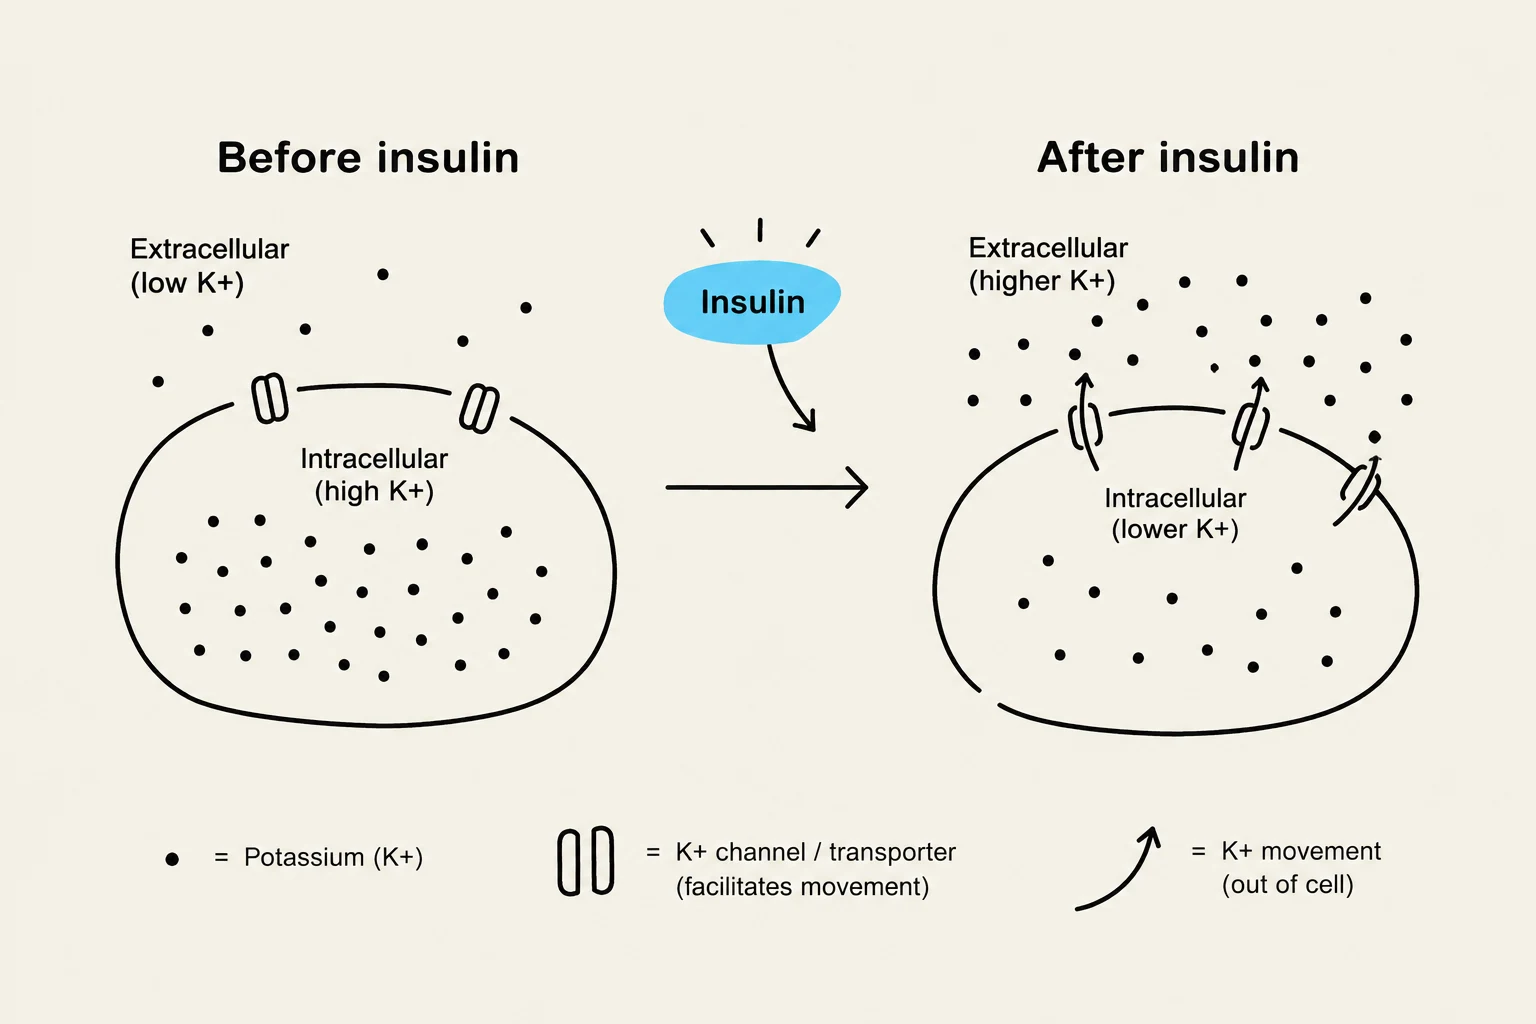
A critical aspect of DKA is the movement of potassium ($K^+$). Insulin's job is to move both sugar and potassium into the cells. As insulin deficiency occurs, potassium shifts out of the cells and into the bloodstream, causing hyperkalemia (high potassium).
However, as treatment begins and insulin is administered, potassium is driven back into the cells. This can lead to a dangerous drop in serum potassium, known as hypokalemia.
Diagram illustrating the effect of insulin on potassium (K+) levels inside and outside a cell. Before insulin, extracellular K+ is low and intracellular K+ is high. After insulin binds, K+ channels open, facilitating the movement of K+ out of the cell, leading to lower intracellular K+ and higher extracellular K+.
HHNS is the more severe complication typically seen in Type 2 diabetes. While it shares the feature of extreme hyperglycemia, it lacks the acidic component of DKA.
Clinical Presentation
HHNS can be remembered by the mnemonic HHNS:
H - Highest Sugar: Blood glucose levels are often much higher than in DKA.
H - Higher Fluid Loss: Extreme dehydration occurs due to osmotic diuresis.
N - No Ketones/No Acid: Unlike DKA, there is no fruity breath and no metabolic acidosis.
S - Slower Onset & Stable Potassium: The onset is more gradual, and potassium levels tend to remain within the normal range (3.5–5.0).
Patients with HHNS are at high risk of death from hypovolemia (low blood volume), whereas DKA patients are more likely to die from hypokalemia.
Treatment Protocols and Nursing Interventions
Treatment for both conditions requires a systematic approach focusing on hydration, glucose control, and electrolyte stabilization.
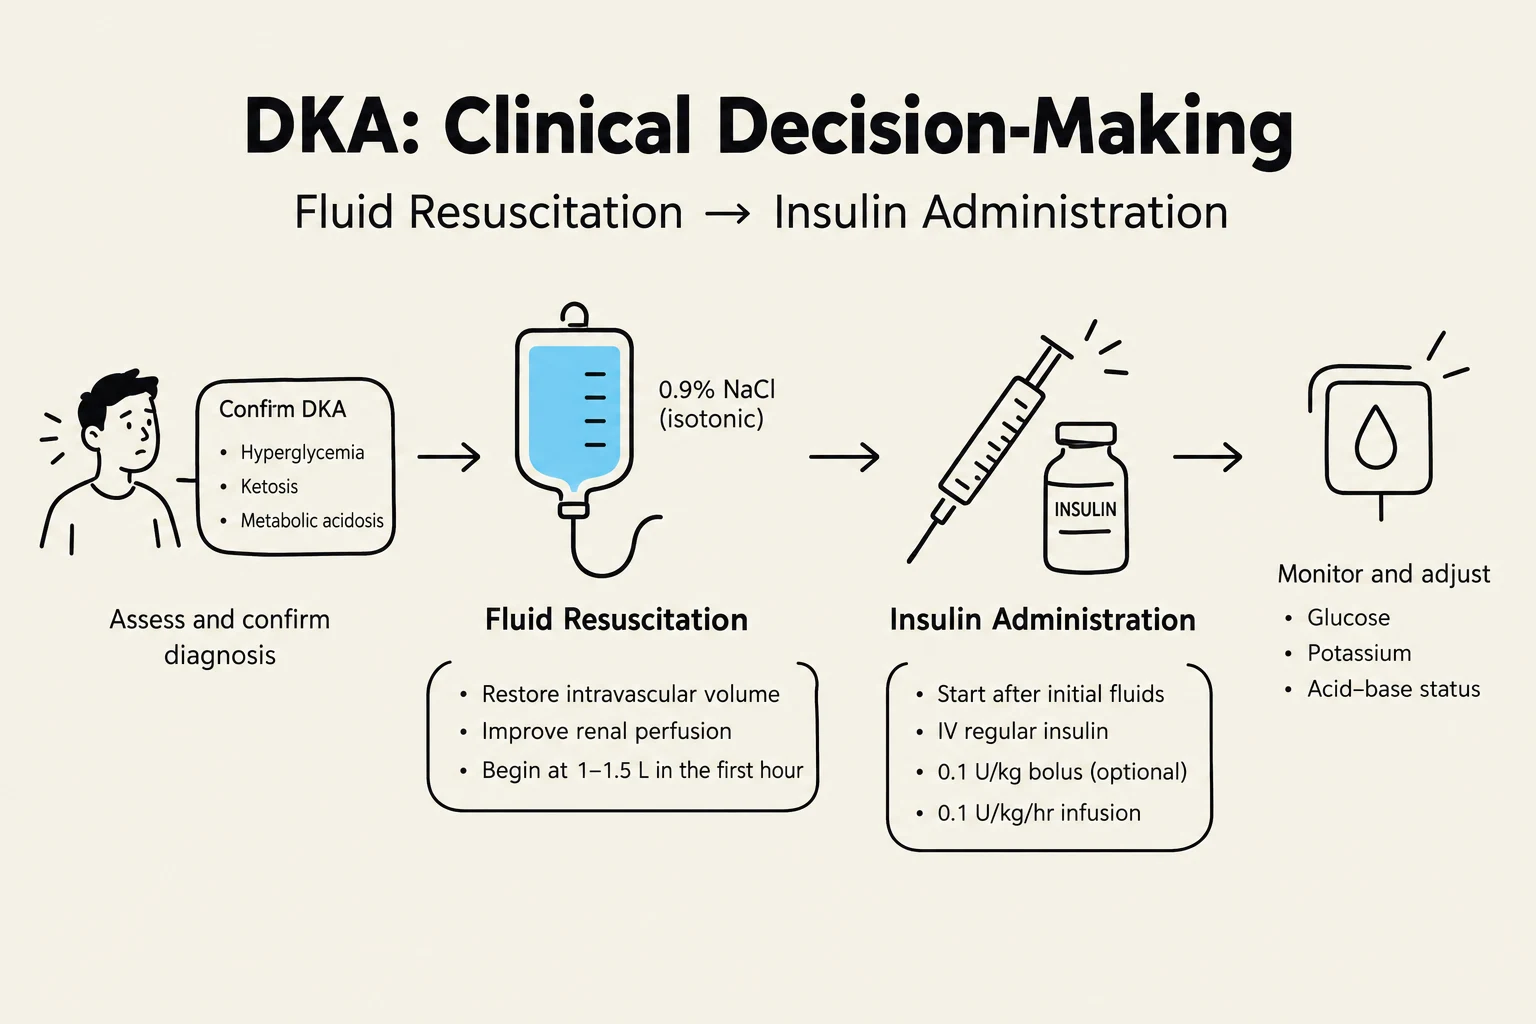
1. Fluid Resuscitation and Hydration
The first priority in both DKA and HHNS is addressing dehydration.
Initial Step: Administer 0.9% Normal Saline (NS).
Subsequent Step: For HHNS, once stabilized, transition to hypotonic fluids.
DKA Specifics: Once blood glucose drops below 200 mg/dL (or ketones resolve), the protocol shifts to subcutaneous insulin and 1/2 Normal Saline with D5W.
2. Insulin Administration
Insulin is used to "kill the sugar," but it must be done slowly to "land the plane smooth and smooth".
DKA Protocol: If blood glucose is over 250 mg/dL, use IV Regular insulin only (via bolus or titration).
Monitoring: Blood glucose must be monitored hourly during treatment.
3. Potassium Replacement
Because insulin drives potassium into the cells, potassium replacement is often necessary even if the patient's initial lab values appear normal.
Safety First: Always place the patient on a heart monitor before administering potassium. Never push potassium IV, as this can cause death.
Administration: Use an IV pump for slow infusion, typically limited to 10–20 mg per hour.
NCLEX Tip: Potassium and the Heart
Monitor the ECG for changes in potassium levels:
Hyperkalemia (High K+): Peaked T-waves and ST elevation.
Hypokalemia (Low K+): Flat T-waves, ST depression, and U-waves.
4. Re-assessment of Success
To ensure the patient is responding to hydration and treatment, monitor the following:
Blood Pressure & Capillary Refill: BP should be stable and capillary refill should be ≤ 3 seconds.
Urine Output: Should be at least 30 ml/hr.
Specific Gravity: Should be low (1.005–1.030).
This diagram illustrates the clinical decision-making process for DKA, covering fluid resuscitation and insulin administration.
Patient Education: Sick Day Management
A vital component of preventing DKA is educating patients on "Sick Day Insulin". During illness (such as a stomach virus or flu), the body's stress response causes glucose levels to rise, even if the patient is not eating. Patients must be taught that they should not skip their insulin during illness, as this significantly increases the risk of developing DKA.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.