Understanding Diabetes Mellitus and Insulin Function
An overview of the pathophysiology of Type 1 and Type 2 Diabetes Mellitus, including the roles of insulin and glucagon in glucose regulation, the mechanisms of each diabetes type, and their associated complications.
Diabetes Mellitus is one of the most prevalent metabolic disorders in modern medicine, affecting a significant portion of the global population. At its core, the disease represents a breakdown in the body's ability to regulate blood glucose levels, leading to systemic complications that can affect nearly every organ system. To understand how diabetes develops, we must first understand the delicate balance between glucose regulation and the hormones that control it.
The Biochemistry of Glucose Regulation
In a healthy individual, the body maintains blood glucose within a narrow range to ensure a steady supply of energy for cells, particularly the brain, which relies on a constant glucose supply. This regulation is managed by a tug-of-war between two primary peptide hormones: insulin and glucagon.
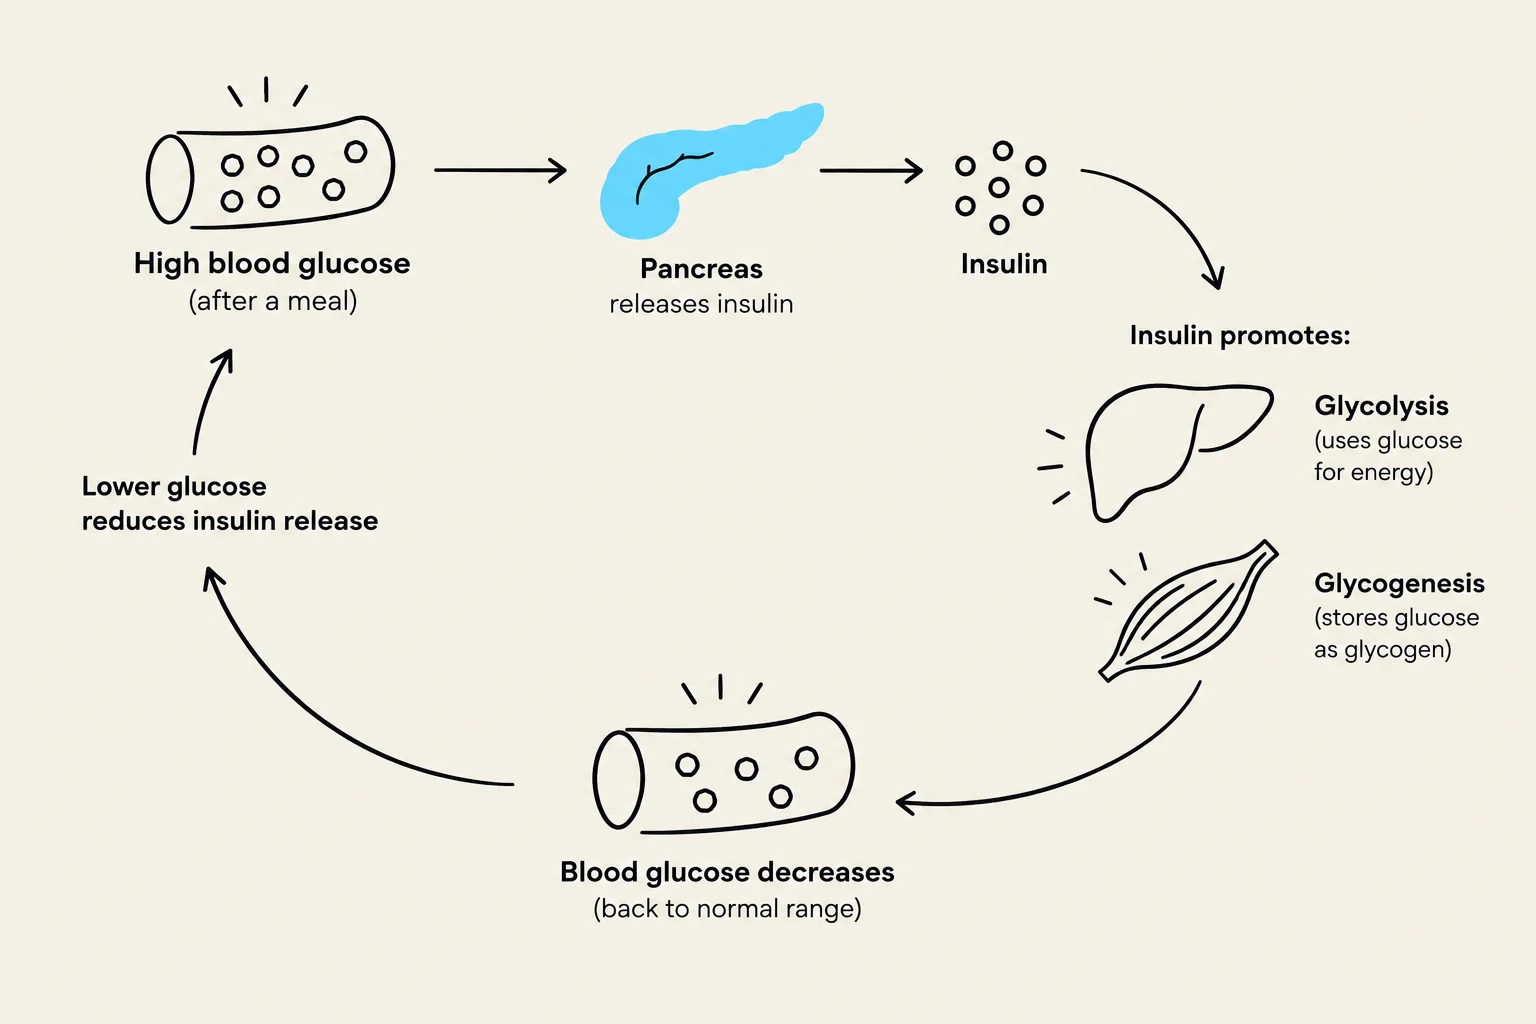
Insulin is the anabolic hormone responsible for lowering blood glucose. It acts like a "key" that binds to specific receptors on cell membranes, allowing glucose to enter cells—most notably muscle and fat cells. Once inside, insulin promotes several energy-storing processes:
Glycolysis: The breakdown of glucose to produce immediate energy.
Glycogenesis: The conversion of excess glucose into glycogen for storage in the liver and muscles.
Conversely, when blood sugar drops (such as during fasting or exercise), the pancreas releases glucagon. This hormone triggers catabolic processes to raise blood glucose:
Glycogenolysis: The breakdown of stored glycogen back into glucose.
Gluconeogenesis: The formation of new glucose from non-carbohydrate sources, such as amino acids.
This diagram illustrates the regulation of blood glucose levels by insulin. After a meal, high blood glucose triggers the pancreas to release insulin. Insulin then promotes glycolysis in cells for energy and glycogenesis in the liver and muscles to store glucose as glycogen. As blood glucose levels decrease back to normal, insulin release is reduced.
Type 1 Diabetes: Absolute Insulin Deficiency
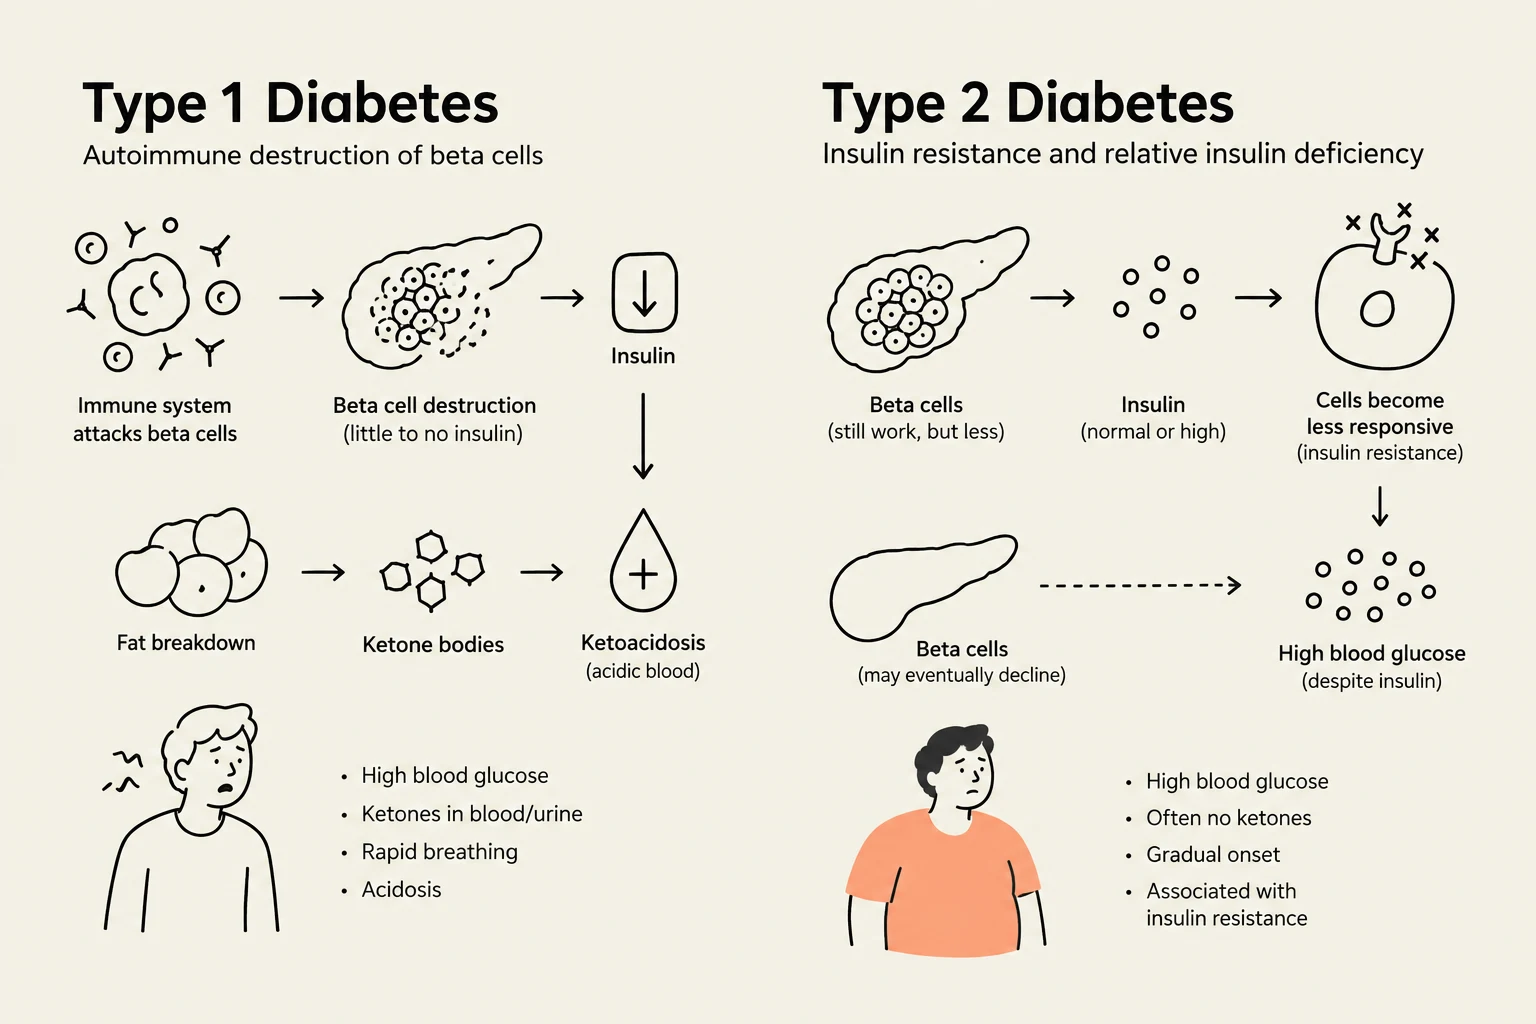
Type 1 Diabetes is characterized by an absolute insulin deficiency. This occurs when the body's immune system destroys the insulin-producing beta cells in the pancreas. While it was historically called "juvenile-onset" diabetes, it can appear at any age, though it often has an abrupt onset in children or young adults.
Because there is no insulin to "open the door" to the cells, the body enters a state of cellular starvation despite having high levels of glucose in the bloodstream. To compensate, the body begins rapid lipolysis (the breakdown of fat) to find alternative fuel. This massive influx of fatty acids to the liver results in the production of keto acids (ketones).
Clinical Manifestations of Type 1
The accumulation of keto acids leads to metabolic acidosis, a life-threatening condition where the blood pH drops. This often culminates in Diabetic Ketoacidosis (DKA), characterized by:
Polyphagia: Excessive hunger as cells starve for energy.
Polyuria: Excessive urination caused by osmotic diuresis, where high glucose levels pull water into the urine.
Polydipsia: Excessive thirst resulting from the dehydration caused by polyuria.
Clinical Note: Electrolyte Shifts
When treating DKA with insulin, be aware of potassium shifts. Insulin "chases" potassium into the cells, which can lead to hypokalemia (low blood potassium). Conversely, the acidosis itself can cause hyperkalemia (high blood potassium) as the body tries to exchange hydrogen ions for potassium to maintain electrical balance.
Type 2 Diabetes: Insulin Resistance and Progression
Unlike Type 1, Type 2 Diabetes is characterized by insulin resistance. In this state, the body's tissues—particularly fat and muscle—do not respond effectively to the insulin being produced. This is strongly associated with obesity and a sedentary lifestyle.
The progression of Type 2 is often insidious (slow), described as the "frog in boiling water" because the symptoms develop so gradually that the patient may not realize they are ill for years. Prolonged hyperglycemia can eventually damage the insulin receptors and impair the pancreatic beta cells, leading to a relative insulin deficiency.
Hyperglycemic Hyperosmolar State (HHS)
While Type 1 is associated with DKA, Type 2 patients are more prone to Hyperglycemic Hyperosmolar State (HHS). HHS involves extreme hyperglycemia and profound dehydration without the significant ketoacidosis seen in Type 1, because there is usually just enough insulin present to prevent massive fat breakdown.
This illustration compares Type 1 and Type 2 Diabetes, detailing their causes, mechanisms, and symptoms.
Clinical Monitoring and Complications
Monitoring Glucose Control
To manage diabetes, clinicians use several tools:
HbA1c (Glycated Hemoglobin): This test provides an average of blood glucose levels over the previous three months, offering a long-term view of glycemic control.
Blood Glucose Monitoring: Essential for detecting immediate fluctuations, such as hypoglycemia (low blood sugar) or hyperglycemia (high blood sugar).
Acute Fluctuations: The Dawn Phenomenon and Somogyi Effect
Patients may experience unexplained morning hyperglycemia due to two distinct phenomena:
Dawn Phenomenon: A natural rise in blood glucose in the early morning hours caused by the release of cortisol.
Somogyi Effect: A "rebound" hyperglycemia that occurs after an undetected period of hypoglycemia during the night.
Chronic Complications
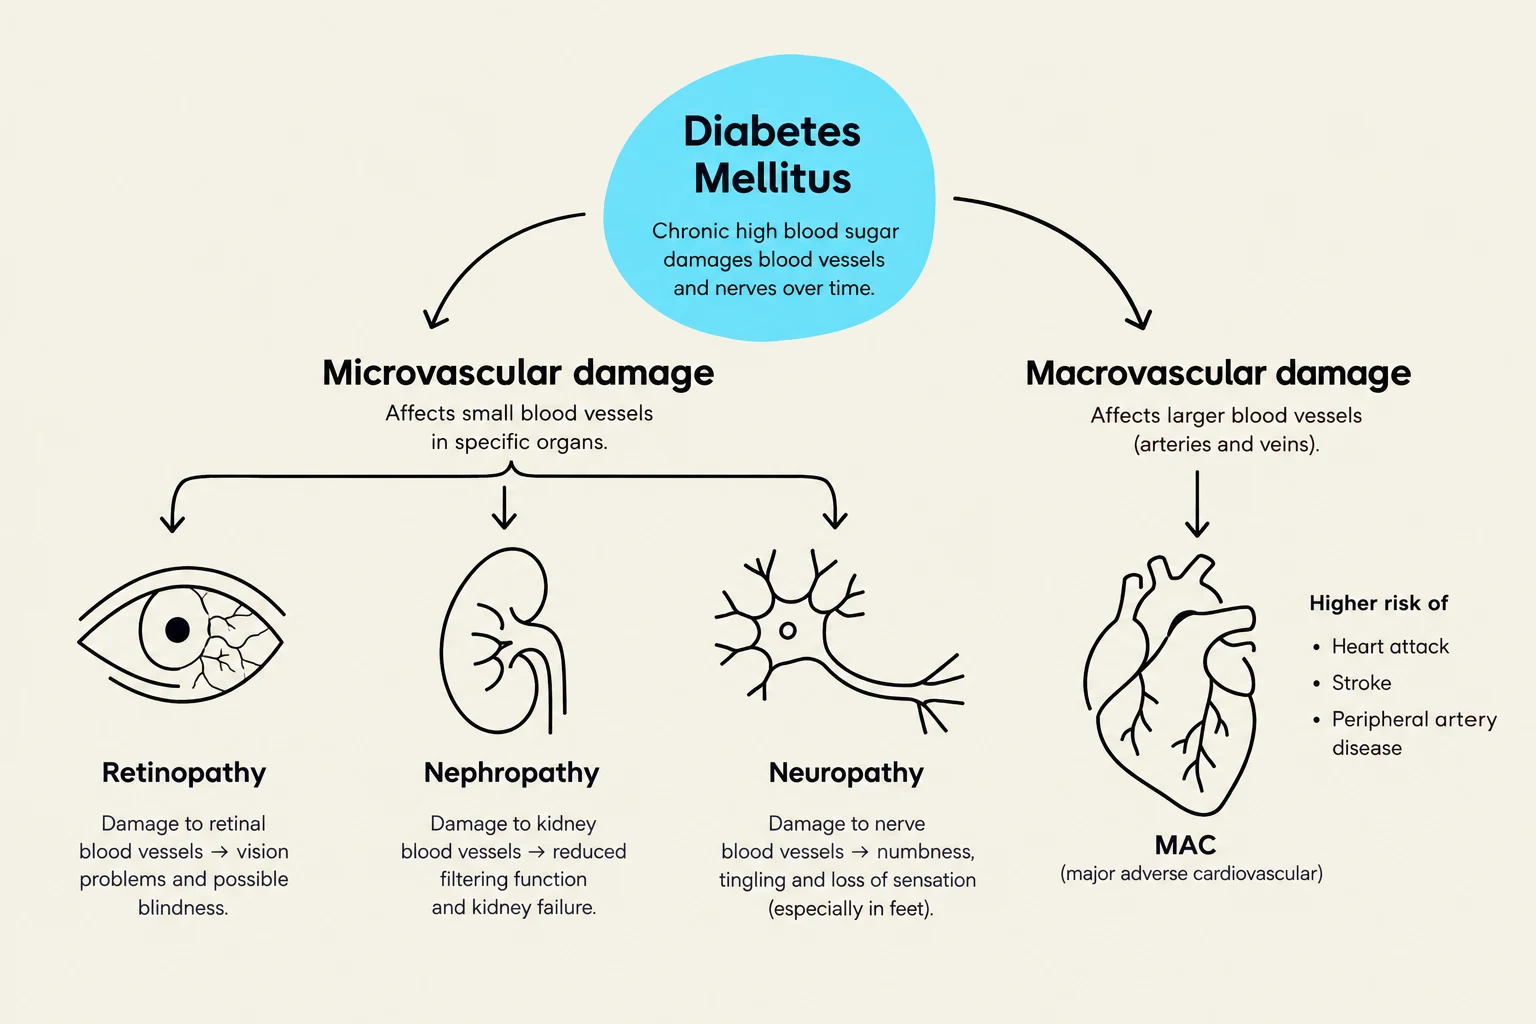
Chronic hyperglycemia acts like "superglue" in the body, damaging vessels and nerves over time.
Microvascular Damage: High sugar levels damage small vessels, leading to diabetic retinopathy (blindness), diabetic nephropathy (kidney failure), and neuropathy (nerve damage).
Macrovascular Damage: Damage to larger vessels increases the risk of atherosclerosis, leading to coronary artery disease, stroke, and peripheral vascular disease.
Neuropathy: This can manifest as autonomic dysfunction (affecting digestion, bladder control, or heart rate) or sensory neuropathy, where patients experience burning pain or lose the ability to feel injuries, such as those on the feet.
This diagram illustrates the microvascular and macrovascular complications of Diabetes Mellitus, including retinopathy, nephropathy, neuropathy, and major adverse cardiovascular events.
Exam Tip: Hypoglycemia Recognition
When assessing a patient for hypoglycemia, look for the "adrenergic" response (tremors, palpitations, diaphoresis/sweating) and the "neuroglycopenic" response (confusion, slurred speech, or lethargy).
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.