Understanding and Managing Gastroesophageal Reflux Disease (GERD)
This content explains Gastroesophageal Reflux Disease (GERD), a chronic digestive disorder where stomach acid flows back into the esophagus. It details the pathophysiology, common symptoms like heartburn and regurgitation, diagnostic procedures such as EGD, and management strategies including dietary changes, lifestyle
Gastroesophageal Reflux Disease (GERD) is a chronic digestive disorder that occurs when stomach acid frequently flows back into the tube connecting your mouth and stomach (the esophagus). This backwash (acid reflux) can irritate the lining of the esophagus, leading to various symptoms ranging from mild discomfort to severe mucosal damage. Understanding the relationship between diet, lifestyle, and the physiological mechanics of the digestive tract is essential for effective management and the prevention of long-term complications.
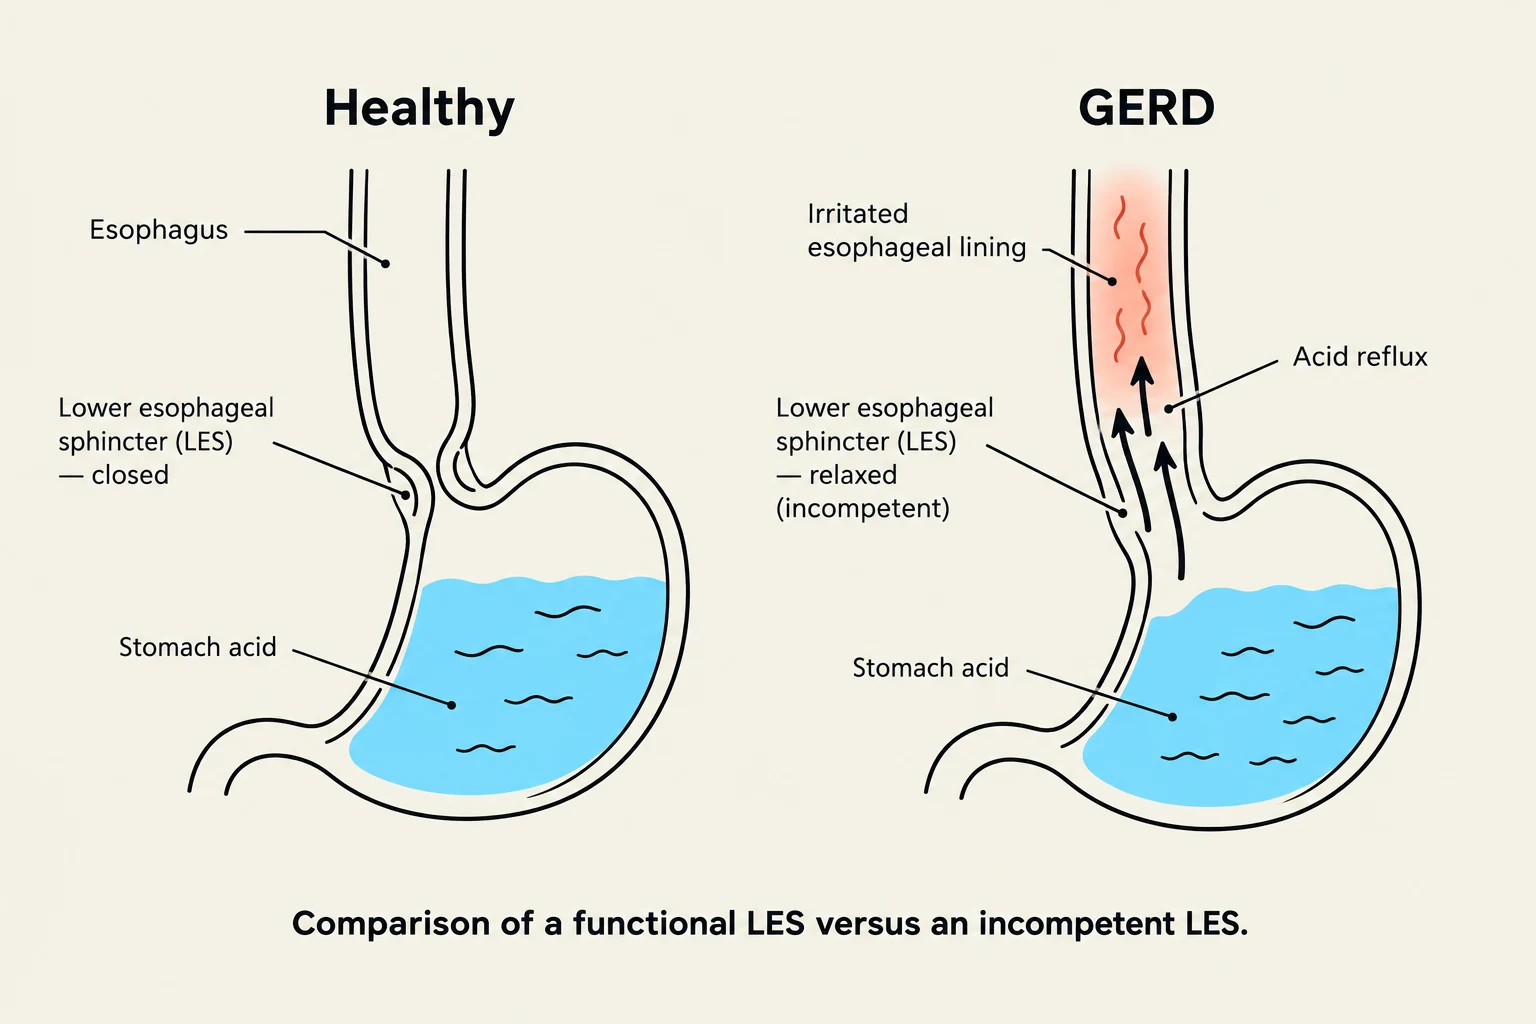
Comparison of a functional Lower Esophageal Sphincter (LES) versus an incompetent LES, illustrating the difference between a healthy stomach and GERD.
Pathophysiology and Etiology
The primary mechanism behind GERD is an incompetent lower esophageal sphincter (LES). The LES acts as a muscular valve at the junction of the esophagus and the stomach; under normal conditions, it opens to allow food into the stomach and closes tightly to prevent acid from escaping upward. When this sphincter fails to close properly or relaxes inappropriately, gastric contents can reflux into the esophagus.
Several etiological factors contribute to an incompetent LES or increased intra-abdominal pressure, which exacerbates reflux:
Physical Factors: Obesity and pregnancy increase pressure on the stomach.
Chemical/Dietary Triggers: Nicotine, alcohol, caffeine, and certain specific foods.
Psychological Factors: Stress and anxiety can exacerbate the reflux process.
Clinical Manifestations and Assessment
Patients presenting with GERD may experience a wide array of symptoms. The most common include:
Pyrosis (Heartburn): A burning sensation in the chest.
Dyspepsia: Indigestion or discomfort in the upper abdomen.
Regurgitation: The feeling of acid or food returning to the throat.
Dysphagia: Difficulty swallowing.
Beyond these classic symptoms, GERD can manifest through respiratory or otolaryngologic (ear, nose, and throat) issues, such as asthma, chronic bronchitis, pneumonia, or even dental erosion caused by acid exposure.
Diagnostic Procedures
If symptoms are frequent (more than twice a week for mild symptoms or once a week for moderate-to-severe symptoms), healthcare providers may recommend an Esophagogastroduodenoscopy (EGD). This procedure allows for direct visualization of the esophageal lining and the ability to perform a biopsy to check for complications.
Clinical Alert: Complications
Chronic, untreated GERD can lead to significant mucosal damage, including esophagitis (inflammation of the esophagus) and Barrett’s Esophagus, a condition where the esophageal lining changes to resemble the lining of the intestine, increasing the risk of malignancy.
Management: Lifestyle and Nutritional Interventions
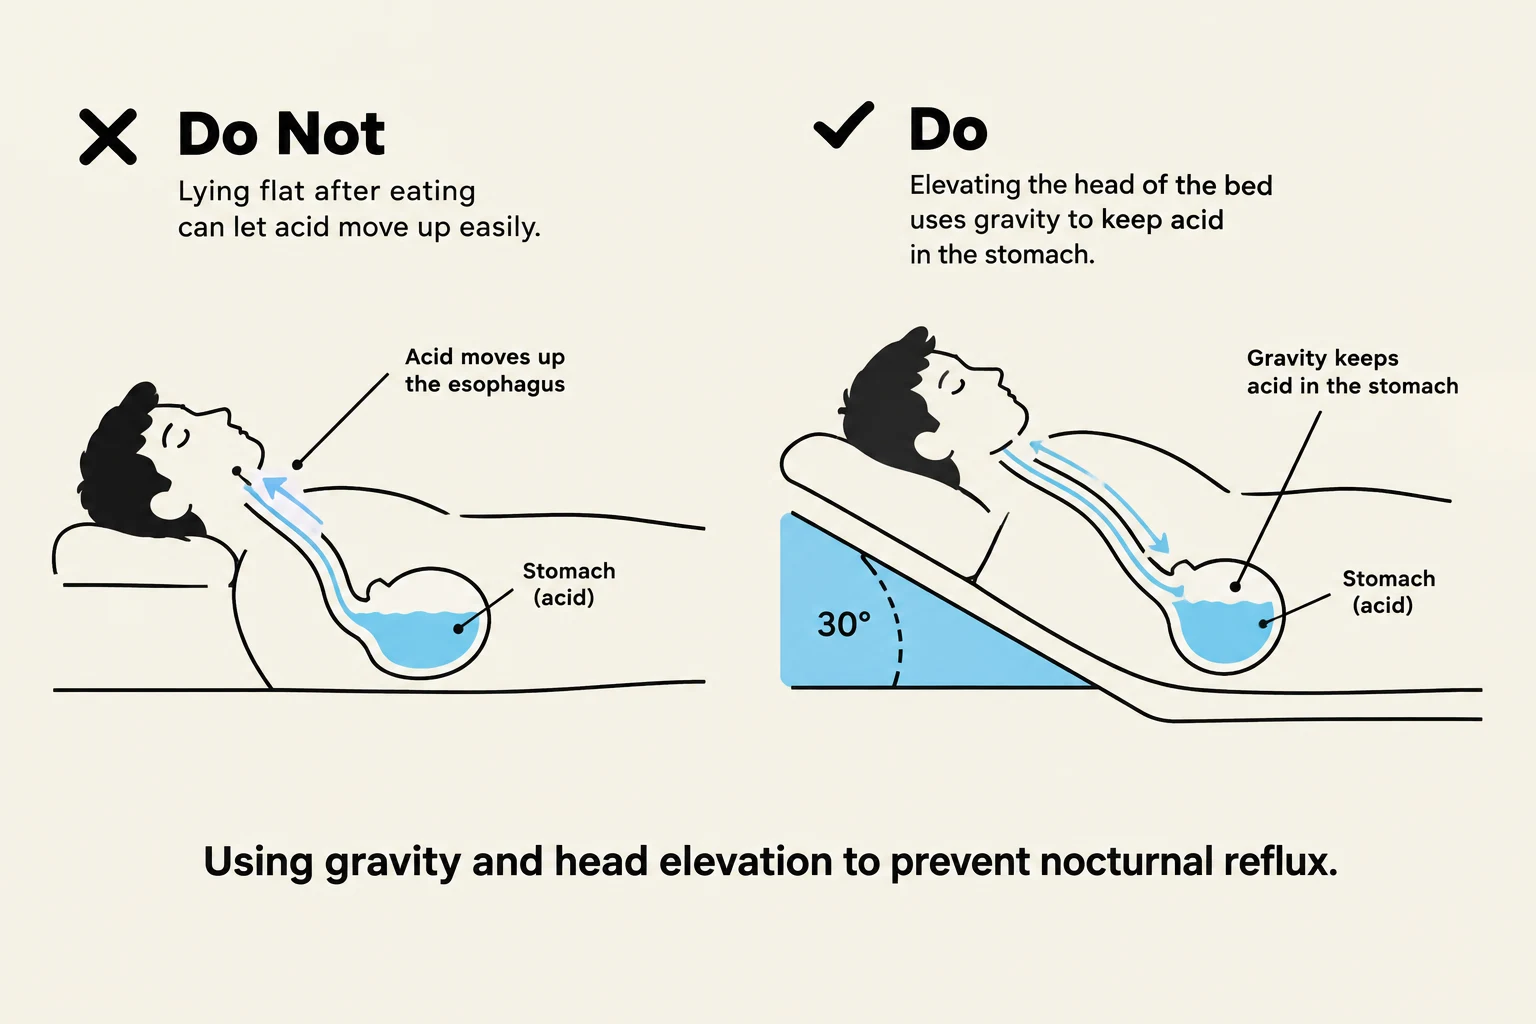
This illustration demonstrates how elevating the head of the bed can help prevent nocturnal reflux by using gravity to keep stomach acid in the stomach.
Because diet and lifestyle directly impact LES function and gastric pressure, these interventions are considered a cornerstone of GERD management.
Dietary and Meal Timing Strategies
Avoid Trigger Foods: Limit or eliminate caffeine, alcohol, and other known irritants.
Manage Meal Timing: Do not eat within 3 hours of bedtime, and remain upright for at least 2–3 hours after eating to use gravity to keep acid down.
Fluid Intake: Rather than drinking large amounts of liquid during meals, which can increase stomach volume, try drinking fluids between meals.
Small, Frequent Meals: While not explicitly listed as a single bullet, the emphasis on avoiding large volumes and managing timing supports the use of smaller portions to reduce pressure.
Postural and Physical Changes
Elevation: Keep the head of the bed (HOB) elevated greater than 30 degrees to prevent nocturnal reflux.
Weight Management: Maintaining a healthy weight reduces the physical pressure exerted on the LES.
Clothing: Avoid tight-fitting clothes that compress the abdomen.
Other Tips: Chewing gum or sucking on lozenges may help, and smoking cessation is vital.
Pharmacological Management
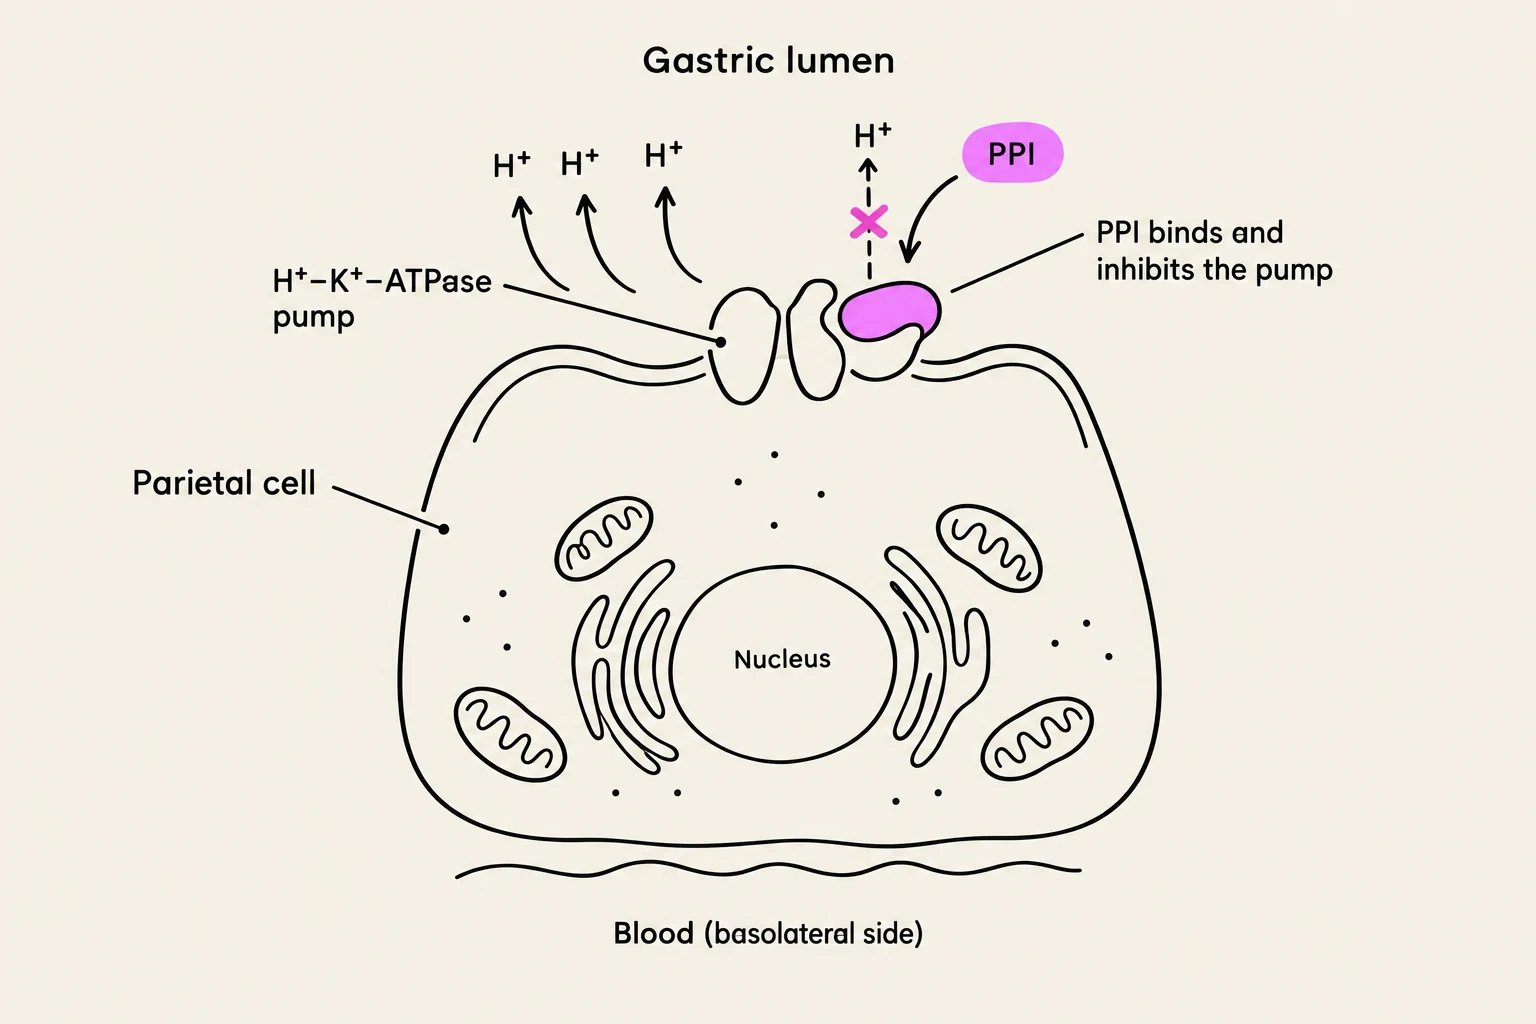
Diagram illustrating the mechanism of action of a proton pump inhibitor (PPI) on a parietal cell, showing how it binds to and inhibits the H+-K+-ATPase pump, reducing acid secretion into the gastric lumen.
Medications are used to either reduce the acidity of the gastric contents or improve the movement of food through the digestive tract.
Medication Class
Example
Mechanism/Use
Nursing/Patient Education
Proton Pump Inhibitors (PPIs)
Omeprazole (Prilosec)
Most effective for healing esophagitis; reduces acid production.
Take before the first meal of the day; long-term use should be avoided.
H2 Receptor Blockers
Famotidine (Pepcid)
Reduces symptoms and promotes some healing.
Used for symptom control.
Antacids
Maalox, Mylanta
Neutralizes pH for mild, acute symptoms.
Take 1–3 hours after meals; note that they may interfere with the absorption of other medications.
Prokinetics
Metoclopramide (Reglan)
Increases LES pressure and improves gastric emptying.
Helps improve regurgitation and vomiting.
Surgical and Advanced Interventions
For patients who do not respond to lifestyle changes and medications, or for those with severe complications, surgical options may be considered.
Laparoscopic Fundoplication: A surgical procedure to strengthen the LES. Patients should be aware that they may experience dysphagia (difficulty swallowing) during the first month following the operation.
LINX Reflux Management System: A device implanted around the LES to help it stay closed. Important Safety Note: Patients with the LINX system must avoid MRIs.
Endoscopic Mucosal Resection (EMR): This is primarily used as a diagnostic tool to assess the extent of mucosal changes.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.