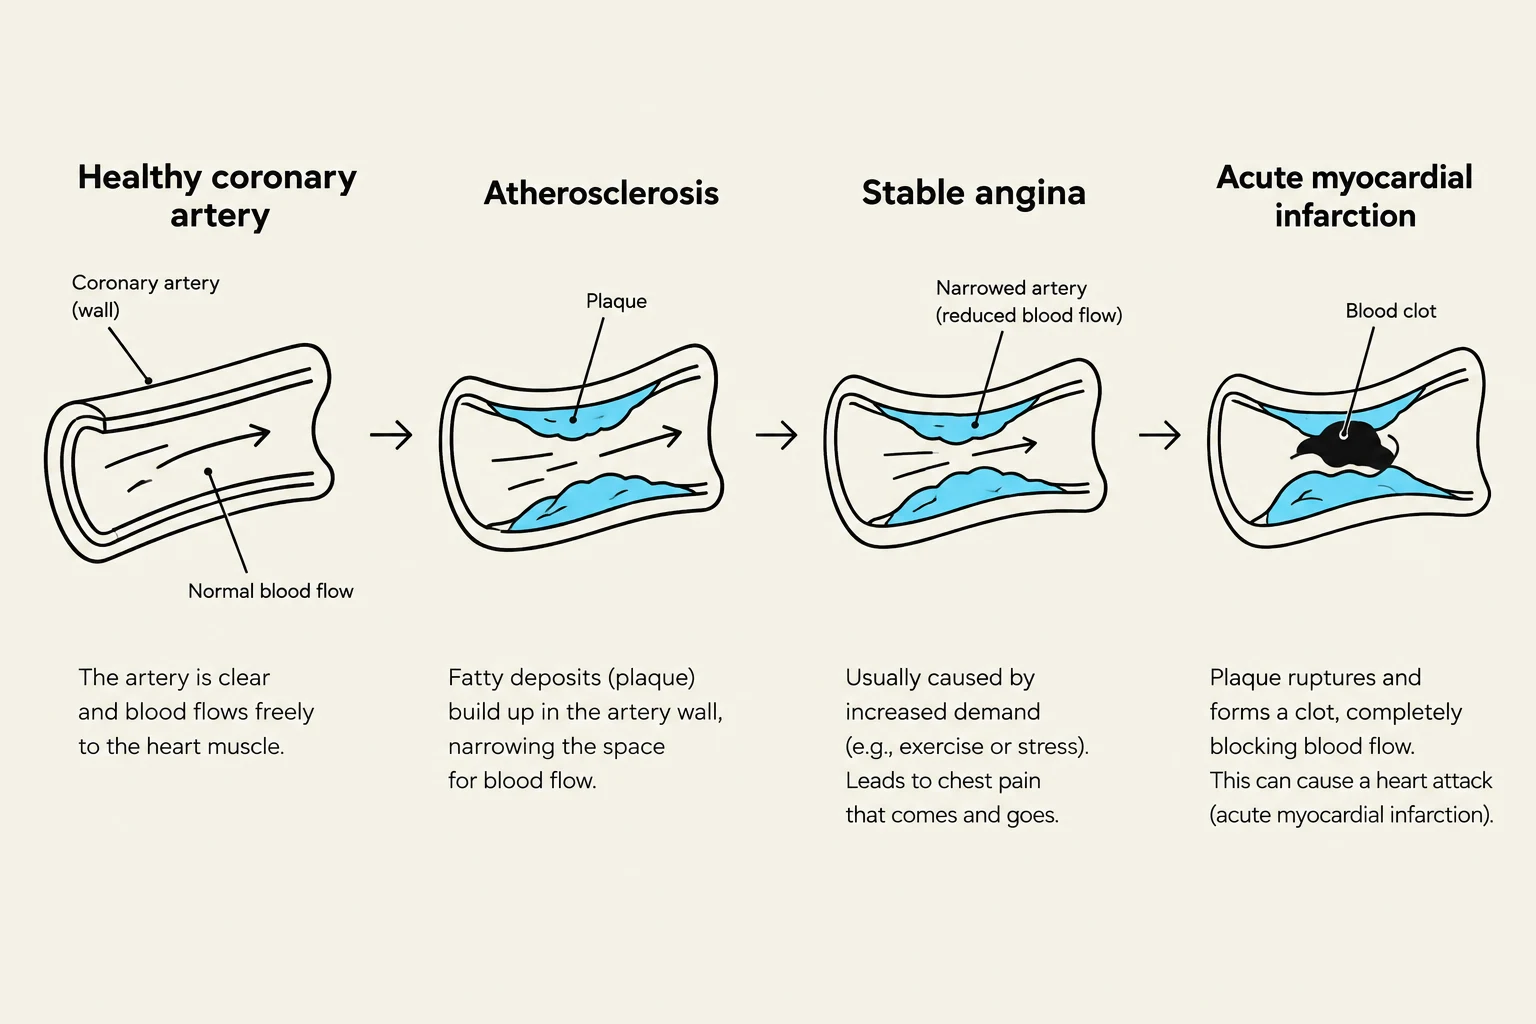
This content provides a comprehensive overview of coronary heart disease (CHD), also known as coronary artery disease (CAD) or ischemic heart disease. It details the disease continuum from stable angina to acute coronary syndrome (ACS) and myocardial infarction (MI), explaining the underlying mechanism of atheroscleros
Coronary heart disease (CHD) is a critical area of cardiovascular health that requires a deep understanding of anatomy, risk management, and acute intervention. Often referred to interchangeably as coronary artery disease (CAD) or ischemic heart disease, this condition occurs when the coronary arteries—the vessels responsible for perfusing the heart muscle with oxygenated blood—become compromised. When these vessels are blocked, the heart muscle suffers from a lack of oxygen, which can lead to a spectrum of clinical outcomes ranging from predictable chest pain to life-threatening myocardial infarction.
Understanding the Disease Continuum
Coronary artery disease is best understood as a continuum of severity rather than a single static event. At one end of the spectrum is stable angina, a chronic condition where the patient experiences predictable chest pain (angina pectoris) during exertion. This is typically caused by fixed atherosclerotic plaques that limit blood flow during periods of increased demand.
As the condition progresses and becomes unpredictable, it enters the realm of acute coronary syndrome (ACS). ACS is an umbrella term used when symptoms become unstable, signaling that a patient is at high risk for an acute myocardial infarction (MI). In an acute MI, there is actual heart muscle death, which can be identified through laboratory testing.
The underlying mechanism for almost all cases of CAD is atherosclerosis, commonly known as the "hardening of the arteries". This process involves the buildup of plaque within the arterial walls, narrowing the lumen and restricting blood flow.
Diagram illustrating the progression of coronary artery health from a healthy state to atherosclerosis, stable angina, and acute myocardial infarction due to plaque buildup and blood clots.
Risk Factors: Modifiable vs. Non-Modifiable
To effectively care for these patients, clinicians must distinguish between what can be changed and what cannot.
Non-Modifiable Risk Factors
These are inherent characteristics that a patient cannot alter:
Age: The risk of CAD increases as a person gets older.
Gender: Historically, male patients have been at a higher risk than females.
Family History: A genetic predisposition, especially if younger relatives have developed heart disease, significantly increases risk.
Modifiable Risk Factors
These are the primary targets for nursing interventions and patient education:
Serum Lipids: Elevated cholesterol and triglycerides contribute to plaque formation.
Hypertension: High blood pressure causes physical damage to the arterial system over time.
Smoking: Tobacco use is directly proportional to risk. Importantly, the benefits of smoking cessation begin almost immediately.
Lifestyle Factors: Obesity (particularly "apple-shaped" abdominal obesity), physical inactivity, and chronic stress or depression are all significant contributors.
Exam Tip: When teaching patients about smoking cessation, emphasize that switching to "light" or filtered cigarettes does not reduce the risk. The only effective intervention is complete cessation.
Diagnostic Strategies
When a patient presents with symptoms of angina—which can manifest as substernal pain, radiation to the neck, or even the left arm, both arms, or epigastric area—clinicians must determine the cause.
To differentiate between cardiac pain and non-cardiac issues like gastric reflux, providers check serum troponins. Elevated troponin levels indicate heart muscle death.
Diagnostic testing often follows a tiered approach:
EKG: The initial step to assess electrical activity.
Stress Testing: This can be an exercise test on a treadmill or a pharmacological stress test for patients unable to exercise physically. The drug used in a pharmacological test increases heart rate and contractility to simulate stress.
Cardiac Catheterization: If a patient is deemed high risk, they may undergo catheterization to visualize blockages directly.
This diagram illustrates the diagnostic process for angina, starting with patient history and EKG, followed by a stress test if angina is likely, and potentially coronary angiography for confirmation. If angina is not likely, other causes are considered.
Pharmacological Management
The goal of treatment for stable angina is to decrease the heart's workload and increase oxygen supply.
Antiplatelet Therapy
Patients at risk for CAD are typically prescribed antiplatelet therapy, such as aspirin (81mg or 325mg), to prevent clot formation.
Symptom Relief and Prevention
Beta Blockers: These are crucial as they are the only class proven to prevent re-infarction and improve survival after an MI.
Calcium Channel Blockers: Often used in conjunction with beta blockers.
Nitrates: These are the first-line treatment for acute anginal symptoms because they act as coronary vasodilators.
Deep Dive: Nitroglycerin Administration
Nitroglycerin (NTG) works rapidly to dilate coronary arteries. It can be administered via sublingual, translingual, or topical (patch/ointment) routes.
Route
Usage/Notes
Sublingual
Most common; works in < 3 mins; should feel a "tingling".
Translingual
Placed on the tongue.
Patch/Ointment
Used for prevention; use gloves to avoid self-vasodilation.
Critical Safety Alert: If a patient takes one dose of sublingual nitroglycerin and the chest pain does not subside within five minutes, they must call 911 immediately and take an aspirin. Do not wait to complete "three doses" before seeking emergency help; time is of the essence.
Nursing Considerations for Nitroglycerin:
Blood Pressure: Always check blood pressure before administration, as NTG is a vasodilator and can cause significant hypotension.
Contraindications: Never combine NTG with medications used for erectile dysfunction, as this can be fatal.
Storage: Sublingual tablets should be kept in their original dark brown bottle to protect them from light.
This diagram illustrates the administration routes, mechanism of action, and common side effects of nitroglycerin, including sublingual tablets, sprays, and transdermal patches, along with details on onset, duration, and key side effects like postural hypotension and headache.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.