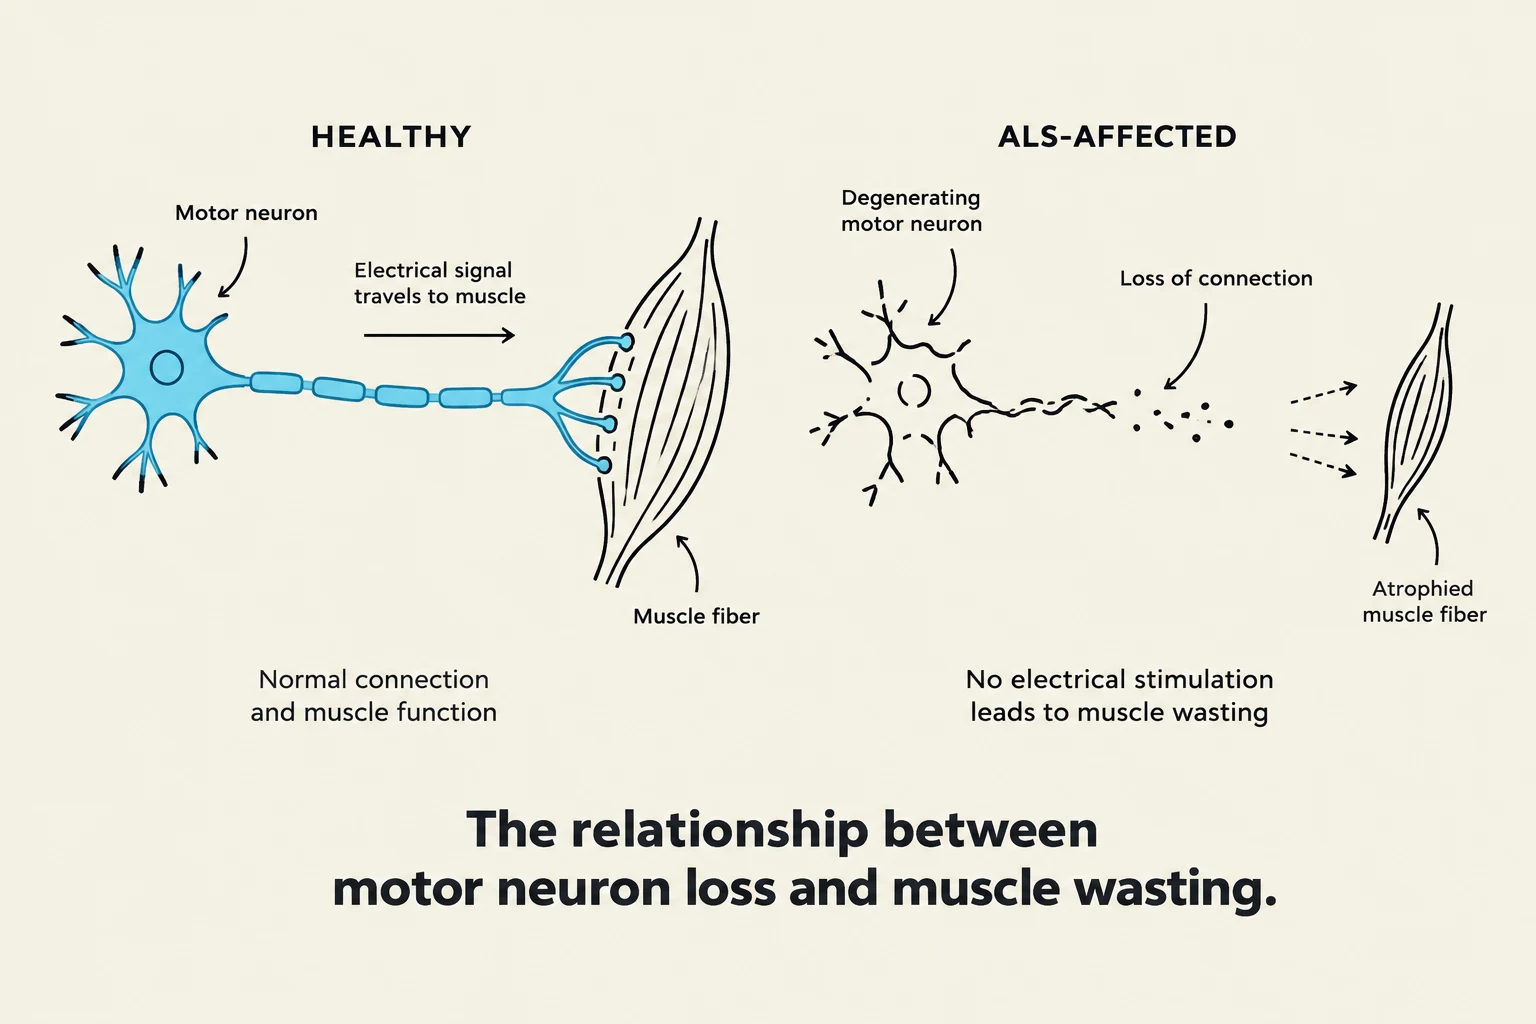
Amyotrophic Lateral Sclerosis (ALS), frequently referred to as Lou Gehrig's Disease, is a progressive and terminal neurodegenerative disorder. Named for its specific pathological processes, the disease involves both amyotrophy—the progressive wasting of muscles—and lateral sclerosis, which refers to the demyelination and subsequent hardening of the spinal column due to the buildup of scar tissue. As the disease advances, it spreads through the nervous system until all muscle groups are eventually involved, which is the defining characteristic of the condition.
This diagram illustrates the difference between a healthy motor neuron and its connection to a muscle fiber, and a degenerating motor neuron in ALS, leading to muscle wasting due to loss of connection and electrical stimulation.
Pathophysiology and Risk Factors
The progression of ALS is characterized by the loss of motor neurons, leading to a total loss of muscle control. While the exact cause is not always known, there is no cure for the disease. Understanding the patient profile is essential for early recognition and clinical preparation.
Risk Factors include:
Age: Typically occurs between the ages of 40 and 60.
Gender: More commonly affects men.
Genetics: A positive family history increases risk.
Medical History: Presence of autoimmune diseases.
Lifestyle and Environment: Smoking, viral infections, military veteran status, and exposure to environmental toxins.
Clinical Manifestations
The clinical presentation of ALS often begins subtly, with symptoms localized to specific limbs before spreading to the rest of the body. Because the disease affects motor neurons, the primary symptoms revolve around muscle dysfunction.
Early and Progressive Symptoms
Patients often report fatigue and a lack of coordination. As the motor neurons fail, several distinct physical signs emerge:
Fasciculations: Visible muscle twitching under the skin.
Spasticity and Cramps: Increased muscle tension and painful contractions.
Progressive Weakness: A gradual loss of strength that eventually affects all muscle groups.
Bulbar and Respiratory Symptoms
As the disease reaches the muscles responsible for communication and vital functions, more severe complications arise:
Dysarthria: Slurred or difficult speech.
Dysphagia: Difficulty swallowing, which poses a significant risk for choking and aspiration.
Respiratory Distress: As the muscles used for breathing weaken, patients face life-threatening respiratory failure.
Clinical Note: It is crucial to remember that while motor functions decline, the patient's ability to think, reason, and maintain cognitive awareness typically remains intact. This can lead to significant psychological distress, including fear, anxiety, and depression.
Diagnostic Procedures
Because ALS can mimic other neurological disorders, diagnostics focus on ruling out alternative causes and confirming nerve and muscle dysfunction.
Nerve Conduction Velocity (NCV) Studies: These are typically administered before an EMG to measure the speed at which nerves transmit electrical signals.
Electromyography (EMG): This procedure measures the electrical impulses generated by nerve and muscle activity.
Muscle Biopsy: Direct examination of muscle tissue to assess for damage.
Imaging and Laboratory Tests:
MRI: Used to rule out spinal cord diseases.
Blood Tests: To detect heavy metals (like lead), abnormal proteins, or hormone levels associated with other neurological diseases.
Lumbar Puncture: To analyze cerebrospinal fluid for genetic, viral, autoimmune, or neurotoxic abnormalities.
Management and Goals of Care
Since there is no cure, the primary goals of care are to maintain the patient's quality of life, control symptoms, prevent complications, and increase mobility through adaptive technology.
Pharmacological Interventions
Medications are used to manage both the disease progression and the resulting symptoms:
Riluzole (Rilutek®): One of the few effective drugs for ALS; it may slow disease progression and prolong life by a few months.
Antispasmodics: Drugs like Baclofen, Dantrolene sodium, or Diazepam are used to manage muscle spasticity.
Pain Management: NSAIDs (e.g., ibuprofen) for general discomfort or Tramadol for more significant pain.
Psychological Support: Antidepressants to address the emotional impact of the diagnosis.
Multidisciplinary Support
An interdisciplinary team is essential for holistic care:
Physical and Occupational Therapy: To assist with movement and daily living activities.
Speech Therapy: To manage dysarthria and dysphagia.
Dietitian: To manage nutritional needs, especially as swallowing becomes difficult.
Adaptive Devices: The use of splints, braces, and wheelchairs to maintain independence for as long as possible.
Late-Stage Management and End-of-Life
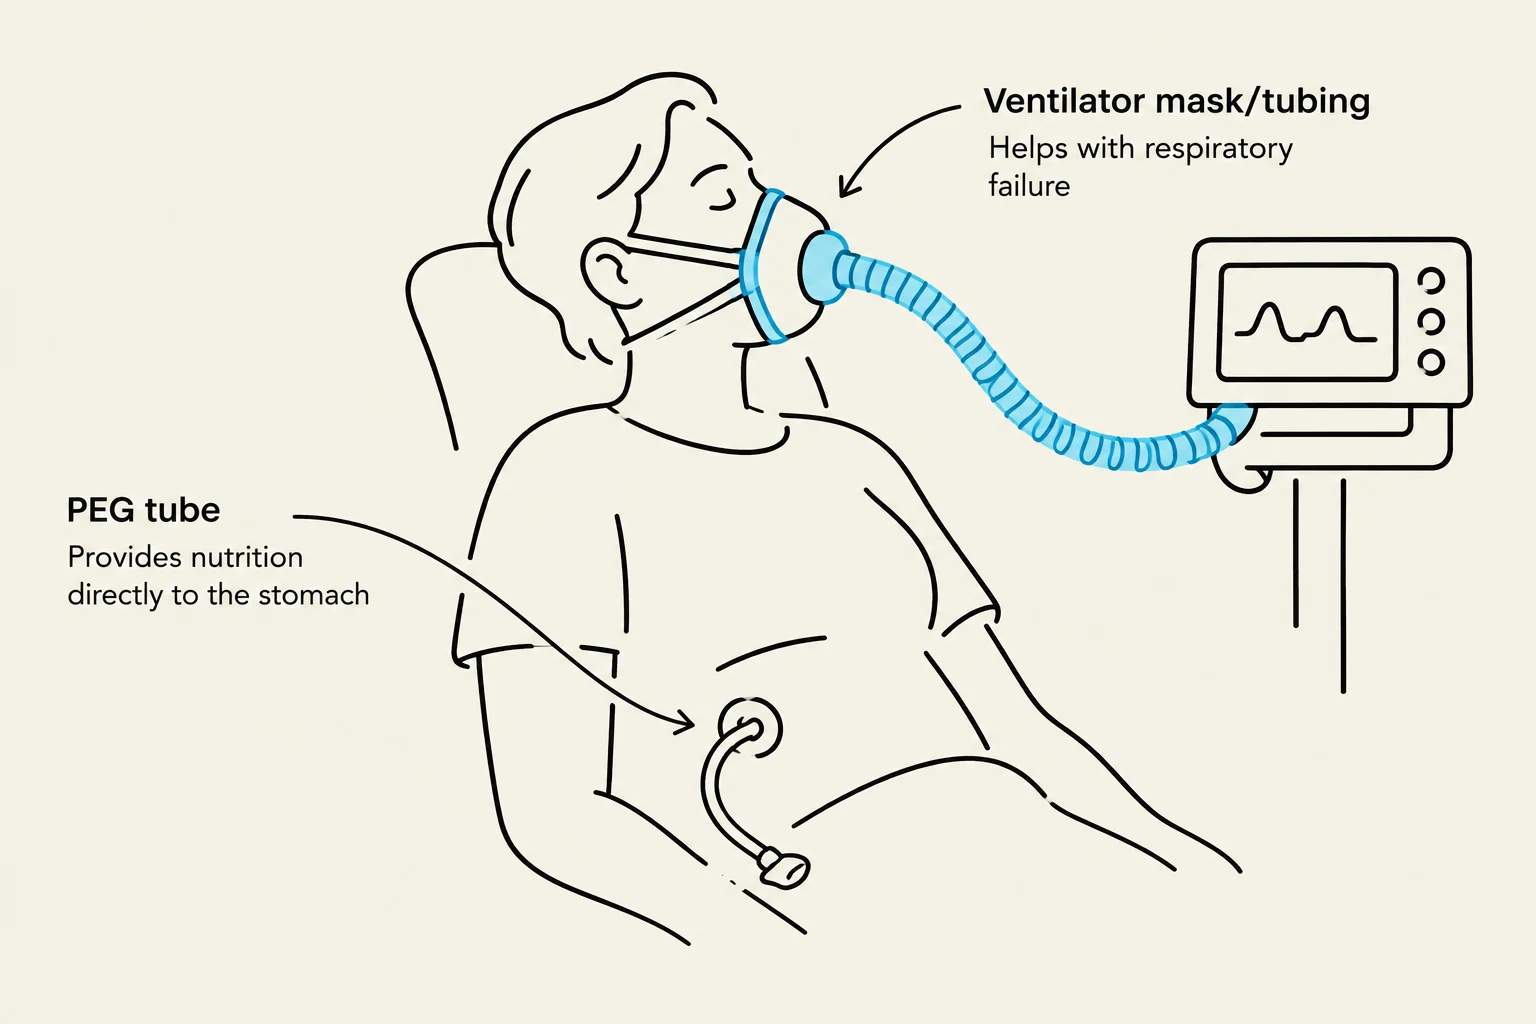
Illustration showing a patient with a PEG tube for nutrition and a ventilator mask for respiratory support.
In the late stages, patients become progressively incapacitated. As respiratory muscles fail, medical interventions such as ventilators may be required to support breathing. To manage nutrition when swallowing is no longer safe, a Percutaneous Endoscopic Gastrostomy (PEG) tube is often inserted.
Ethical and Legal Considerations
Because ALS is a progressive, terminal illness, patients and families should engage in Advance Care Planning early in the disease process. This includes:
Discussing DNR (Do Not Resuscitate) and DNI (Do Not Intubate) orders.
Establishing Living Wills and Durable Power of Attorney for Healthcare.
Addressing legal concerns regarding employment or insurance discrimination.
Exam Tip: In end-of-life care, the focus shifts from curative treatment to palliative care—which aims to relieve suffering and maximize quality of life—and hospice care, which is specifically for patients with a prognosis of less than six months to live.
Complications to Monitor
As the disease reaches its final stages, healthcare providers must be vigilant for:
Breathing and speaking difficulties.
Eating and nutritional challenges.
Potential for dementia.
As the patient approaches death, nurses should monitor for signs of imminent death, such as changes in respiration (e.g., Cheyne-Stokes breathing), cyanosis, and decreased urinary output. The ultimate goal remains to facilitate a "good death" that is respectful of the patient's dignity and guided by their personal values and preferences.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.