This content provides a comprehensive overview of trauma and dissociative disorders, including Posttraumatic Stress Disorder (PTSD) in children and adults, dissociative identity disorder, dissociative amnesia, and related somatic symptom disorders. It also details nursing process applications, treatment modalities like
Trauma is not merely a psychological experience; it is a neurobiological event that can fundamentally alter how the brain processes reality, memory, and safety. When an individual experiences an event that overwhelms their ability to cope, the brain may employ unconscious defense mechanisms to ensure survival. These mechanisms can lead to a spectrum of disorders, ranging from Posttraumatic Stress Disorder (PTSD) to complex dissociative states. Understanding these disorders requires looking at the intersection of developmental stages, neurobiology, and specialized nursing interventions.
Trauma-Related Disorders in Children
Trauma manifests differently depending on a child's developmental stage. Because children often lack the cognitive tools to verbalize complex emotions, their trauma frequently presents through behavioral changes and attachment disruptions.
Posttraumatic Stress Disorder (PTSD) in Children
In preschool-aged children, PTSD may present as reduced play, repetitive play involving the traumatic event, social withdrawal, and intense negative emotions. Children may also struggle with self-blame, internalizing the trauma as something they caused.
Attachment and Social Engagement Disorders
Trauma involving caregivers or inconsistent caregiving can lead to specific attachment disorders:
Reactive Attachment Disorder (RAD): Often resulting from relationship trauma and inadequate caregiving, this is characterized by severe emotional inhibition where the child "holds back" emotions.
Disinhibited Social Engagement Disorder (DSED): In contrast to RAD, this involves indiscriminate social behaviors, such as a child being willing to "go off" with complete strangers.
Risk Factors and Resilience
The etiology of childhood trauma is multifactorial. Neurobiological factors include the polyvagal response, while psychological factors are often explained through attachment theory—the idea that early bonds with caretakers are embedded in emotional and somatic memories. Environmental stressors, such as poverty, parental substance abuse, or exposure to violence, significantly increase risk. However, resilience can be fostered through strong social support, positive emotions, and the development of self-efficacy.
This diagram illustrates the neurobiological and psychological factors that can contribute to dissociative responses following trauma, including the polyvagal response and attachment styles.
Posttraumatic Stress Disorder (PTSD) in Adults
In adults, PTSD is defined as a distinct, measurable neurobiological alteration where the brain remains "stuck" in a fight-or-flight state. This involves a failure of the prefrontal cortex to regulate the brain's "panic button" (the amygdala), and a failure of the hippocampus to keep traumatic memories in the past, causing them to feel as though they are happening in real time.
The Four Symptom Clusters
Current diagnostic standards categorize PTSD symptoms into four distinct clusters:
Intrusion: Involuntary re-experiencing of the trauma, such as flashbacks or recurring nightmares.
Avoidance: Deliberate avoidance of stimuli associated with the trauma, such as people, places, or conversations.
Negative Changes in Cognition and Mood: This includes an inability to remember key aspects of the event, a negative self-image, and persistent feelings of depression or hopelessness.
Alterations in Arousal and Reactivity: Characterized by hypervigilance (scanning the room), irritability, difficulty concentrating, sleep disturbances, and an exaggerated startle response.
Treatment Modalities
Pharmacological treatment often involves SSRIs (such as sertraline, paroxetine, or venlafaxine) to manage comorbid depression or anxiety. It is important to note that benzodiazepines are not recommended for routine PTSD treatment, though they may be used for severe, acute anxiety.
Preferred psychological interventions include:
Cognitive Behavioral Therapy (CBT): To restructure faulty perceptions.
Eye Movement Desensitization and Reprocessing (EMDR): An evidence-based therapy where the patient processes traumatic memories while following rhythmic eye movements, helping painful memories fade and be replaced by positive beliefs.
Exam Tip: When assessing a patient with PTSD, always screen for depression first, as it is a common comorbid condition.
Dissociative Disorders
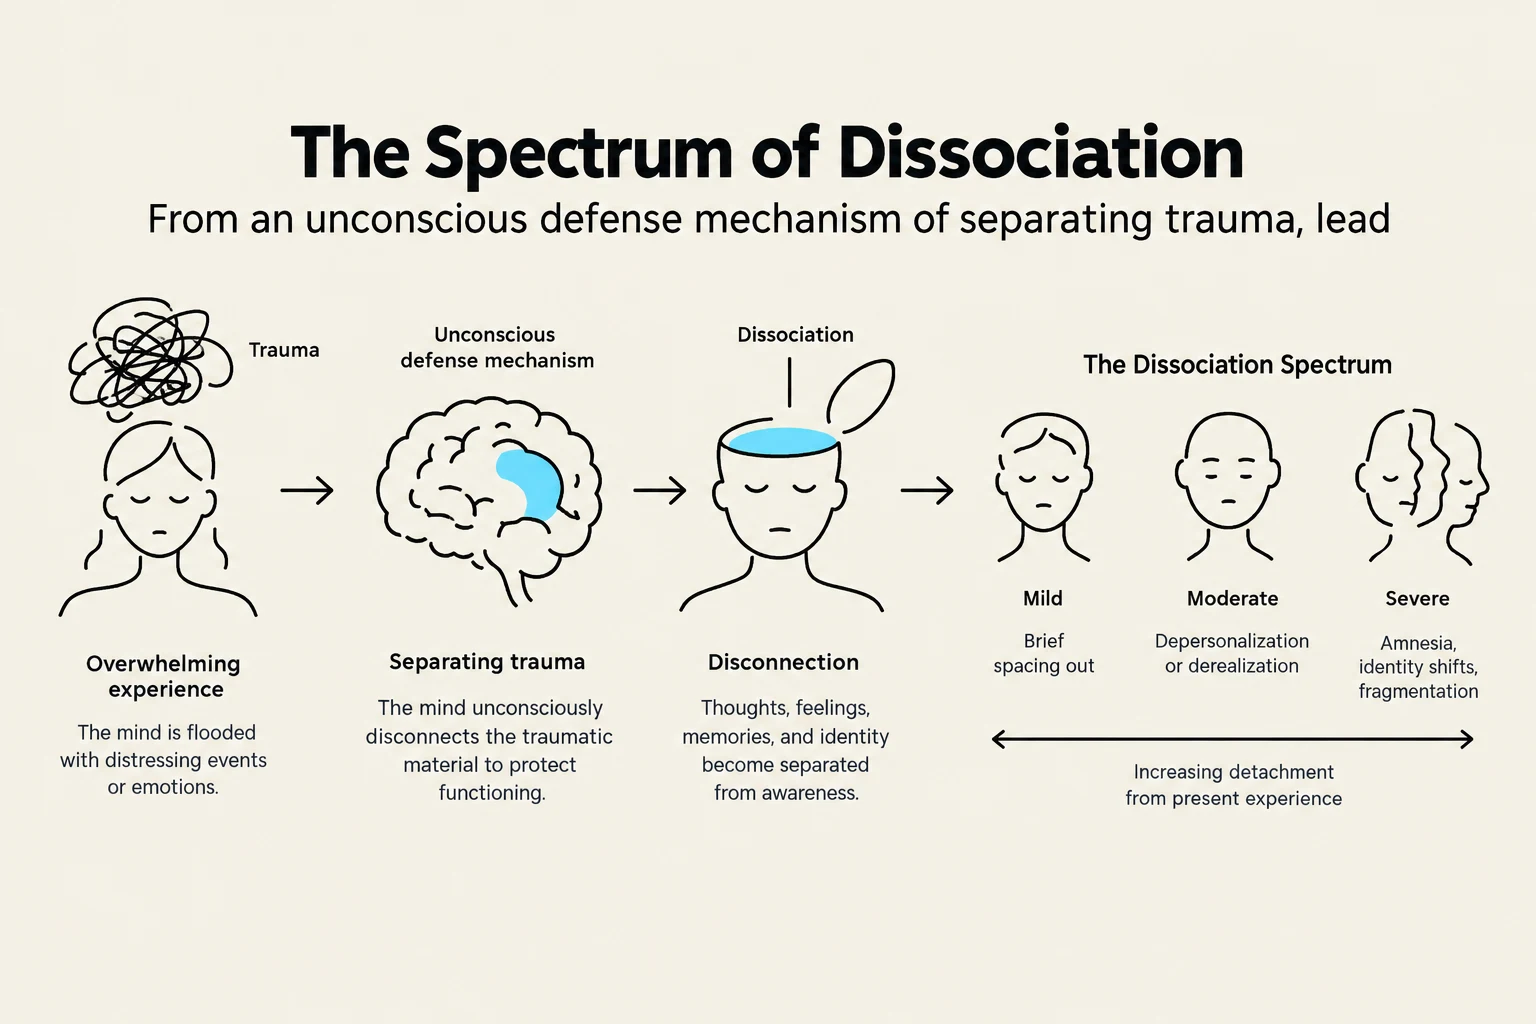
Dissociation is an unconscious defense mechanism where the brain separates a traumatic event or identity from the self to manage overwhelming anxiety. This "emotional separation" can be a survival mechanism, sometimes allowing a child to maintain an attachment to an abusive caregiver by dissociating from the abuse itself.
Dissociative Identity Disorder (DID)
DID involves the presence of two or more distinct personality states, known as alters. Each alter has its own unique pattern of perceiving, relating to, and thinking about the self and the environment. The primary personality is often unaware of the alters' actions, leading to "lost time" or unexplained events.
Dissociative Amnesia and Fugue
Dissociative Amnesia: An inability to recall important personal information, often related to traumatic or stressful events.
Dissociative Fugue: A specifier of dissociative amnesia where an individual engages in purposeful travel or wandering and experiences an inability to recall their identity or autobiographical history.
This diagram illustrates the spectrum of dissociation, a defense mechanism against trauma, ranging from mild spacing out to severe amnesia and identity fragmentation.
Somatic Symptom and Related Disorders
While dissociative disorders involve a separation of consciousness, somatic symptom disorders involve physical symptoms that cause significant distress.
Somatic Symptom Disorder: Distressing physical symptoms where the suffering is authentic, even if a medical diagnosis is not found. It is characterized by excessive thoughts and behaviors related to these symptoms.
Illness Anxiety Disorder: (Formerly hypochondriasis) A preoccupation with having a serious illness despite a lack of medical evidence.
Conversion Disorder (Functional Neurological Symptom Disorder): Neurological symptoms, such as paralysis or blindness, that are incompatible with recognized neurological disease.
Factitious Disorder: Artificially fabricating symptoms to assume the "sick role". This includes Munchausen syndrome (self-inflicted) and Munchausen by proxy (inflicting illness on a dependent).
Note on Malingering: Unlike Factitious Disorder, Malingering is not a mental health disorder. It is the intentional feigning of symptoms for external material or legal gain (e.g., disability compensation).
Nursing Process Application
Nursing care for trauma and dissociative patients focuses on safety, stabilization, and reintegration into reality.
Assessment and Implementation
Nurses must assess for suicide risk, specifically looking for feelings of hopelessness, helplessness, or worthlessness. In children, assessment may involve observation through play.
Implementation often follows a three-stage approach:
Stage 1: Provide safety and stabilization.
Stage 2: Reduce arousal and regulate emotion.
Stage 3: Catch up developmental skills and increase coping.
The Window of Tolerance and Grounding
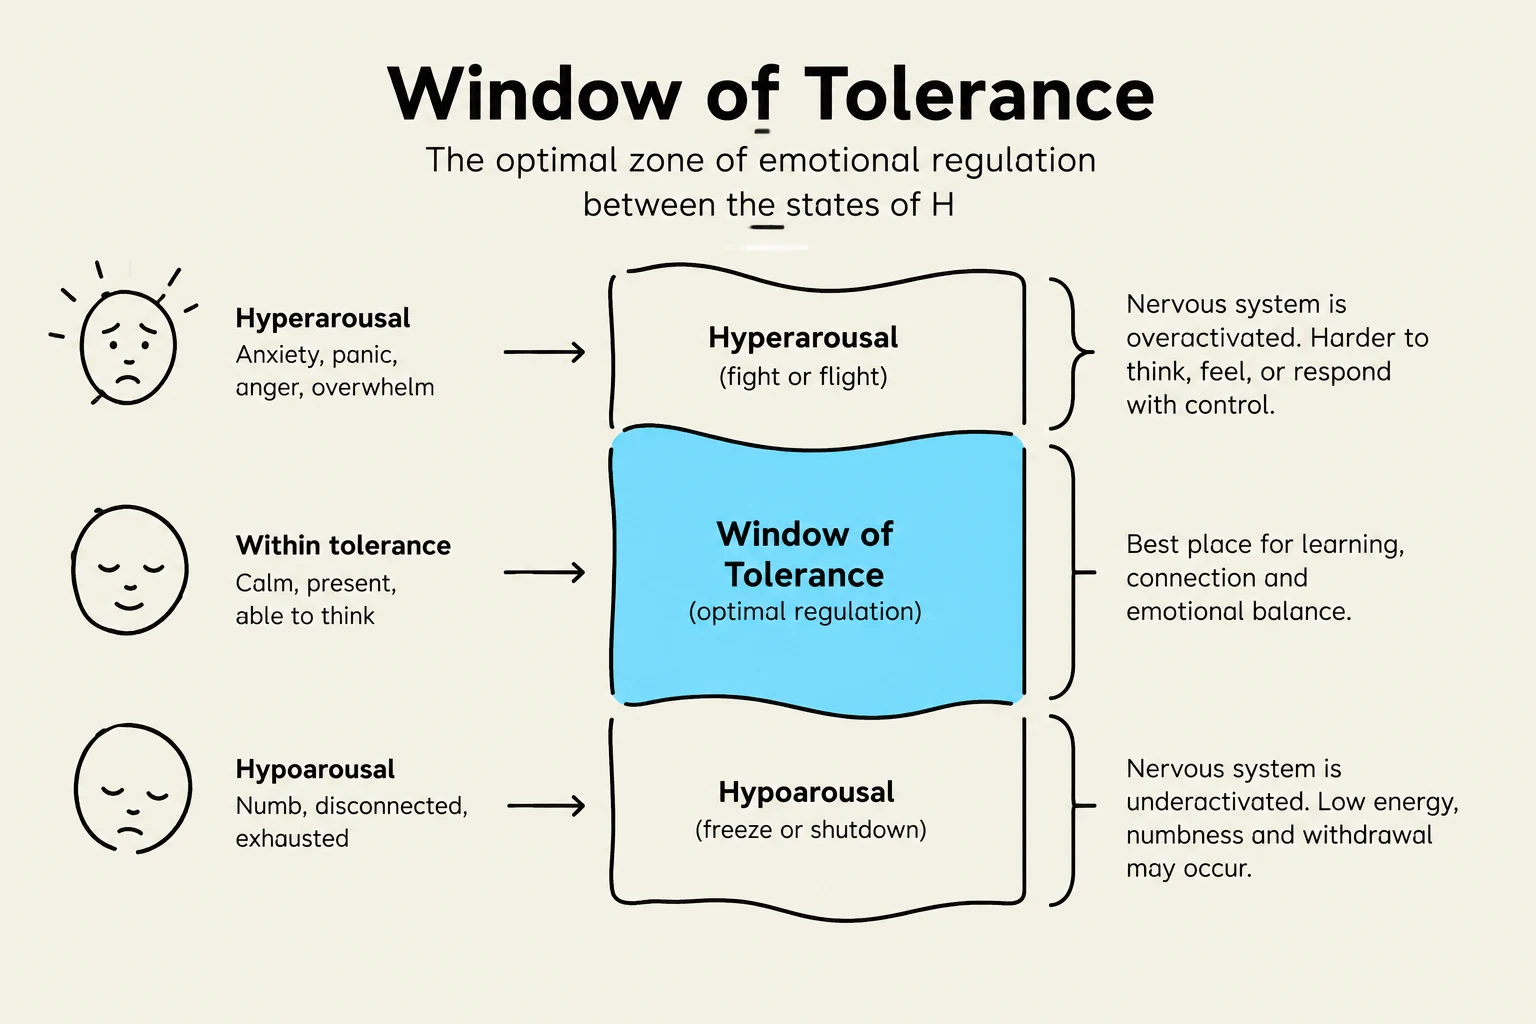
A key concept in trauma nursing is the window of tolerance—the zone where a patient can effectively manage and process emotions without becoming hyperaroused (fight/flight) or hypoaroused (shutdown).
To help patients stay within this window during moments of dissociation or flashbacks, nurses teach grounding techniques to maintain presence in reality. Examples include:
Stomping feet on the ground.
Touching different fabrics.
Engaging in physical exercise.
This diagram illustrates the Window of Tolerance, which represents the optimal zone for emotional regulation, situated between states of hyperarousal (fight or flight) and hypoarousal (freeze or shutdown).
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.