


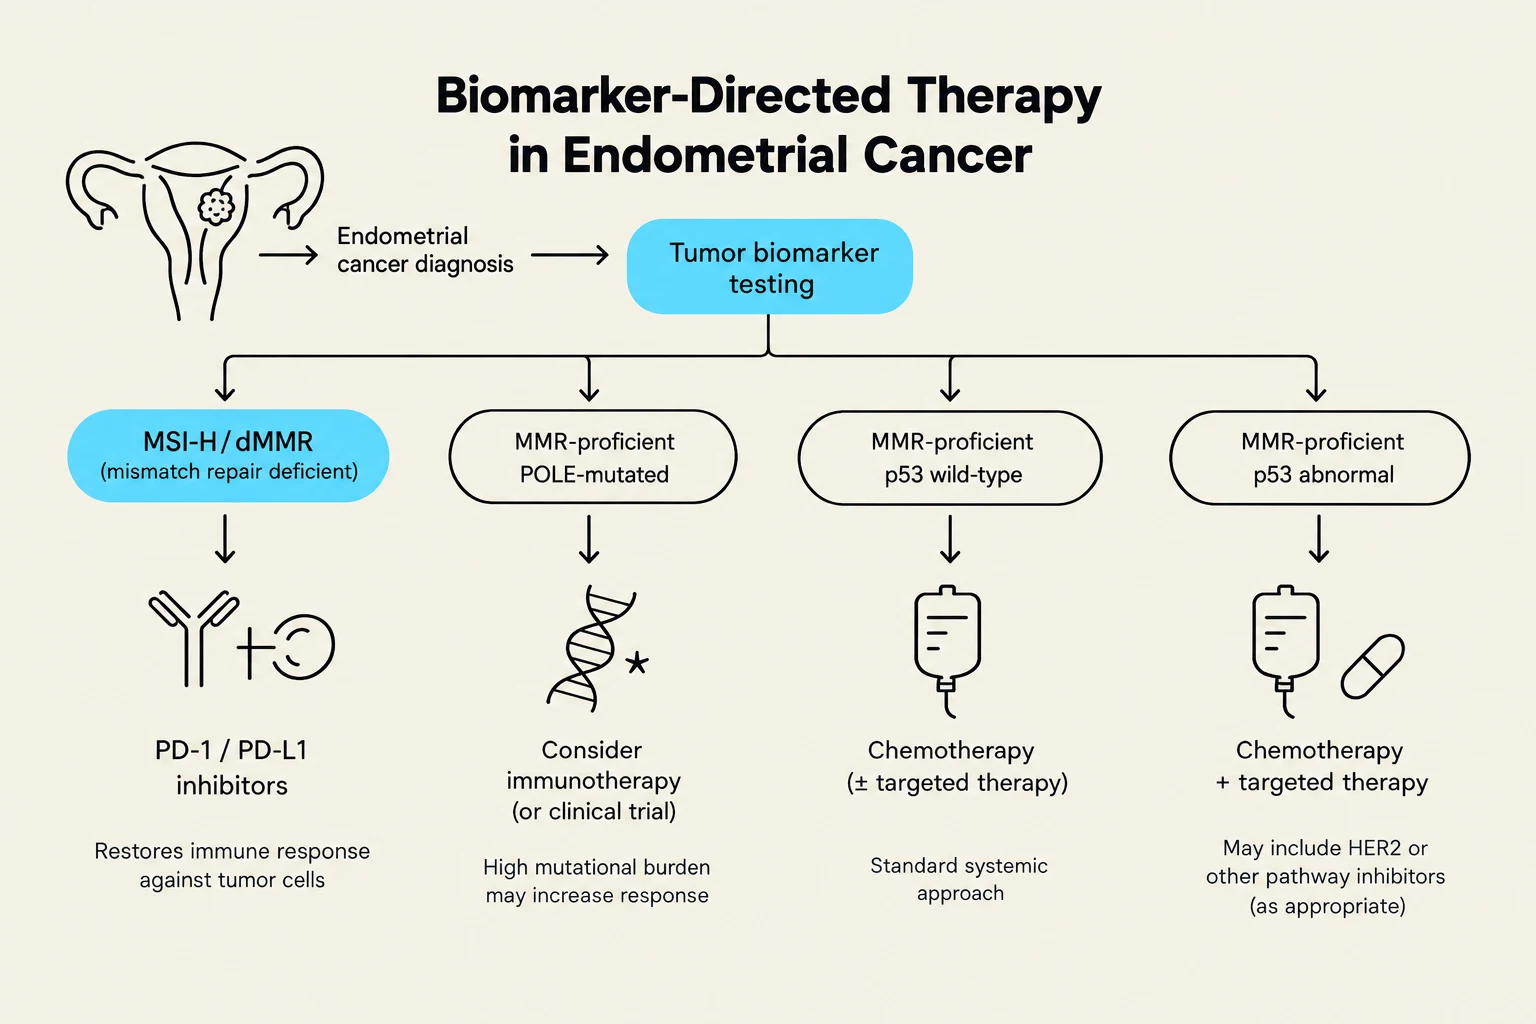
The management of endometrial cancer has undergone a paradigm shift, moving from a "one-size-fits-all" chemotherapy approach to a highly personalized model driven by molecular profiling. Modern treatment strategies now integrate histological subtype, mismatch repair (MMR) status, tumor mutational burden (TMB), and specific genetic fusions to guide systemic therapy, radiotherapy, and surveillance protocols.
Systemic Therapy: Chemotherapy and Standard Regimens
For many patients, particularly those with high-grade histologies or advanced stages, systemic chemotherapy remains a cornerstone of treatment.
Combination Chemotherapy
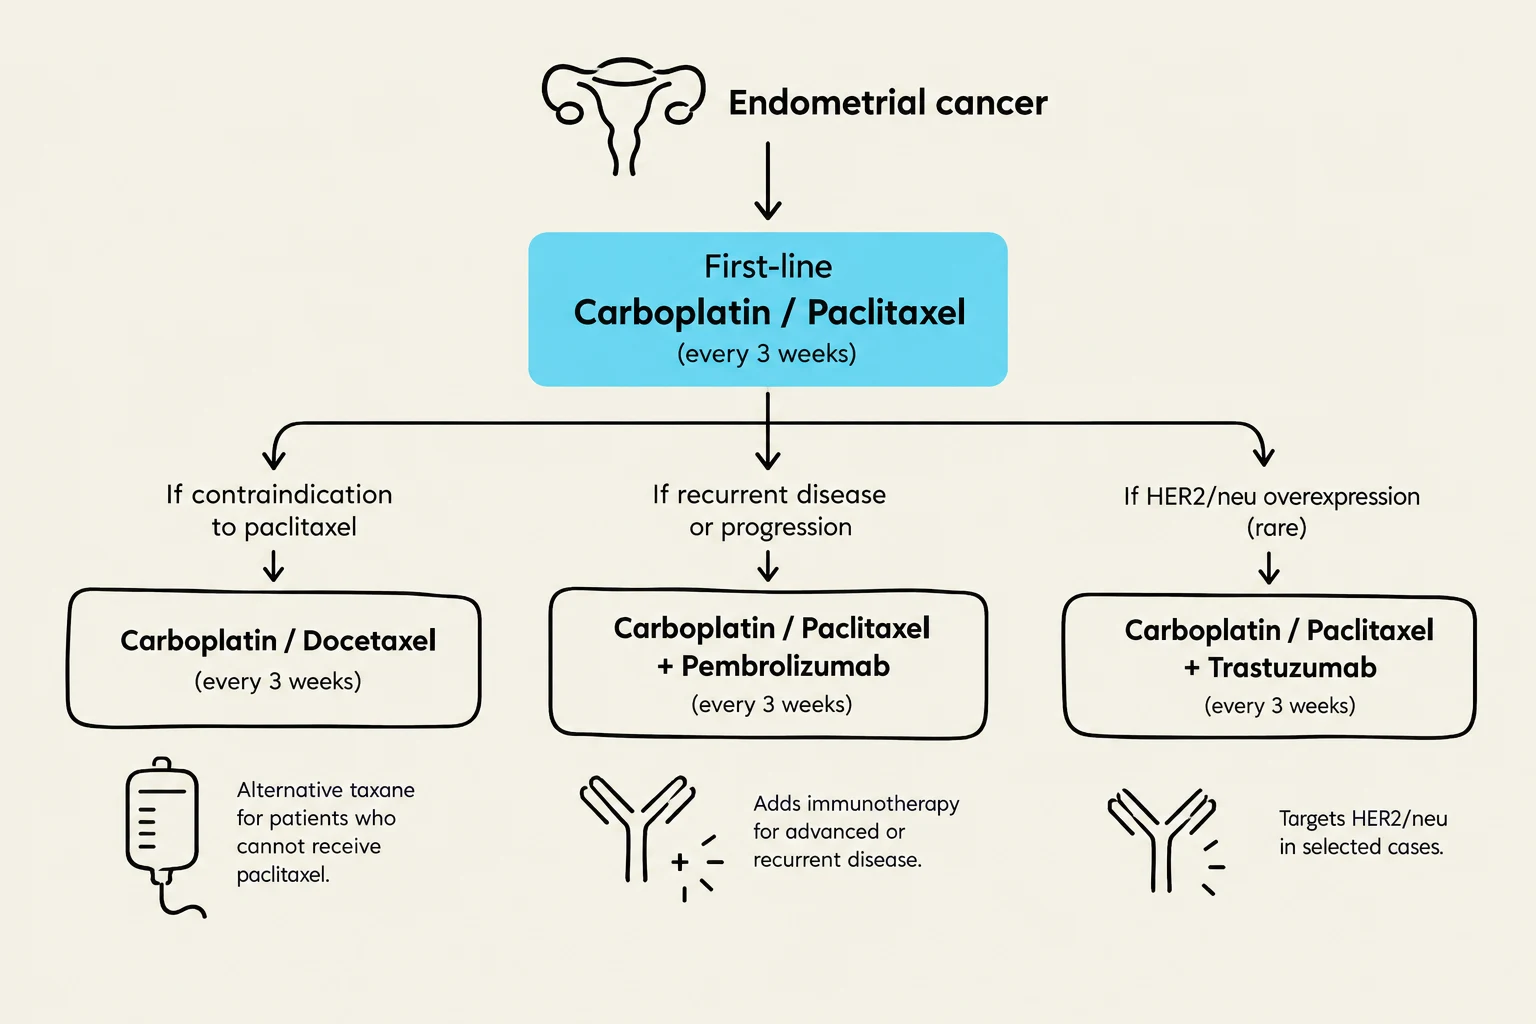
The preferred first-line or standard regimen for many endometrial cancers, including carcinosarcoma, is the combination of carboplatin and paclitaxel. In stage III–IV tumors with measurable disease, clinicians may also consider adding bevacizumab to this regimen. For certain pMMR (mismatch repair proficient) tumors, newer combinations such as carboplatin/paclitaxel/durvalumab or durvalumab/olaparib are being utilized.
Single-Agent and Subsequent Therapy
When disease progresses or if combination therapy is not tolerated, single-agent options are available. Paclitaxel is noted as the most active single agent in second-line settings. Other options include doxorubicin or bevacizumab. While regimens involving cisplatin, doxorubicin, and paclitaxel exist, they are often associated with higher toxicity, such as peripheral neuropathy.
Carcinosarcoma-Specific Management
Carcinosarcoma requires specialized consideration. Beyond standard platinum-based regimens, ifosfamide-based combinations (e.g., ifosfamide/paclitaxel or ifosfamide/cisplatin) may be utilized. Notably, for advanced or recurrent carcinosarcoma, trastuzumab deruxtecan is recommended regardless of the tumor's HER2 status.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.
Continue reading freeAlready have an account? Log in
Updated