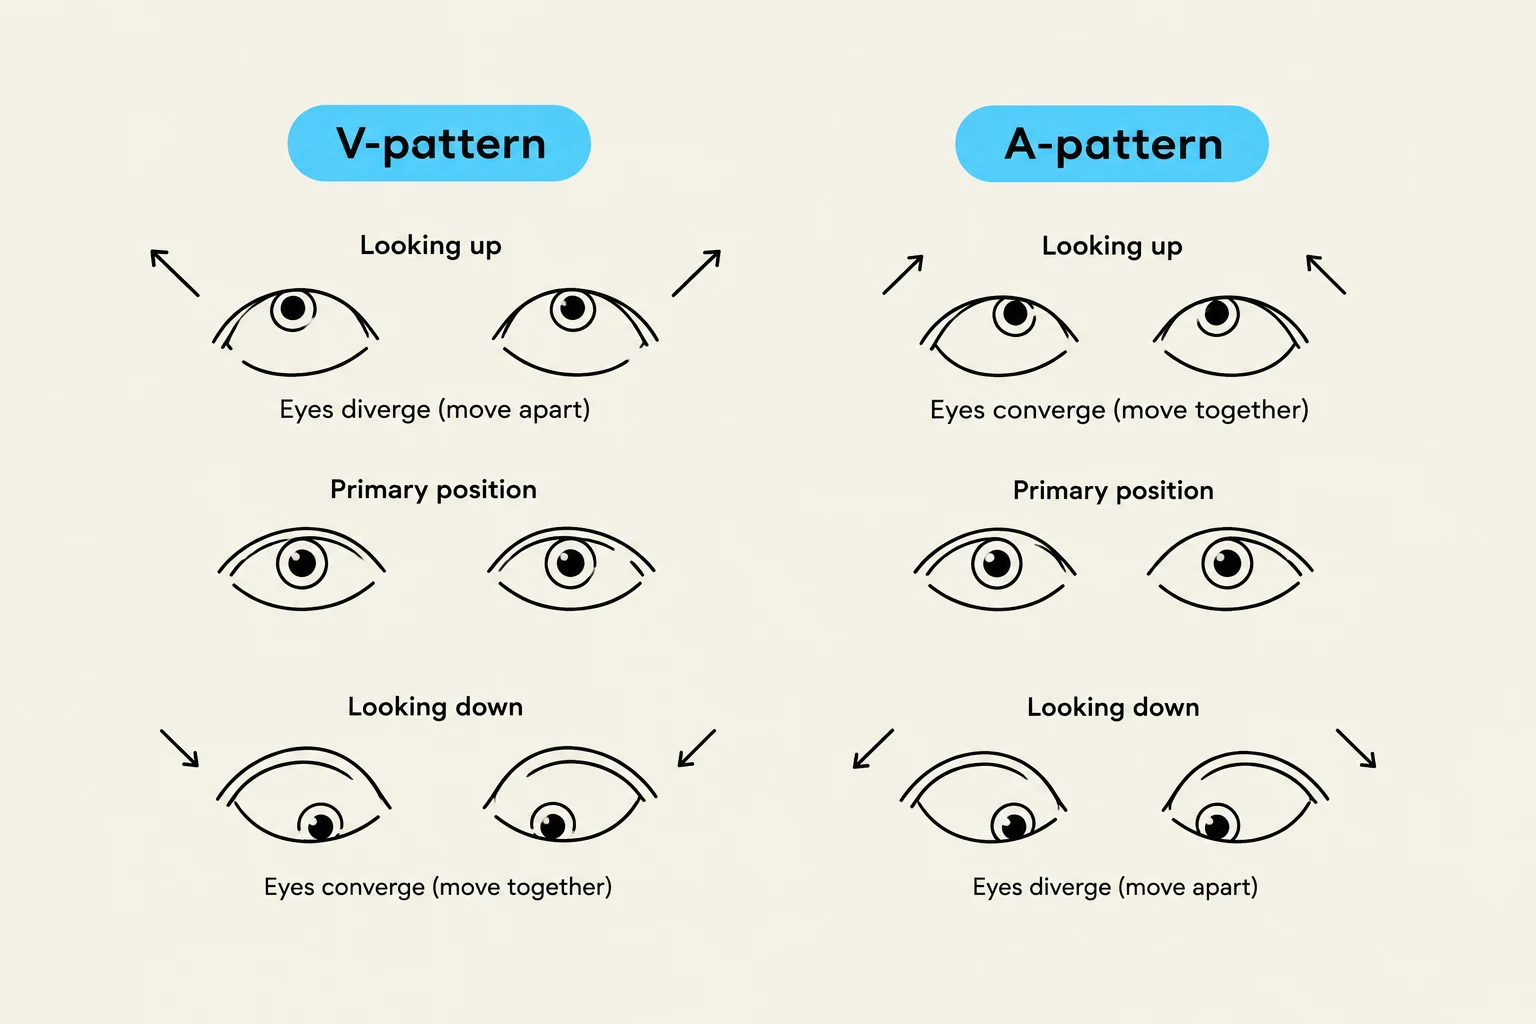
Addressing Oblique Over-action
If the V-pattern is driven by IO over-action, the goal is to weaken the muscle to reduce the excessive convergence seen during elevation. Surgical options include:
- IO Recession: A standard weakening procedure.
- IO Myectomy: Removal of a portion of the muscle.
- Anterior Transposition of the IO: Often used in specific cases like Dissociated Vertical Deviation (DVD).
If the pattern is instead driven by Superior Rectus (SR) over-action, the aim is to reduce abduction on elevation, typically through bilateral SR recession.
Horizontal Muscle Transposition
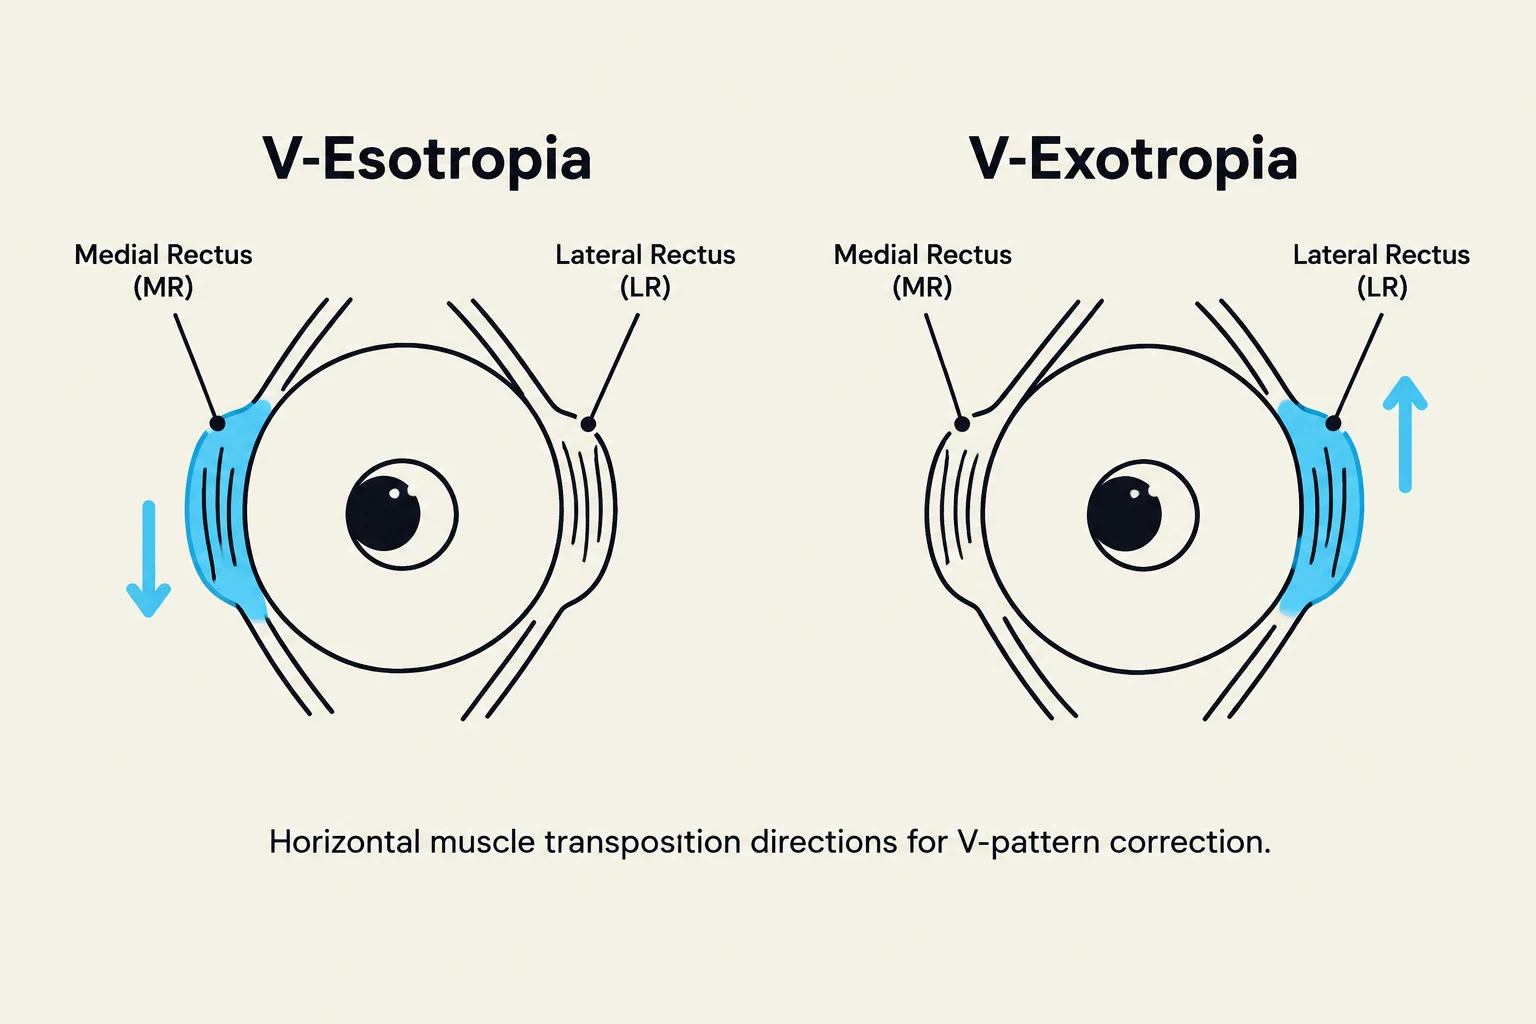
When oblique involvement is minimal, surgeons may use transposition of the horizontal muscles to compensate for the pattern. The direction of transposition depends on the type of V-pattern:
- V-Esotropia: The medial rectus (MR) is transposed downwards.
- V-Exotropia: The lateral rectus (LR) is transposed upwards.
Managing A-Pattern Strabismus
A-patterns involve increased convergence on elevation and increased divergence on depression. These are most commonly driven by superior oblique (SO) over-action.
Addressing Oblique Over-action
To manage SO over-action, the surgeon aims to weaken the muscle to reduce excessive adduction during depression. Common techniques include:
- SO Posterior Tenectomy
- SO Posterior Tenotomy
- SO Z-tenotomy
- SO Split Lengthening
- SO Tendon Spacer (e.g., silicon expander)
Alternatively, if the pattern is driven by inferior rectus (IR) over-action, bilateral IR resection may be considered.
Horizontal Muscle Transposition
If oblique muscles are not the primary target, horizontal transposition can be used:
- A-Esotropia: The MR is transposed upwards.
- A-Exotropia: The LR is transposed downwards.
Advanced Surgical Techniques
Slanting Muscle Insertions
Introduced by Bietti, this technique is used when there is no marked oblique over-action. It relies on the principle that horizontal muscle tension is stronger at the upper margin than the lower margin during elevation.
| Goal | Technique |
|---|
| Reduce V-Exotropia | Recess the upper margin of the LR more than the lower |
| Reduce A-Exotropia | Recess the lower margin of the LR more than the upper |
| Reduce A-Esotropia | Recess the upper margin of the MR more than the lower |
| Reduce V-Esotropia | Recess the lower margin of the MR more than the upper |
Combined Procedures and Success Rates
For complex cases, combining oblique weakening (such as an SO Z-tenotomy) with horizontal muscle surgery (recess/resect) is highly effective. Research indicates that these combined approaches yield success rates between 60% and 90%.
Risks and Complications
Surgeons must remain vigilant regarding several potential complications:
- Torsional Disturbances: Performing surgery on a single eye carries a risk of inducing unwanted torsion.
- Inducing SO Weakness: When correcting A-exotropia, there is a risk of inadvertently weakening the superior oblique.
- Vertical Displacement: The vertical displacement of horizontal muscles during transposition can induce unwanted cyclodeviation.
Exam Note: If a patient presents with an A-exotropia and you are performing horizontal surgery, be aware that an abnormally high LR insertion or an abnormally low MR insertion can exacerbate the pattern post-operatively. Correcting these via transposition can minimize risk.