Explores the biological mechanisms of stroke recovery, including neuroplasticity, diaschisis, and interhemispheric balance. Discusses differentiating recovery from compensation and predicting patient outcomes using clinical and neuroimaging predictors.
Understanding the trajectory of stroke recovery requires a deep dive into both the biological mechanisms of the brain and the clinical realities of patient outcomes. For clinicians, the goal is not just to observe change, but to differentiate between true neurological recovery and compensatory strategies, while using evidence-based models to predict a patient's functional potential.
The Nature of the Injury: Ischemic vs. Hemorrhagic
Stroke recovery begins with understanding the primary insult to the brain tissue. There are two main types of stroke that result in direct tissue damage and the death of neurons:
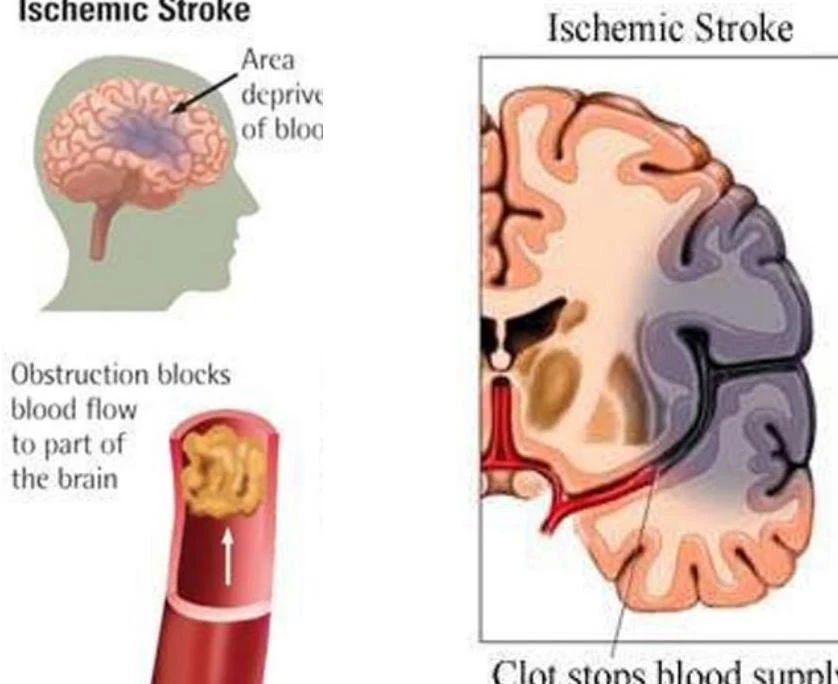
Ischemic Stroke: This occurs when an obstruction, such as a blood clot, blocks blood flow to a specific part of the brain.
Diagram illustrating an ischemic stroke, where a blood clot obstructs blood flow to the brain, leading to an area deprived of oxygen.
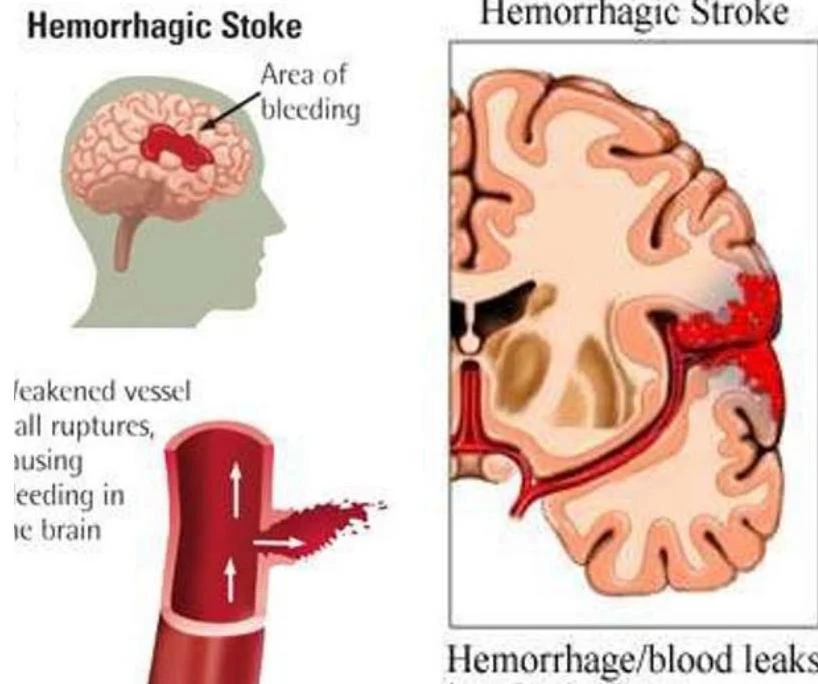
Hemorrhagic Stroke: This occurs when a blood vessel ruptures, causing blood to leak into the surrounding brain tissue.
Diagram illustrating a hemorrhagic stroke, showing bleeding within the brain and a ruptured blood vessel.
In both cases, the "core" of the lesion represents irreversible loss of function, while the surrounding "penumbra" represents tissue that is impaired but potentially salvageable if protected.
Indirect Effects: Diaschisis and Interhemispheric Balance
The clinical deficits observed immediately after a stroke often extend far beyond the actual site of the lesion. This is due to two primary indirect effects:
Diaschisis
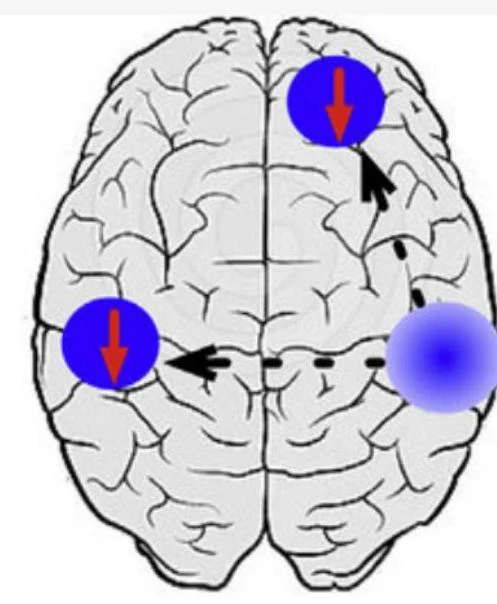
Diaschisis is the sudden loss of function in brain regions that are structurally intact but functionally connected to the lesioned area. This suppression results in reduced neuronal activity and metabolic dysfunction in those connected regions.
Diagram illustrating brain regions with directional arrows.
As the brain stabilizes, the resolution of diaschisis can lead to spontaneous functional improvement.
Interhemispheric Balance
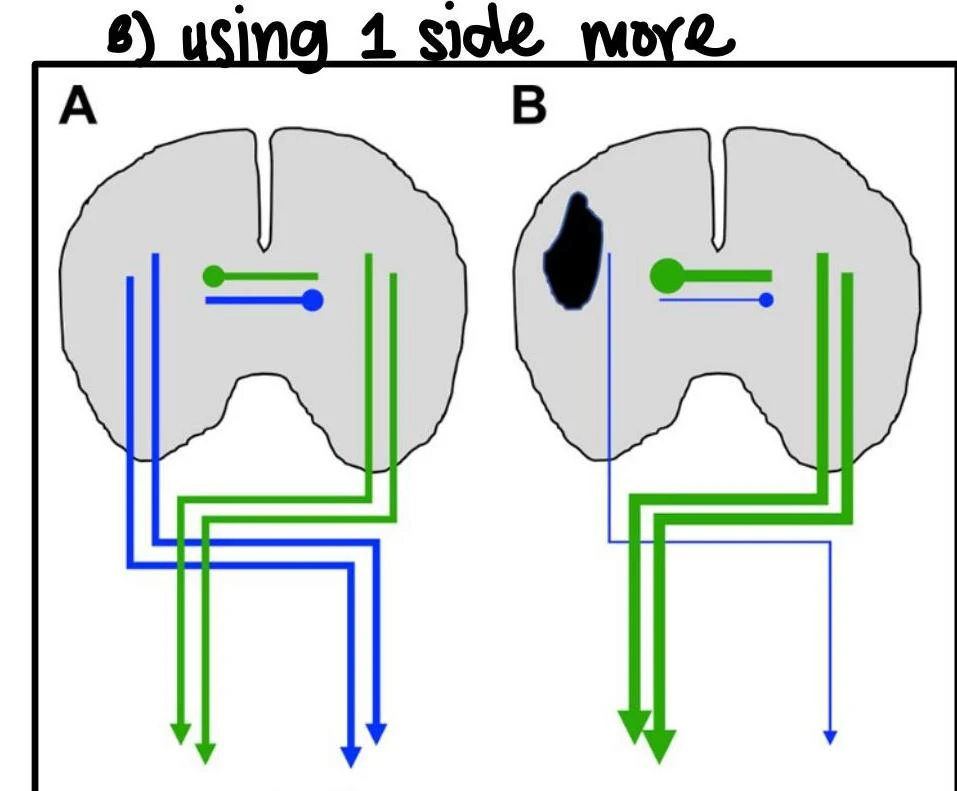
A healthy brain maintains a mutual transcallosal inhibition between hemispheres. Following a stroke, this balance is disrupted:
Acute Phase (~1 week): The unaffected side may over-inhibit the affected side, enhancing suppression.
Sub-Acute Phase (~6 months): Spontaneous recovery occurs, but there is a risk of maladaptive recovery if the contralateral hemisphere becomes excessively active.
Chronic Phase (>6 months): The brain either restores balance or remains hindered by continued excessive inhibition.
Diagram illustrating neural pathways in cross-section of the spinal cord, comparing a normal state (A) with a state exhibiting a lesion (B).
Mechanisms of Neuroplasticity and Regeneration
The brain's ability to remodel itself in response to stimulus is known as neuroplasticity. This reorganization is the fundamental mechanism behind learning and skill acquisition.
Biological Mechanisms of Change
Several micro-level processes drive this reorganization:
Resolution of Neural Shock: Occurring over hours to days, this involves the reduction of edema and the recovery of synaptic effectiveness.
Denervation Supersensitivity: A phenomenon where a neuron becomes more sensitive to neurotransmitters because its primary synaptic input has been lost.
Recruitment of Silent Synapses: The "unmasking" of latent synapses that were previously inactive due to competition within neuronal pathways. As the saying goes, "Neurons that fire together, wire together".
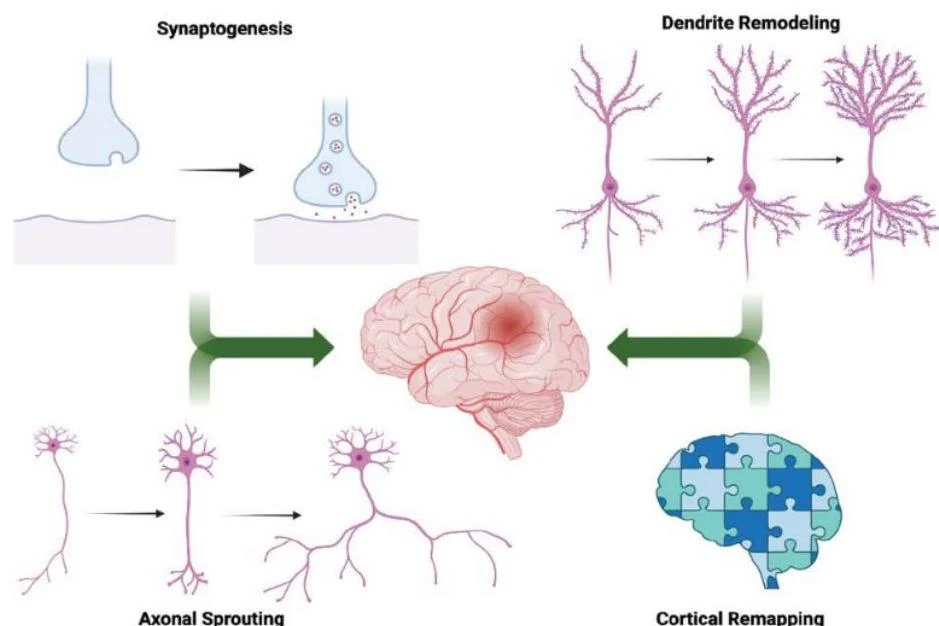
Regenerative and Reactive Sprouting: Surviving neurons generate new axonal projections or dendritic remodeling to replace lost connections. This process takes weeks to months and is highly dependent on goal-directed, task-specific training.
This illustration depicts key neuroplasticity processes: synaptogenesis, axonal sprouting, dendrite remodeling, and cortical remapping, all contributing to the brain's ability to adapt and reorganize.
Cortical Remapping
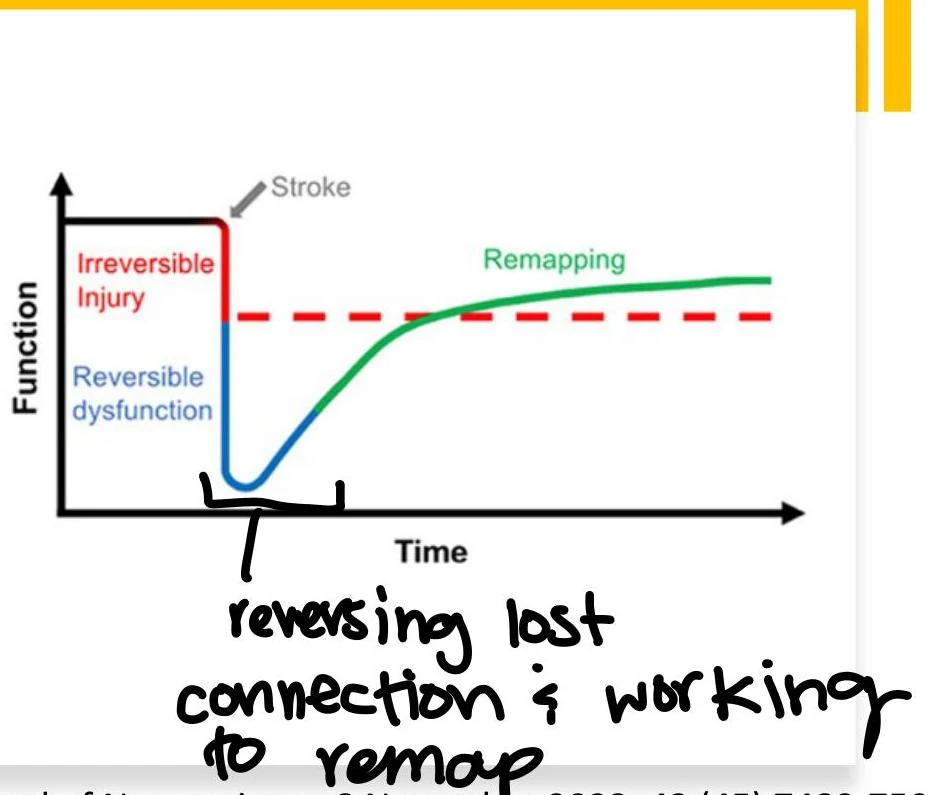
Through intensive practice, the brain can shift functional representations of motor and sensory systems to perilesional areas (areas surrounding the lesion).
A graph illustrating the impact of a stroke on function over time, showing irreversible injury, reversible dysfunction, and the process of remapping or recovery.
Recovery vs. Compensation
It is critical for clinicians to distinguish between these two pathways, as they lead to different functional outcomes:
Feature
Recovery
Compensation
Neural Mechanism
Restoring function in the original neural tissue
Residual neural tissue takes over a lost function
Behavioral Goal
Restoring original movement patterns and isolation
Achieving a task through a new, different strategy
Clinical Warning: Learned Non-Use
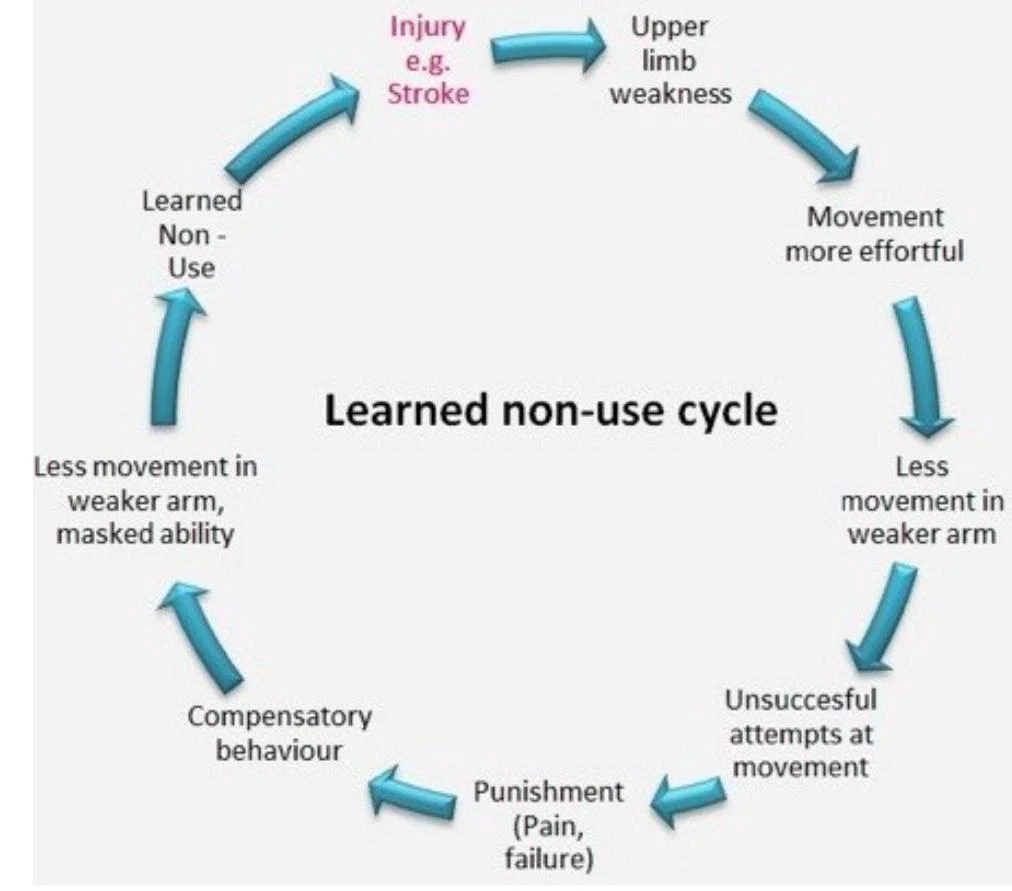
If a patient relies too heavily on compensatory strategies, they may fall into a cycle of "learned non-use," where the affected limb is used less and less, further hindering the potential for true neurological recovery.
The learned non-use cycle illustrates how an injury, such as a stroke, can lead to upper limb weakness, making movement more effortful. This results in less movement in the weaker arm, leading to unsuccesful attempts at movement, and potentially punishment through pain or failure. Consequently, compensatory behaviors develop, and less movement in the weaker arm, masked ability, and learned non-use perpetuate the cycle.
Predicting Outcomes and Discharge Planning
Effective discharge planning requires integrating clinical data with predictive models.
Neuroimaging and Clinical Predictors
CT/Perfusion: A larger infarct core (>25 mL) predicts poorer 90-day recovery, while a salvageable penumbra predicts improvement.
ASPECTS Score: A higher score (closer to 10) indicates better functional independence.
NIHSS Score: This is a primary predictor of discharge destination. A score <5 often leads home, while scores >14 may require long-term care.
Specialized Prediction Algorithms
Clinicians can use specific algorithms to tailor rehabilitation intensity:
1. Upper Limb (PREP 2 Algorithm): This uses MRC Manual Muscle Test (MMT) grades for shoulder abduction and finger extension at 72 hours post-stroke to categorize recovery potential into Excellent, Good, Limited, or Poor.
2. Mobility (TWIST Algorithm): This predicts the probability of independent walking at 6 months based on age, knee extension strength, and postural control.
Predictor
Impact on Prognosis
Motor Arm/Leg
Highly predictive of hand function/ADLs and gait/QOL
Age > 75
Associated with higher likelihood of discharge to care facilities
Initial GCS < 12
Associated with lower functional recovery
Summary of Discharge Settings
The choice of setting depends on the patient's medical complexity and rehabilitation needs:
Inpatient Rehab Facility (IRF): High intensity (≥3 hours/day); for those with moderate-to-significant deficits.
Skilled Nursing Facility (SNF): Lower intensity; for those with lower tolerance for intensive therapy.
Home/Outpatient: For mild-to-moderate deficits with adequate support.
Exam Tip: Remember that "Demand Stimulates Supply." Intensive, task-specific, and goal-directed training is required to drive the biological mechanisms of neuroplasticity.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.