Somatic Symptom, Factitious Disorders, and Impulse Control Disorders
An overview of somatic symptom disorders, factitious disorders, and impulse control disorders, including their characteristics, etiology, and nursing management.
In psychiatric nursing, distinguishing between physical illness and psychological manifestations of distress is a critical skill. Patients presenting with physical complaints may be experiencing genuine physiological issues, or their symptoms may be manifestations of complex psychological processes. This article explores the spectrum of somatic symptom disorders, factitious disorders, and impulse control disorders, providing a framework for assessment and nursing management.
Somatic Symptom Disorders
Somatic symptom disorders involve physical symptoms that cause significant distress or impairment, often without a clear, singular medical explanation that accounts for the severity of the patient's reaction. It is vital to remember that a medical illness may be present; the diagnosis is driven by the excessive nature of the thoughts, feelings, and behaviors related to those symptoms.
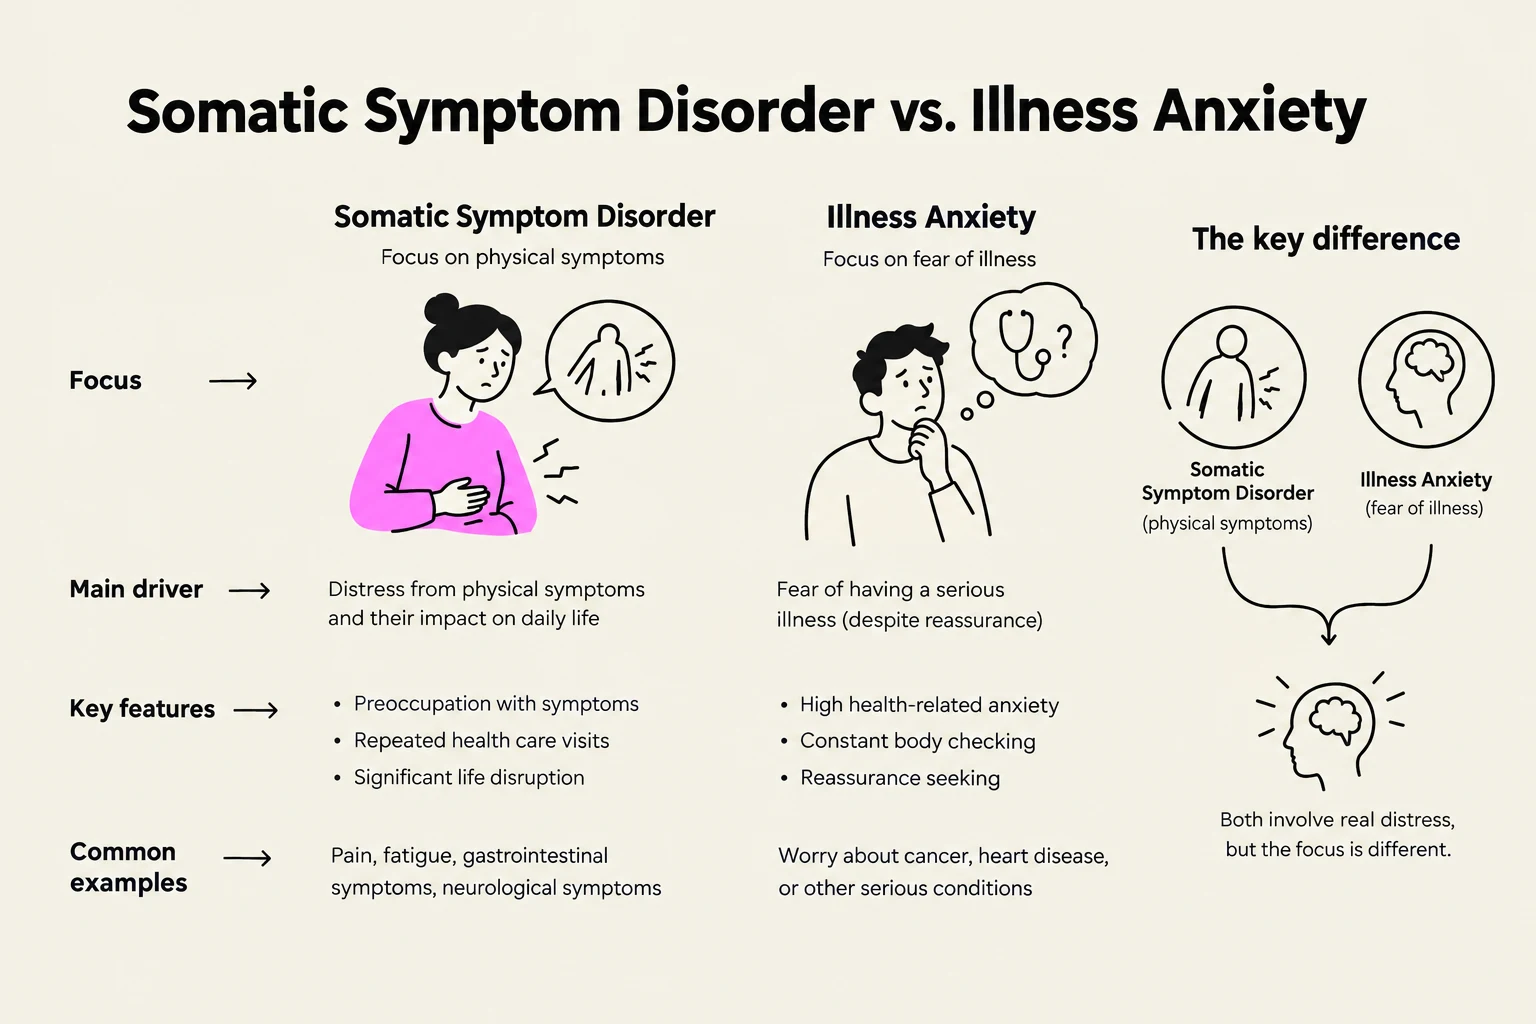
Somatic Symptom Disorder
This disorder is characterized by a preoccupation with distressing somatic symptoms. The patient's level of anxiety and the time spent on these symptoms are disproportionate to any actual medical findings.
Illness Anxiety Disorder
Replacing the older term "hypochondriasis," this disorder involves a preoccupation with having or acquiring a serious illness. Unlike somatic symptom disorder, where the focus is on the symptoms themselves, the focus here is on the anxiety regarding health. Patients often misinterpret normal physical sensations as signs of catastrophe, and the course of the illness is typically chronic and relapsing.
Conversion disorder involves neurological symptoms—such as paralysis, blindness, or movement disorders—that are incompatible with recognized neurological diseases. A classic, though not diagnostic, finding is "la belle indifférence," where the patient appears strangely unconcerned about their significant physical deficit.
This diagram compares Somatic Symptom Disorder and Illness Anxiety, highlighting their distinct focuses on physical symptoms versus fear of illness, their main drivers, key features, and common examples. It also illustrates that both conditions involve real distress, but differ in their primary focus.
Etiology of Somatic Symptom Disorders
The development of these disorders is multifactorial, involving a complex interplay of biological, psychological, and environmental influences.
Biological Factors: Genetic predispositions play a role.
Psychological Factors:
Psychodynamic theories suggest symptoms may represent the repression of internal conflicts.
Behavioral theories focus on "secondary gains," where the illness allows the patient to avoid responsibilities or receive care.
Cognitive theories suggest patients misinterpret bodily sensations and become excessively alarmed.
Environmental Factors: Childhood maltreatment and toxic stress are significant contributors. Research has even linked childhood trauma to elevated C-reactive protein, a biomarker for inflammation.
Factitious Disorders and Malingering
While somatic symptom disorders involve a struggle with perceived illness, factitious disorders involve the intentional fabrication of symptoms.
Factitious Disorder
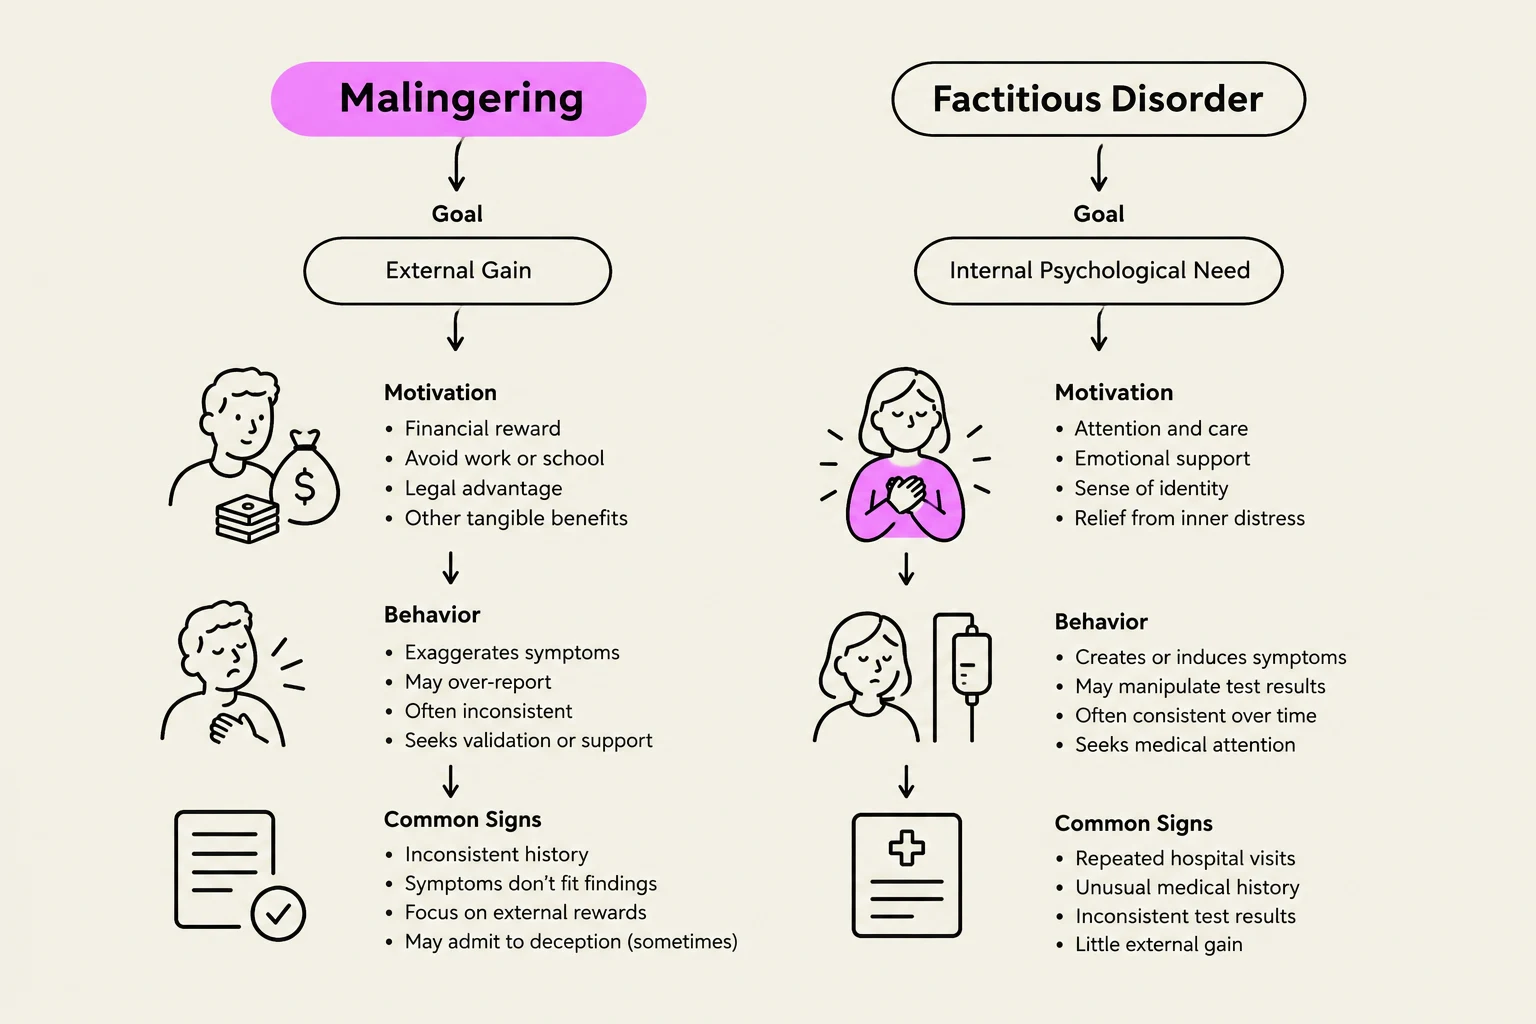
In these disorders, individuals deliberately and dramatically fabricate symptoms or self-inflict injuries to assume the "sick role". This is often driven by a psychological need for attention or care rather than external incentives.
Factitious Disorder Imposed on Another (Munchausen Syndrome by Proxy): This occurs when a caregiver feigns illness in a vulnerable dependent (such as a child) to gain attention or sympathy.
Malingering
It is crucial for nurses to distinguish factitious disorder from malingering. Malingering is not a mental health disorder. Instead, it is a deceptive behavior motivated by external, material gain, such as obtaining prescription medications, avoiding work, or receiving disability compensation.
This diagram illustrates the differences between malingering and factitious disorder, focusing on their goals, motivations, behaviors, and common signs.
Impulse Control Disorders
Impulse control disorders involve the inability to resist an urge or temptation to perform an act that is harmful to oneself or others.
Oppositional Defiant Disorder (ODD)
Characterized by an angry, irritable mood and defiant or vindictive behavior toward authority figures, ODD must persist for at least 6 months. This often leads to academic problems and social difficulties.
Intermittent Explosive Disorder (IED)
IED involves recurrent aggressive impulses that are out of proportion to the provocation. While previously viewed as an adult disorder, DSM-5-TR criteria apply to children aged 6 and older.
Conduct Disorder
This disorder involves a pattern of violating the rights of others and societal norms. It is categorized by onset:
Childhood-onset: Symptoms appear before age 10, often involving antisocial reasoning.
Adolescent-onset: Symptoms appear later, often involving peer groups.
Associated behaviors include pyromania (setting fires for pleasure) and kleptomania (compulsive stealing).
Nursing Process Application
Assessment
Nurses must assess for both self-directed and other-directed violence, especially in impulse control disorders. For somatic disorders, assessment should focus on:
Coping skills: How does the patient handle stress?
Secondary gains: What benefits (attention, avoidance) are derived from the symptoms?
Cognitive style: Does the patient distort reality (e.g., interpreting a headache as a brain tumor)?
Communication: Can the patient express emotional needs directly rather than through physical symptoms?
Interventions
Nursing management varies based on the specific disorder but generally includes:
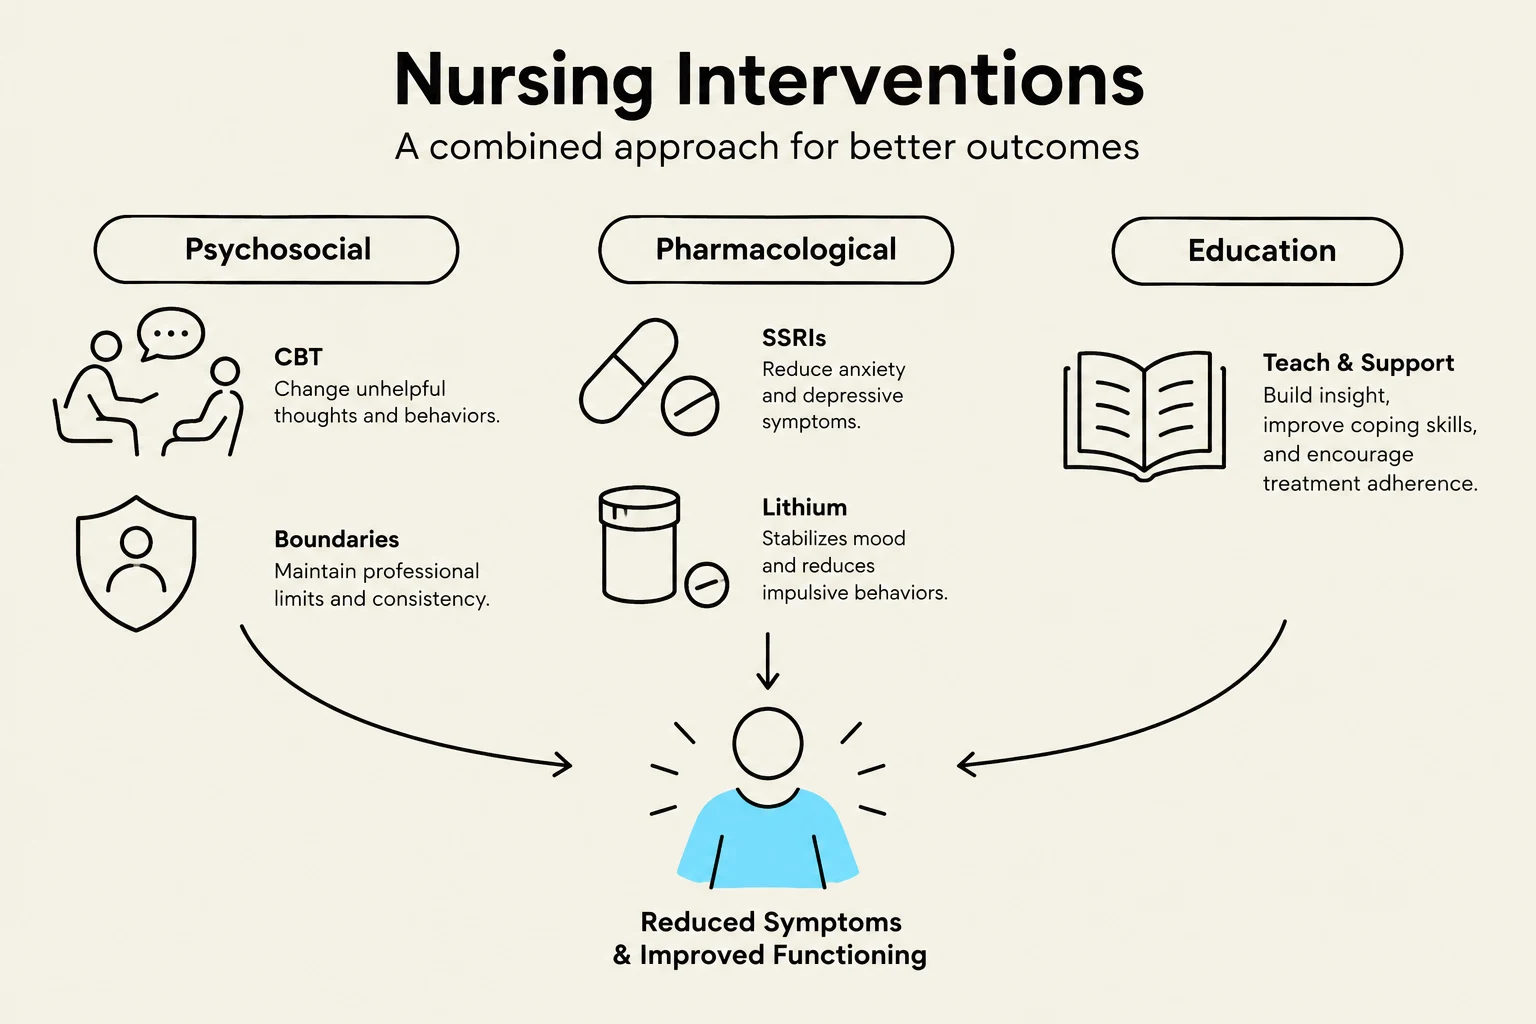
Psychosocial Interventions: Establishing boundaries, individual or group therapy, and assertiveness training. For impulse control, therapy focuses on correcting faulty personality development.
Health Teaching: Educating patients about bodily functions and stress management.
Pharmacological Management:
Somatic/Anxiety: SSRIs may be used.
Impulse Control: For explosive symptoms, medications such as SSRIs, lithium, or anticonvulsants may be indicated.
Case Management: For somatic symptom patients, case management is essential to reduce "doctor shopping" and minimize unnecessary healthcare costs.
Exam Tip: If a question asks you to differentiate between Malingering and Factitious Disorder, look for the motivation. If the patient wants money, drugs, or to avoid jail, it is Malingering. If the patient wants to be the center of attention or play the "sick role," it is Factitious Disorder.
This diagram illustrates a combined approach to nursing interventions, categorizing them into Psychosocial, Pharmacological, and Education. Psychosocial interventions include Cognitive Behavioral Therapy (CBT) and establishing boundaries. Pharmacological interventions involve medications like SSRIs and Lithium. Education focuses on teaching and support to build insight and improve coping skills. The goal of these interventions is reduced symptoms and improved functioning.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.