


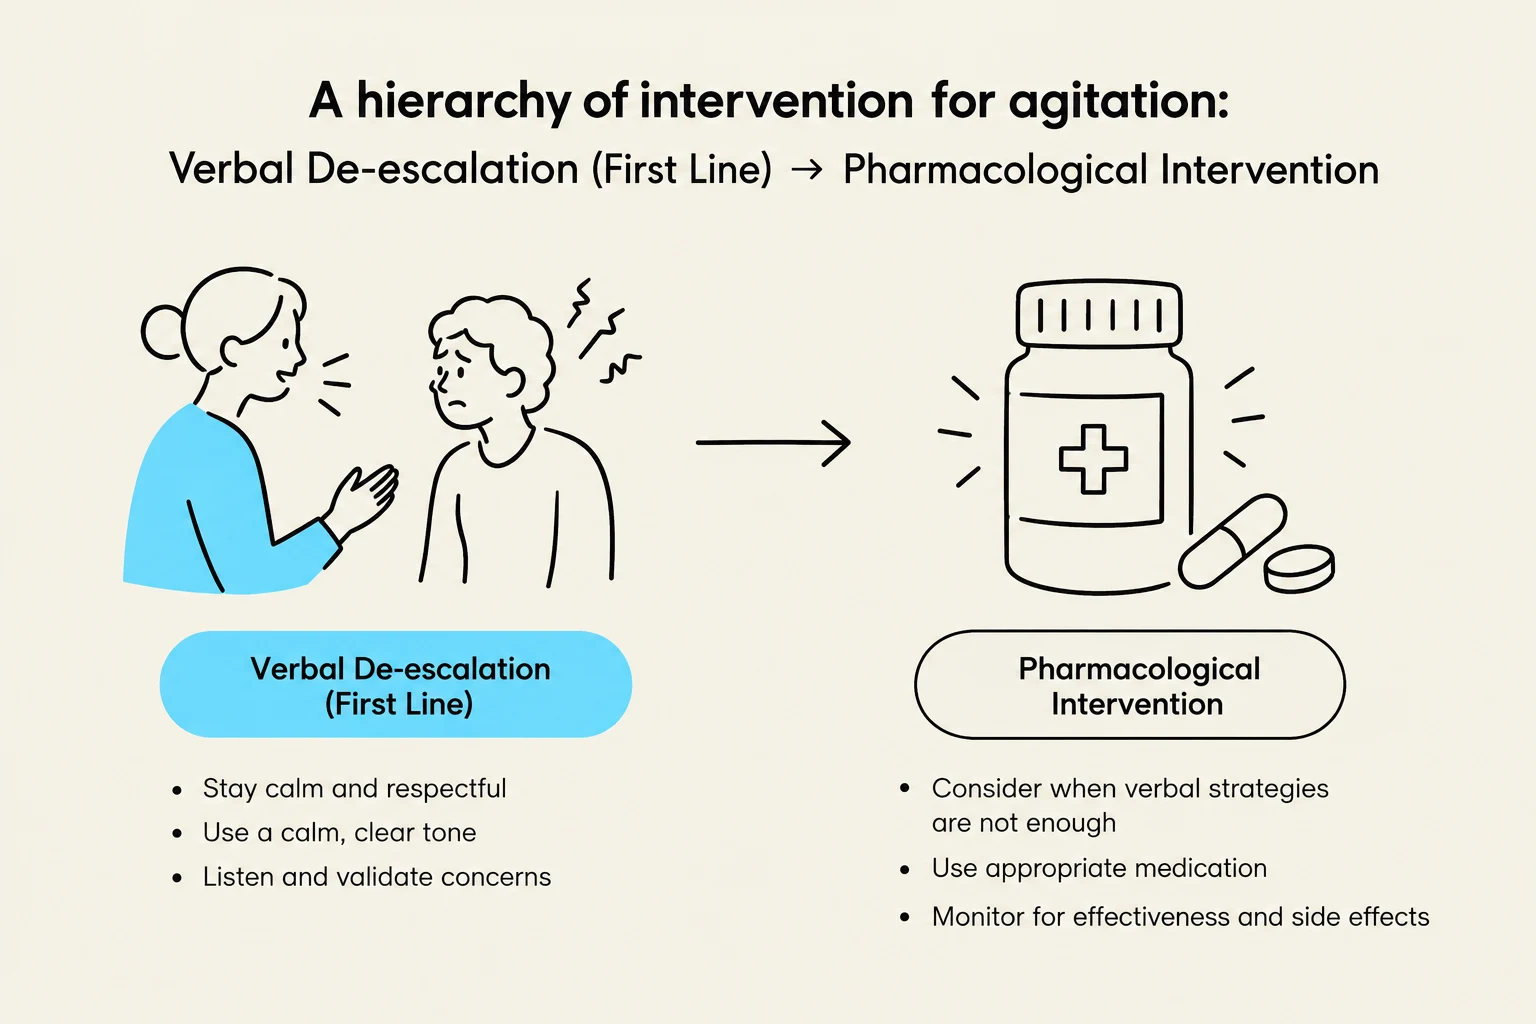
In psychiatric nursing and clinical practice, safety is the foundational priority. When a patient enters a state of crisis—whether through suicidal ideation, auditory command hallucinations, or acute physical agitation—the clinician's primary goal shifts from therapeutic rapport-building to immediate risk mitigation and stabilization. Effective crisis management requires a systematic approach to assessment, environmental control, and rapid intervention to ensure the safety of the patient, the staff, and others in the vicinity.
Assessing Suicide Risk
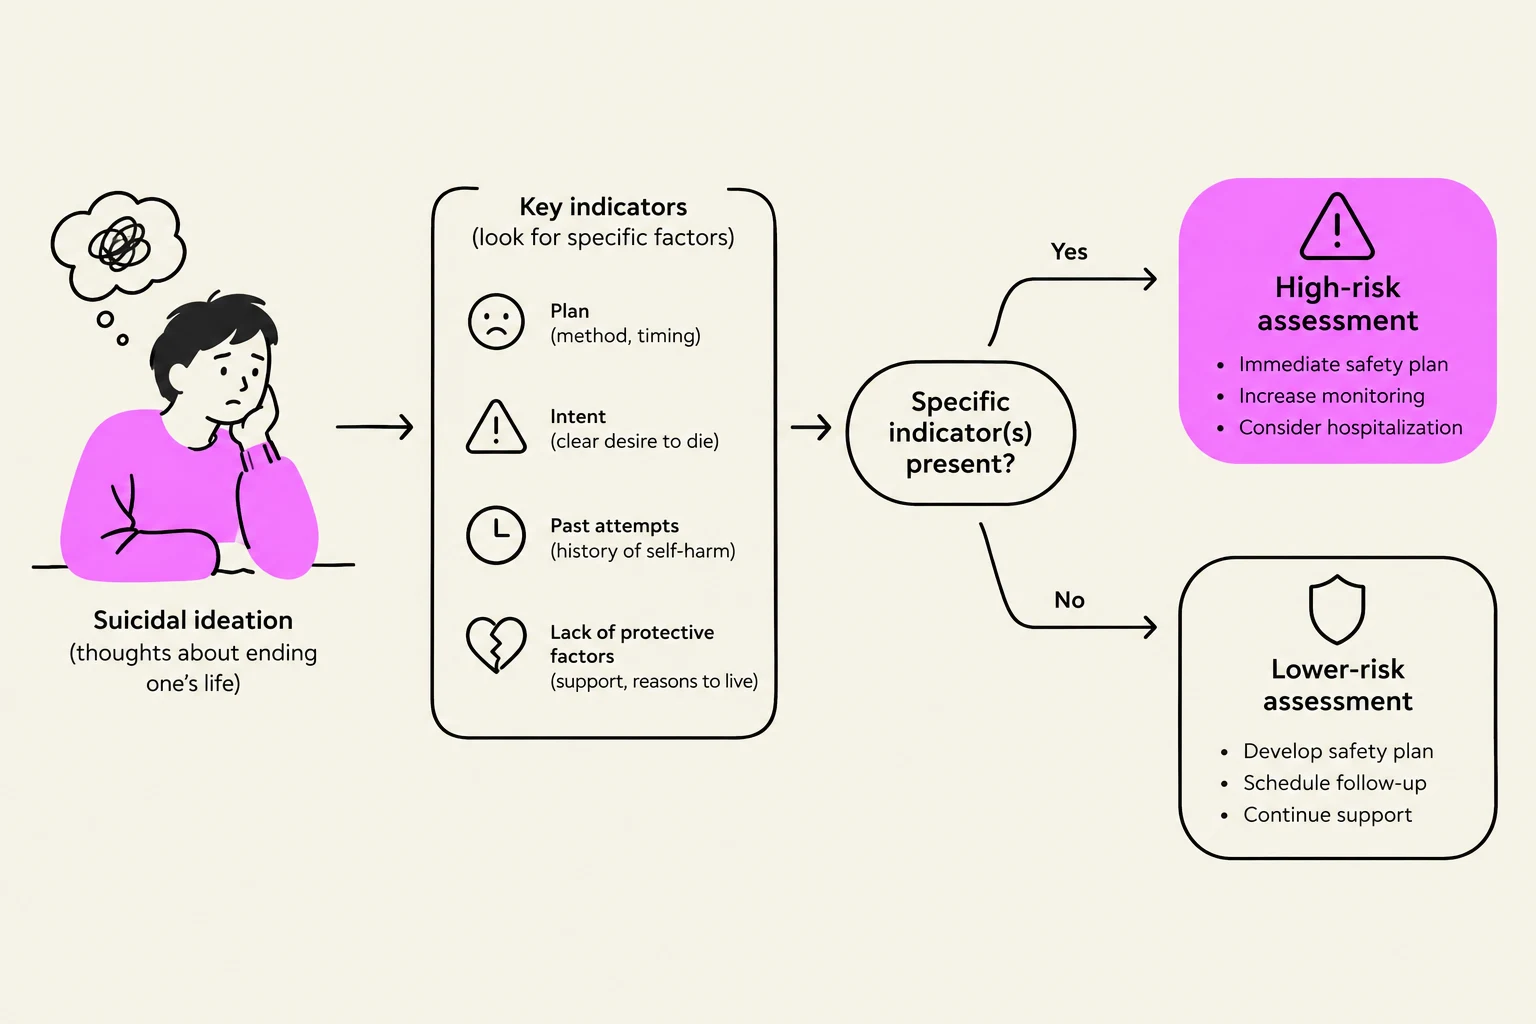
Suicide risk assessment is a continuous process rather than a one-time event. It involves evaluating a patient's intent, plan, and access to means. Clinicians must move beyond asking "Are you thinking of hurting yourself?" to more specific, probing questions that gauge the immediacy of the threat.
Key components of a suicide risk assessment include:
- Ideation: Does the patient have thoughts of death or self-harm?
- Plan: Has the patient formulated a specific method?
- Means: Does the patient have access to the tools required for their plan (e.g., medications, firearms, sharp objects)?
- Intent: How likely is the patient to act on these thoughts in the immediate future?
Exam Tip: When assessing suicide risk, always ask directly about the patient's plan and access to means. Asking about suicide does not "plant the seed"; rather, it provides a vital opportunity for intervention and demonstrates that you are a safe person to talk to.
Managing Command Hallucinations
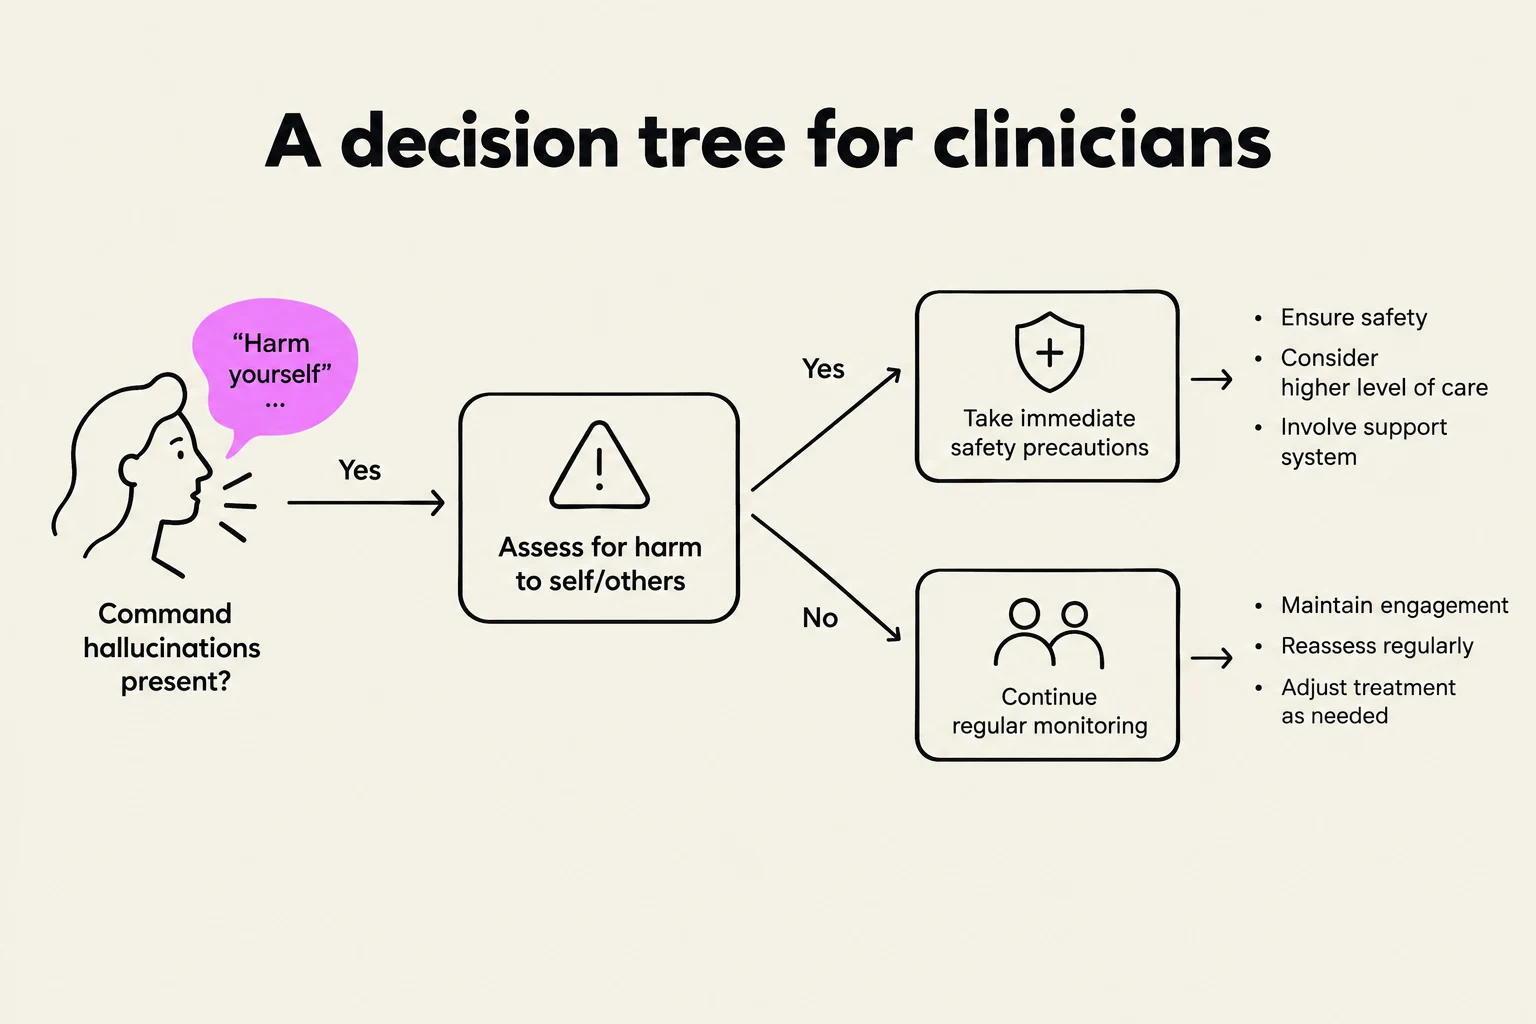
Command hallucinations occur when a patient hears voices that instruct them to perform specific actions. These are particularly dangerous because the "command" may direct the patient to harm themselves or others.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.
Continue reading freeAlready have an account? Log in
Updated