Respiratory Gas Exchange: Oxygen Transport and pH Regulation
Explains the essential processes of oxygen transport by hemoglobin, the factors influencing the oxyhemoglobin dissociation curve, and the bicarbonate buffer system's role in maintaining blood pH. Covers carbon dioxide transport and the Bohr effect.
The survival of every cell in the human body depends on a continuous supply of oxygen (O2) for aerobic metabolism and the efficient removal of carbon dioxide (CO2), a metabolic byproduct. This process, known as respiratory gas exchange, is not merely a matter of breathing air in and out; it involves complex biochemical transport mechanisms, specialized proteins, and sophisticated buffering systems that ensure gases reach their destinations and the blood maintains a stable pH.
Oxygen Transport and the Role of Hemoglobin
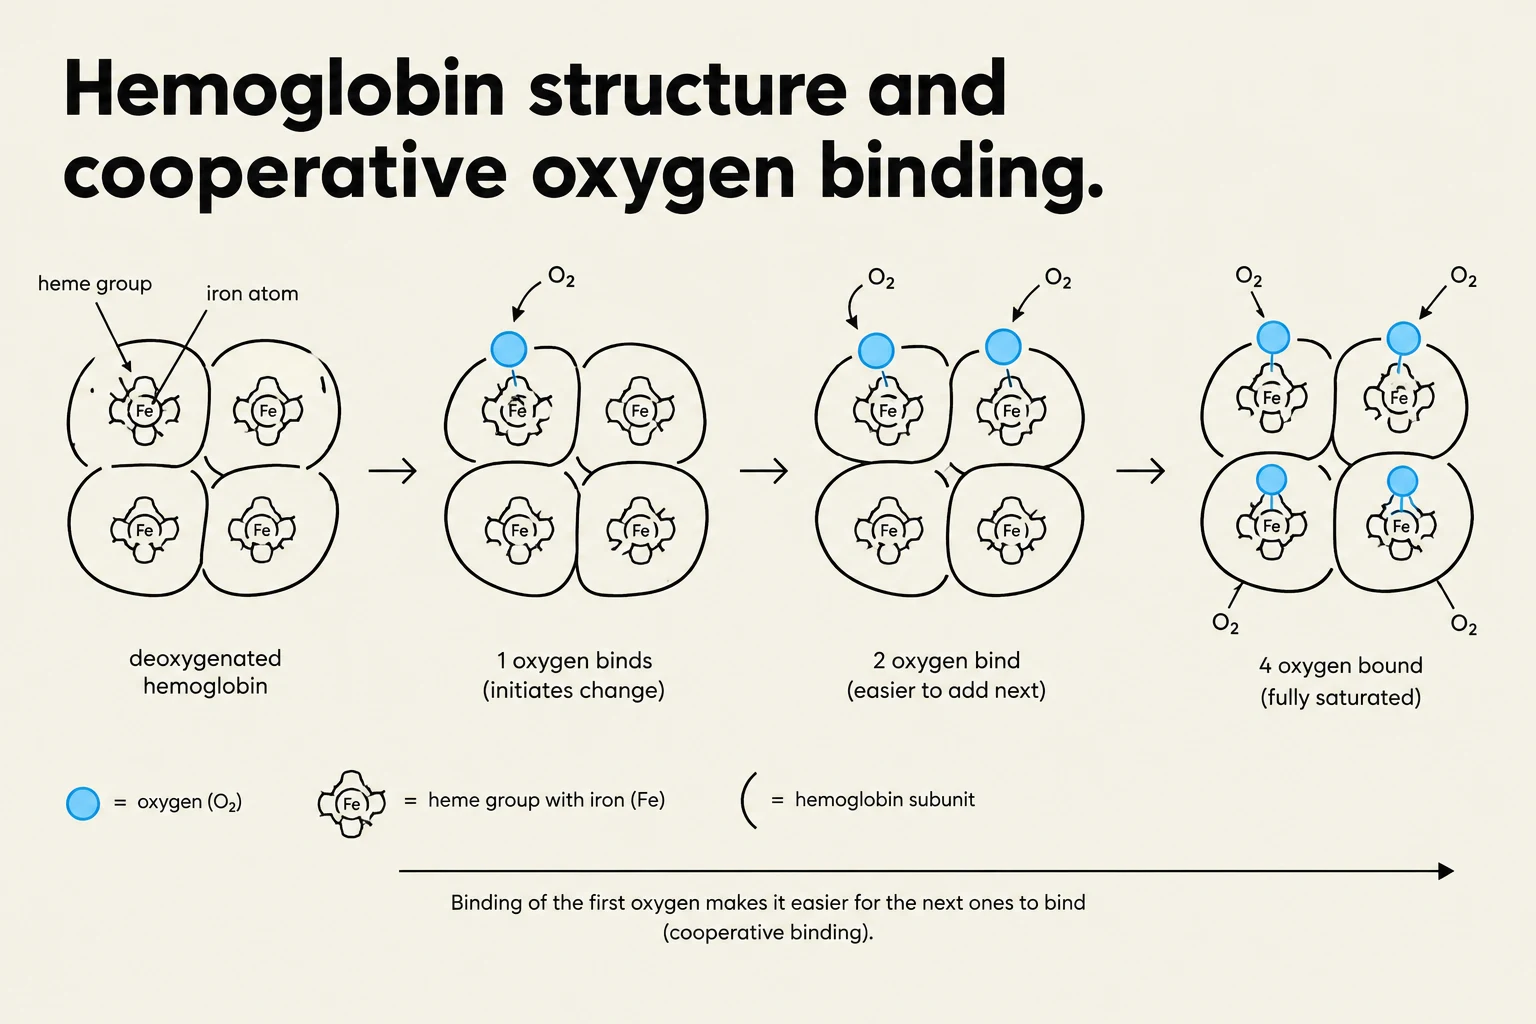
This diagram illustrates the structure of hemoglobin and how oxygen molecules bind to it cooperatively. It shows the transition from deoxygenated hemoglobin to fully saturated hemoglobin as oxygen binds to the heme groups containing iron atoms.
While a small amount of oxygen dissolves directly into the blood plasma, the solubility of O2 in liquid is extremely low. To meet the high metabolic demands of tissues, the body relies on hemoglobin, a specialized protein found within red blood cells.
Each hemoglobin molecule consists of four polypeptide subunits, each containing an iron-bearing heme group. This structure allows a single hemoglobin molecule to bind up to four molecules of oxygen. The binding process is highly efficient due to a phenomenon called cooperativity: when one oxygen molecule binds to a heme group, it induces a conformational change in the protein structure that increases the affinity of the remaining heme groups for oxygen.
The Oxyhemoglobin Dissociation Curve
The oxyhemoglobin dissociation curve and Bohr effect shifts.
The relationship between the partial pressure of oxygen (PO2) and the percentage of hemoglobin saturation is represented by the oxyhemoglobin dissociation curve. This curve is characteristically sigmoidal (S-shaped), which is a direct result of the cooperative binding mentioned above.
Understanding the Curve's Shape
The Plateau (Lungs): At high PO2 (such as in the pulmonary capillaries), the curve levels off. This ensures that even if the alveolar PO2 drops slightly, hemoglobin remains nearly fully saturated, providing a safety margin for oxygen uptake.
The Steep Portion (Tissues): As blood moves into the systemic tissues where PO2 is lower, the curve becomes very steep. This allows for the rapid and efficient unloading of oxygen exactly where it is needed most.
Factors Shifting the Curve
The affinity of hemoglobin for oxygen is not static; it changes based on the local chemical environment of the tissues. A "shift" in the curve determines whether hemoglobin holds onto oxygen more tightly or releases it more readily.
Right Shift (Decreased Affinity): When hemoglobin's affinity for O2 decreases, it releases oxygen more easily to the tissues. This is often triggered by:
Increased partial pressure of CO2 (PCO2)
Decreased pH (increased acidity/H+ ions)
Increased temperature
Increased 2,3-BPG (a metabolic byproduct)
Note: This is often referred to as the Bohr Effect.
Left Shift (Increased Affinity): When hemoglobin holds onto oxygen more tightly, the curve shifts left. This occurs during:
Decreased PCO2
Increased pH (alkalinity)
Decreased temperature.
Exam Tip: If a question asks how a fever affects oxygen delivery, remember that increased temperature causes a right shift. This decreases hemoglobin's affinity for O2, meaning it "drops off" more oxygen to the metabolically active (and hot) tissues.
Carbon Dioxide Transport and the Bicarbonate Buffer System
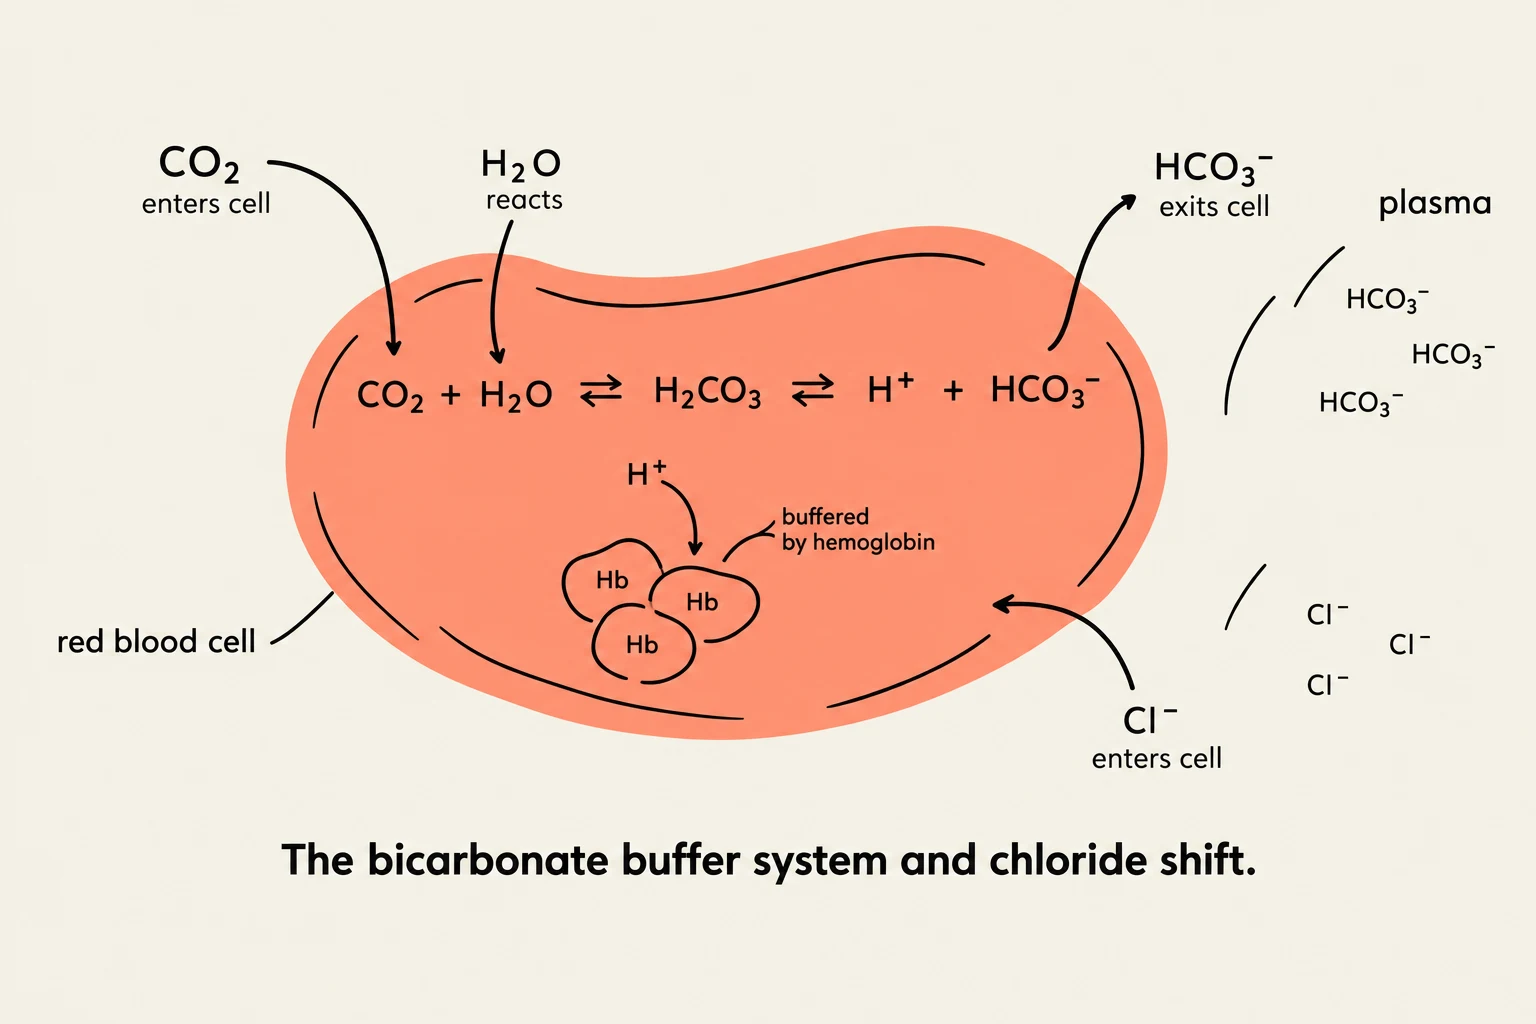
The bicarbonate buffer system and chloride shift.
While oxygen is being delivered, carbon dioxide must be transported from the tissues back to the lungs. CO2 is transported in three main ways: dissolved in plasma, bound to hemoglobin (carbaminohemoglobin), or as bicarbonate ions.
The most significant method of transport is via the bicarbonate buffer system. This system is vital not only for transporting CO2 but also for regulating the pH of the blood, which must stay within a narrow range (approximately 7.35 to 7.45) to maintain homeostasis.
The Chemical Mechanism
When CO2 enters the red blood cell, it reacts with water (H2O) to form carbonic acid (H2CO3). This reaction is catalyzed by the enzyme carbonic anhydrase. The carbonic acid then spontaneously dissociates into a hydrogen ion ($H^+$) and a bicarbonate ion (HCO3−).
The equilibrium can be expressed by the following equation:
CO2+H2O⇌H2CO3⇌H++HCO3−
pH Regulation and the Chloride Shift
As the reaction proceeds, the production of $H^+$ ions can lower the pH (making the blood more acidic). To prevent this, the $H^+$ ions are buffered by hemoglobin. Meanwhile, the bicarbonate ions (HCO3−) diffuse out of the red blood cell into the plasma.
To maintain electrical neutrality, as the negatively charged bicarbonate leaves the cell, negatively charged chloride ions ($Cl^-$) move from the plasma into the red blood cell. This process is known as the chloride shift.
Summary Table: Gas Exchange Dynamics
Factor
Effect on O2 Affinity
Curve Shift
Physiological Context
↑PCO2
Decrease
Right
Active metabolism/Exercise
↓ pH (Acidosis)
Decrease
Right
Lactic acid buildup
↑ Temperature
Decrease
Right
Fever or intense exercise
↓PCO2
Increase
Left
Hyperventilation
By integrating the cooperative binding of hemoglobin with the chemical buffering of the bicarbonate system, the body ensures that gas exchange is not just a passive movement of molecules, but a highly regulated response to the metabolic needs of the organism.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.