This content covers the pathophysiology, clinical management, and nursing interventions for renal diseases, including obstruction, infection, glomerular disorders, and end-stage renal disease (ESRD). It details dialysis modalities, transplantation, fluid management, hypertension treatment, nutritional therapy, and phar
The renal system is a complex regulatory network responsible for filtering metabolic waste, maintaining electrolyte balance, and regulating blood pressure and fluid volume. When the kidneys fail to perform these functions—whether due to acute obstruction, infection, or chronic glomerular damage—the body enters a state of metabolic crisis. For healthcare providers, managing renal disease requires a multifaceted approach encompassing precise pharmacological dosing, specialized dialysis modalities, strict nutritional control, and vigilant post-operative monitoring.
Pathophysiology of Renal Obstruction and Infection
Urinary tract obstructions (obstructive uropathy) occur when the flow of urine is interfered with along the urinary tract. This can be caused by tumors, stones, or trauma. A significant consequence of obstruction is hydronephrosis, which is the enlargement of the renal calyces due to a retrograde increase in hydrostatic pressure within the renal pelvis. If the obstruction is acute and complete, it can lead to a rapid decrease in the Glomerular Filtration Rate (GFR) and subsequent renal failure.
Kidney stones (renal calculi) are a common cause of obstruction. These can consist of calcium salts, uric acid crystals (often associated with gout), struvite (associated with urea-splitting organisms), or cystine (a hereditary disorder). Large stones, such as staghorn calculi, can fill the renal pelvis and require surgical intervention.
Infections also play a critical role in renal health. Cystitis (bladder inflammation) and urethritis (urethral inflammation) are common lower urinary tract infections. If bacteria ascend the ureters, they can cause acute pyelonephritis, an infection of the renal pelvis, calyces, and medulla. Chronic pyelonephritis can lead to progressive inflammation, fibrosis, and permanent tubule destruction, eventually progressing to renal failure.
Glomerular Disorders and End-Stage Renal Disease (ESRD)
Glomerular disorders involve inflammation of the glomerulus, often caused by infections, toxins, or immune responses. A classic example is Acute Post-streptococcal Glomerulonephritis (APSGN), which occurs 7–10 days after a streptococcal infection. This condition is characterized by hematuria, RBC casts, proteinuria, hypertension, and edema.
When kidney damage becomes irreversible and the GFR drops below 15 mL/min, the patient reaches End-Stage Renal Disease (ESRD). At this stage, the kidneys can no longer filter wastes, leading to dangerous accumulations of fluid, electrolytes, and metabolic toxins.
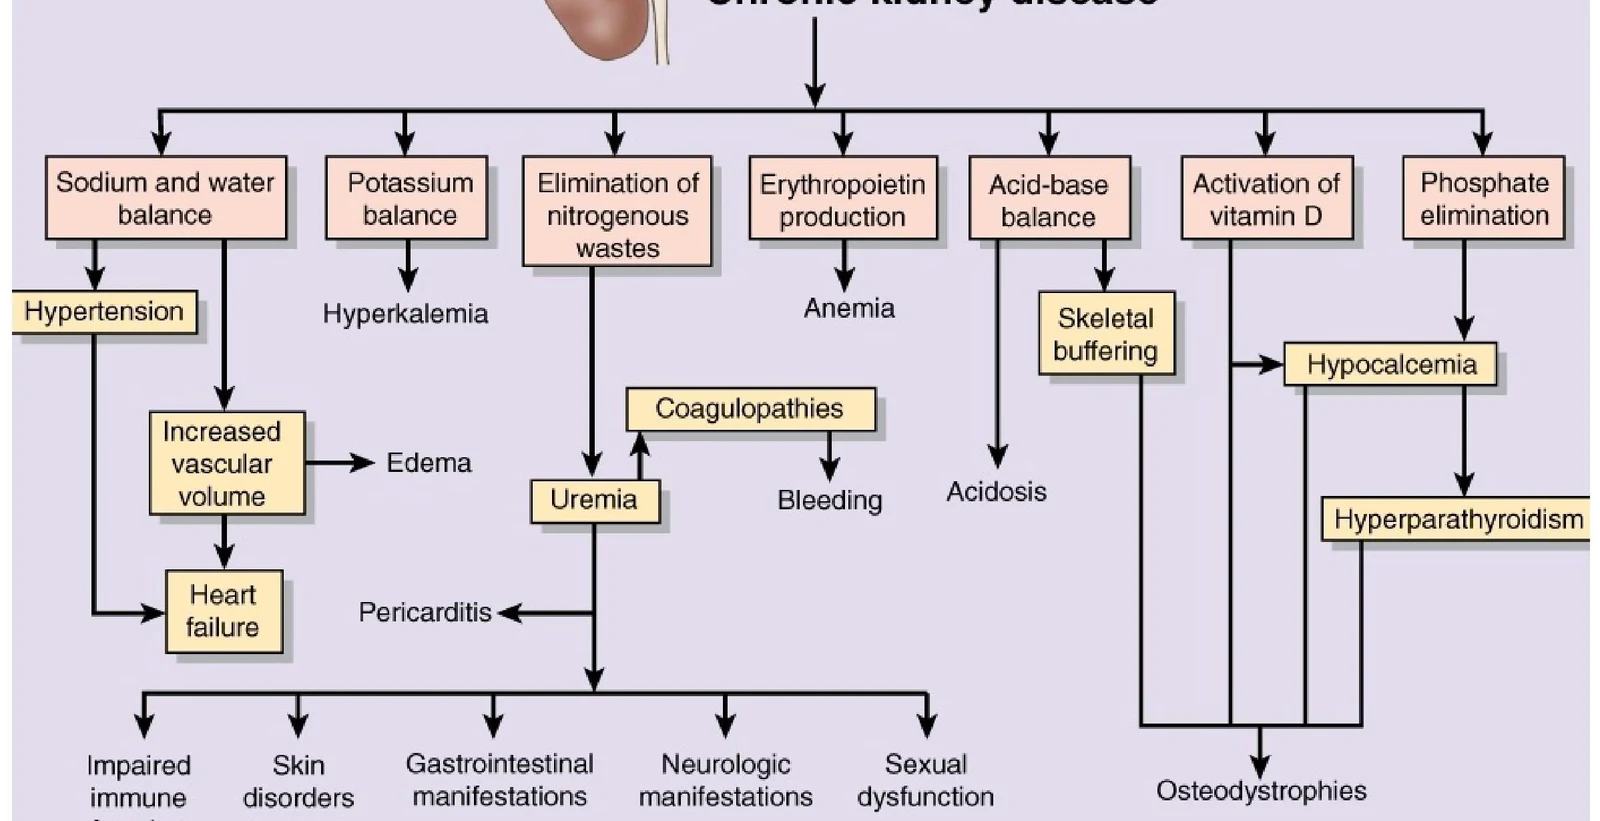
This diagram illustrates the various complications of chronic kidney disease, including effects on sodium and water balance, potassium balance, waste elimination, erythropoietin production, acid-base balance, vitamin D activation, and phosphate elimination, leading to conditions like hypertension, hyperkalemia, anemia, edema, uremia, acidosis, hypocalcemia, and ultimately osteodystrophies.
Clinical Management: Dialysis and Transplantation
Patients with ESRD require renal replacement therapies to maintain homeostasis.
Dialysis Modalities
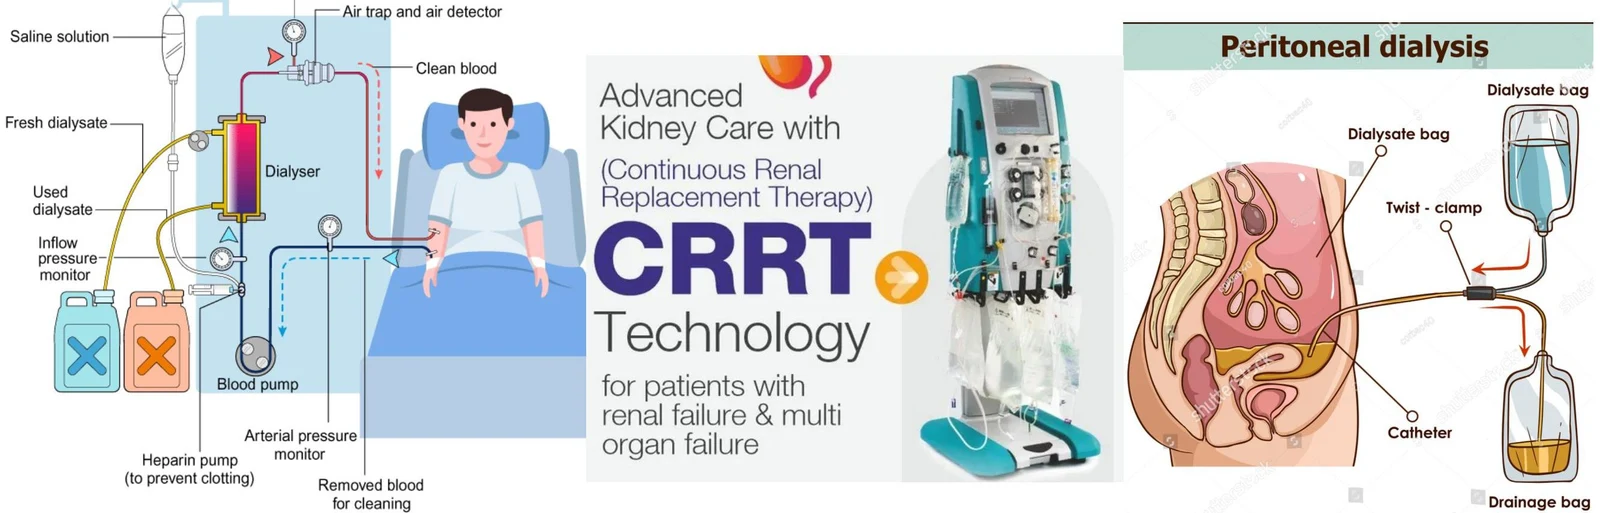
Hemodialysis: Uses a vascular access point (such as an arteriovenous fistula, graft, or central venous catheter) to filter blood through a machine.
Peritoneal Dialysis: Uses the patient's peritoneal membrane as a filter. A catheter is inserted into the abdominal cavity to facilitate the exchange of fluids.
Continuous Renal Replacement Therapy (CRRT): A specialized form of dialysis used for hemodynamically unstable patients.
Diagrams illustrating hemodialysis and peritoneal dialysis procedures.
Kidney Transplantation
Transplantation is often the preferred treatment for ESRD and is most successful if performed before the onset of dialysis. Success depends heavily on HLA and ABO compatibility.
Nursing Alert: Post-Operative Monitoring
After a kidney transplant, nurses must vigilantly monitor for signs of rejection. Key indicators include:
Oliguria (decreased urine output)
Fever and increasing blood pressure
Edema and weight gain
Tenderness or swelling over the transplanted area (iliac fossa)
Rising creatinine levels (which may be the only sign in patients on cyclosporine)
Nursing Interventions and Clinical Care
Managing Excess Fluid Volume
A primary nursing diagnosis for patients with ESRD is Excess Fluid Volume related to decreased glomerular filtration. This occurs because high hydrostatic pressure pushes excess fluid into the interstitial spaces, resulting in peripheral edema.
Nursing Interventions for Fluid Management:
Strict I&O Monitoring: Record all intake and output every shift to prevent fluid overload.
Vital Sign Assessment: Monitor heart rate, blood pressure, and respiratory rate every 2 hours; increases in these values can signal rising fluid volume.
Edema Assessment: Monitor the grade of peripheral edema.
Hypertension Treatment Algorithm
Hypertension is a frequent complication of renal disease. Management follows a structured approach based on severity:
Stage
Blood Pressure (mmHg)
Recommended Treatment
Stage 1
SBP 140–159 or DBP 90–99
Thiazide-type diuretics; consider ACEI, ARB, BB, or CCB
Note: For patients with "compelling indications," specific drugs for those indications should be prioritized alongside standard antihypertensives.
Nutritional Therapy
Nutritional management is critical to minimize metabolic demands and prevent the accumulation of toxins.
This diagram illustrates the progression of Chronic Kidney Disease (CKD), outlining risk factors, stages of the disease (Early CKD, Declining eGFR, Kidney Failure), and corresponding diet and nutrition interventions.
Dietary interventions typically involve:
Fluid Restriction: To manage edema and hypertension.
Electrolyte Control: Managing intake of potassium, sodium, and phosphorus to prevent life-threatening imbalances.
Pharmacological Considerations and Risks
When administering medications to renal patients, clinicians must be aware of renal dosing principles—adjusting dosages based on the patient's decreased GFR to prevent toxicity.
Furthermore, clinicians must be cautious with Radio Opaque Contrast media, as these can pose risks to patients with compromised renal function. Always assess baseline creatinine and hydration status before procedures involving contrast.
Exam Tip: Electrolyte Emergencies
In cases of severe hyperkalemia (high potassium), remember the emergency interventions:
Calcium Gluconate: To protect the heart from cardiac effects.
Insulin: To drive potassium into the cells.
Kayexalate: To facilitate potassium excretion.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.