Explores the mechanics of breathing, including airflow resistance, pulmonary elasticity (compliance and recoil), and alveolar surface tension. Discusses the role of surfactant and lung volumes like minute ventilation and alveolar ventilation.
The ability to breathe effectively depends on a complex interplay of physical forces, chemical regulators, and anatomical structures. To move air in and out of the body, the respiratory system must overcome resistance in the airways, manage the elastic properties of lung tissue, and stabilize the microscopic air sacs known as alveoli. Understanding these mechanics requires a deep dive into how pressure gradients, surface tension, and the autonomic nervous system work together to maintain homeostasis.
Airflow Resistance and Bronchial Control
Airflow is driven by a pressure gradient: air moves from areas of higher pressure to areas of lower pressure. The ease with which this air moves is determined by airflow resistance, which is primarily controlled by the radius of the airways.
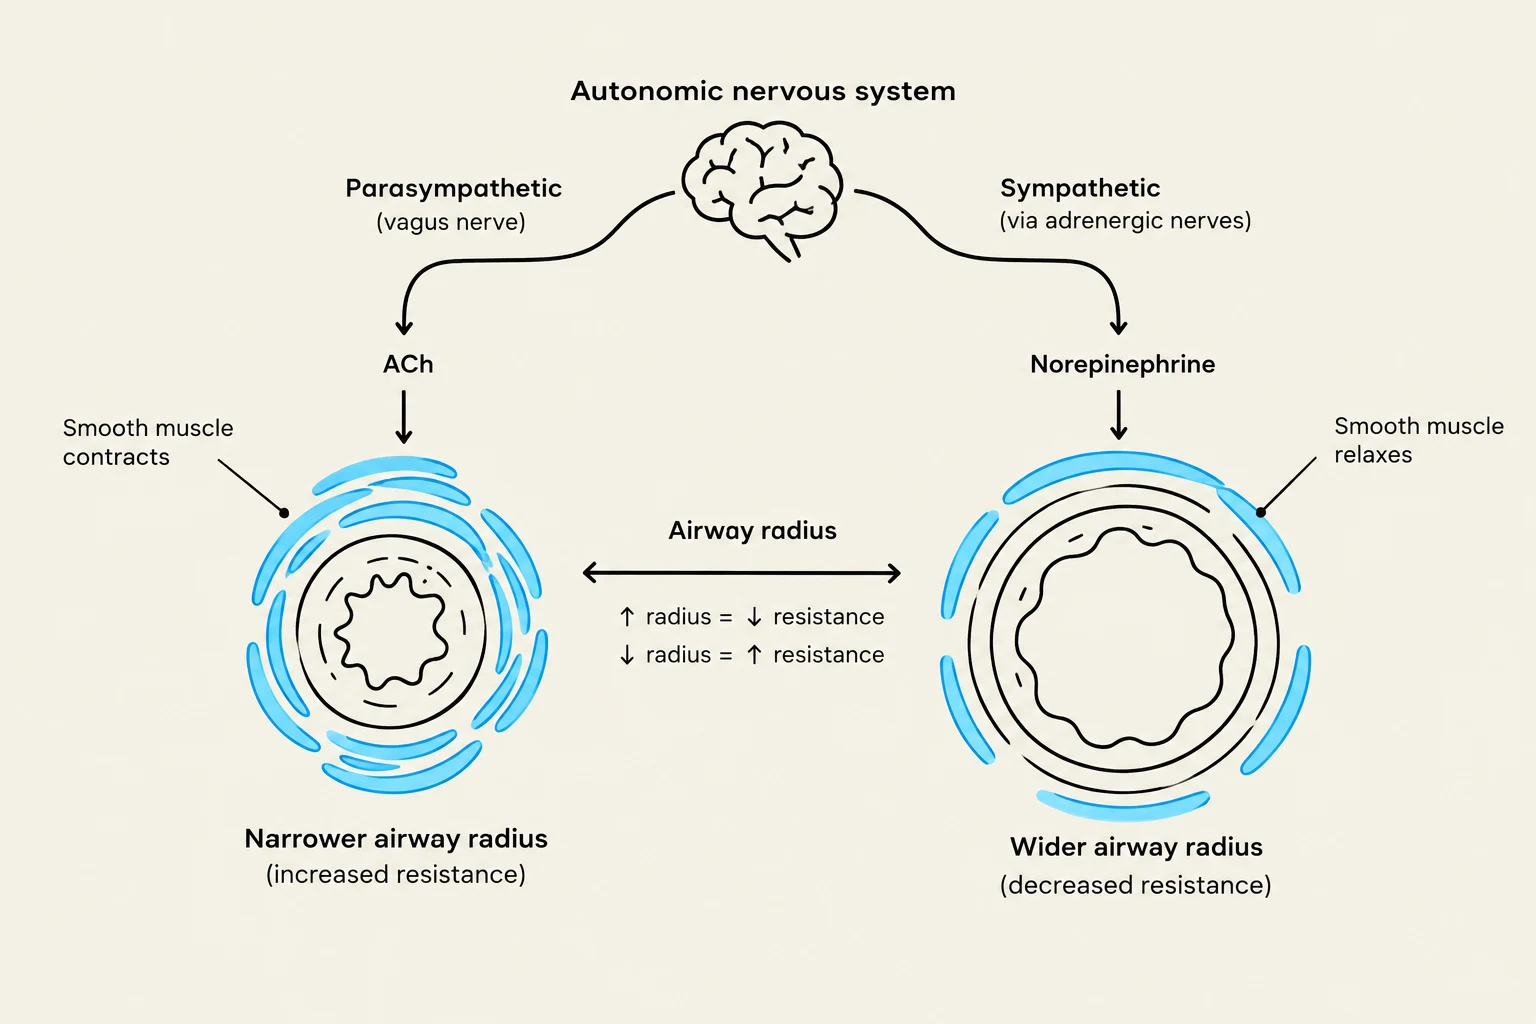
The diameter of the bronchioles is regulated by the smooth muscle surrounding them, which is under the control of the autonomic nervous system:
Bronchodilation: The sympathetic nervous system (SNS) promotes smooth muscle relaxation, increasing the airway radius and decreasing resistance.
Bronchoconstriction: The parasympathetic nervous system (PNS) promotes smooth muscle contraction, decreasing the airway radius and increasing resistance.
Pathological conditions like asthma can lead to excessive bronchoconstriction, significantly increasing the work required to breathe.
This diagram illustrates how the autonomic nervous system regulates airway radius. The parasympathetic nervous system, via acetylcholine (ACh), causes smooth muscle contraction, leading to a narrower airway and increased resistance. Conversely, the sympathetic nervous system, via norepinephrine, causes smooth muscle relaxation, resulting in a wider airway and decreased resistance.
Pulmonary Elasticity: Compliance and Recoil
The lungs are not rigid structures; they possess unique elastic properties that allow them to expand and contract. This "elastic behavior" is a result of both the elastic connective tissue within the lung parenchyma and the surface tension at the alveolar level. Two key concepts define this behavior:
Compliance (C): This is a measure of the lung's distensibility, or how easily it can be stretched. It is mathematically expressed as the change in volume (ΔV) divided by the change in pressure (ΔP):
C=ΔPΔV
Elastic Recoil: This is the tendency of the lungs to return to their original shape after being stretched. This recoil is essential for passive expiration, as the inward pull of the lungs helps push air out when the inspiratory muscles relax.
Exam Tip: Remember that compliance and elastic recoil are inversely related in a functional sense. High compliance means the lungs stretch easily but may have difficulty recoiling, whereas high elastic recoil means the lungs snap back strongly but may be difficult to inflate.
Alveolar Surface Tension and the Role of Surfactant
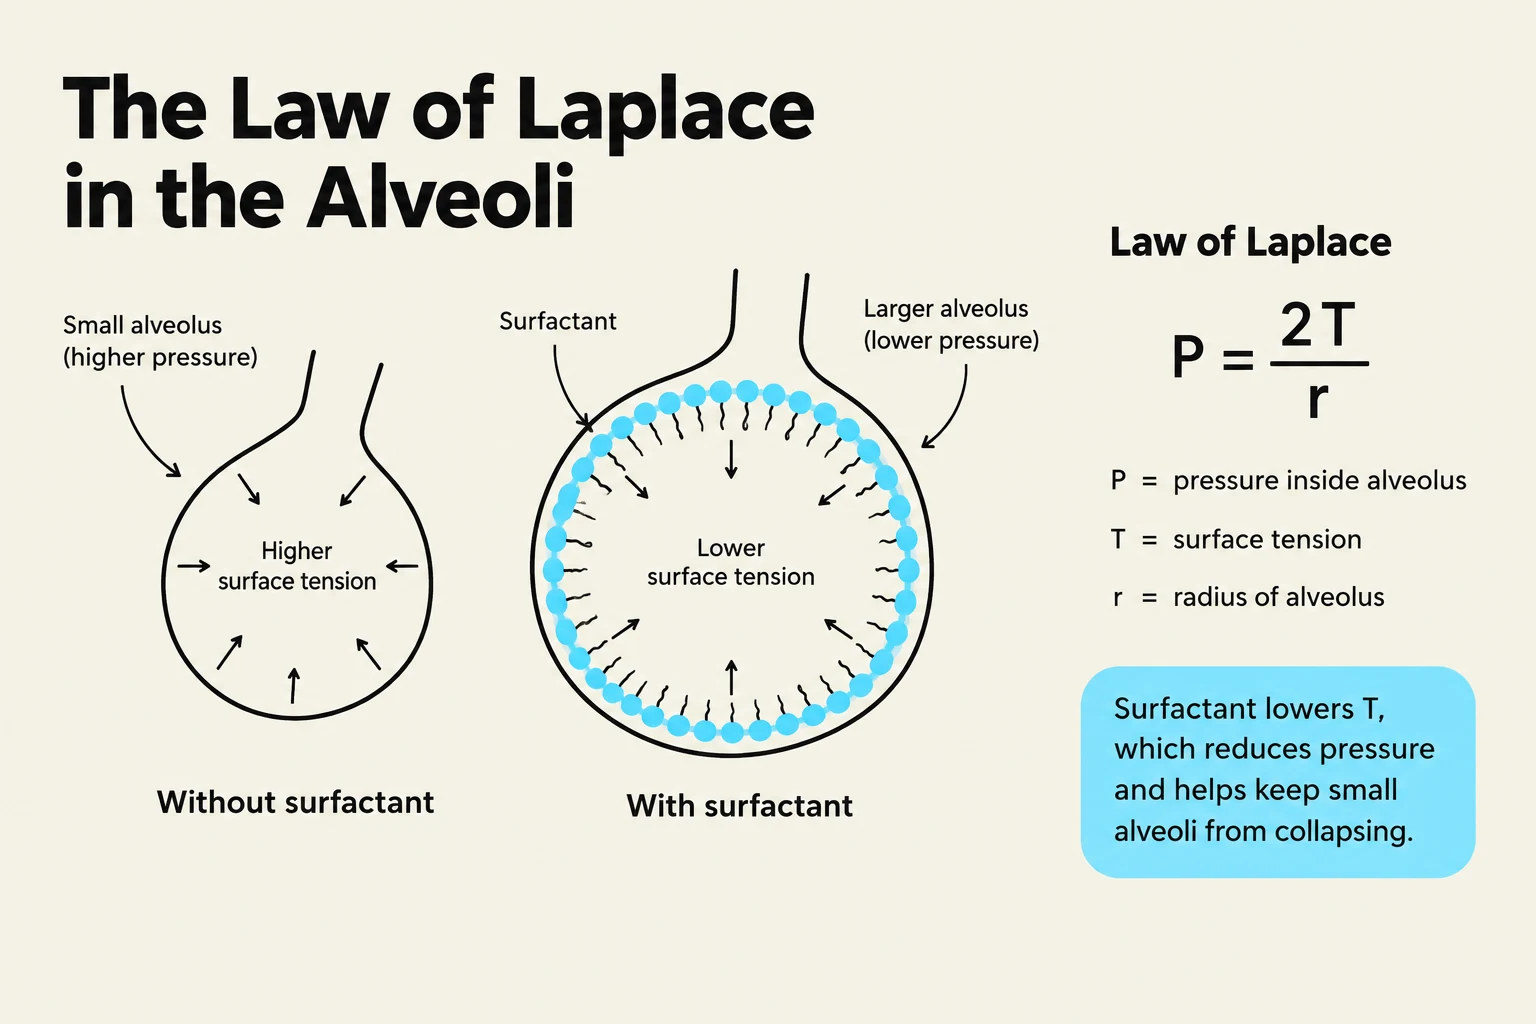
At the microscopic level, the alveoli are lined with a thin layer of water. Because water molecules are highly attracted to one another, they create alveolar surface tension. This surface tension creates an inward force that resists the expansion of the alveoli (decreasing compliance) and promotes the shrinking of the alveolar size.
The tendency of these small air sacs to collapse is described by the Law of Laplace, which states that the pressure (P) required to keep a bubble (or alveolus) inflated is proportional to the surface tension (T) and inversely proportional to the radius (r):
P=r2T
According to this law, smaller alveoli have a much greater tendency to collapse than larger ones.
To prevent this collapse, Type II alveolar cells secrete pulmonary surfactant. Surfactant is composed of approximately 90% lipids and 10% proteins. The lipids interfere with the interaction between water molecules, effectively reducing surface tension. This provides several critical benefits:
Increased Compliance: It makes the lungs easier to inflate.
Stabilization: It helps keep alveolar sizes relatively uniform during the respiratory cycle, preventing small alveoli from collapsing into larger ones.
Fluid Regulation: By reducing surface tension, it minimizes fluid accumulation in the alveoli, which preserves the efficiency of gas diffusion.
This diagram illustrates the Law of Laplace as applied to alveoli, explaining how surfactant reduces surface tension and pressure, preventing small alveoli from collapsing.
Lung Volumes and Ventilation
To quantify respiratory function, we measure various lung volumes and capacities. While total lung volume varies by sex (approximately 5.7L in men and 4.2L in women), clinicians focus on how much air is actually participating in gas exchange.
It is vital to distinguish between total air moved and air that actually reaches the gas-exchange surfaces:
Minute Ventilation (Pulmonary Ventilation): The total volume of air breathed in and out in one minute.
Minute Ventilation=Tidal Volume (TV)×Respiratory Rate (RR)
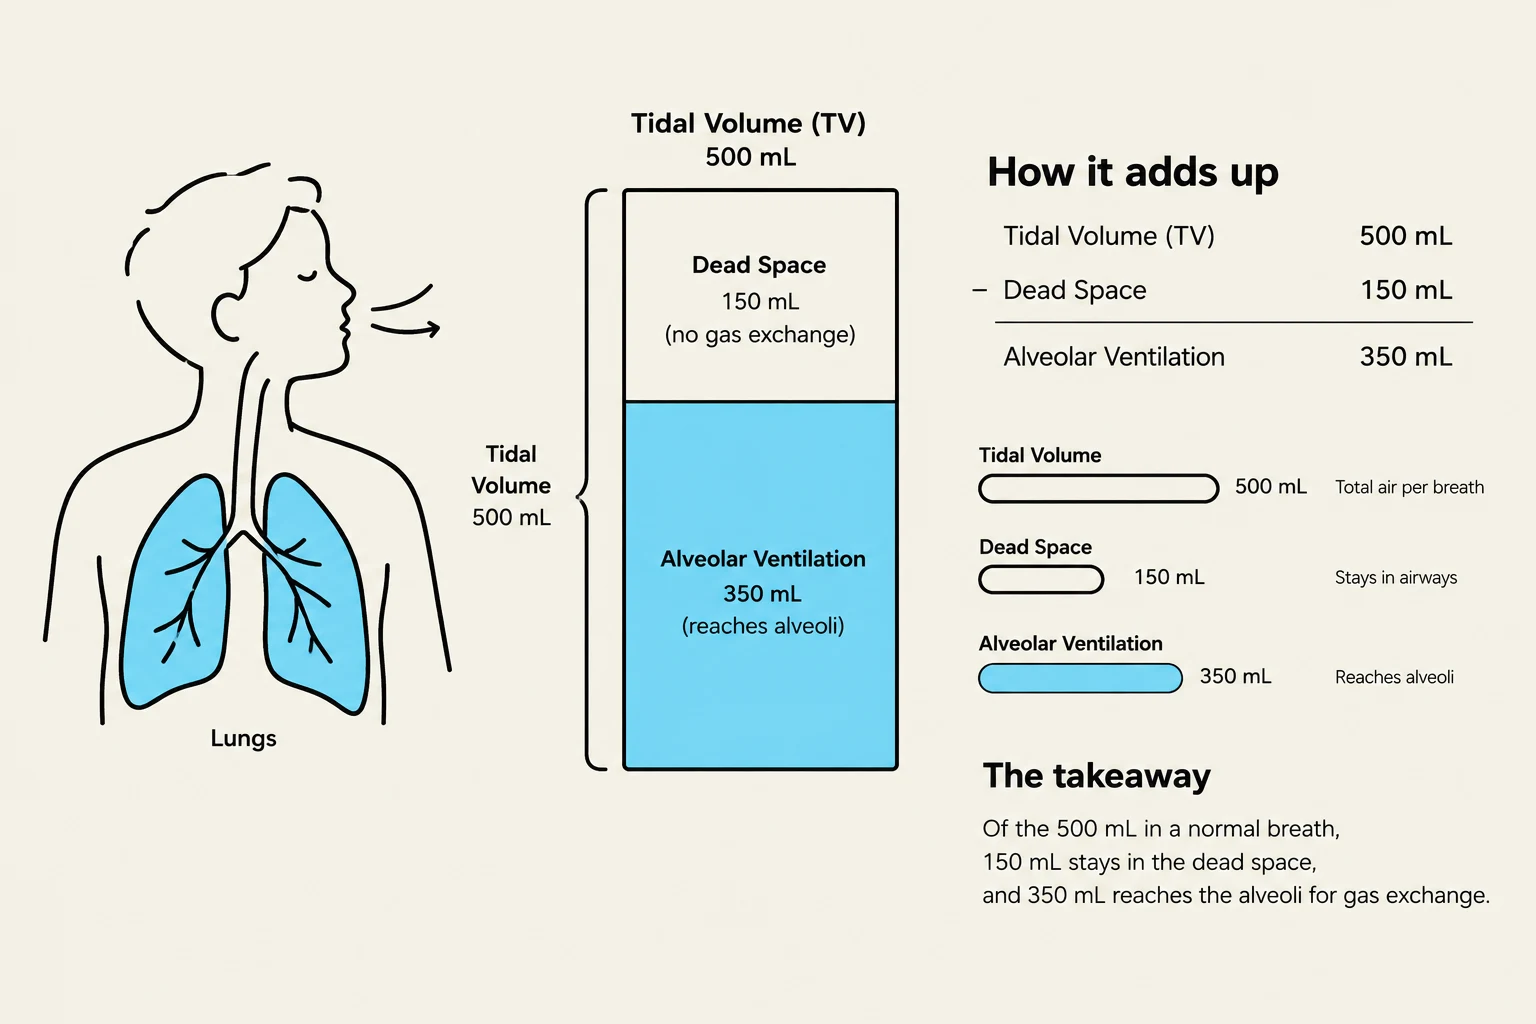
Anatomical Dead Space: The volume of air within the conducting airways (trachea, bronchi, etc.) where no gas exchange occurs.
Alveolar Ventilation: The actual volume of fresh air that reaches the alveoli per minute.
Alveolar Ventilation=(TV−Dead Space Volume)×RR
This diagram illustrates the concept of tidal volume and alveolar ventilation in the human respiratory system, showing how a normal breath of 500 mL is divided into dead space (150 mL) and alveolar ventilation (350 mL).
Note: Even during normal breathing, a significant portion of ventilation (roughly 30%) is "wasted" on dead space because that air never reaches the respiratory zone for gas exchange.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.