


Preparing for the Psychiatric-Mental Health Nurse Practitioner-Board Certified (PMHNP-BC) examination requires more than just memorizing drug names; it demands a deep understanding of clinical nuances, the ability to differentiate between similar presentations, and a firm grasp of legal and ethical standards. This review synthesizes high-yield clinical scenarios to help you navigate complex diagnostic dilemmas, medication management, and therapeutic interventions.
Differential Diagnosis and Clinical Presentation
One of the most challenging aspects of the PMHNP role is distinguishing between psychiatric symptoms and organic medical conditions.
Mood and Stress Disorders
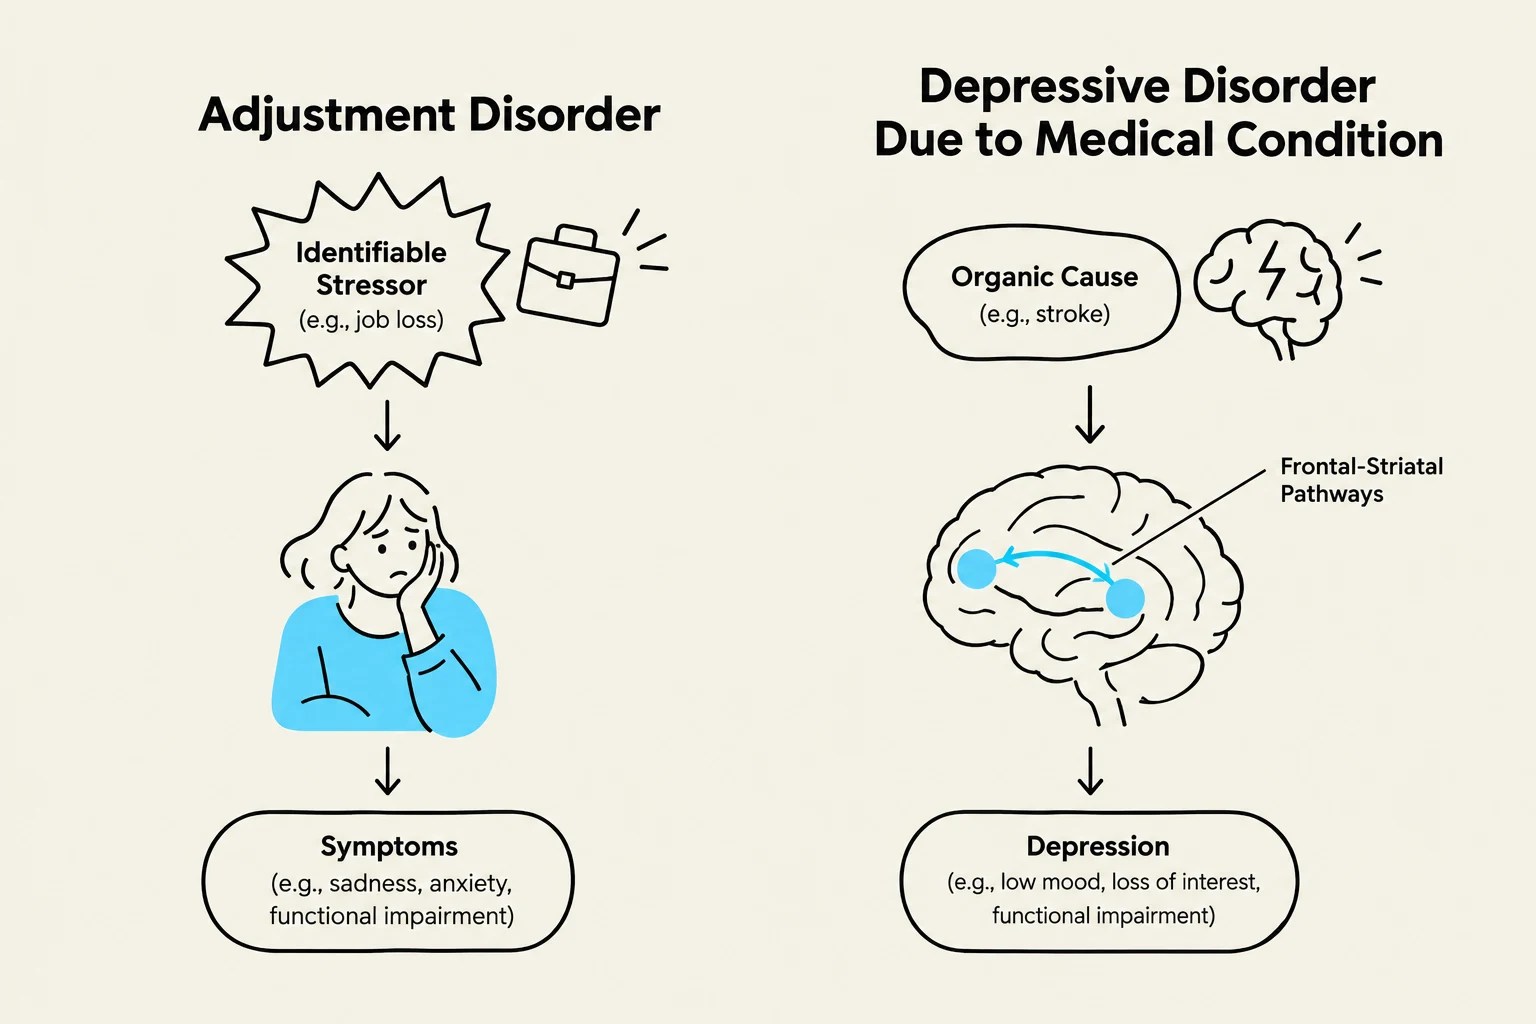
When evaluating a patient with depressive symptoms, you must differentiate between Adjustment Disorder and Depressive Disorder Due to a Medical Condition. Adjustment Disorder involves emotional or behavioral symptoms that develop within three months of an identifiable stressor (such as job loss or a medical diagnosis) but do not meet the full criteria for another disorder. In contrast, Depressive Disorder Due to a Medical Condition occurs when the depression is a direct organic consequence of physical brain tissue damage, such as a stroke affecting the frontal-striatal pathways.
Neurological and Developmental Red Flags
Clinical assessment often involves identifying "red flags" that point toward neurological rather than purely psychological etiologies:
- Moro (Startle) Reflex: This is a normal finding in infancy but must disappear by 4 months; its persistence may suggest neurological damage.
- Trendelenburg Sign: A positive sign indicates hip-abductor weakness, which should not be confused with psychological anxiety.
- Acute Disseminated Encephalomyelitis (ADEM): This autoimmune demyelinating condition requires immediate assessment for neurological asymmetry.
- Cognitive Screening: For older adults with new memory complaints, the Mini-Cog (combining three-word recall and a clock-drawing test) is a rapid screen. For a deeper dive into executive dysfunction or Mild Cognitive Impairment (MCI), the MoCA (Montreal Cognitive Assessment) is preferred.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.
Continue reading freeAlready have an account? Log in
Updated