Psychiatric Medication Interactions and Drug-Induced Mood Changes
An educational overview of how psychiatric medications interact with other drugs and physiological factors, focusing on the CYP450 enzyme system, lithium management, and drug-induced mood changes like mania and depression.
Managing psychiatric patients requires more than just selecting the right molecule for a diagnosis; it requires a deep understanding of how that molecule interacts with the patient's unique physiology, lifestyle, and concurrent medications. A sudden shift in mood, a new tremor, or a loss of therapeutic efficacy is rarely a random event. Often, these changes are the direct result of drug-drug interactions, enzyme induction, or the introduction of non-psychiatric medications.
The Role of the CYP450 Enzyme System
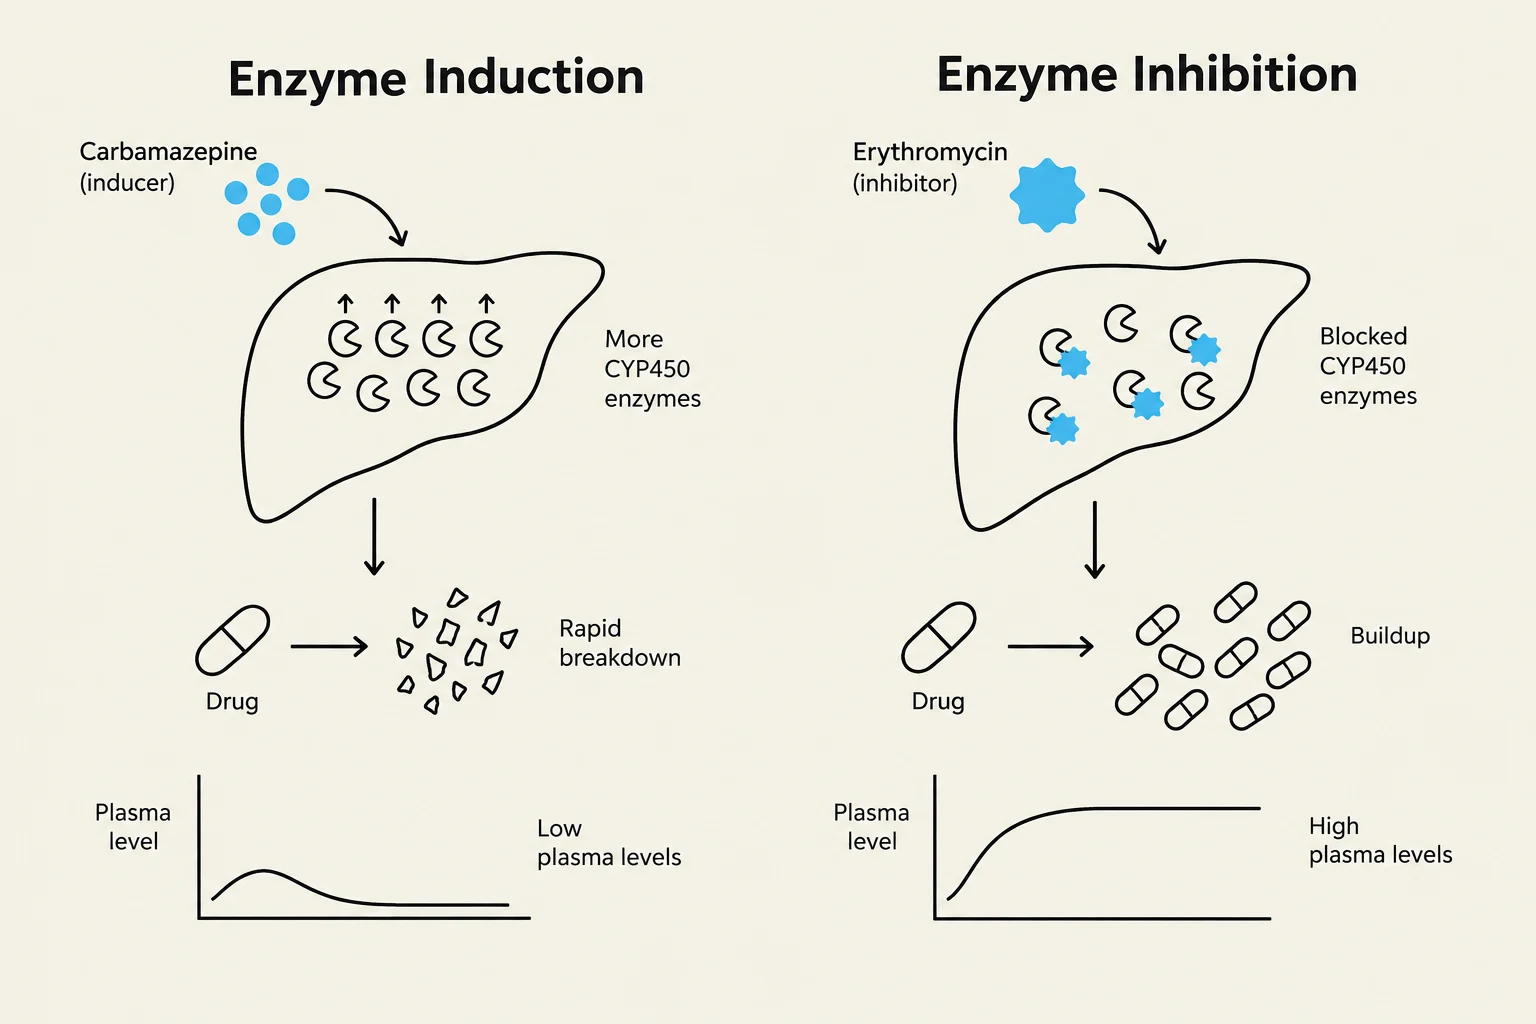
Diagram illustrating enzyme induction and inhibition. Enzyme induction, caused by substances like carbamazepine, increases CYP450 enzymes in the liver, leading to rapid drug breakdown and low plasma levels. Enzyme inhibition, caused by substances like erythromycin, blocks CYP450 enzymes, resulting in drug buildup and high plasma levels.
The Cytochrome P450 (CYP450) enzyme system in the liver is the primary engine for drug metabolism. When a patient takes a medication that influences these enzymes, the concentration of other drugs in their bloodstream can rise to toxic levels or fall to subtherapeutic levels.
Enzyme Inducers: Decreasing Drug Efficacy
Enzyme inducers increase the activity of the CYP450 system, essentially "speeding up" the liver's ability to clear drugs from the body. This leads to lower plasma concentrations and a loss of therapeutic effect.
CYP3A4 Induction: Medications such as carbamazepine (Tegretol), phenytoin, phenobarbital, and rifampin are potent inducers. For example, carbamazepine induces the CYP3A4 enzyme, which can accelerate the metabolism of inhaled corticosteroids like fluticasone (Flonase), rendering them subtherapeutic.
Hormonal Impact: Carbamazepine also induces hepatic enzymes that lower the concentration of hormonal oral contraceptives, significantly decreasing their effectiveness.
Enzyme Inhibitors: Increasing Toxicity Risk
Conversely, enzyme inhibitors slow down the metabolism of drugs, causing them to accumulate in the bloodstream. This significantly increases the risk of adverse effects and toxicity.
Macrolide Antibiotics: Antibiotics like erythromycin and clarithromycin are potent CYP450 inhibitors. When prescribed to a patient on antipsychotics, they can cause a rapid increase in antipsychotic levels, leading to sedation, extrapyramidal symptoms (EPS), QT prolongation, and general neuroleptic toxicity.
Specific Interactions: Erythromycin can potently inhibit the CYP3A4 system, causing a dangerous spike in carbamazepine levels, which may induce acute toxicity.
The Smoking Variable: CYP1A2 Induction
Tobacco smoke is a unique physiological factor because it induces the CYP1A2 enzyme. This induction increases the clearance of several key psychiatric medications, including clozapine, olanzapine, and duloxetine.
Clinical Pearl: The Smoking Cessation Trap
If a stable patient who smokes suddenly ceases tobacco use, the induction of CYP1A2 stops. This leads to a rapid, dangerous increase in the plasma levels of clozapine or olanzapine, raising the risk of toxicity, including sedation, hypotension, or seizures.
Lithium Management and Toxicity
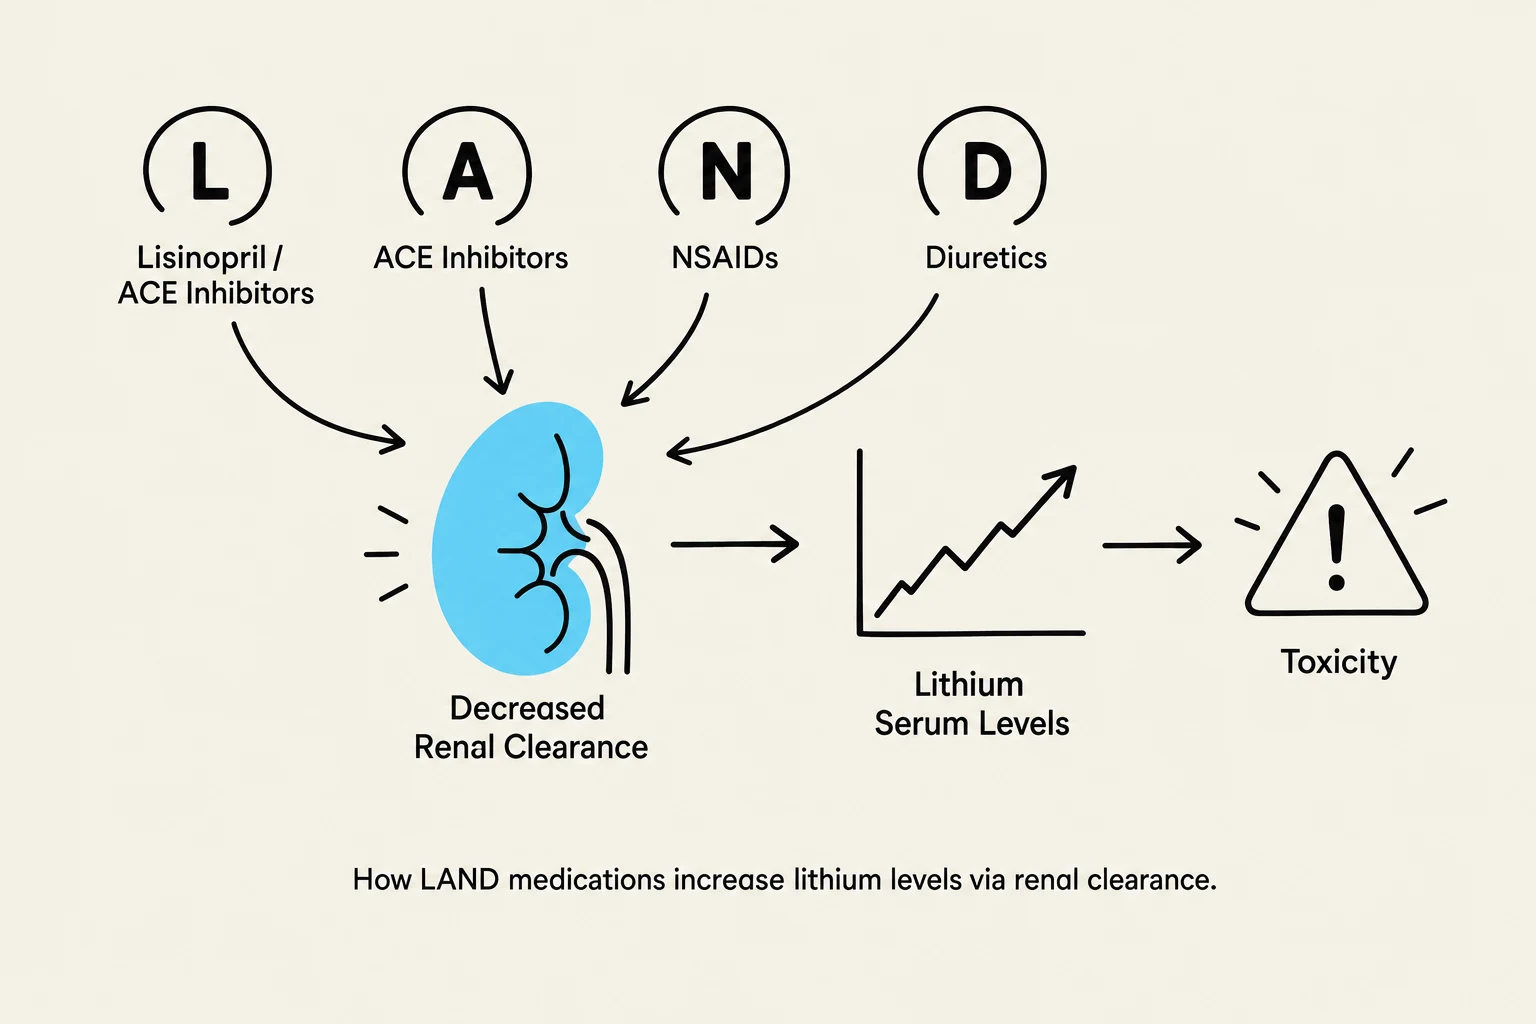
This diagram illustrates how certain medications (Lisinopril/ACE Inhibitors, ACE Inhibitors, NSAIDs, Diuretics) can lead to decreased renal clearance, resulting in increased lithium serum levels and potential toxicity.
Lithium remains a gold standard for long-term suicide prevention in patients with bipolar disorder. However, its narrow therapeutic index makes it highly susceptible to fluctuations in serum levels.
The standard therapeutic range for lithium is:
0.6–1.2 mEq/L
Recognizing Toxicity
Clinicians must distinguish between common side effects and true toxicity. A fine tremor is a common, often benign side effect of lithium. However, the development of a coarse tremor—especially when accompanied by ataxia, confusion, nystagmus, blurred vision, or gastrointestinal distress (vomiting/diarrhea)—is a hallmark of toxicity.
Early Toxicity: Levels between 1.3–1.4 mEq/L require close monitoring.
Severe Toxicity: Levels ≥1.5 mEq/L necessitate immediate discontinuation of the medication.
The "LAND" Mnemonic for Lithium Interactions
Certain medications decrease the renal clearance of lithium, causing levels to rise. Use the mnemonic "LAnD" to remember the primary culprits:
L — Lisinopril (and other ACE Inhibitors/ARBs)
A — ACE Inhibitors
N — NSAIDs (e.g., ibuprofen, indomethacin)
D — Diuretics (specifically Thiazides like hydrochlorothiazide)
Note: Aspirin and Sulindac are generally considered safer alternatives regarding lithium interaction.
Drug-Induced Mood Changes
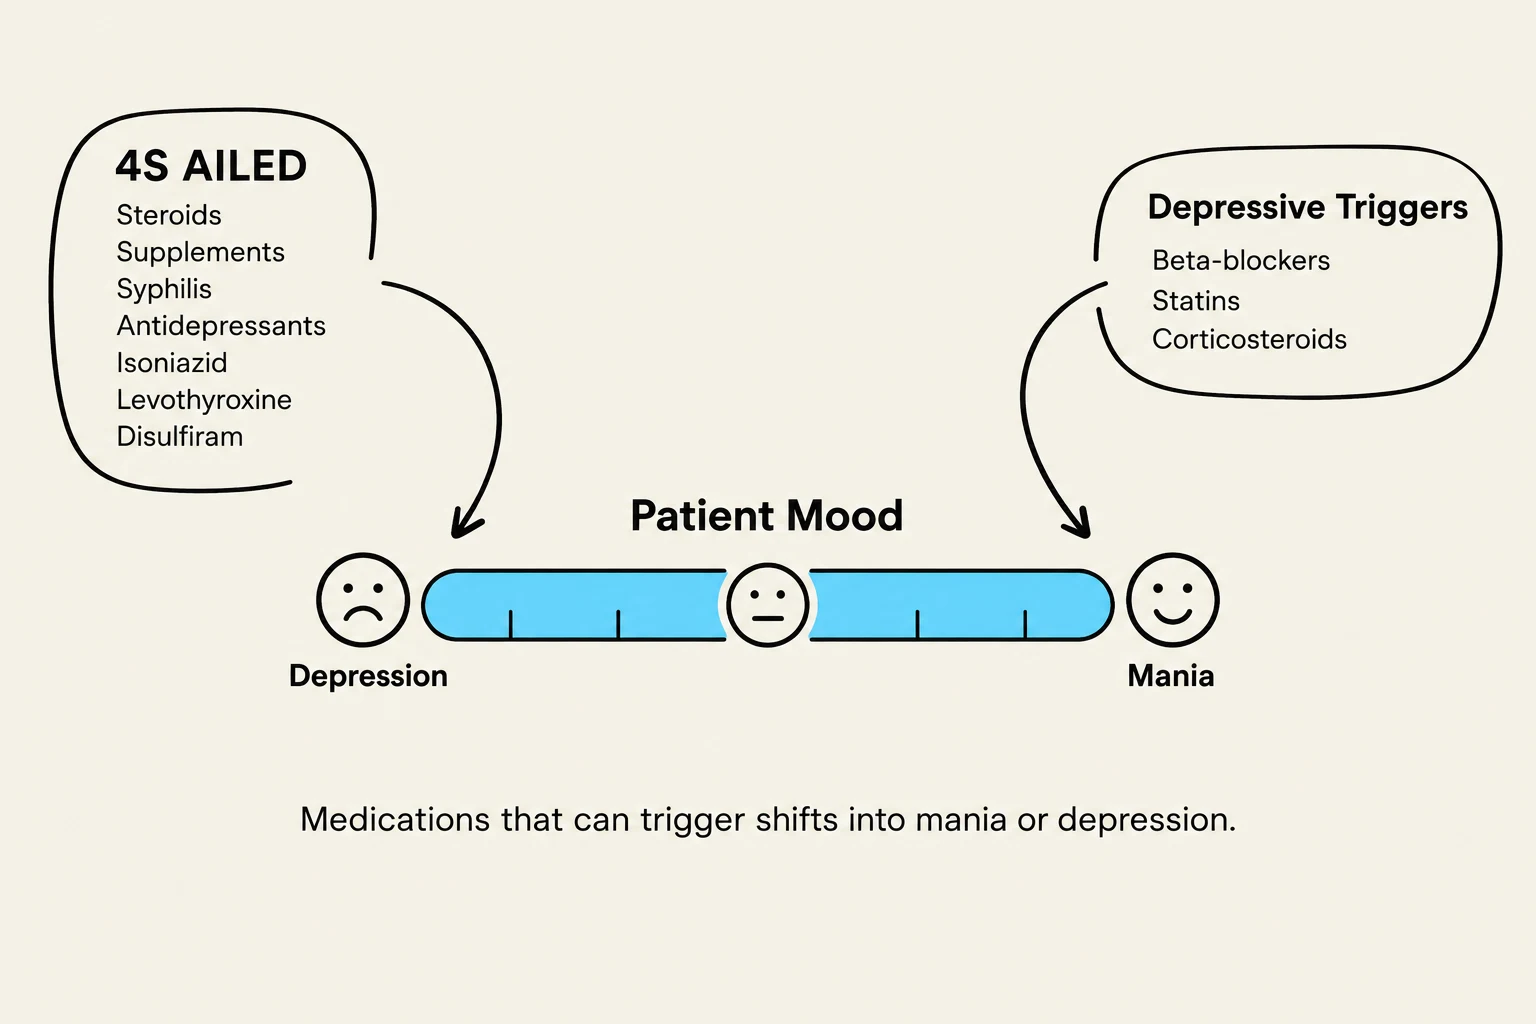
This diagram illustrates how certain medications and conditions can influence patient mood, potentially leading to shifts between depression and mania.
When a patient experiences a sudden, unexplained shift in mood, clinicians should look beyond the primary psychiatric diagnosis and investigate recent medication changes.
Drug-Induced Mania
A sudden onset of mania or agitation may be precipitated by several non-psychiatric agents. A helpful mnemonic for this is the 4S AILED method:
Letter
Category
Examples
S
Steroids
Prednisone, Dexamethasone, Fluticasone (in susceptible patients)
S
Supplements
SAM-e, St. John’s Wort, Ginseng
S
Syphilis
Late-stage neurosyphilis
A
Antidepressants
SSRIs and SNRIs
I
Isoniazid
Used in Tuberculosis treatment
L
Levothyroxine
Can induce a hyperthyroid state
E
—
(N/A)
D
Disulfiram
Used in alcohol use disorder treatment
Drug-Induced Depression
Conversely, several medications can trigger or worsen depressive symptoms:
Corticosteroids (e.g., prednisone)
Beta-blockers
Statins
Isotretinoin (Accutane)
Interferon
Exam Tip: Steroid-Induced Psychosis
If a patient on high-dose corticosteroids (like dexamethasone) suddenly develops mania, agitation, or psychosis, the priority is to collaborate with the medical prescriber to reassess or discontinue the steroid.
Summary of Clinical Priorities
Scenario
Suspected Cause
Immediate Action
Patient on Clozapine stops smoking
CYP1A2 induction stops → Toxicity
Decrease dose; monitor for sedation/seizures
Patient on Lithium starts Ibuprofen
Decreased renal clearance → Toxicity
Hold Lithium; check levels, electrolytes, and BUN/Cr
Patient on Carbamazepine starts Erythromycin
CYP3A4 inhibition → Toxicity
Hold Carbamazepine; check levels
Patient on SSRI starts Sumatriptan
Serotonin Syndrome
Stop serotonergic agents; monitor for clonus/fever
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.