Propofol: Pharmacokinetics, Pharmacodynamics, and Clinical Effects
An in-depth explanation of propofol, a widely used intravenous anesthetic agent. This covers its pharmacokinetic profile, including redistribution, metabolism, and elimination, as well as its pharmacodynamic actions on GABA-A and NMDA receptors. The document also details its physiological effects on the central nervous
Propofol (2,6-diisopropylphenol) is the most commonly used intravenous induction agent in modern anesthesia. As an alkylphenol, it is highly lipid-soluble and is typically prepared in a lipid emulsion containing soybean oil, glycerol, and egg lecithin. Because of its rapid onset and short duration of action, it is ideal for both the induction of general anesthesia and the maintenance of anesthesia via Total Intravenous Anesthesia (TIVA). However, its unique chemical properties necessitate strict aseptic handling and careful monitoring of physiological parameters.
Pharmacokinetics: The "Redistribution" Phenomenon
The clinical profile of propofol is defined by a rapid onset and a very quick recovery. When an intravenous bolus is administered, the drug rapidly enters highly perfused organs, such as the brain, reaching peak effects within approximately one minute.
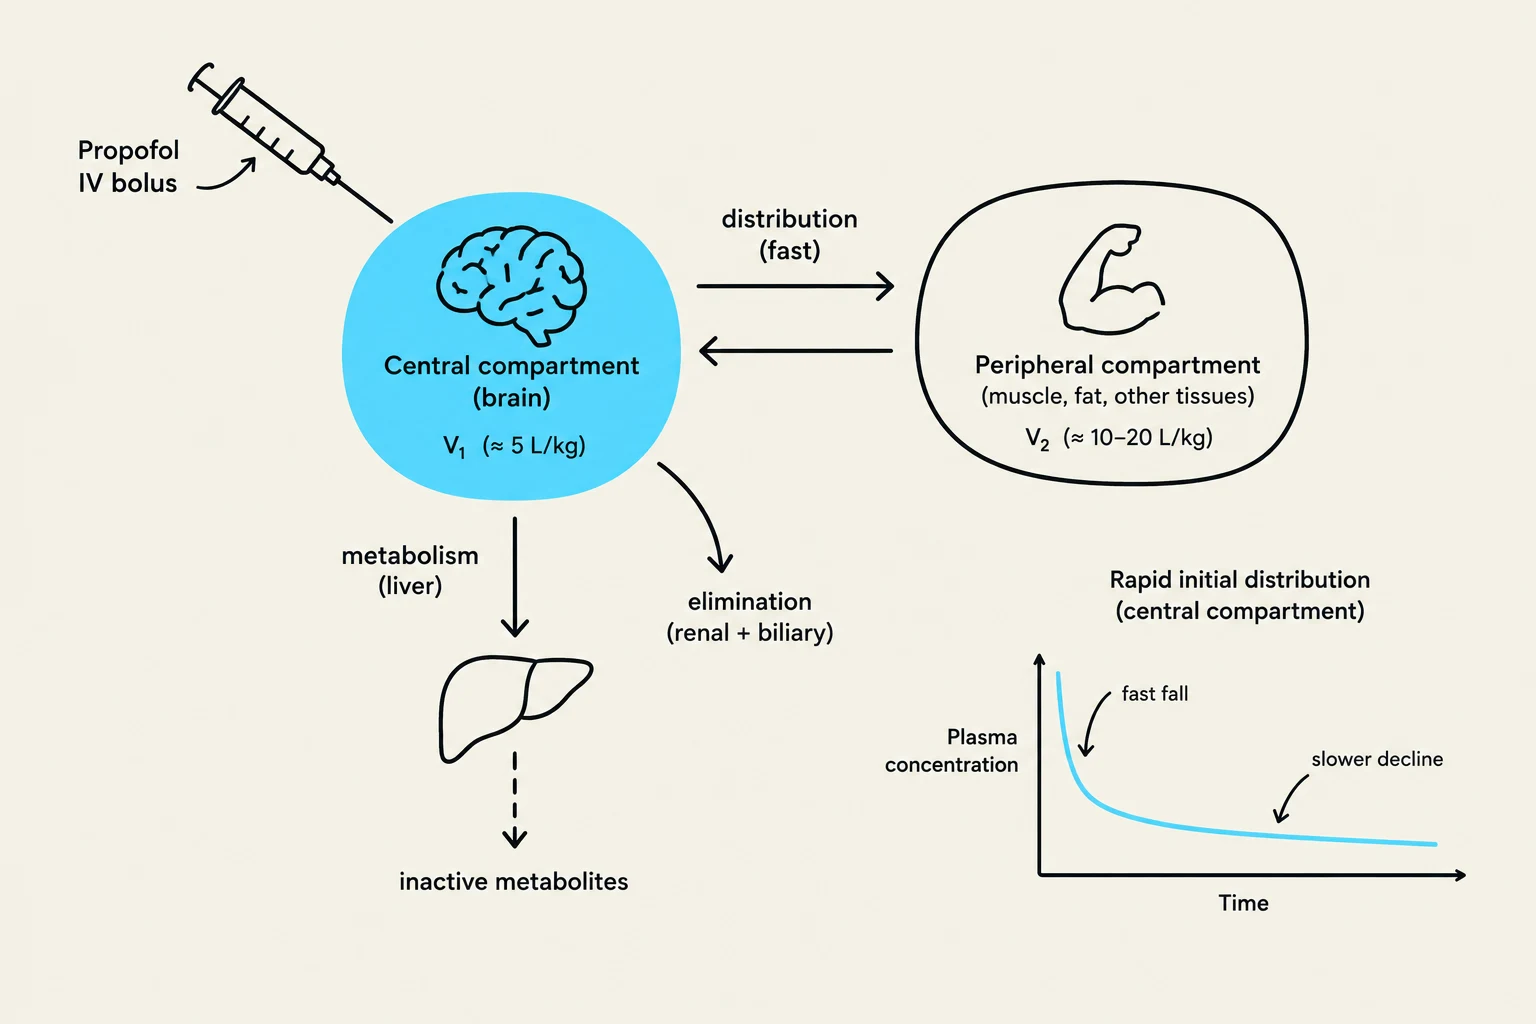
A common misconception in clinical practice is that the rapid awakening seen after a propofol bolus is due to immediate metabolism. In reality, the initial decline in brain and blood concentrations is driven by redistribution. After the initial peak in the central compartment (the brain), the drug moves from these highly perfused tissues to less well-perfused peripheral compartments, such as muscle and fat. This redistribution results in a rapid awakening, typically within 5 to 15 minutes.
Diagram illustrating the pharmacokinetic model of propofol distribution, metabolism, and elimination in the body, showing central and peripheral compartments and plasma concentration over time.
Metabolism and Elimination
While redistribution governs the initial recovery, metabolism governs the eventual clearance of the drug from the body. Propofol is rapidly metabolized in the liver through oxidation and conjugation via enzymes including CYP2B6, UGT1A4, and CYP2C6.
Interestingly, the total clearance of propofol can actually exceed hepatic blood flow, suggesting that extra-hepatic metabolism (such as in the lungs) also plays a role. This characteristic explains why the elimination of propofol remains relatively stable even in patients with severe cirrhosis. The elimination half-life is generally between 1 and 2 hours.
Protein Binding and the Free Fraction
Propofol is highly protein-bound, primarily to plasma albumin (approximately 48%) and erythrocytes (approximately 50%). This leaves a free, pharmacologically active fraction of less than 2%.
Clinical conditions that decrease plasma protein levels—such as renal disease, hepatic disease, or pregnancy—can increase the free fraction of the drug. An increase in the free fraction can lead to an exaggerated clinical effect, such as deeper sedation or more profound hypotension, even if the total plasma concentration appears normal.
Context-Sensitive Half-Time
For clinicians managing continuous infusions, the "context-sensitive half-time" is a critical concept. This refers to the time required for the plasma concentration to decrease by 50% after the cessation of an infusion. Unlike drugs like diazepam or thiopental, which show a steep increase in context-sensitive half-time as the infusion duration increases, propofol maintains a relatively low and stable half-time, making it suitable for long-term infusions and TIVA.
Pharmacodynamics: Mechanism of Action
Propofol exerts its effects by inducing global central nervous system (CNS) depression. Its primary mechanism is the direct stimulation of GABAA receptors, where it acts to potentiate the effects of endogenous γ-aminobutyric acid (GABA).
GABA-A Receptor Interaction
The GABAA receptor is a ligand-gated chloride channel. When propofol binds to the receptor, it increases the sensitivity to GABA or, at high concentrations, can directly open the chloride channel. This results in an influx of chloride ions (Cl−), leading to hyperpolarization of the neuron and subsequent inhibition of action potentials.
Diagram illustrating the mechanism of action of GABA, benzodiazepines, and propofol on the GABAA receptor, leading to increased GABAergic inhibition and decreased neuronal excitability.
NMDA Inhibition and Neuroprotection
In addition to GABAergic activity, propofol inhibits NMDA receptors by modulating Na+ channel gating and affecting the NR1 subunit. By inhibiting NMDA receptors, propofol may prevent the excessive accumulation of glutamate and limit intracellular calcium (Ca2+) influx. This mechanism provides a theoretical, though not clinically proven, neuroprotective capacity by limiting excitotoxicity.
Physiological and Clinical Effects
Propofol has profound effects on multiple organ systems, which must be managed carefully during administration.
Decreases the cerebral metabolic rate of oxygen (CMRO2).
Furthermore, propofol is known for its antiemetic properties, which are thought to be mediated by a decrease in serotonin levels in the area postrema. It also increases dopamine concentrations in the nucleus accumbens, which may contribute to feelings of euphoria upon emergence.
Cardiovascular and Respiratory Systems
The most significant clinical concern with propofol is its tendency to cause hemodynamic depression.
Cardiovascular: Propofol can cause a decrease in systemic blood pressure and systemic vascular resistance. It is also associated with bradycardia, which can be refractory to atropine and may require treatment with isoproterenol.
Respiratory: Propofol frequently causes respiratory depression and can lead to apnea, particularly when used in combination with opioids or benzodiazepines.
Clinical Alert: PRIS
Propofol Related Infusion Syndrome (PRIS) is a rare but serious complication associated with high-dose propofol infusions (exceeding 4 mg/kg/h for more than 48 hours). Symptoms include refractory bradycardia, metabolic acidosis, rhabdomyolysis, and lipemia.
Summary of Clinical Dosing
Dosing must be individualized based on age and comorbidities:
Indication
Adult Dose
Pediatric Dose
Induction
2–2.5 mg/kg IV
2.5–3.5 mg/kg IV
Maintenance
100–200 mcg/kg/min
N/A
Sedation
25–75 mcg/kg/min
N/A
Note: Doses should be reduced in patients over 60 or those with significant pathophysiologic disease.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.