


Supporting a patient's ability to breathe effectively often requires a combination of artificial airways, specialized drainage systems, and surgical interventions. Whether a patient requires short-term assistance due to acute respiratory distress or long-term support for chronic conditions, healthcare providers must master the management of various devices and procedures to ensure airway patency, lung expansion, and gas exchange.
Artificial Airways
Artificial airways are used to bypass obstructions or protect the airway from aspiration. The choice of device depends on the urgency of the situation and the expected duration of support.
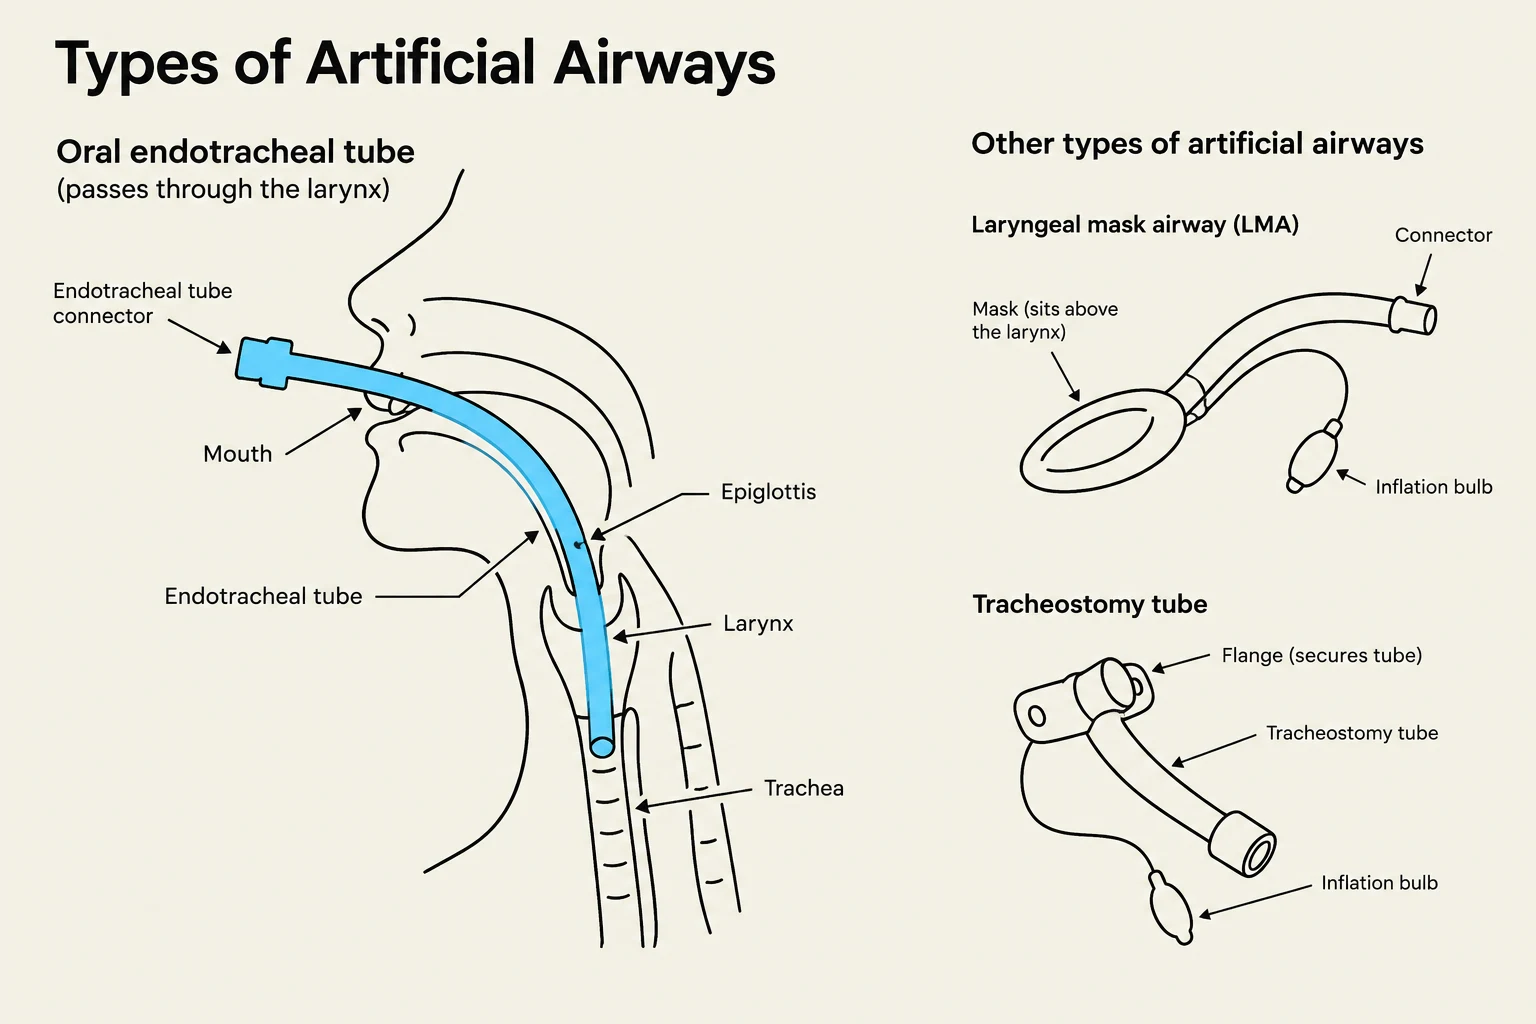
Endotracheal (ET) Tubes
The endotracheal tube is a long, flexible plastic tube used for patients requiring mechanical ventilation. Oral intubation is the preferred method for quickly securing an airway. Common indications for ET tube placement include:
- Acute Respiratory Distress Syndrome (ARDS)
- Apnea or upper airway obstruction
- Ineffective clearance of secretions
- High risk for aspiration
In the ICU, ET tubes are typically used for short-term ventilation, often lasting up to two weeks.
Nasotracheal Tubes and Tracheostomy
When oral intubation is not feasible—perhaps due to facial trauma or swelling—a nasotracheal tube may be used. These are slightly longer than oral tubes and are inserted through the nostril.
For patients requiring long-term mechanical ventilation (exceeding two weeks), a tracheostomy is often indicated. A tracheostomy involves a surgical incision in the anterior neck to create a stoma, allowing a tube to be placed directly into the trachea. This approach is more comfortable for the patient, reduces the risk of long-term damage to the vocal cords, and facilitates easier oral and bronchial hygiene.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.
Continue reading freeAlready have an account? Log in
Updated