


Endometrial cancer management is a highly individualized process guided by the histological type, the stage of the disease, and the patient's desire for future fertility. While surgical intervention remains the cornerstone of treatment for most patients, modern oncology has expanded the toolkit to include specialized fertility-sparing protocols and targeted adjuvant therapies. Understanding these pathways requires a clear distinction between different categories of uterine neoplasms and the specific clinical criteria used to guide decision-making.
Endometrial Cancer Categories
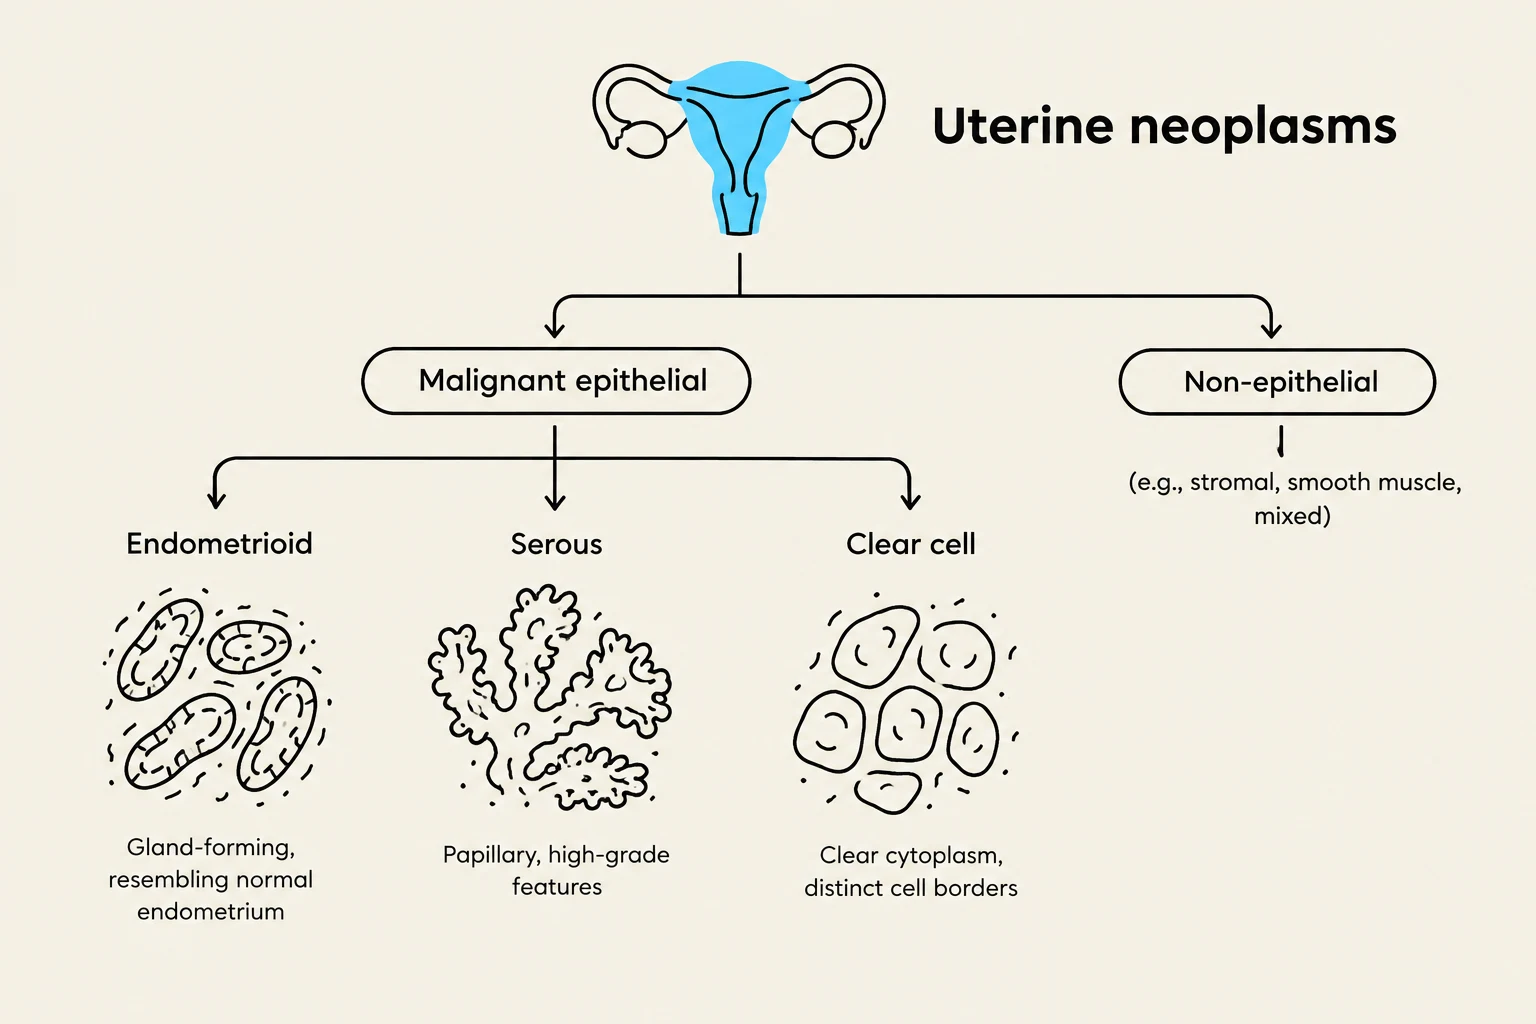
Not all uterine cancers are treated equally. The NCCN Guidelines categorize these neoplasms based on their histological characteristics, which significantly influence prognosis and treatment strategy.
The most common form is pure endometrioid cancer, which is often categorized by its grade and depth of myometrial invasion. In contrast, high-grade histologies—such as serous carcinoma, clear cell carcinoma, undifferentiated carcinoma, and carcinosarcoma—are treated with much higher intensity due to their aggressive nature. Additionally, clinicians must distinguish between epithelial carcinomas and malignant mesenchymal tumors (sarcomas), such as low-grade endometrial stromal sarcoma (ESS) or leiomyosarcoma.
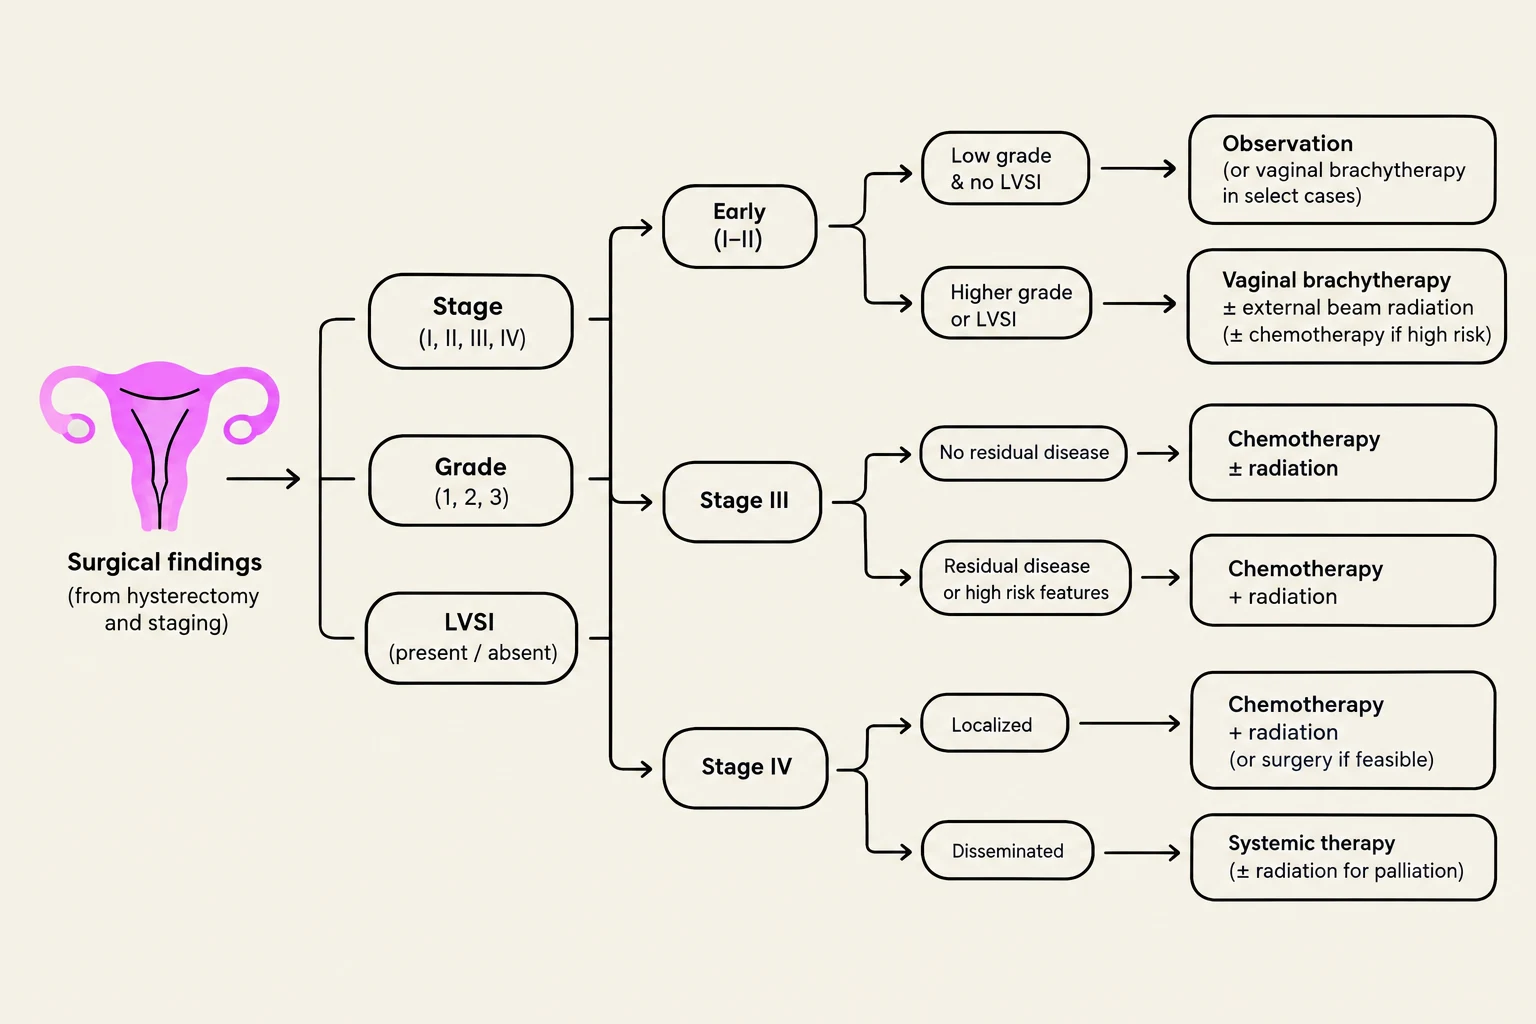
Clinical Pearl: Always check for high-grade features or lymphovascular space invasion (LVSI) during pathology review, as these are critical drivers in determining whether a patient needs adjuvant therapy beyond surgery.
Surgical Management and Staging
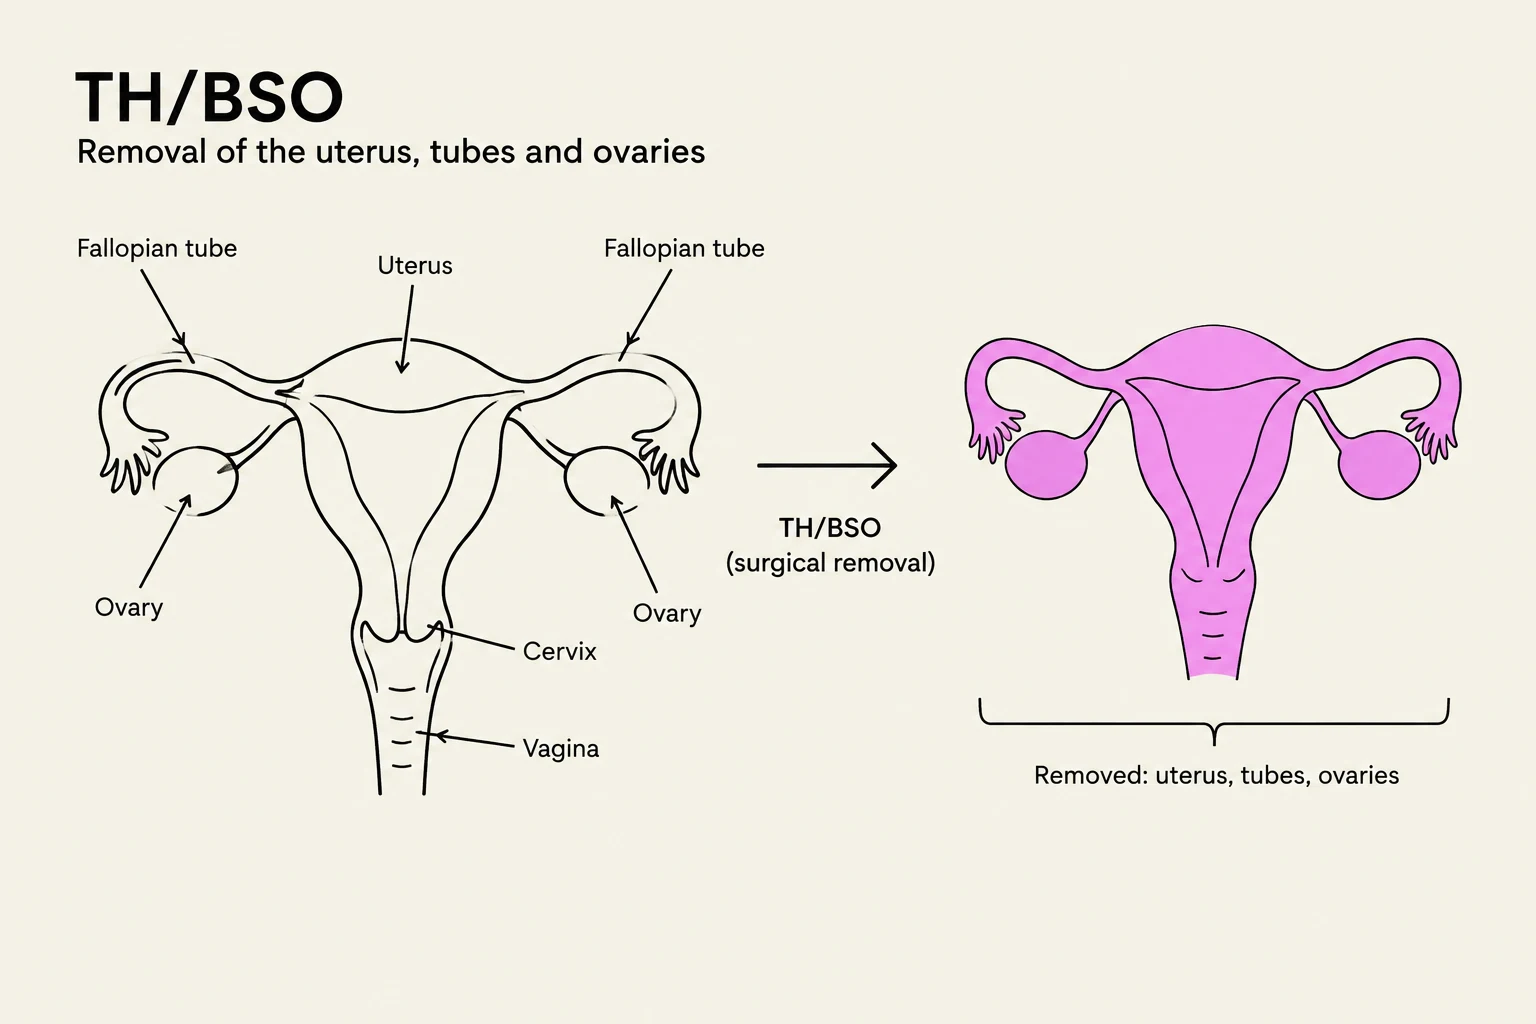
For medically operable patients with disease limited to the uterus, the standard of care is the en bloc removal of the uterus, bilateral tubes, and ovaries, commonly referred to as Total Hysterectomy and Bilateral Salpingo-Oophorectomy (TH/BSO).
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.
Continue reading freeAlready have an account? Log in
Updated