Post-Mortem Forensic Toxicology and Death Investigation
This content explains the principles and practices of post-mortem forensic toxicology, including the role of toxicologists in death investigations, sample collection, analytical methods, and interpretation of results. It covers various case types, biological sample matrices, and challenges in interpreting drug concentr
When a death occurs under sudden, unexpected, or suspicious circumstances, a complex multidisciplinary investigation begins. While a medical examiner or pathologist looks for physical trauma or disease, the forensic toxicologist looks for the invisible: the presence of drugs, alcohol, or poisons that may have influenced the circumstances of death. Post-mortem forensic toxicology is the application of scientific methods to investigate crime and death by analyzing biological samples for chemical substances.
The Framework of Death Investigation
A death investigation is not a solitary task; it is a collaborative effort involving various agencies such as the Office of the Chief Coroner (OCCO), police services, the Ministry of Labour, and specialized units like the Special Investigations Unit (SIU).
In many jurisdictions, such as Ontario, the coroner's role is to "speak for the dead to protect the living". Coroners investigate sudden deaths to answer five fundamental questions: Who was the deceased? When did they die? Where did they die? How did they die? And by what means did the death occur?.
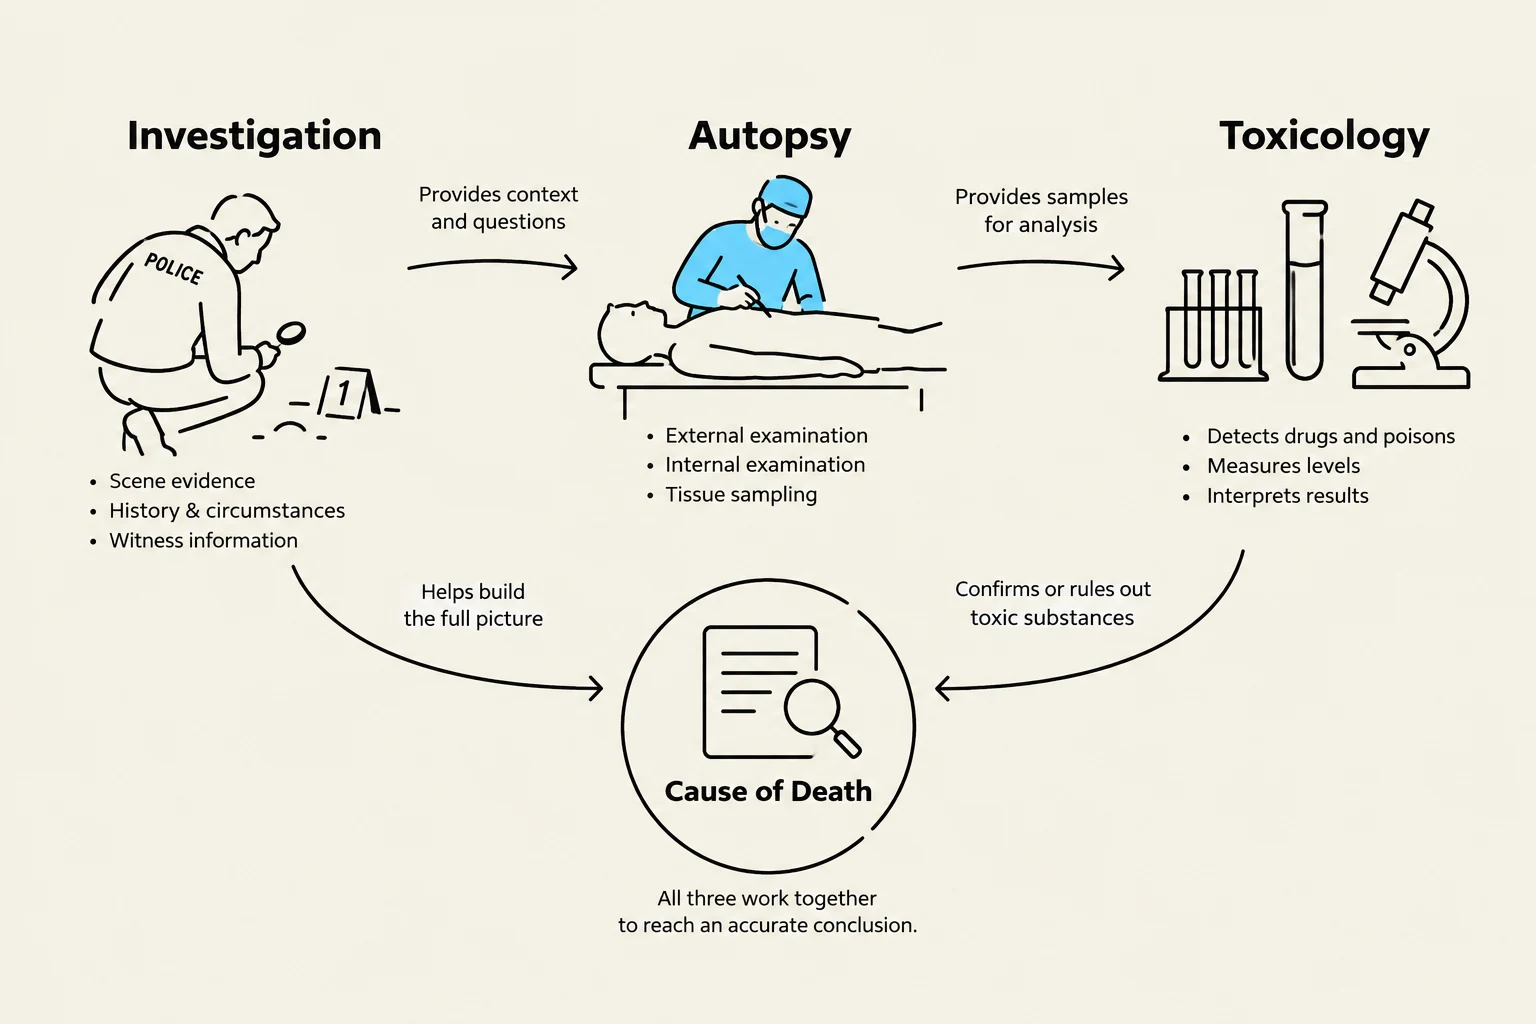
When a death is suspicious, an autopsy is performed by a forensic pathologist—a medical doctor with specialized training in the study of disease. While the pathologist examines the physical body, the toxicologist analyzes the chemical composition of the tissues.
Key Distinction: The forensic toxicologist does not determine the cause of death. Instead, they interpret drug findings and provide an expert opinion to the forensic pathologist and coroner, who then use that data to determine the final cause and manner of death.
This diagram illustrates the three main components involved in determining the cause of death: investigation, autopsy, and toxicology. Each stage contributes information that helps build a comprehensive understanding of the circumstances surrounding a death.
Coroner’s Case Types and Testing Protocols
The type of toxicology testing ordered depends heavily on the circumstances of the death. Not every case requires an exhaustive screen; instead, protocols are tailored to the suspected cause.
Drug-Related Deaths: If there is no clear anatomical cause of death but the history suggests intoxication, extensive drug screening and ethanol analysis are performed.
Exclusionary Toxicology: In cases where a clear cause is found (e.g., a fall or drowning), toxicology may be used to "rule out" drugs or alcohol as contributing factors.
Specialized Cases:
Fire-related deaths: Analysis for Carbon Monoxide (CO) is critical.
Motor Vehicle Collisions: Often involves ethanol and drug screening.
Child Deaths (<5 years): May include specific tests for acetaminophen and confirmation of ketoacidosis using ethanol and beta-hydroxybutyrate (BHB).
Homicides/SIU Investigations: Typically involve full ethanol, drug, and THC screening.
Biological Sample Collection and Matrix Selection
The accuracy of a toxicological report depends on the quality of the biological samples collected during the autopsy. Different tissues provide different types of information.
Blood: The Gold Standard
Blood is the most useful specimen for determining the physiological effect of a drug at the time of death because its concentration can be directly correlated to pharmacological effects. However, post-mortem blood is not "true" blood due to autolysis (the breakdown of cells by their own enzymes).
To minimize errors, toxicologists prefer peripheral blood (e.g., from the femoral or iliac veins) over central blood (e.g., from the heart). This is because central blood is highly susceptible to Post-Mortem Redistribution (PMR)—a process where drugs diffuse from high-concentration organs (like the liver or stomach) into the surrounding blood after death, artificially inflating the concentration levels.
Other Critical Matrices
Urine: Useful for detecting the presence of a drug or its metabolites, but because it is a pooled sample collected over time, it does not correlate well with the drug's effect at the exact moment of death.
Vitreous Humour: The fluid in the eye is sequestered from much of the body's decomposition and trauma, making it an excellent source for ethanol analysis.
Liver: Since the liver is the site of metabolism, drugs may be found in higher concentrations here, making it useful for detection when other samples are unavailable.
Stomach Contents: Can reveal undissolved tablets or drugs recently ingested orally.
This diagram illustrates Post-Mortem Redistribution (PMR), where drugs diffuse from organs like the liver and stomach into the central circulation after death, potentially increasing blood drug levels.
Challenges in Interpretation: Stability and Tolerance
Interpreting a concentration number is rarely straightforward. A toxicologist must consider several complicating factors:
1. Drug Stability and Metabolism
Some drugs break down naturally after death or during storage. For example, cocaine breaks down into benzoylecgonine. Furthermore, the ratio between a "parent drug" and its "metabolite" can indicate whether the ingestion was acute or chronic.
Worked Example: Amitriptyline Interpretation
Case 1 (Therapeutic): Parent drug > Metabolite (e.g., 0.18 mg/L>0.063 mg/L)
Case 2 (Chronic): Metabolite > Parent drug (e.g., 0.70 mg/L>0.40 mg/L)
Case 3 (Acute Overdose): Parent drug ≫ Metabolite (e.g., 4 mg/L≫0.20 mg/L)
2. Individual Tolerance
A concentration that is fatal for one person might be therapeutic for another. For instance, a cancer patient using high doses of opioids may have blood concentrations that overlap with those found in fatal overdoses.
Exam Tip: When interpreting results, always look for the "Parent-to-Metabolite" ratio. A very high parent drug concentration relative to the metabolite often suggests a rapid death following an acute dose.
The Coroner’s Inquest
In some cases, a public hearing known as an inquest is held. This is mandatory for deaths in custody, deaths involving police use of force, or deaths at construction sites.
An inquest is not a criminal trial; it is a fact-finding mission. A jury of five citizens hears evidence to answer the five questions of death (who, when, where, how, and by what means). While the jury can make recommendations to improve public safety, these conclusions are not legally binding.
Toxicologists often serve as expert witnesses during these inquests. They are expected to explain complex scientific concepts—such as drug half-lives or the blood-to-plasma ratio—in simple, non-jargon terms for the jury.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.