Polypharmacy and Dental Implications: A Guide for Clinical Practice
This guide explores the challenges and considerations for dental professionals managing patients on polypharmacy, including obtaining comprehensive medication histories, understanding the dental implications of specific drug classes, managing adverse drug reactions, and the role of dentists in deprescribing.
In modern clinical practice, the "typical" patient is increasingly likely to be managed with multiple medications. Polypharmacy—defined as the treatment of a patient with five or more medicines—is a growing phenomenon, particularly among older populations. As patients move through different healthcare providers, they often accumulate layers of drug therapy, much like a coral reef accumulating layers of coral.
For the dental professional, this presents a significant challenge. Approximately 50% of all medicines have oral implications. Managing these patients requires more than just identifying a few familiar drugs; it requires a comprehensive understanding of how various pharmacological classes interact with dental procedures and oral health.
The Importance of a Comprehensive Medication History
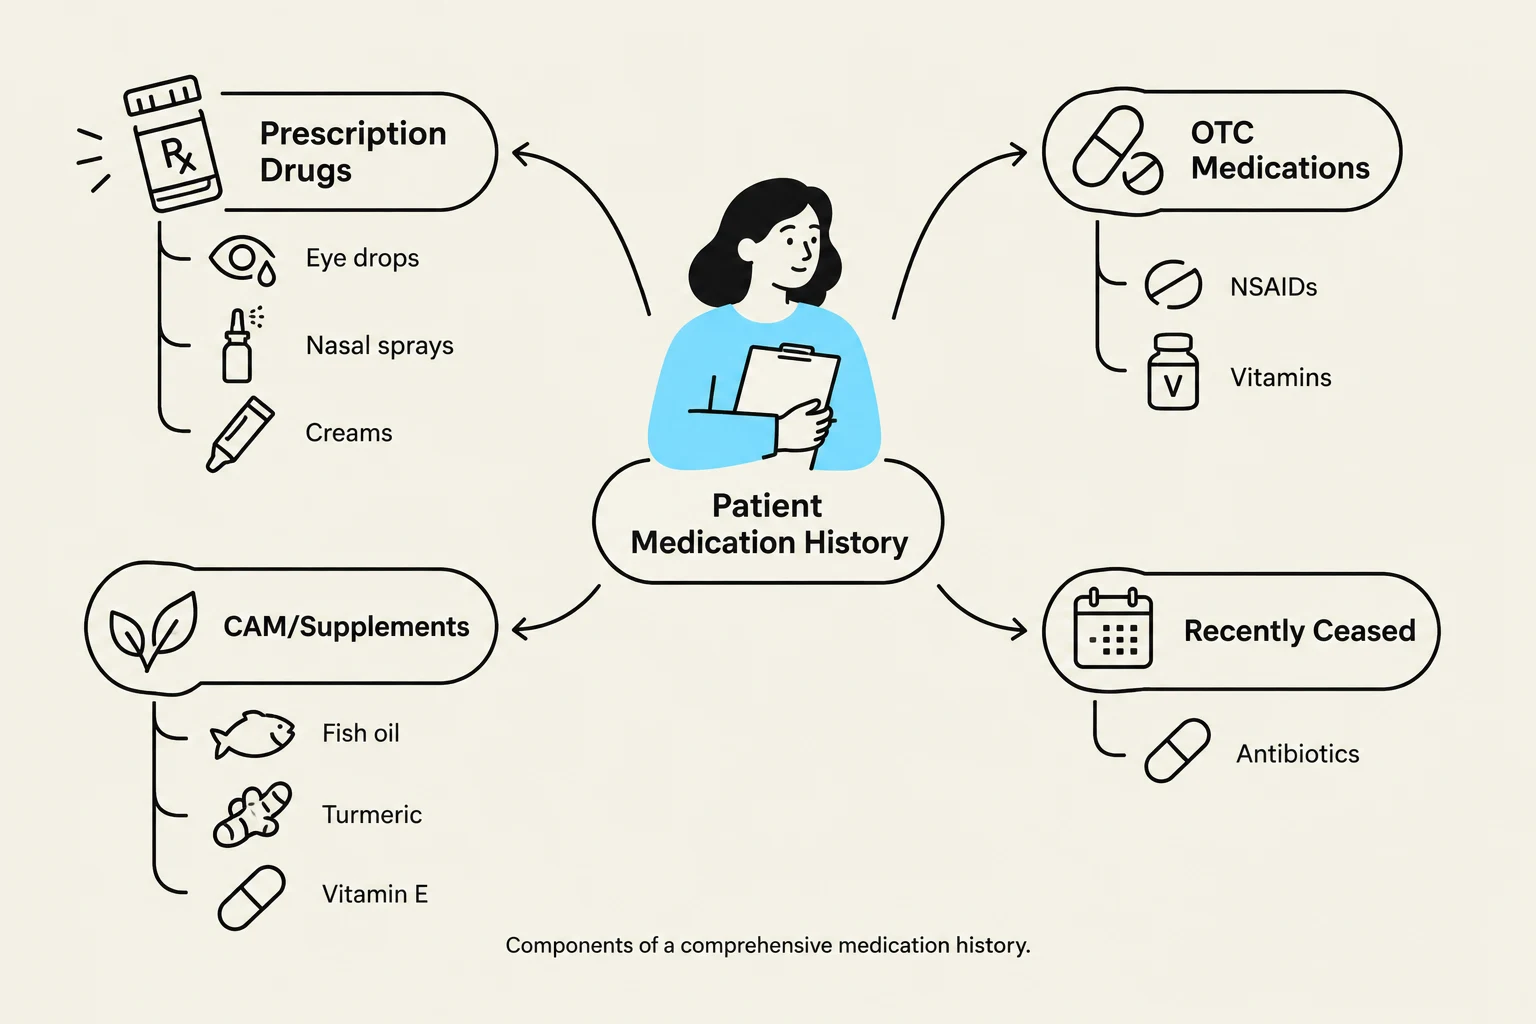
A diagram illustrating the components of a comprehensive patient medication history, including prescription drugs, OTC medications, CAM/supplements, and recently ceased medications.
The first step in managing a polypharmacy patient is obtaining an accurate and exhaustive medication history. A common pitfall is relying solely on a list provided by a General Practitioner (GP), which may be incomplete or outdated. To provide safe care, dental professionals must investigate the "whole person".
A truly comprehensive history should include:
Prescription drugs: Including eye drops, nasal sprays, and dermatological creams.
Over-the-counter (OTC) medications: Such as NSAIDs or vitamins.
Complementary and Alternative Medicines (CAM): Herbs and supplements (e.g., Fish oil, Turmeric, Vitamin E) which can significantly increase bleeding risks.
Recently ceased medications: Such as a recent course of antibiotics.
Clinical Tip: The Three-Detail Rule
When documenting medicines, do not just list the name. Aim to capture the Drug Name (strength and formulation), the Dose (including duration of treatment), and the Indication (the purpose of the drug).
Major Dental Implications of Specific Drug Classes
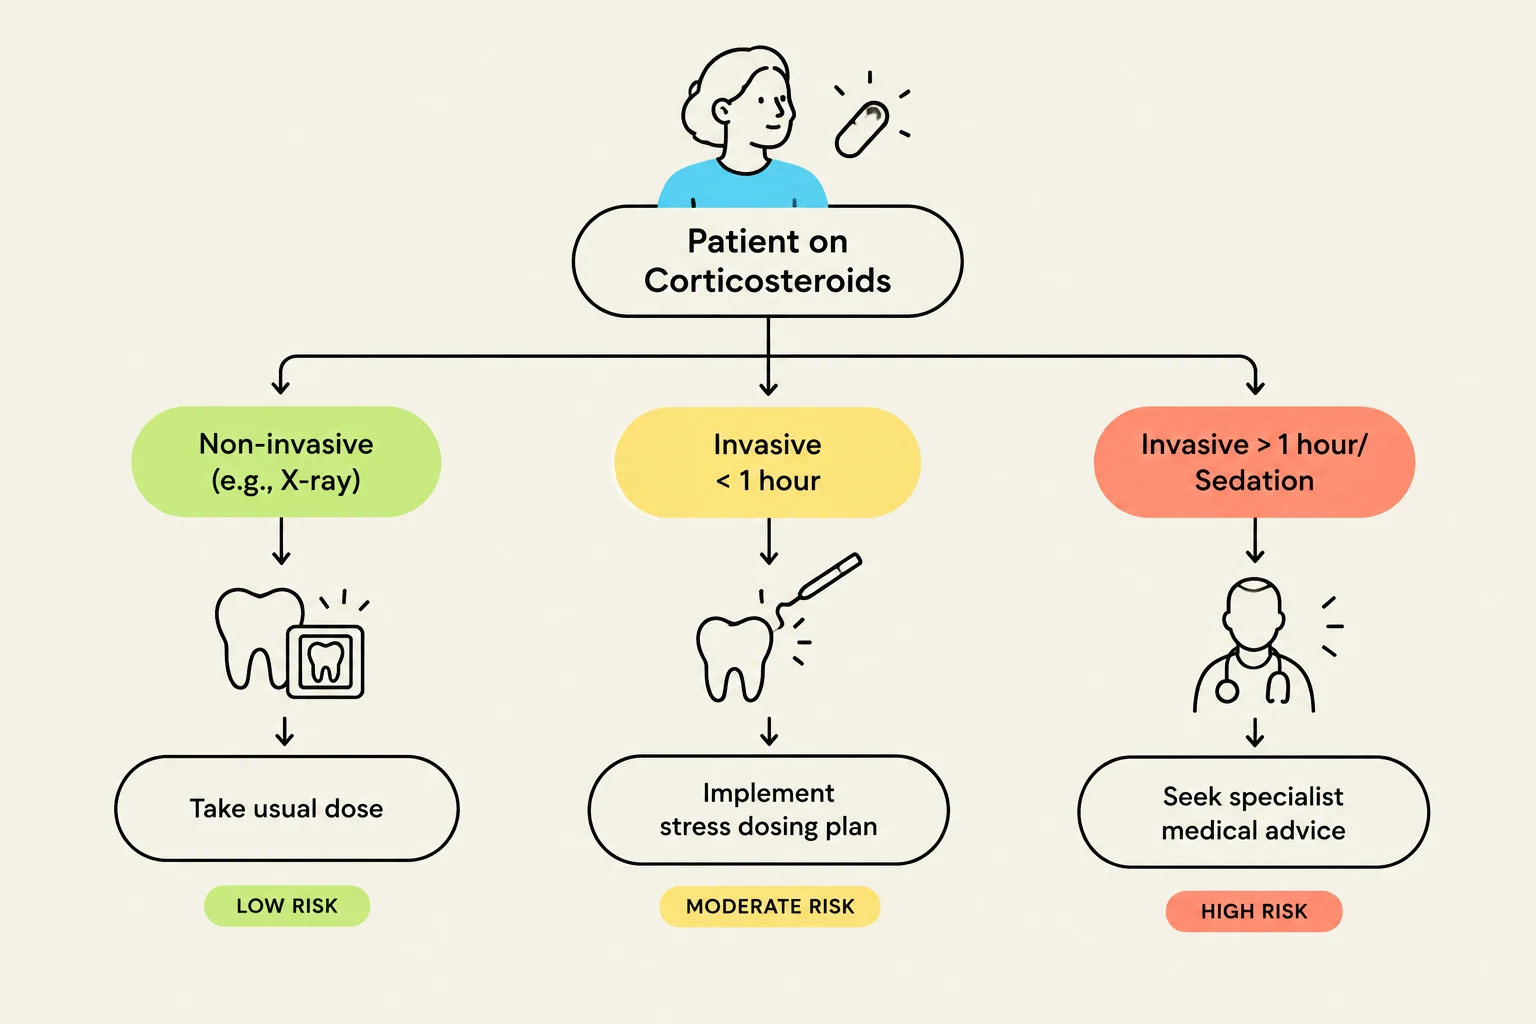
Flowchart illustrating dental procedure considerations for patients on corticosteroids, categorizing risks based on invasiveness and duration.
Medicines can impact dental care through direct oral side effects or by complicating systemic physiological responses during surgery.
1. Corticosteroids and Adrenocortical Suppression
Corticosteroids are potent immunosuppressants that can lead to a wide array of side effects. Short-term effects include hyperglycemia and impaired wound healing, while long-term use can lead to adrenal suppression, osteoporosis, and skin atrophy.
Of particular concern is adrenocortical suppression. Patients taking oral prednisolone ≥5 mg daily for more than 3 weeks are expected to experience suppression.
Perioperative Management of Corticosteroids:
Non-invasive procedures (e.g., X-rays, impressions): No dose increase is required; take the usual dose.
Invasive procedures < 1 hour (e.g., extractions, restorative work): An increased dose of corticosteroid may be required. Patients should have a pre-established "stress dosing" action plan.
Invasive procedures > 1 hour or requiring sedation/GA: Seek specialist medical advice.
2. Bisphosphonates and Denosumab
These medications are frequently associated with Osteonecrosis of the Jaw (ONJ).
Managing patients on Denosumab (e.g., Prolia) requires specific caution. Unlike bisphosphonates, denosumab discontinuation is associated with rapid rebound bone loss and increased fracture risk.
Management Strategy: Do not delay the next dose! If extractions are necessary, try to schedule them at the end of the dosage interval.
3. Anti-angiogenic Drugs
Drugs such as Bevacizumab (Avastin®) and Sunitinib impair the process of neovascularization, which is essential for wound repair. This leads to impaired cutaneous and oral wound healing. These drugs are also frequently associated with oral pain, stomatitis, and taste disturbances.
4. Immunosuppressants and Biologics
Patients using immunosuppressants (e.g., Methotrexate, Cyclosporine) or biologics (e.g., TNF-inhibitors like Humira) face a significantly increased risk of serious infection and malignancy. When treating patients on these agents, clinicians must also consider the side effects of any co-administered drugs, such as methotrexate.
Managing Adverse Drug Reactions (ADRs) in the Oral Cavity
ADRs can manifest in numerous ways, often complicating diagnosis and treatment. Common manifestations include:
Xerostomia (Dry mouth): Often caused by anticholinergics, antidepressants, or inhaled medications.
Bleeding Risks: Caused by anticoagulants, antiplatelets, NSAIDs, and even certain supplements like Fish oil or Turmeric.
Movement Disorders: Such as bruxism or orobuccolingual dyskinesia (OBLD), sometimes linked to antipsychotics or antidepressants.
Infection: Such as oral candidiasis (thrush), particularly with inhaled corticosteroids.
Exam/Clinical Note: Allergy vs. ADR
Do not blindly accept a patient's claim of "allergy." Distinguish between a true allergy and an Adverse Drug Reaction (ADR). Always document the name of the actual drug, the description of the reaction, and how long ago it occurred.
The Role of the Dentist in Deprescribing
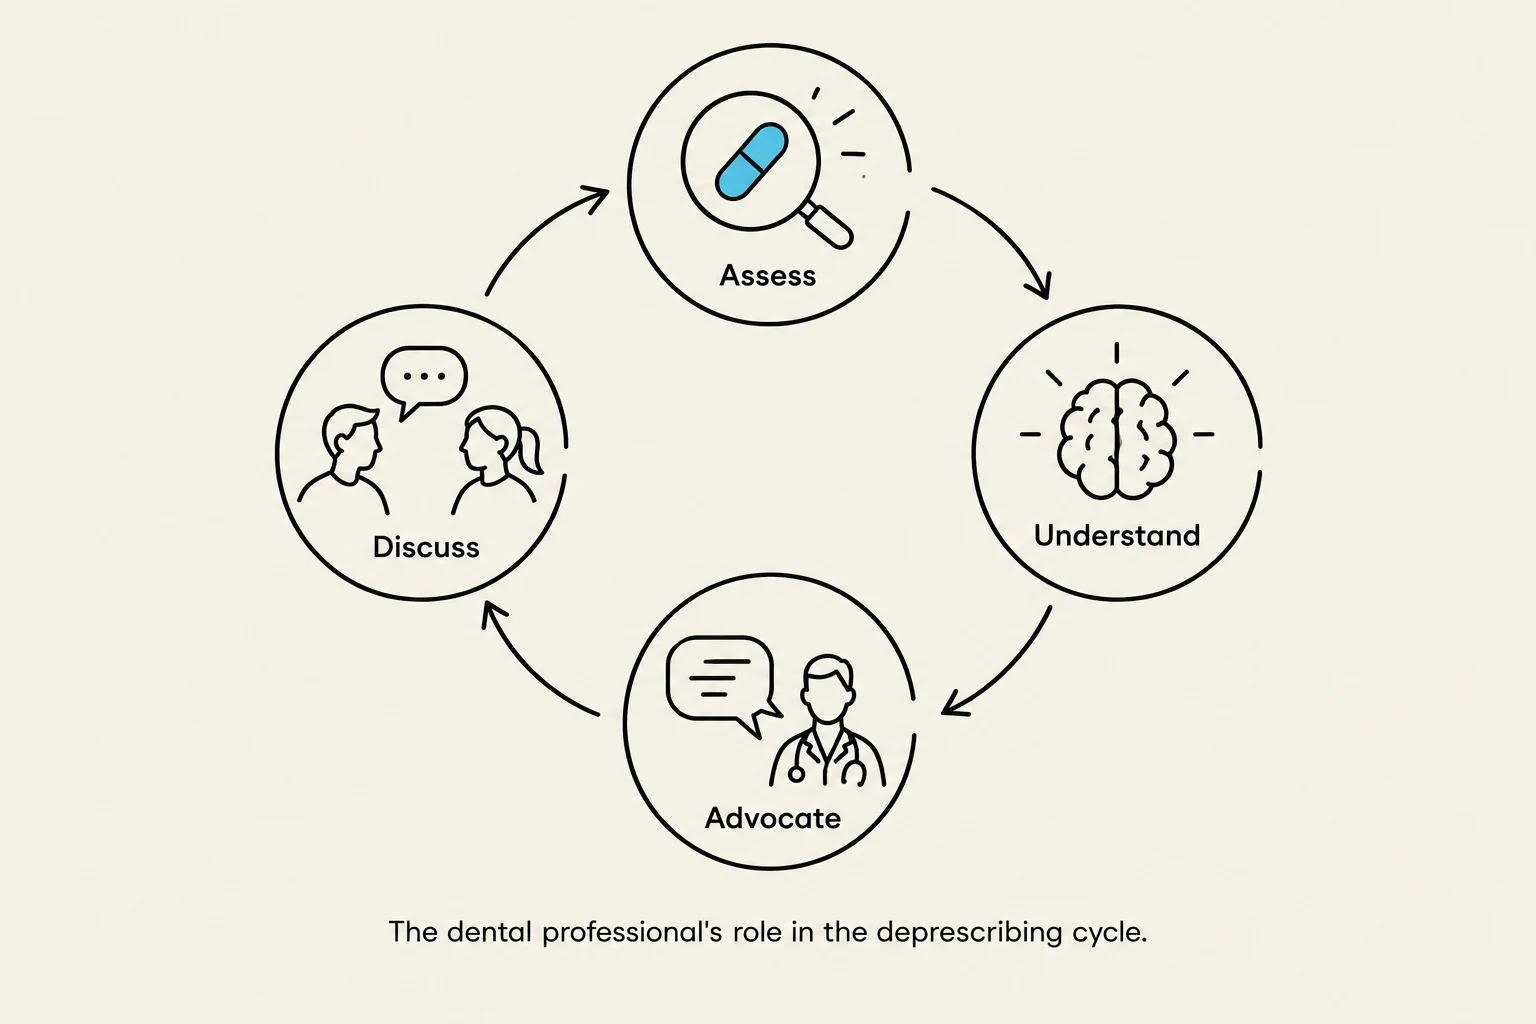
The dental professional's role in the deprescribing cycle.
Deprescribing is the planned and supervised process of reducing or stopping a medication that may be causing harm or is no longer providing benefit.
While prescribing is the primary role of physicians, dental professionals play a vital role in the deprescribing cycle. Because many drugs cause oral side effects that diminish a patient's quality of life (QOL), dentists can act as advocates.
Four actions for dental professionals:
Assess: Determine if a medication confers more risk to oral health than overall systemic benefit.
Understand: Recognize that medical prescribers generally view successful deprescribing as a positive clinical outcome.
Advocate: Communicate drug-induced oral health problems (like severe xerostomia or bleeding) to the patient's physician.
Discuss: Talk to the patient about the possibility of reducing or ceasing drugs to improve their oral QOL.
Summary Table of Key Implications
Drug Class
Primary Dental Risk/Implication
Anticoagulants/Antiplatelets
Increased risk of bleeding
Bisphosphonates/Denosumab
Osteonecrosis of the jaw (ONJ)
Corticosteroids
Impaired wound healing, infection, ONJ
Anticholinergics/Inhalers
Xerostomia (Dry mouth)
Cytotoxics/Immunomodulators
Increased infection risk, stomatitis
Anti-angiogenics
Impaired wound healing, oral pain
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.