A comprehensive guide to the physical examination of the ears, nose, and mouth, covering anatomy, inspection techniques, and common findings for healthcare professionals.
The physical assessment of the head, neck, ears, and nose is a critical component of a comprehensive clinical examination. These structures are not merely anatomical landmarks; they are the gateways to the special senses of hearing, smell, and taste, and they provide vital information regarding respiratory health, neurological integrity, and systemic conditions like gout or genetic syndromes. A systematic approach involving inspection, palpation, and specialized testing ensures that both structural abnormalities and functional deficits are identified.
Anatomy and Landmarks of the Head and Neck
Before diving into specific sensory organs, a clinician must understand the bony and soft tissue framework of the head and neck. The skull provides a protective housing for the brain and is composed of fused bones, including the frontal, parietal, temporal, and occipital bones, as well as the nasal, zygomatic, ethmoid, lacrimal, sphenoid, and maxillary bones. The mandible is the only movable bone of the skull.
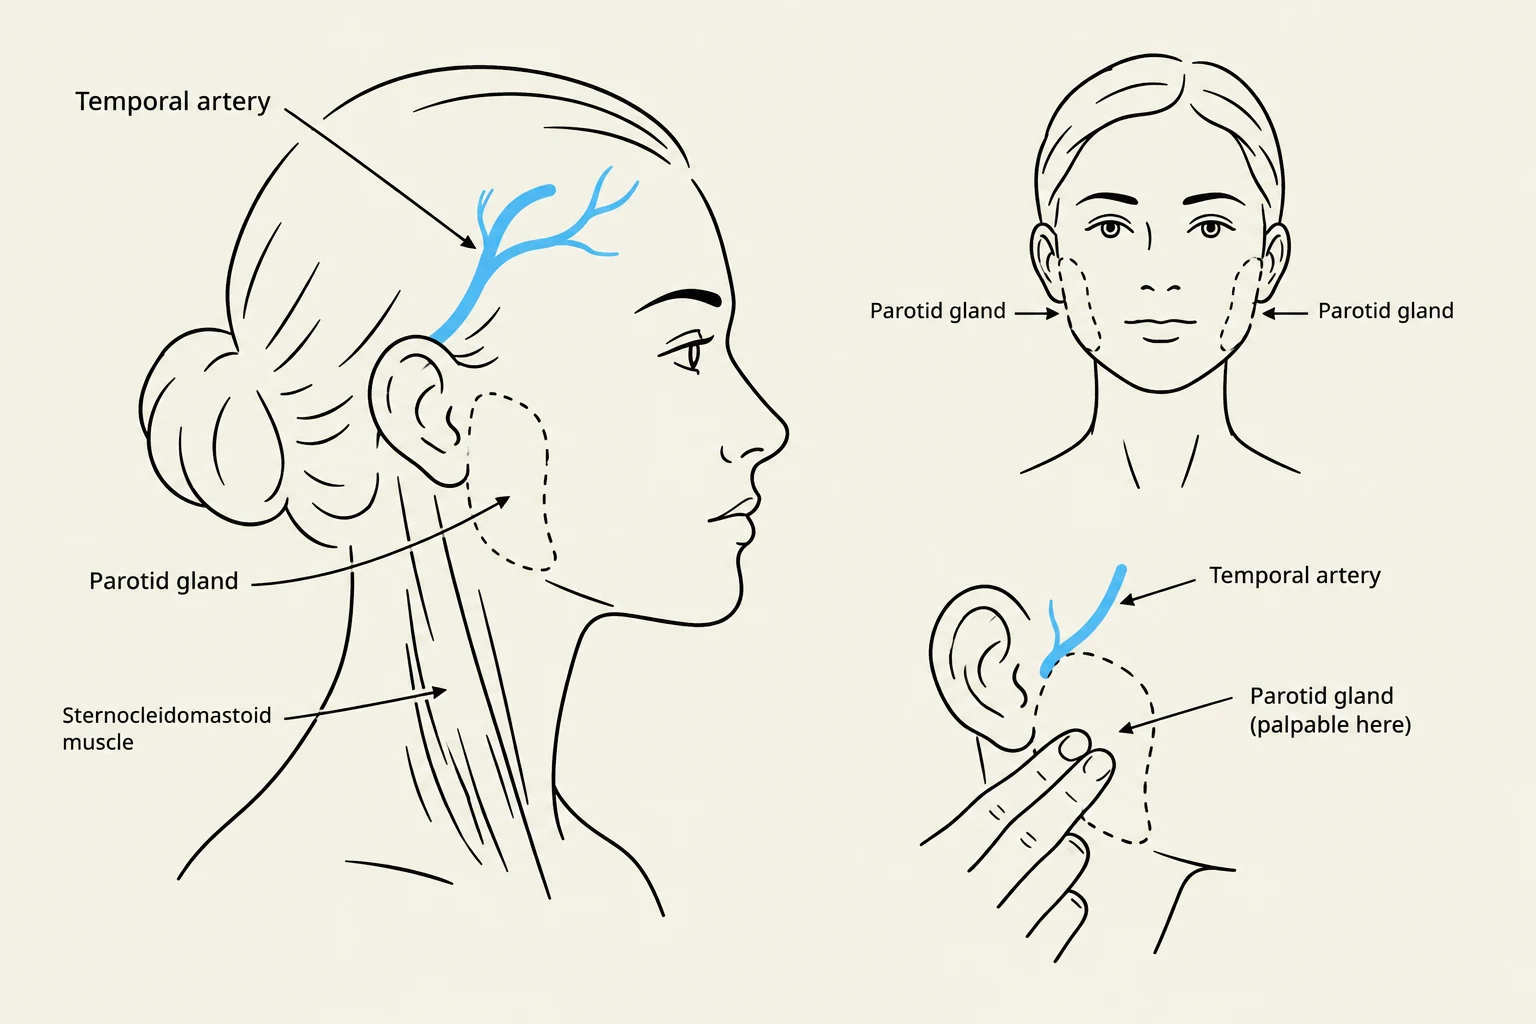
Key facial landmarks include the palpebral fissures (the openings between the eyelids) and the nasolabial folds. For vascular assessment, the temporal artery is a primary landmark, located anterior to the ear and temporal muscle.
Head and Neck Inspection and Palpation
When assessing the head, observe for position (tilted or tremors), symmetry, and any lesions or trauma. In infants, clinicians may need to use transillumination if there is a rapidly increasing head circumference. Palpation should include the scalp, hair texture, and, in infants, the sutures and fontanels.
The neck assessment focuses on symmetry, tracheal alignment, and the presence of masses or webbing. During palpation, note the position of the trachea and the movement of the hyoid bone during swallowing. The thyroid gland should be palpated for size, consistency, and nodules; if an enlargement is noted, auscultation for bruits is required.
Anatomical illustration showing the location of the temporal artery and parotid gland on the human head, with a depiction of the sternocleidomastoid muscle.
Ear Assessment: Structure and Function
The ear is a complex sensory organ responsible for hearing and maintaining equilibrium. It is divided into the external, middle, and inner ear.
Auricle Inspection
The assessment begins with the auricle (or pinna). The clinician should inspect the size, shape, color, and symmetry of the auricle. Specific landmarks and abnormalities to look for include:
Darwin tubercle: A small, cartilaginous prominence on the helix.
Preauricular skin tags: Small pieces of skin located just in front of the ear.
Cauliflower ear: Thickened, deformed cartilage resulting from blunt trauma and necrosis.
Tophi: Small, whitish uric acid crystals along the margins of the auricle, which may indicate gout.
Sebaceous cysts: Elevations in the skin that may indicate a blocked gland.
To assess the position of the auricle, draw an imaginary line between the inner canthus of the eye and the most prominent part of the occiput; the top of the auricle should be at or above this line.
Auditory Canal and Tympanic Membrane
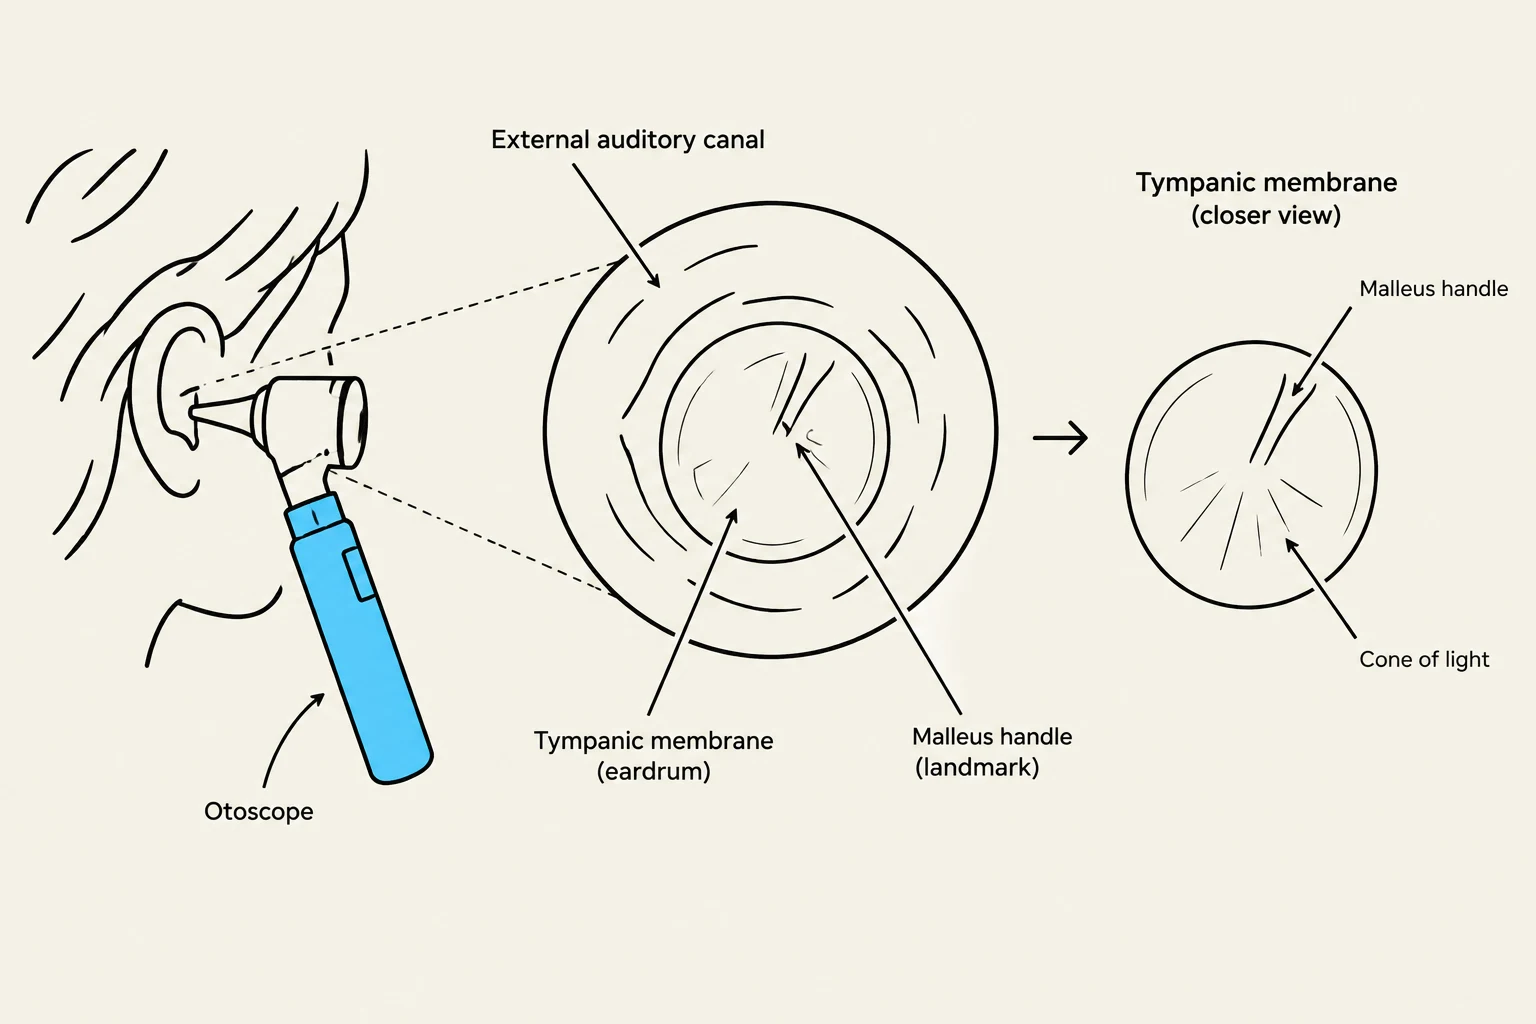
Using an otoscope, the clinician inspects the external auditory canal for cerumen (wax), lesions, discharge, or foreign bodies. A foul-smelling, purulent discharge may suggest otitis externa or a foreign body, while bloody discharge following trauma may indicate a skull fracture.
When performing otoscopy, pull the auricle downward and back for adults (or upward and back for children) to straighten the S-shaped canal. The clinician then inspects the tympanic membrane (TM) for color, contour, landmarks, and mobility.
Clinical Tip: If a patient has been crying, the tympanic membrane may appear pinkish-red due to dilated blood vessels. To distinguish this from acute otitis media, check for mobility; a membrane from crying remains mobile, whereas one from infection does not.
Diagram illustrating the use of an otoscope to view the external auditory canal and tympanic membrane, including a closer view of the tympanic membrane showing the malleus handle and cone of light.
Hearing Assessment
Hearing can be evaluated through several methods:
Whisper Test: Assessing the patient's response to a whispered voice.
Tuning Fork Tests: Using the Weber and Rinne tests to evaluate air and bone conduction.
Audiometry: Formal hearing testing, which is particularly important for children at regular intervals.
For toddlers, clinicians may use noisemakers (like a rattle) or meaningful words (like "Mickey Mouse") to elicit a response.
Nose and Sinus Assessment
The nose serves as the gateway for the respiratory tract and the sense of smell (Cranial Nerve I).
External Nose and Nares
Inspect the nose for shape, size, color, and the patency of the nares. A "saddle nose" deformity may indicate a previous fracture or cartilage inflammation. Look for the "allergic salute"—a transverse crease at the junction of the nose's bone and cartilage—which suggests chronic upward rubbing due to allergies.
Nasal Cavity and Septum
Using an otoscope, the clinician can inspect the internal nasal cavity.
Nasal Mucosa: Should appear pink and moist. Redness may indicate infection, while bluish-gray, boggy mucosa may suggest allergies. A rounded, elongated mass projecting from the mucosa is known as a polyp.
Nasal Septum: Should be midline and relatively straight. Deviations can cause asymmetric nasal cavities.
Clinical Pearl: Chronic cocaine use can lead to nasal mucosal destruction, loss of taste and smell, and perforation of the nasal septum.
Sinus Inspection
The paranasal sinuses (frontal and maxillary) should be palpated for tenderness or edema. Note that maxillary sinuses typically develop by age 4, while frontal sinuses develop between ages 7 and 8. Persistent nasal discharge, congestion, or cough lasting more than 10 days after an upper respiratory infection may indicate a sinus infection.
Mouth and Oral Cavity
While often grouped with the nose and ears, the mouth assessment is vital for assessing nutrition and dental health. Inspect the lips, teeth, gingivae, and tongue.
Key findings include:
Early childhood caries: Dark, decayed areas on incisors often caused by bedtime bottles of juice or formula.
Bruxism: Flattened edges on teeth indicating compulsive grinding.
Fluorosis/Tetracycline staining: Mottled or pitted teeth caused by excessive fluoride or tetracycline use during tooth development.
By integrating the inspection of the ears, nose, and mouth with a thorough understanding of the head and neck anatomy, clinicians can effectively screen for a wide array of sensory, respiratory, and systemic pathologies.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.