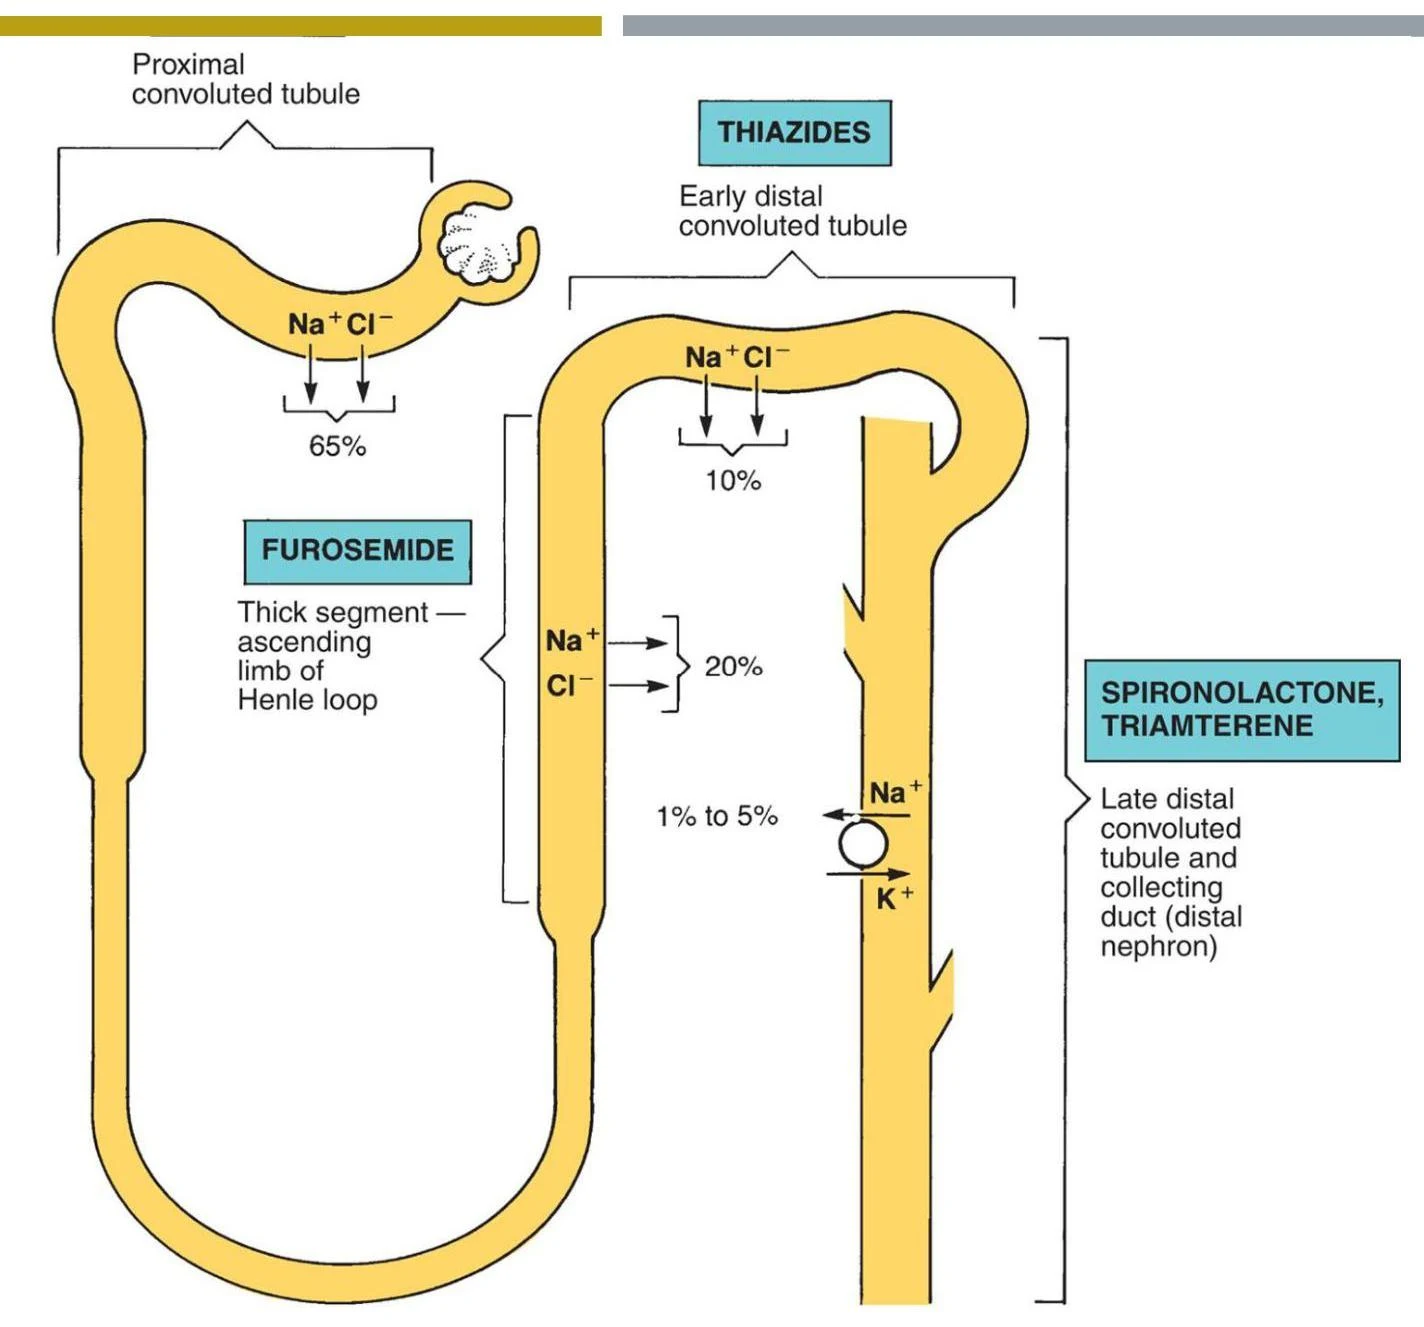
- Indications: Hypertension and edema.
- Nursing Considerations: Monitor for hypokalemia (low potassium) and hyponatremia (low sodium). Administer early in the day to prevent nocturia (waking up at night to urinate).
Loop Diuretics
Furosemide is a potent diuretic that inhibits the sodium-potassium pump in the ascending Loop of Henle. These produce a much more profound diuresis than thiazides and are often used for acute pulmonary edema or severe volume overload.
- Risks: High risk of ototoxicity (hearing damage), hypokalemia, and hypovolemia.
- Nursing Considerations: Monitor urine output and daily weights closely. If given IV, the effect can begin within 5 minutes.
Potassium-Sparing Diuretics and Aldosterone Antagonists
Spironolactone acts as an aldosterone antagonist in the distal nephron. While it provides only a modest increase in urine production, it prevents the excretion of potassium. It is frequently used in combination with other diuretics to counteract the potassium loss caused by thiazides or loop diuretics.
- Risk: The primary danger is hyperkalemia (high potassium).
- Nursing Considerations: Patients should avoid potassium supplements and diets excessively rich in potassium to prevent dangerous levels.
Exam Tip: When reviewing diuretics, always categorize them by their effect on potassium. Thiazides and Loop diuretics cause potassium loss (hypokalemia), while Spironolactone causes potassium retention (hyperkalemia).
Antihypertensive Medication Classes
Antihypertensives aim to reduce blood pressure by either decreasing systemic vascular resistance (vasodilation) or decreasing the workload of the heart.
Calcium Channel Blockers (CCBs)
Amlodipine inhibits calcium ions from entering the channels of vascular smooth muscle. This results in vasodilation, which reduces blood pressure and is used to treat both hypertension and angina.
- Side Effects: Hypotension, flushing, and peripheral/facial edema.
Beta-Adrenergic Blockers
Metoprolol is a selective inhibitor of beta-1 adrenergic receptors located in the heart. By blocking these receptors, the medication reduces the heart rate and the force of contraction, thereby reducing cardiac output and renin secretion from the kidneys.
- Note: These are generally not considered first-line therapy for hypertension.
- Nursing Considerations: Always assess heart rate and blood pressure before administration, as they can cause bradycardia. In diabetic patients, be aware that they can mask the symptoms of hypoglycemia.
ACE Inhibitors and ARBs
These two classes target the Renin-Angiotensin-Aldosterone System (RAAS), which is a major long-term regulator of blood pressure.
- ACE Inhibitors (e.g., Captopril): These competitively inhibit the angiotensin-converting enzyme, preventing the conversion of Angiotensin I to Angiotensin II. This reduces both vasoconstriction and the secretion of aldosterone.
- Key Side Effect: A persistent dry cough or life-threatening angioedema.
- Angiotensin II Receptor Blockers (ARBs) (e.g., Candesartan): Instead of stopping the production of Angiotensin II, ARBs bind directly to the receptors, blocking the hormone's ability to cause vasoconstriction and aldosterone secretion.
- Commonality: Like ACE inhibitors, ARBs carry a risk of hyperkalemia.
Clinical Application: Peripheral Vascular Disease (PVD)
Understanding these medications is vital when managing patients with PVD, which includes both Arterial and Venous diseases.
- Peripheral Arterial Disease (PAD): Characterized by thickening of artery walls and narrowing of the vessels. Patients often experience "intermittent claudication" (pain during exercise that resolves with rest) and may present with cool, pale skin and diminished pulses.
- Chronic Venous Insufficiency: Occurs when vein valves fail, leading to blood pooling and edema. This often results in brownish skin discoloration (hemosiderin staining) and irregular, draining ulcers near the medial malleolus.
| Feature | Peripheral Artery Disease (PAD) | Venous Disease |
|---|
| Pulses | Decreased or absent | Present (may be hard to feel due to edema) |
| Skin Temp | Cool | Warm |
| Edema | Absent (usually) | Common in lower legs |
| Ulcer Location | Toes, foot, or lateral malleolus | Medial malleolus |
| Ulcer Appearance | "Punched out," smooth margins | Irregular, draining |