Pharmacology of Cocaine and Amphetamines: Mechanisms, Metabolism, and Impact
This content examines the pharmacology of cocaine and amphetamines, detailing their distinct mechanisms of action, pharmacokinetic profiles, metabolic pathways, and the resulting psychological and neurological effects. It compares their effects on neurotransmitter systems, particularly dopamine, and discusses the long-
Stimulant drugs represent a significant class of psychoactive substances that profoundly alter central nervous system activity. While both cocaine and amphetamines are categorized as potent stimulants, they are chemically distinct and utilize different biological mechanisms to achieve their effects. Understanding the nuances between these substances—ranging from how they cross the blood-brain barrier to how they are metabolized by the liver—is essential for grasping their varying potentials for addiction, toxicity, and long-term neurological damage.
Cocaine: From Alkaloid to Neurotransmitter Disruptor
Cocaine is a natural alkaloid extracted from the leaves of the Erythroxylum plant. Depending on its preparation, it exists in several forms: coca paste (40-85% purity), cocaine hydrochloride (a hydrophilic salt used for snorting or intravenous injection), and cocaine base (a crystallized form suitable for inhalation/smoking).
Pharmacokinetics and the Blood-Brain Barrier
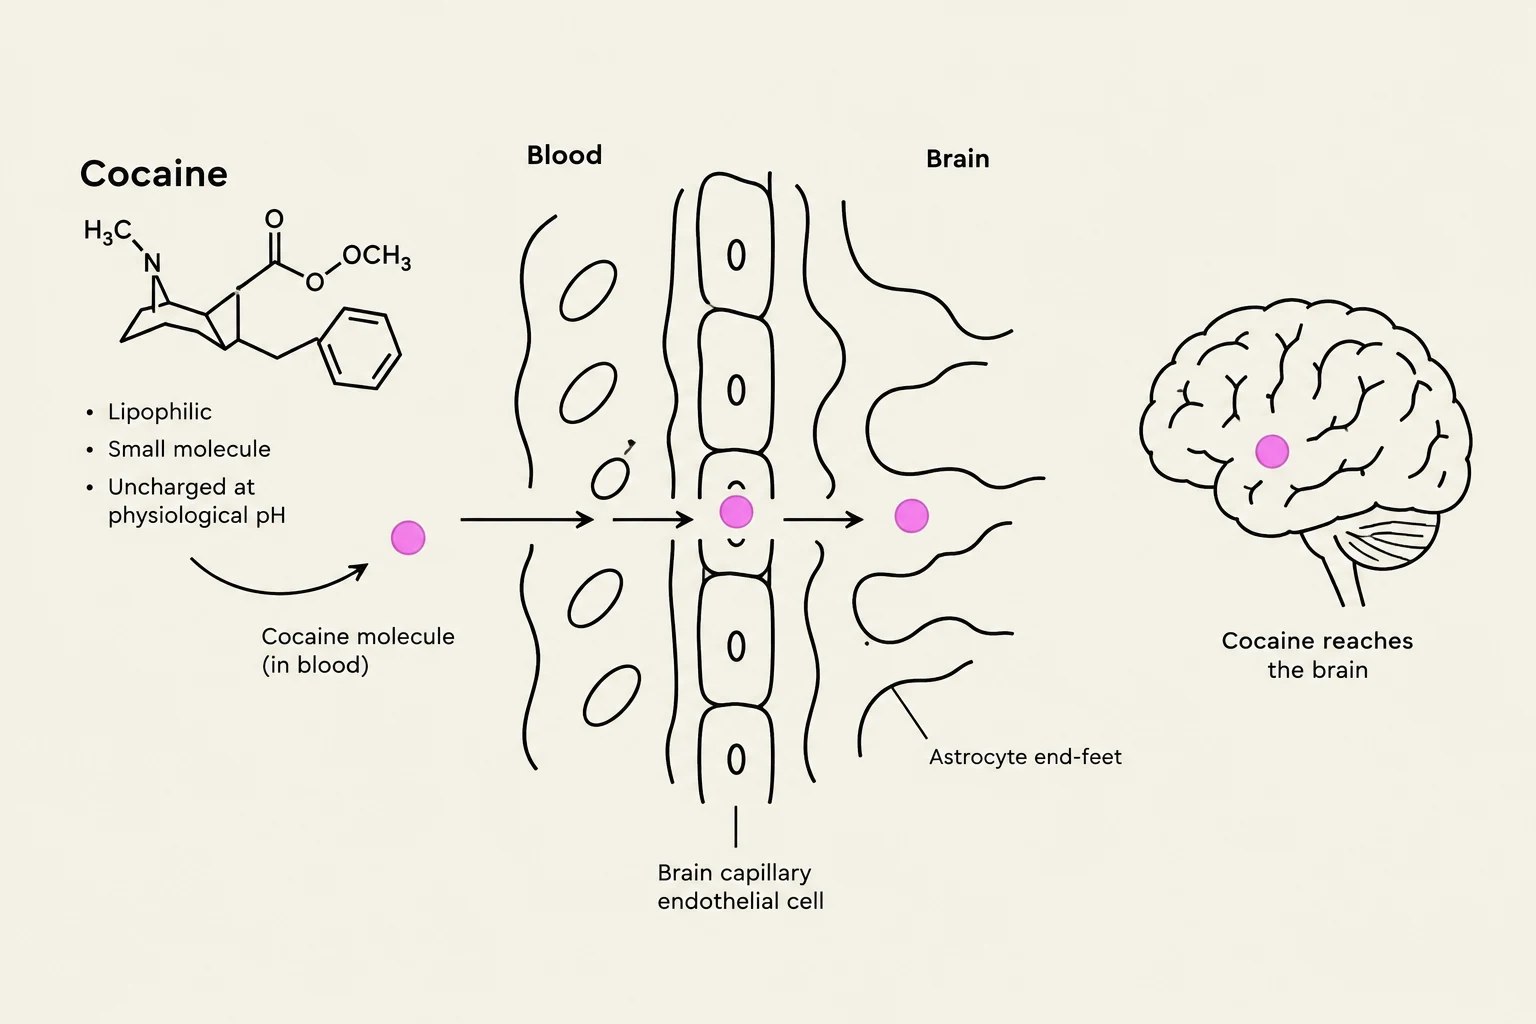
The route of administration significantly influences the onset and duration of cocaine's effects. Because cocaine is relatively lipophilic, it crosses the blood-brain barrier (BBB) with ease. Interestingly, cocaine does not just pass through the BBB; it actually increases the barrier's permeability, allowing other ions and substances to flow across more easily than they normally would.
Clinical Note: While cocaine is lipophilic, the hydrochloride salt form dissociates in the blood. Once in the brain, the concentration of cocaine can be up to 7 times higher than the concentration found in the blood.
Diagram illustrating the passage of a cocaine molecule from the bloodstream into the brain, highlighting its properties as a lipophilic, small, and uncharged molecule at physiological pH, and its interaction with brain capillary endothelial cells and astrocyte end-feet.
Metabolism and the "Cocaethylene" Risk
Cocaine has a relatively short half-life of approximately 50 minutes. It is metabolized in the blood and liver by the enzyme butyrylcholinesterase into benzoylecgonine.
A critical pharmacological interaction occurs when cocaine is consumed alongside alcohol. This combination alters metabolism to produce a unique metabolite called cocaethylene. Cocaethylene acts on the same pharmacological targets as cocaine but possesses a much longer half-life of approximately 150 minutes, significantly extending the drug's presence in the body.
Pharmacodynamics: Reuptake Inhibition
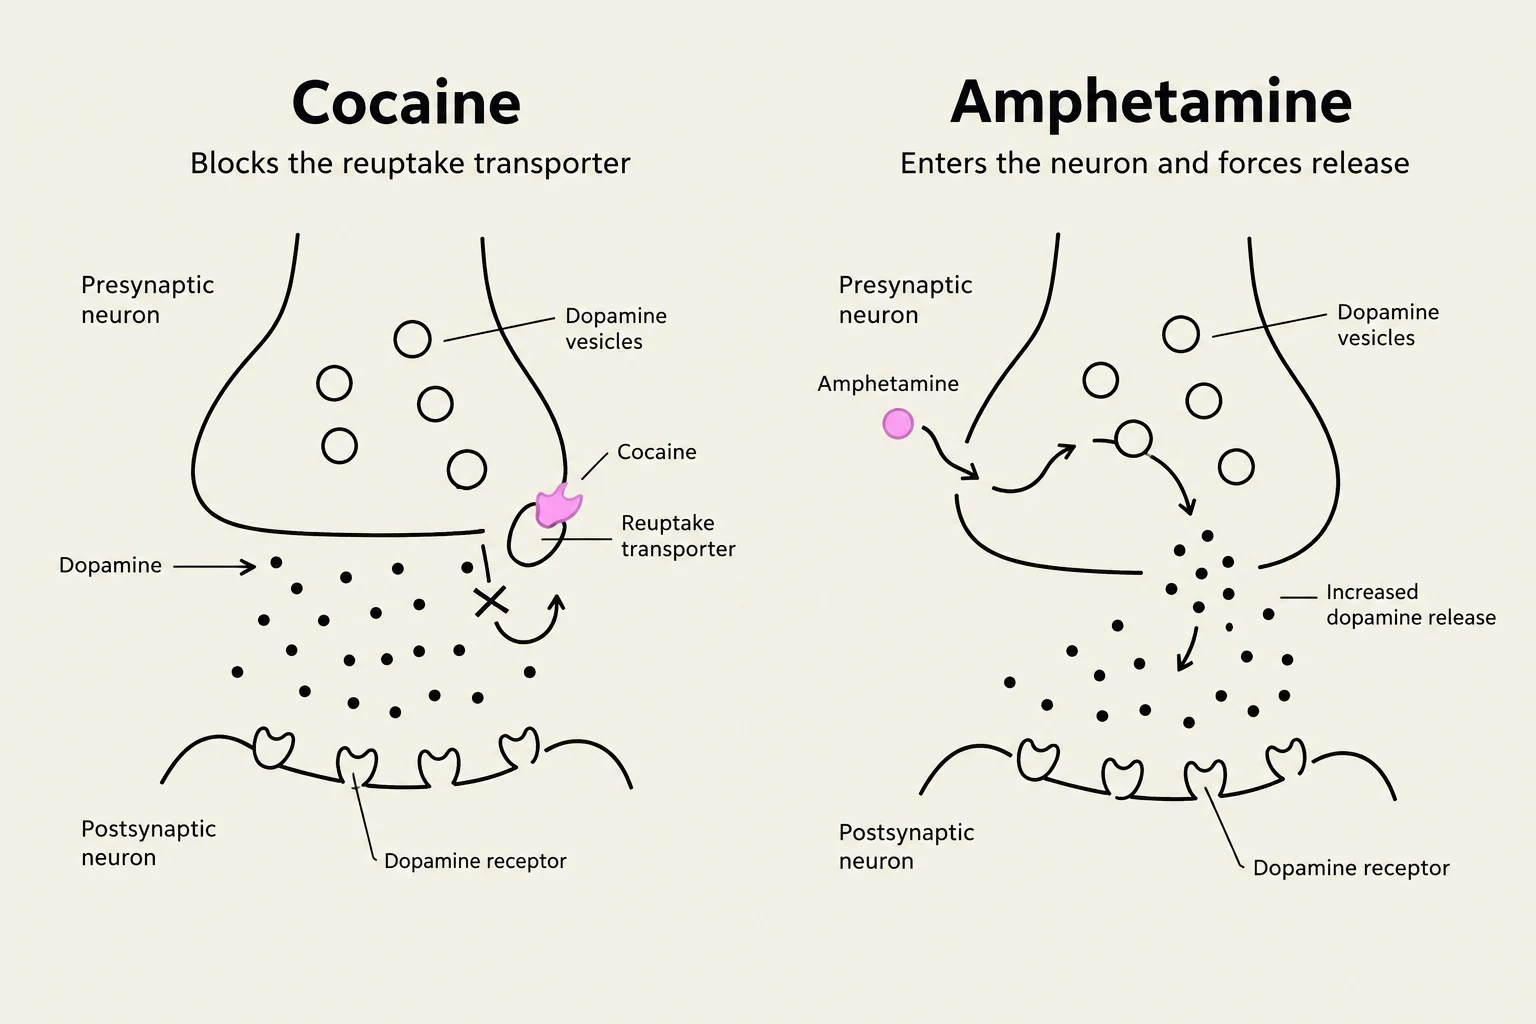
The primary mechanism of cocaine is acting as a reuptake inhibitor. Under normal physiological conditions, neurotransmitters are released into the synaptic cleft and then transported back into the presynaptic neuron via transporters to terminate the signal. Cocaine blocks these transporters, preventing the reuptake of:
Dopamine
Norepinephrine
Serotonin
Epinephrine
The intense euphoria and high potential for addiction are primarily driven by the accumulation of dopamine within the nucleus accumbens. Research using optogenetics and dopamine antagonists has confirmed that the nucleus accumbens is a central target for cocaine-seeking behavior.
Amphetamines: Synthetic Stimulants and Massive Dopamine Release
Unlike cocaine, amphetamines are synthetic compounds. They exist in various isomeric forms, which dictate their potency and efficacy:
d-amphetamine: The right isomer, more potent than the l-isomer.
l-amphetamine: The left isomer.
Methamphetamine: A highly potent derivative with significantly higher lipid solubility, allowing for much faster diffusion into the brain compared to other amphetamines.
A More Aggressive Mechanism of Action
While cocaine simply blocks the "vacuum cleaner" (the reuptake transporter), amphetamines are much more aggressive. Amphetamines:
Enter the presynaptic neuron via transporters.
Bind to vesicle transporters, causing dopamine to build up inside the cell rather than in the vesicles.
Forcefully eject dopamine into the synaptic cleft.
Block the enzyme monoamine oxidase (MAO), which is responsible for breaking down dopamine, thereby ensuring even more neurotransmitter remains available.
Diagrams illustrating the mechanisms of action of cocaine and amphetamine on dopamine neurotransmission in the brain. Cocaine blocks the reuptake transporter, increasing dopamine levels in the synaptic cleft. Amphetamine enters the neuron and forces the release of dopamine, also leading to increased synaptic dopamine.
Metabolism and Excretion
Amphetamines have much longer half-lives than cocaine, ranging from 6 to 14 hours depending on the specific isomer. Because they are metabolized slowly, they are often excreted in their active state, leading to prolonged effects.
Exam Tip: When considering drug excretion, remember that urinary pH matters. For amphetamines, taking antacids that make the urine more basic can reduce the rate of elimination.
Psychological and Physiological Comparison
Both drug classes trigger sympathetic nervous system activation, leading to increased heart rate, elevated blood pressure, increased body temperature, and suppressed appetite. However, their psychological profiles and long-term impacts differ.
Psychological Effects
Effect Level
Cocaine Profile
Amphetamine Profile
Low/Acute Dose
Euphoria, high energy, improved mood, increased alertness
(Low dose/ADHD) Improved cognition, attention, and energy
Severe paranoia, extreme psychosis, repetitive behavior
Long-term Neurological Consequences
Chronic use of both substances is neurotoxic, but the damage manifests in specific ways:
Cocaine: Chronic use is associated with a reduction in grey matter (the regions containing cell bodies). This can lead to cognitive decline, though some reduction may be reversible upon cessation. It also alters dopamine signaling by increasing the sensitivity of D1 receptors and decreasing the sensitivity of D2 receptors.
Amphetamines: High doses can damage the axon terminals of dopamine and serotonin synapses, cause the shrinking of both grey and white matter, and lead to the loss of neurons in the hippocampus.
Substance Use Disorder
For both drugs, the transition from recreational use to substance use disorder is marked by the brain's reward circuits being fundamentally altered. Once dependence is established, the user often finds themselves managing debilitating withdrawal symptoms as much as they are pursuing the initial "high". Treatment typically involves Cognitive Behavioral Therapy (CBT) or medications designed to mitigate withdrawal or lower cravings by targeting glutamate activity in the prefrontal cortex.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.