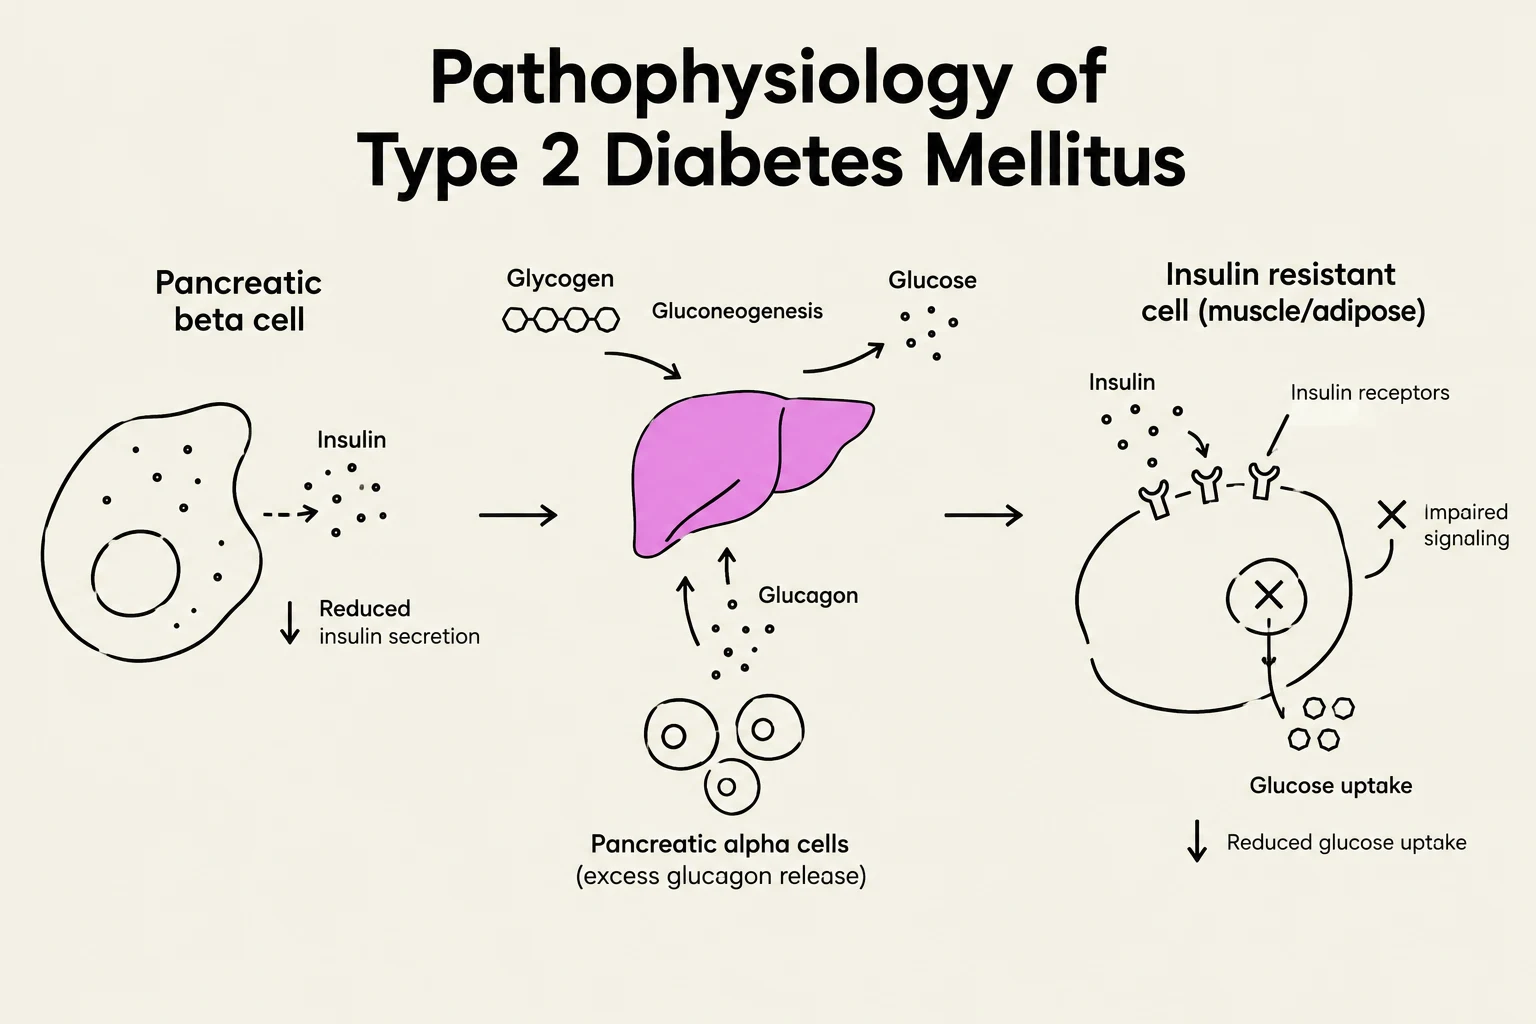
Type 2 Diabetes Mellitus (T2DM) is a progressive metabolic disorder characterized by a combination of decreased insulin production and decreased insulin sensitivity (insulin resistance). As the disease advances, the body struggles to maintain insulin homeostasis, often resulting in increased glucagon production by alpha-cells and a loss of the critical insulin spike typically seen during meal times.
Diagram illustrating the pathophysiology of Type 2 Diabetes Mellitus, showing reduced insulin secretion from pancreatic beta cells, impaired insulin signaling in insulin-resistant cells, and the role of the liver and pancreatic alpha cells.
Effective clinical management requires a multi-faceted approach. Beyond simply lowering blood glucose, modern therapy aims to reduce the risk of microvascular complications (retinopathy, nephropathy, and neuropathy) and macrovascular complications (coronary artery disease, peripheral artery disease, and cerebrovascular accidents). Because obesity is a primary risk factor for T2DM, weight management has become a central pillar of treatment, with many pharmacological agents offering dual benefits for both glycemic control and weight reduction.
First-Line Therapy and Traditional Agents
Biguanides (Metformin)
Metformin remains the first-line therapy for both Type 2 Diabetes and pre-diabetes. While its exact mechanism of action is not fully understood, it is known to reduce gluconeogenesis in the liver, increase glucose uptake at target cells, and decrease intestinal absorption of glucose.
Metformin is generally weight-neutral and carries a low risk of hypoglycemia. However, clinicians must monitor for common gastrointestinal side effects, such as nausea, vomiting, and diarrhea, which affect over 50% of patients. Long-term use may also lead to Vitamin B12 deficiency.
Thiazolidinediones (TZDs)
Agents like Pioglitazone (Actos®) improve peripheral insulin sensitivity by acting on the peroxisome proliferator-activated receptor-gamma (PPARγ). While effective, TZDs are associated with weight gain due to slowed fat breakdown and fluid retention. Because of the risk of fluid retention, they are strictly contraindicated in patients with heart failure.
Alpha-Glucosidase Inhibitors
Acarbose (Glucobay®) works by blocking the intestinal absorption of carbohydrates, preventing the breakdown of complex carbs into glucose. This medication is weight-neutral but frequently causes GI side effects like flatulence, cramping, and diarrhea.
Clinical Pearl: Hypoglycemia Management
When treating hypoglycemia in a patient taking an alpha-glucosidase inhibitor, you cannot rely on complex carbohydrates or sucrose (table sugar) because the medication blocks their breakdown. You must use pure glucose (e.g., glucose tablets or gel) to ensure rapid absorption.
Incretin-Based Therapies: The New Frontier
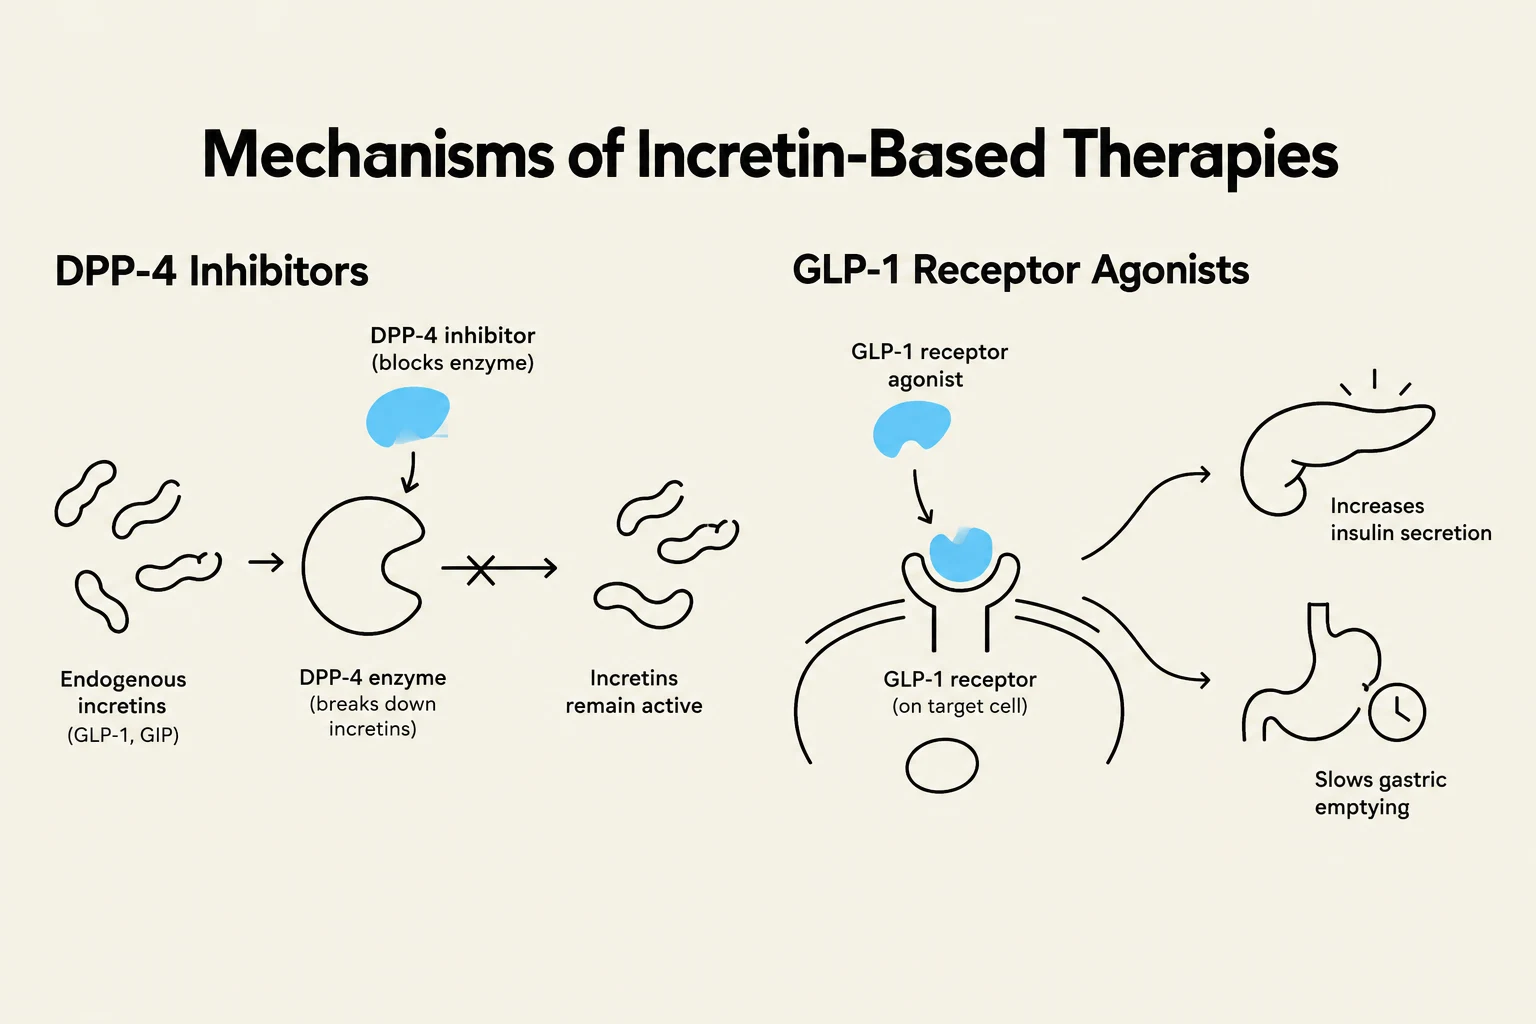
Diagram illustrating the mechanisms of DPP-4 inhibitors and GLP-1 receptor agonists in regulating incretin hormones, which affect insulin secretion and gastric emptying.
Incretins (GLP-1 and GIP) are hormones released by the GI tract that increase insulin secretion, decrease glucagon secretion, and slow gastric emptying.
DPP-4 Inhibitors
Dipeptidyl-peptidase-4 (DPP-4) inhibitors, such as Sitagliptin (Januvia®) and Linagliptin (Trajenta®), prevent the rapid breakdown of endogenous incretins. These drugs are generally weight-neutral and have a low risk of hypoglycemia. Linagliptin is often the drug of choice for patients with renal impairment.
GLP-1 Receptor Agonists (GLP-1RA)
These agents stimulate incretin receptors directly, providing more potent effects than DPP-4 inhibitors.
Liraglutide (Saxenda®/Victoza®): Saxenda® is specifically approved for weight loss and can promote a loss of approximately 5% of body weight.
Semaglutide (Ozempic®/Wegovy®): Wegovy® is approved for weight loss and can lead to a 5–10% reduction in body weight.
Incretin Mimetics (Dual Agonists)
Tirzepatide (Mounjaro®/Zepbound®) represents a significant advancement by targeting both GLP-1 and GIP receptors. This dual action provides enhanced efficacy, with studies showing weight loss as high as 21% after 18 months of use.
Renal and Cardiovascular Considerations
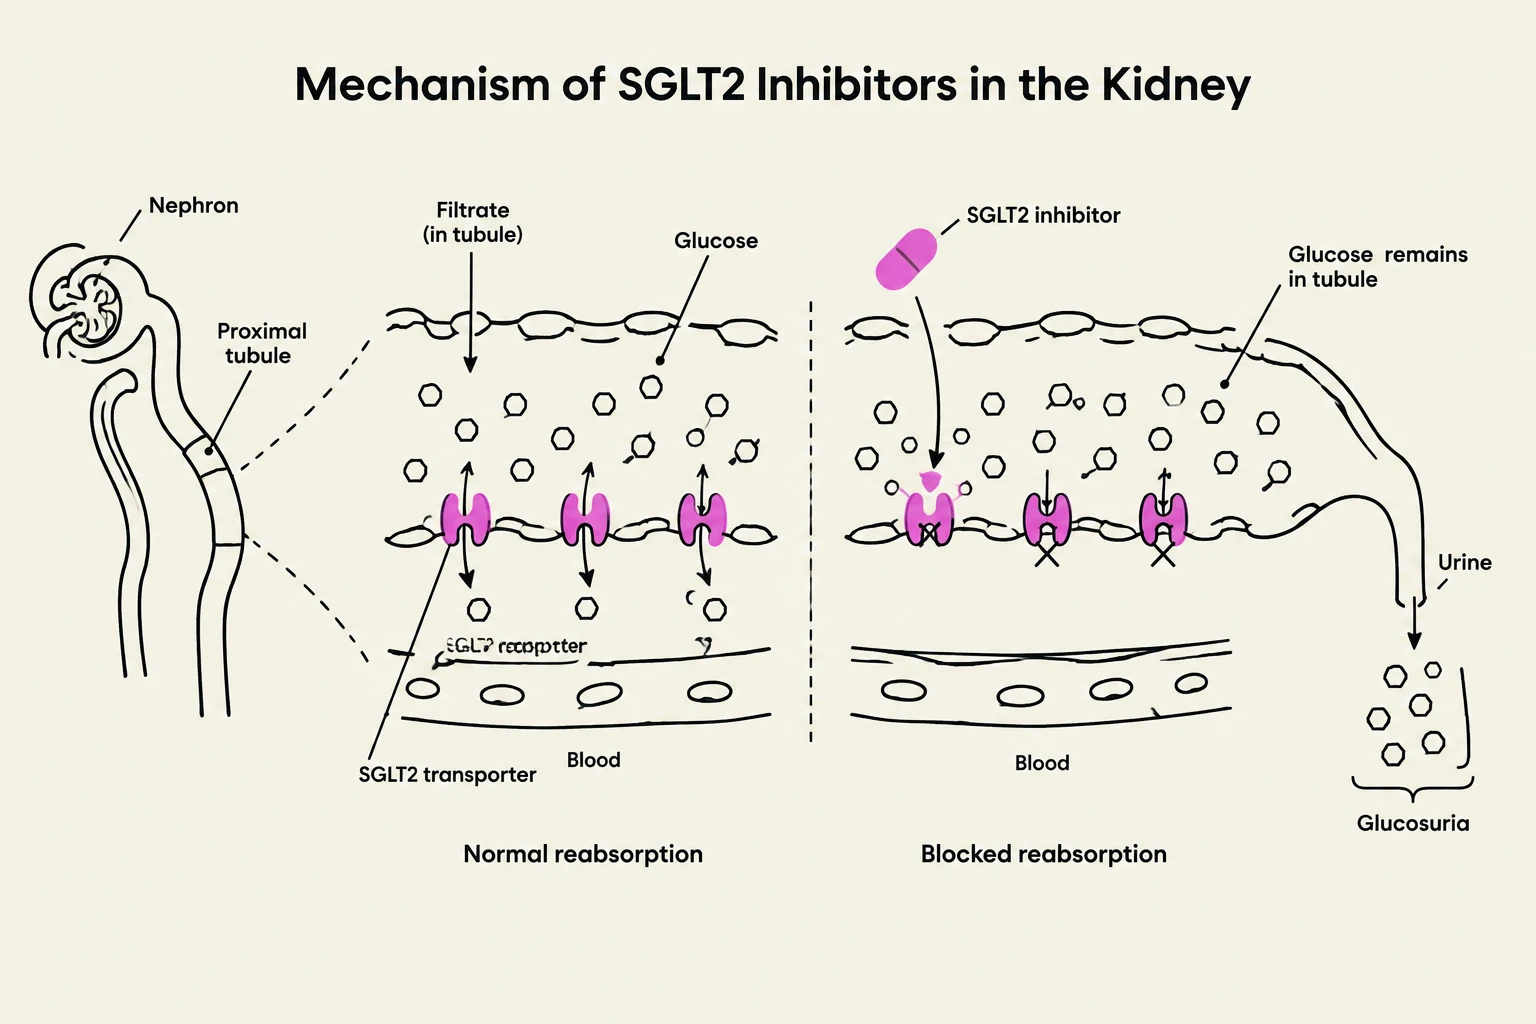
Diagram illustrating the mechanism of SGLT2 inhibitors in the kidney, showing how they block glucose reabsorption in the proximal tubule, leading to glucosuria.
SGLT2 Inhibitors
Sodium-Glucose Cotransporter-2 (SGLT2) inhibitors, such as Empagliflozin (Jardiance®) and Dapagliflozin (Forxiga®), work by preventing the kidneys from reabsorbing glucose, allowing it to be excreted in the urine.
This class offers significant benefits beyond glucose lowering:
Weight Loss: Modest weight loss of approximately 2–3 lbs.
Cardio-Renal Protection: They provide protection for the heart and kidneys, even in patients without diabetes.
Warning: Side Effects of SGLT2i
Because these drugs promote glucose excretion in the urine, patients are at an increased risk for recurrent vaginal yeast infections and urinary tract infections. Additionally, the osmotic effect of glucose can lead to dehydration and hypotension.
Insulin Secretagogues and Hypoglycemia Risk
Insulin secretagogues, specifically Sulfonylureas (e.g., Glyburide, Glimepiride), stimulate pancreatic beta cells to release more insulin. While effective at lowering A1C, they carry two major risks:
Weight Gain: Insulin is an anabolic hormone.
Hypoglycemia: This is a significant concern, especially in elderly populations. Glyburide, in particular, has been noted for having the highest hypoglycemic risk among sulfonylureas.
Meglitinides (e.g., Repaglinide) are a sub-class of secretagogues that provide a shorter, more targeted insulin release, making them useful for patients with unpredictable meal schedules.
Pharmacological Weight Management Agents
When weight management is a primary clinical goal, several non-diabetes-specific agents may be utilized:
Medication
Mechanism of Action (MOA)
Common Side Effects
Orlistat (Xenical®)
Inhibits the lipase enzyme, preventing the absorption of dietary fats.
Diarrhea, gas, bloating, and oily rectal leakage.
Bupropion/Naltrexone (Contrave XR®)
Impacts brain reward centers to decrease appetite and cravings.
Nausea, constipation, dry mouth, and headache.
Exam Tip: Contrave Contraindications
Always screen patients for a history of seizures, eating disorders (anorexia/bulimia), or active alcohol withdrawal before prescribing Bupropion/Naltrexone, as these are absolute contraindications.
Summary Table of T2DM Drug Classes
Drug Class
Weight Effect
Hypoglycemia Risk
Key Benefit
Biguanides
Neutral/Loss
Low
First-line therapy
SGLT2i
Loss
Low
Cardio-renal protection
GLP-1RA
Significant Loss
Low
CV risk reduction
Dual Agonists (GIP/GLP-1)
Very High Loss
Low
Superior weight management
DPP-4i
Neutral
Low
Well-tolerated
Sulfonylureas
Gain
High
Low cost
Thiazolidinediones
Gain
Low
Improves insulin sensitivity
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.