Pharmacological Interventions for Labour Pain Management
An overview of pharmacological methods used to manage pain during different stages of labour, including inhaled analgesia, systemic opioids, and regional anesthesia like epidurals. Discusses mechanisms, administration, and potential side effects.
Managing pain during labour is a critical component of obstetric care, requiring a balance between maternal comfort and fetal safety. As labour progresses through different stages, the nature of the pain changes—from the uterine ischemia and cervical distension of the first stage to the intense, localized stretching of the perineum during the second stage. To address these varying sensations, healthcare providers utilize a spectrum of pharmacological interventions, ranging from inhaled gases to regional anesthesia.
Inhaled Analgesia: Nitrous Oxide
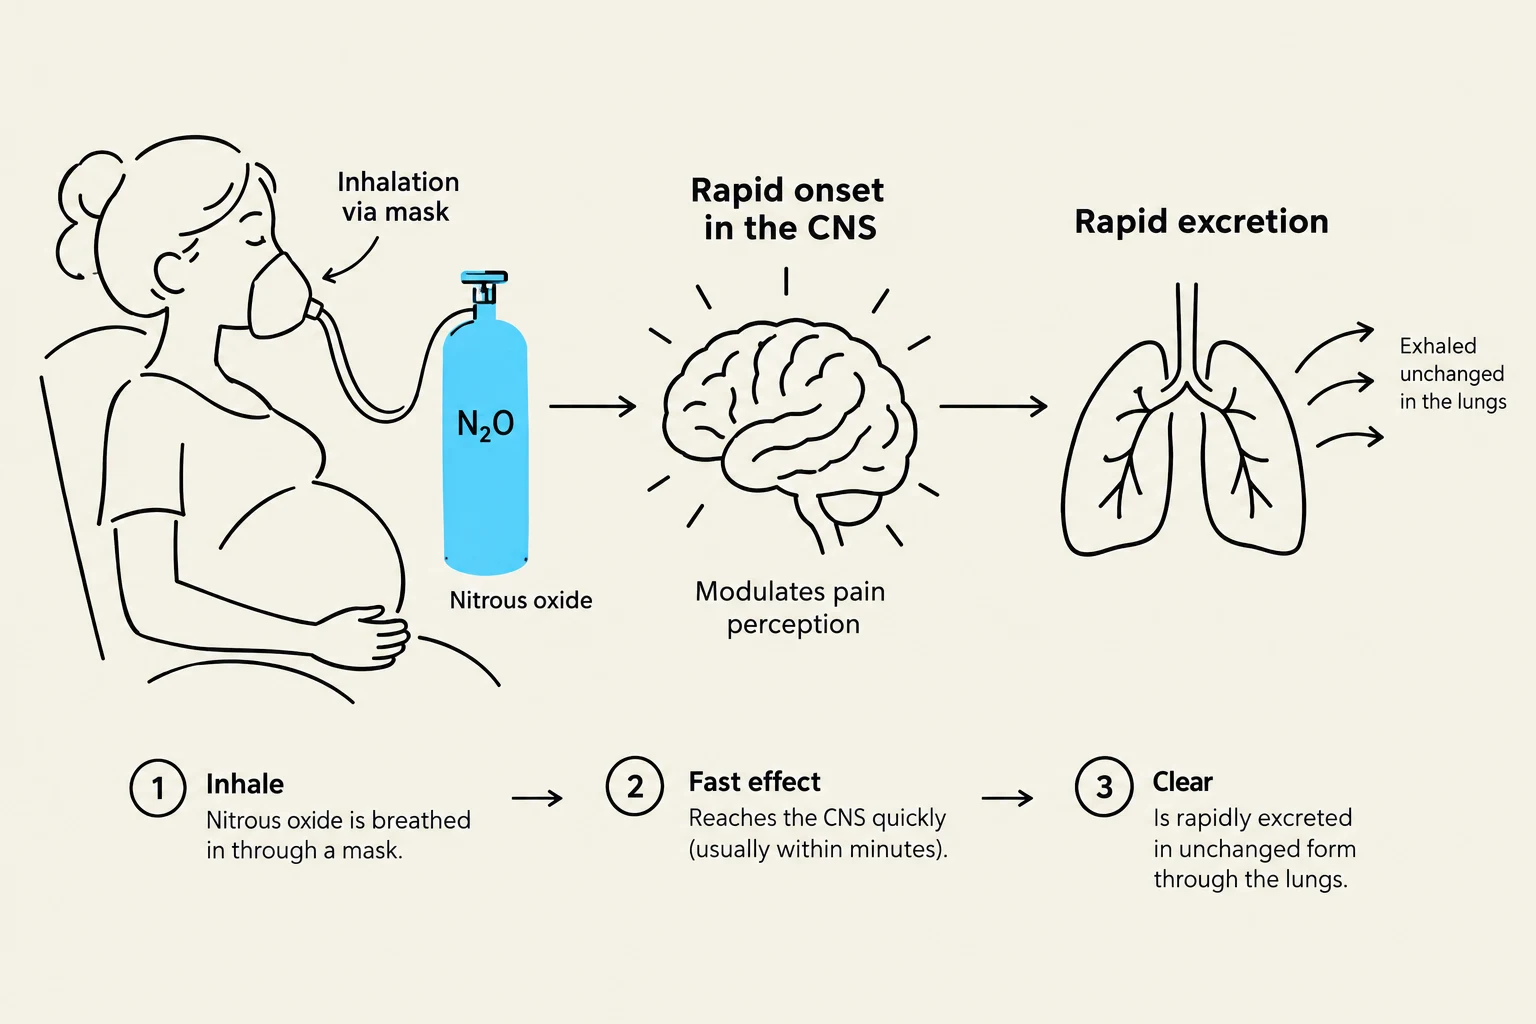
Nitrous oxide, often referred to as "laughing gas," is a non-invasive option that can be used during any stage of labour. It consists of a 50/50 mixture of oxygen and nitrous oxide administered via a mask.
As a central nervous system (CNS) depressant, it works by altering the perception of pain stimuli rather than eliminating the pain entirely. One of its primary advantages is that it allows the birther to remain awake and alert, and because it is excreted quickly, it has no significant effect on the fetus or newborn. However, it can cause side effects such as nausea, vomiting, and dizziness.
Clinical Tip: Patient Instruction
Instruct the patient to self-administer the gas. They should take the mask off between contractions and ensure a tight seal between the mask and their face/nose area. Taking slow, deep breaths achieves the greatest effect.
Diagram illustrating the process of nitrous oxide inhalation, its rapid onset in the central nervous system (CNS) where it modulates pain perception, and its rapid excretion unchanged through the lungs.
Systemic Opioid Analgesia
Systemic opioids are administered to provide relief during the early or active stages of labour. The two most common agents are Morphine and Fentanyl.
Morphine: Typically administered via subcutaneous, intramuscular, or intravenous routes, it has an onset of 5–30 minutes and a duration of 4–5 hours. It is often best timed for early labour.
Fentanyl: This is a faster-acting agent, with an onset of 2–3 minutes, and is typically used during active labour for short-term relief, such as during a procedure or while awaiting an epidural.
While these medications can create a sense of euphoria, they carry significant risks. Because they cross the placenta, they can affect the fetus and newborn, potentially leading to decreased fetal heart rate (FHR) variability or neonatal respiratory depression.
Nursing Alert: Naloxone Hydrochloride (Narcan)
If opioid-induced respiratory depression is suspected in the newborn, Naloxone Hydrochloride (Narcan) must be administered to reverse the effects.
Regional Anesthesia: Epidural Management
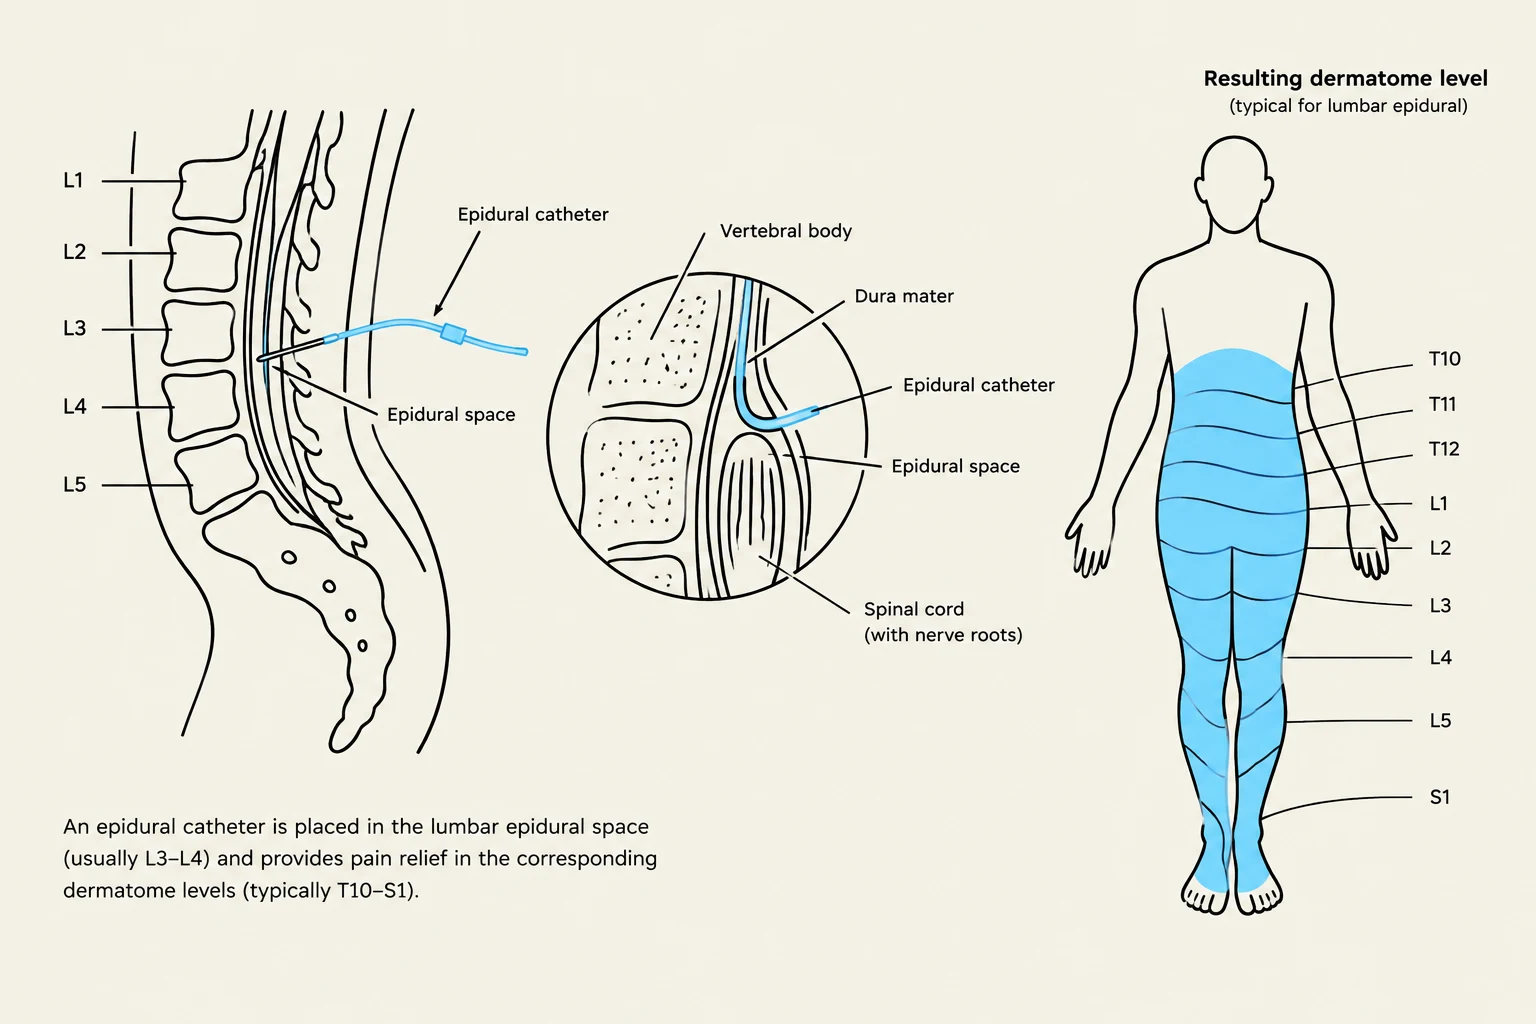
Epidural anesthesia and analgesia are the most common and effective methods for managing labour pain. An epidural involves injecting a local anesthetic (such as Bupivacaine) and/or an opioid analgesic into the epidural space via a catheter inserted into the 4th or 5th lumbar vertebrae.
Mechanism and Effects
The goal of an epidural is to block pain and temperature transmission while ideally preserving motor function.
Epidural Anesthesia: Uses local anesthetics and opioids to provide more profound relief, which may limit movement.
The effectiveness of the block is often assessed by checking the dermatome levels—the specific levels at which the patient can still detect temperature or pain. For a vaginal birth, a dermatome level of T10–T5 is usually sufficient, whereas T12–T10 may suffice for general labour pain.
An illustration showing the placement of an epidural catheter in the lumbar epidural space and the corresponding dermatome levels for pain relief.
Nursing Role in Epidural Care
The nurse plays a vital role in the "before, during, and after" phases of epidural administration:
Before: Provide a history (prenatals, BMI, recent labs) to the anesthesiologist and ensure the patient has voided.
During: Monitor the patient for side effects like tinnitus, tingling lips, or blurred vision. Assist with positioning (lateral or sitting) to allow catheter insertion.
After: Monitor vital signs and FHR every 2 minutes for 10 minutes due to the high risk of maternal hypotension. Assess motor function (the ability to move limbs) before any ambulation is attempted.
Second Stage Interventions: Local and Pudendal Blocks
As the birther enters the second stage of labour, pain becomes more localized to the perineum due to the stretching of tissues and pressure on pelvic structures.
Local Anesthesia to the Perineum: This is administered directly to the perineal tissue before birth to facilitate an episiotomy or to manage lacerations.
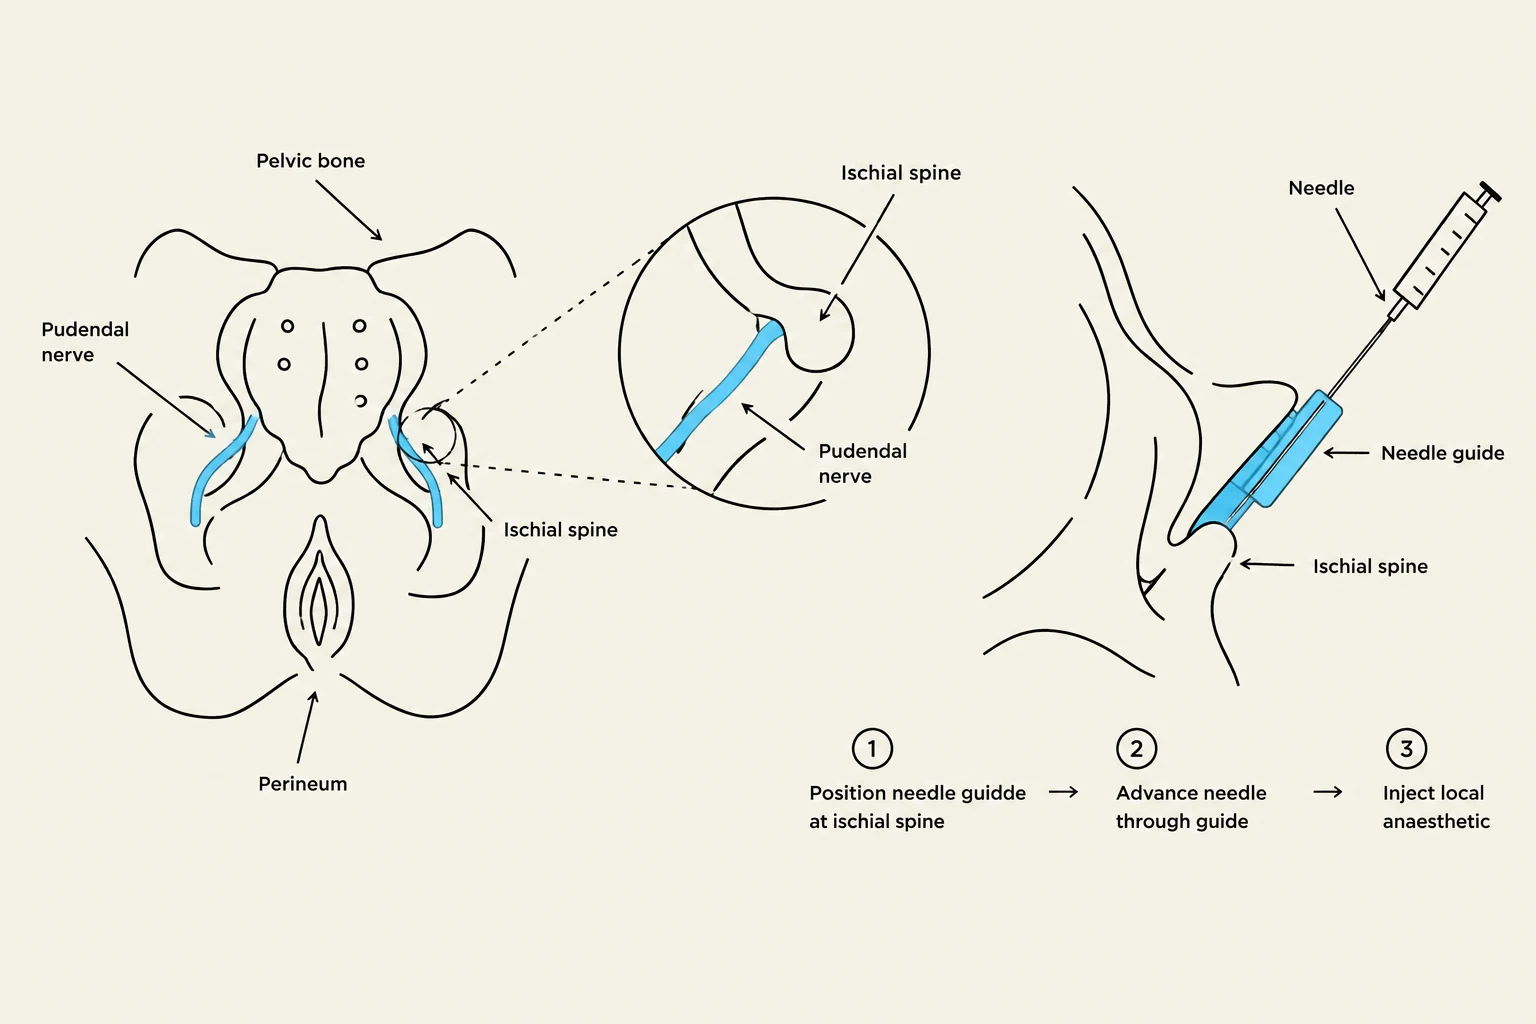
Pudendal Block: This is used for pain relief during an assisted birth or when extensive postpartum repair of a laceration is required.
Diagram illustrating the anatomical location of the pudendal nerve and ischial spine, with a step-by-step guide for administering a local anesthetic injection.
Summary of Side Effects
Pharmacological interventions must be balanced against potential adverse effects: