Pediatric Musculoskeletal and Articular Dysfunction
An overview of pediatric musculoskeletal care, covering developmental hip and foot deformities, bone disorders, spinal issues, injuries, fractures, and inflammatory/neuromuscular conditions. Includes diagnostic markers, treatment timelines, and management priorities.
Pediatric musculoskeletal care involves a complex understanding of how bones, joints, and muscles develop and respond to injury or disease. Unlike adults, children possess growing bones, active growth plates, and a remarkable capacity for remodeling, which necessitates specialized assessment and management strategies. This article explores advanced concepts in pediatric care, ranging from developmental hip and foot deformities to bone disorders, spinal issues, and inflammatory conditions.
Developmental Dysplasia of the Hip (DDH)
Developmental Dysplasia of the Hip (DDH) represents a spectrum of abnormal hip development, ranging from mild instability to complete dislocation. Early detection is the single most critical factor for achieving optimal long-term outcomes.
Recognition and Diagnosis
In infants, clinicians look for specific physical markers during examination:
Hip Joint Laxity: Excessive movement during examination.
Asymmetric Folds: Unequal gluteal or thigh creases when the infant is prone.
Limited Abduction: Restricted hip movement on the affected side.
Leg Shortening: The affected side may appear shorter when the infant is supine.
Diagnosis is often confirmed through the Ortolani and Barlow maneuvers.
Treatment Timeline
Treatment is highly dependent on the child's age:
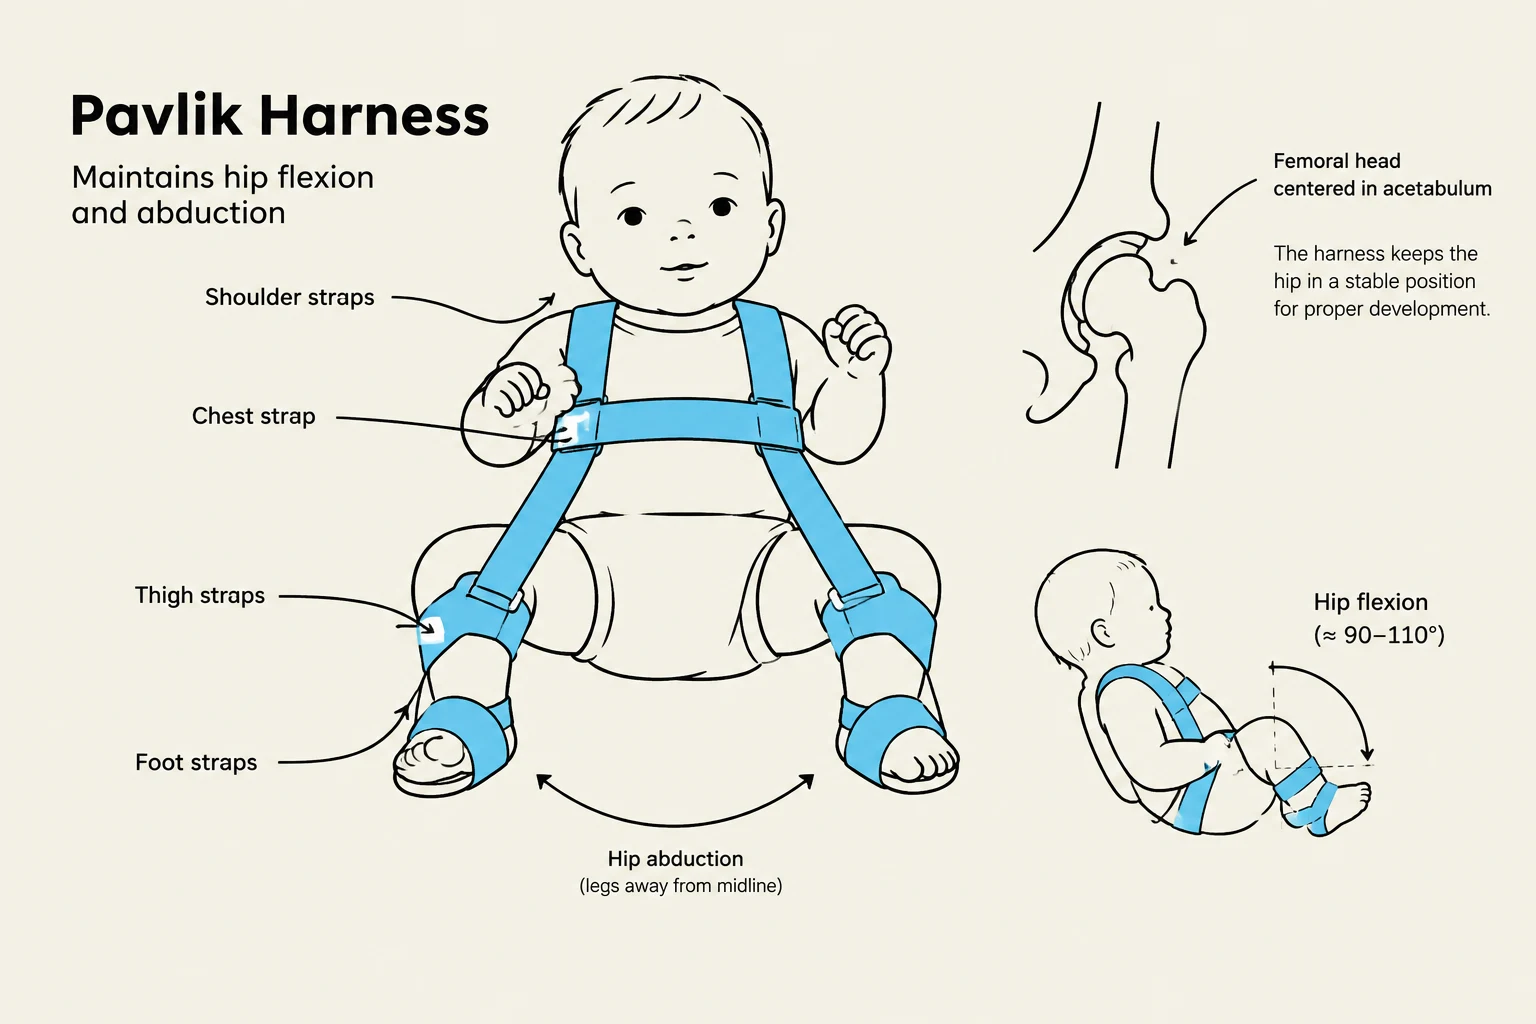
Birth to 6 Months: The Pavlik harness is the first-line, non-invasive treatment. It maintains the hip in flexion and abduction to promote normal acetabular development.
6 to 24 Months: As the child begins walking, closed reduction followed by a spica cast may be required.
Older Children (Post-age 4): Surgical correction via osteotomy becomes necessary, though outcomes are more difficult to manage than in infants.
The Pavlik Harness is illustrated, showing its components and how it maintains hip flexion and abduction for proper hip development in infants. Diagrams depict the femoral head centered in the acetabulum and the range of hip flexion.
Nursing Focus: When caring for an infant in a Pavlik harness, prioritize parent education on proper application, frequent skin assessments under the straps, and constant monitoring of the hip position.
Foot and Spinal Deformities
Clubfoot
Clubfoot is a complex deformity categorized into three types: Positional (mild and responsive to manipulation), Congenital (idiopathic and most common), and Syndromic (associated with other conditions). The standard treatment is the Ponseti method, which involves:
Stage 1 (Correction): Serial casting to gradually realign the foot structure.
Stage 2 (Maintenance): Bracing and exercises to restore muscle balance and prevent relapse.
Stage 3 (Monitoring): Long-term follow-up to address potential recurrence.
Idiopathic Scoliosis
Scoliosis is the most common spinal deformity in children, presenting as a three-dimensional problem involving lateral curvature, spinal rotation (causing rib asymmetry), and thoracic hypokyphosis. It typically appears following a preadolescent growth spurt.
Management requires a multidisciplinary team approach:
Bracing: Used for moderate curves during periods of active growth.
Surgery: Spinal fusion is indicated for severe, progressive curvatures.
Bone Disorders and Infections
Osteogenesis Imperfecta (OI)
OI is a group of heterogeneous inherited connective tissue disorders characterized by excessive bone fragility. Key clinical features include:
Defective periosteal bone formation and reduced cortical thickness.
Classic Signs: Blue sclera, multiple fractures, short stature, a triangular face, and hearing loss.
Management focuses on preventing complications through bisphosphonate therapy to strengthen bone density and rehabilitation to prevent contractures and maintain joint alignment.
Osteomyelitis
Osteomyelitis is an infectious process within the bone tissue, most commonly caused by Staphylococcus aureus. It can present as an abrupt onset of fever, swelling, and severe pain, often mimicking arthritis or leukemia.
Management Priorities:
Aggressive IV Antibiotics: Typically Nafcillin or Clindamycin for 3–4 weeks or longer.
Immobilization: Strict bed rest with limb immobilization.
Imaging: While X-rays may appear normal initially, MRI is the gold standard for showing detailed involvement.
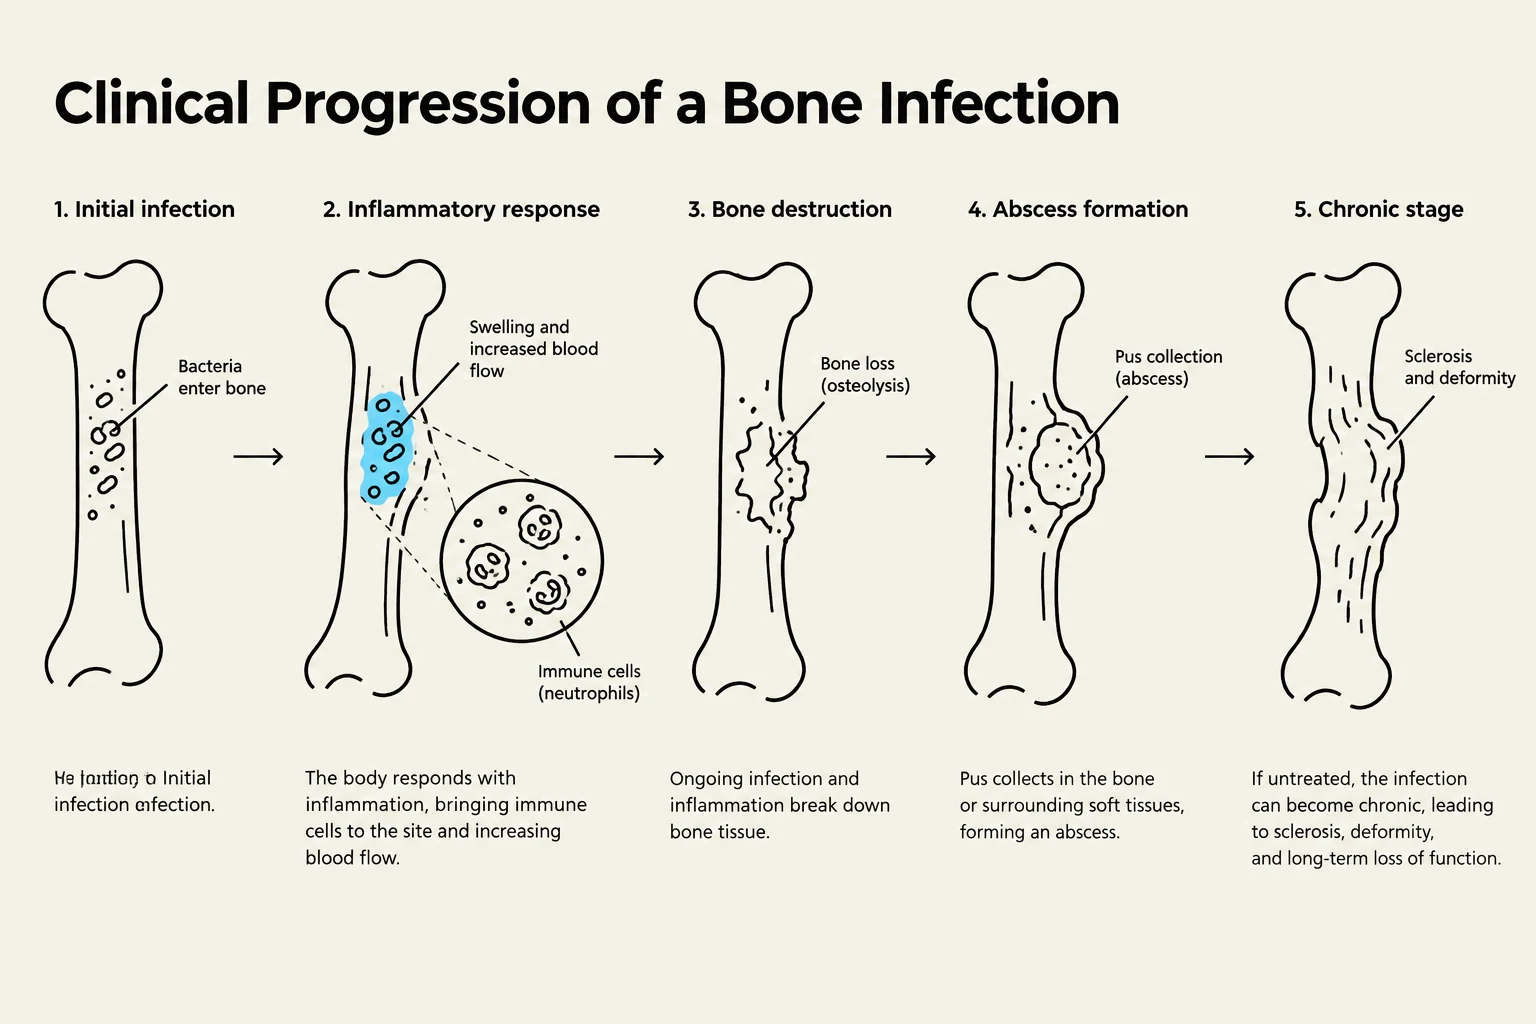
This diagram illustrates the five stages of clinical progression of a bone infection: initial infection, inflammatory response, bone destruction, abscess formation, and the chronic stage.
Injuries and Fractures
Soft-Tissue Injuries
Children frequently experience soft-tissue damage, which can be categorized as:
Contusions: Bruising from blunt force trauma resulting in ecchymosis and swelling.
Sprains: Injuries to ligaments caused by joint stress or trauma.
Strains: Musculotendinous injuries (muscle or tendon) often resulting from overuse.
Dislocations: Bone ends moving out of their normal socket alignment, which can risk blood supply to the femoral head in hip cases.
Pediatric Fracture Management
Children's bones heal faster than adults due to an active periosteum. However, they are uniquely susceptible to Greenstick fractures (incomplete breaks where one side bends) and Growth Plate (Epiphyseal) injuries. Damage to the growth plate is a critical concern as it can lead to limb length discrepancies or angular deformities.
Clinical Alert: The Six Ps of Fracture Assessment
To identify complications like Compartment Syndrome (a surgical emergency), nurses must systematically assess:
Pain: Intensity and tenderness.
Pallor: Skin color and perfusion.
Pulselessness: Distal pulses.
Paresthesia: Sensation distal to the site.
Paralysis: Ability to move distal to the injury.
Pressure: Signs of swelling/tension.
Inflammatory and Neuromuscular Conditions
Juvenile Idiopathic Arthritis (JIA)
JIA is a chronic inflammatory arthritis that typically peaks between ages 1 and 3. It is classified by the number of joints involved (Oligoarthritic vs. Polyarthritic) or by systemic features like high fever and characteristic rashes. Treatment aims to control pain, preserve function, and prevent joint destruction using NSAIDs, DMARDs, or biologics.
Duchenne Muscular Dystrophy (DMD)
DMD is a progressive neuromuscular disease. The primary goal of care is to maintain muscle function and prevent contractures.
Respiratory Care: As the disease progresses, children may require noninvasive positive-pressure ventilation or mechanical in-exsufflators (cough assist) to clear airways.
Cardiac Care: Regular echocardiograms are essential, as cardiomyopathy is a significant risk.
Practice Application
Case Study: Fracture Assessment
A 12-year-old child is admitted with a forearm fracture. Several hours after a cast is applied, the child complains of severe, unrelenting pain that does not respond to medication, and reports tingling and numbness in the fingers. The fingers appear pale and swollen.
What is the priority nursing action?
A. Elevate the arm above heart level.
B. Apply warm compresses.
C. Notify the healthcare provider immediately for possible fasciotomy.
D. Document and reassess in 1 hour.
Rationale: The symptoms (unrelenting pain, paresthesia, pallor) are classic signs of Compartment Syndrome, a surgical emergency that requires immediate medical intervention to prevent permanent tissue damage.
References
Rivera, L. M. Topic 6: Children with Musculoskeletal or Articular Dysfunction Part 2.
Topic 6: Children with Musculoskeletal or Articular Dysfunction Part 1.
Pediatric Orthopedic Conditions and Management.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.