An overview of the parathyroid glands, their role in calcium homeostasis, and the pharmacological management of conditions like hypoparathyroidism and hyperparathyroidism, including osteoporosis treatments.
The endocrine system is a complex network of ductless glands that release chemical messengers, known as hormones, directly into the bloodstream to maintain homeostasis. Among these, the parathyroid glands play a specialized and vital role in managing one of the body's most critical electrolytes: calcium. Because calcium is essential for nerve impulse conduction, muscle contraction, blood clotting, and membrane transport, even slight deviations in its concentration can lead to severe clinical consequences.
Parathyroid Gland Function and PTH
The parathyroid glands consist of two pairs of small, pea-sized glands located adjacent to the two lobes of the thyroid gland in the neck. Their primary responsibility is the secretion of Parathyroid Hormone (PTH).
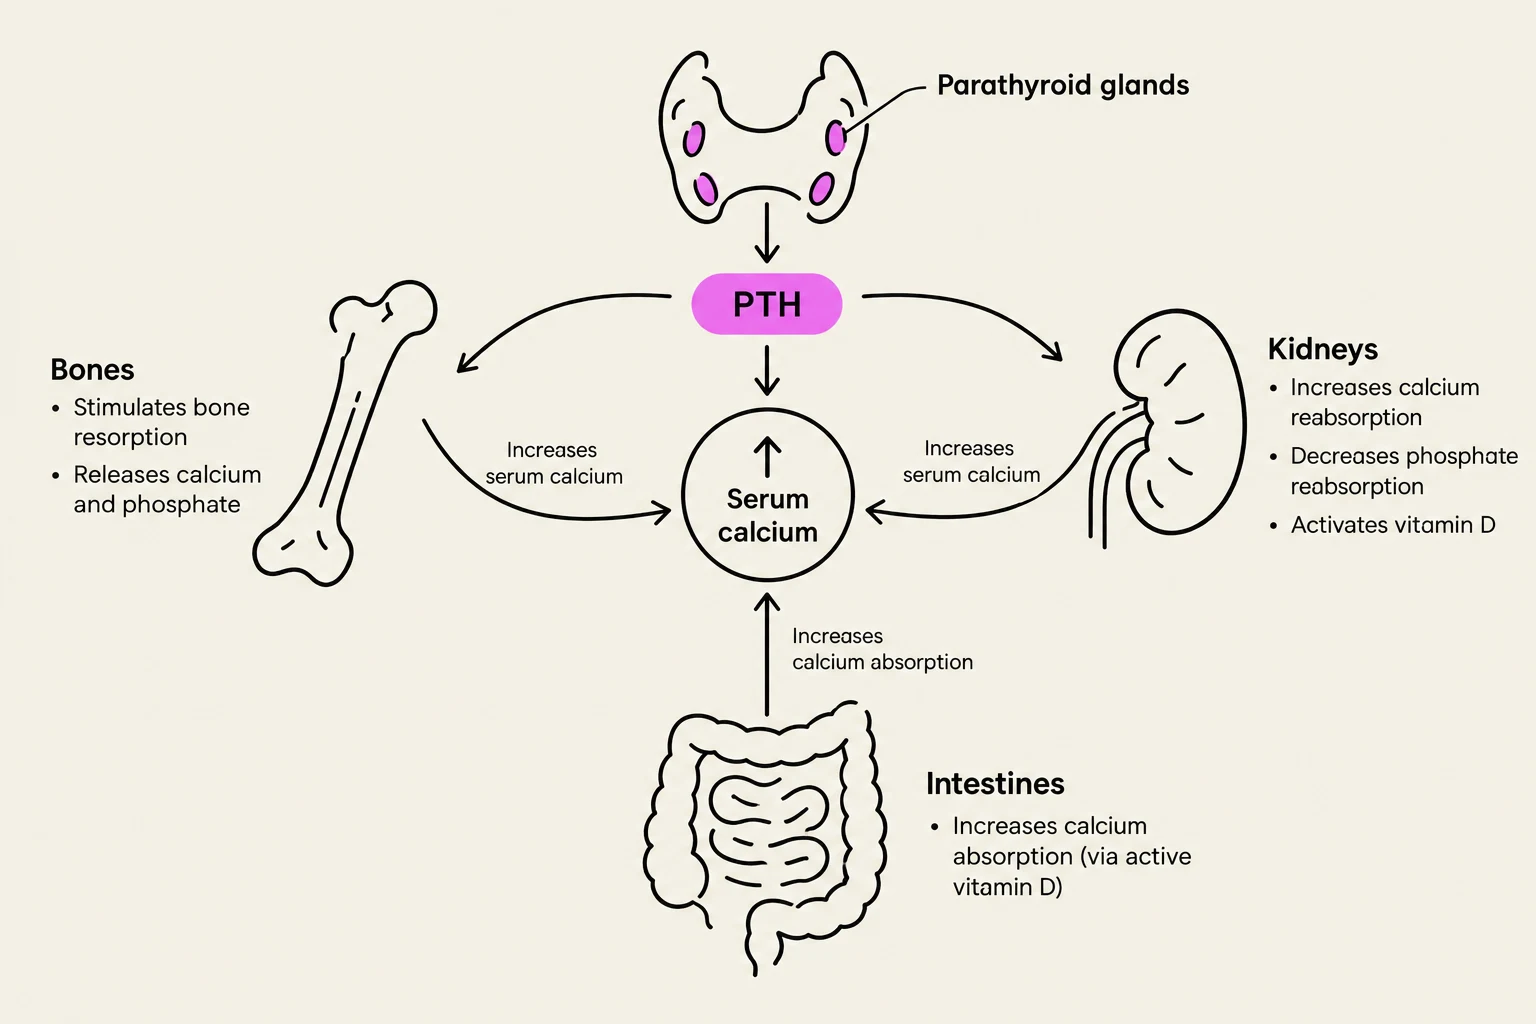
PTH acts as the body's primary regulator of serum calcium levels through three main mechanisms:
Bone Resorption: It stimulates the release of calcium from the bones into the bloodstream.
Renal Reabsorption: It enhances the kidneys' ability to reabsorb calcium rather than excreting it in urine.
Intestinal Absorption: It increases the absorption of calcium from the gastrointestinal tract by enhancing the effects of Vitamin D.
Diagram illustrating the role of parathyroid hormone (PTH) in regulating serum calcium levels by acting on bones, kidneys, and intestines.
Hypoparathyroidism and Hypocalcemia
Hypoparathyroidism is characterized by an absence or deficiency of PTH. This condition most commonly occurs due to the accidental removal of the parathyroid glands during thyroid surgery. The resulting lack of PTH leads to hypocalcemia (low serum calcium levels).
Clinical manifestations of hypocalcemia are often neuromuscular and cardiovascular in nature, including:
Muscular irritability and spasms
Tetany (involuntary muscle contractions)
Seizures
Cardiac dysrhythmias.
Pharmacological Management of Hypoparathyroidism
Treatment focuses on replacing the missing hormone or increasing calcium availability:
Calcium and Vitamin D supplements: The foundational therapy for increasing serum levels.
Calcitriol: A Vitamin D analogue that promotes calcium absorption from the GI tract and facilitates the secretion of calcium from bone into the bloodstream.
Natapara: A recombinant form of parathyroid hormone administered via subcutaneous injection.
Teriparatide (Forteo) and Abaloparatide (Tymlos): These are genetically engineered PTH or PTH-related peptides. While they are used to treat osteoporosis in postmenopausal women, they are relevant to parathyroid pharmacology due to their mechanism of action on bone metabolism.
Exam Tip: Monitoring for Hypoparathyroidism
When treating hypocalcemia, clinicians must monitor for signs of hypercalcemia (excess calcium), which include bone pain, anorexia, nausea, vomiting, thirst, constipation, lethargy, and bradycardia. Additionally, patients should avoid magnesium-containing antacids, as this increases the risk of hypermagnesemia.
Hyperparathyroidism and Hypercalcemia
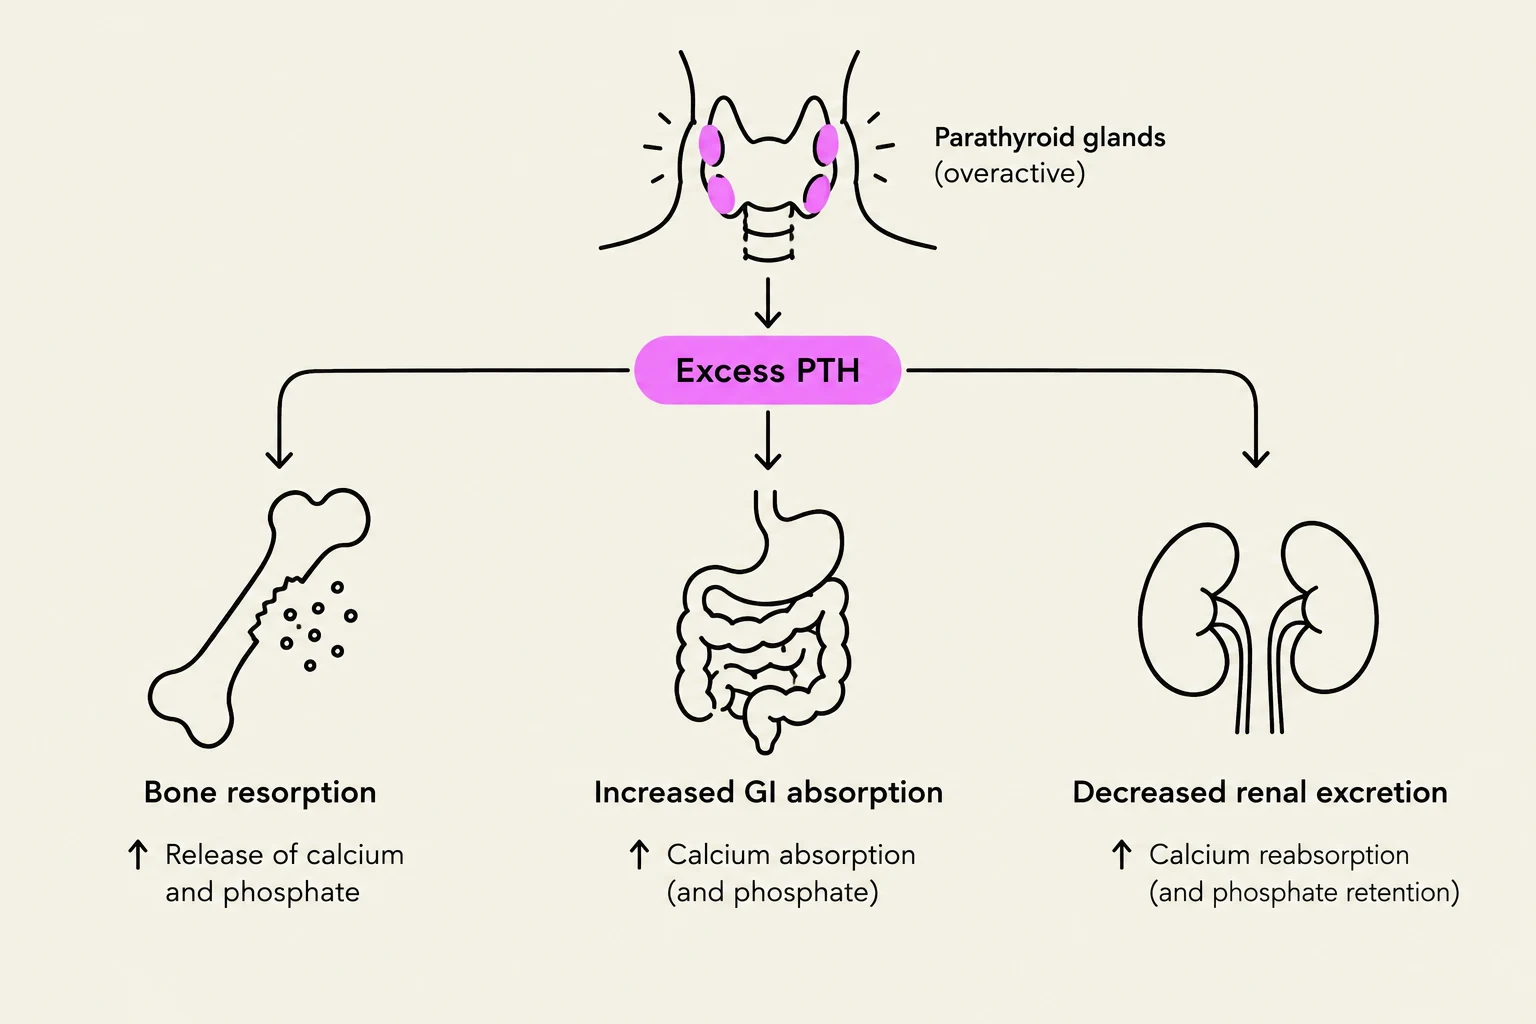
Hyperparathyroidism involves the excessive production of PTH. This can result from parathyroid tumors, ectopic secretion (such as from lung cancer), or genetic disorders.
The excess PTH causes a cascade of effects:
Increased calcium release from bones, which can lead to osteoporosis.
Increased calcium absorption from the GI tract.
Increased renal reabsorption of calcium.
The end result is hypercalcemia (high serum calcium levels).
Pharmacological Management of Hyperparathyroidism
Management aims to lower PTH levels or block its effects on target tissues:
Calcitonin salmon (Miacalcin): A hormone produced by the thyroid gland that acts as a counterbalance to PTH. It inhibits bone resorption and increases calcium excretion by the kidneys.
Cinacalcet (Sensipar): A calcium mimetic that lowers PTH levels, thereby decreasing serum calcium.
Paricalcitol: A Vitamin D analogue used specifically in patients with renal dysfunction to decrease PTH production.
Furosemide (Lasix): A diuretic used to increase the renal excretion of calcium, particularly when cardiac symptoms are present.
This diagram illustrates the effects of excess parathyroid hormone (PTH) on the body, including bone resorption, increased gastrointestinal absorption of calcium and phosphate, and decreased renal excretion of calcium and phosphate.
Osteoporosis Management
Osteoporosis is a condition of decreased bone density, often exacerbated by the bone resorption seen in hyperparathyroidism. While some drugs target the parathyroid gland, many osteoporosis treatments act directly on bone metabolism.
Bisphosphonates
Bisphosphonates (e.g., Alendronate, Ibandronate, Risedronate, Zoledronic acid) are a primary class of drugs used to slow both normal and abnormal bone resorption. Unlike PTH-related drugs, bisphosphonates act on serum calcium levels indirectly by slowing the breakdown of bone matrix.
Critical Nursing Intervention: Oral Bisphosphonate Administration
To prevent esophageal erosion, oral bisphosphonates (such as Alendronate) must be administered according to strict rules:
Take the medication upon arising in the morning.
Take with a full glass of water.
Do not take with any other food or medication for at least 30 minutes.
Remain in an upright position (sitting or standing) for at least 30 minutes after administration.
Monoclonal Antibodies
Denosumab (Prolia) is an alternative monoclonal antibody therapy used for bone density management.
Safety Considerations
When managing osteoporosis with these agents, clinicians must be aware of several risks:
Renal Dysfunction: Caution is required as many of these drugs are cleared by the kidneys.
Hypocalcemia: Bisphosphonates should not be used if a patient is already hypocalcemic.
Osteonecrosis of the Jaw: A rare but serious side effect associated with bisphosphonate therapy.
Femoral Fractures: Long-term use (over 5 years) may increase the risk of femoral shaft fractures.
Diagram illustrating two osteoporosis treatments: Bisphosphonates and Denosumab, detailing their mechanisms of action and administration.
Keep reading for free.
Create an account to finish this reading and make it part of your study routine.