This content explains volume expanders, including crystalloids, medications, and blood products, and their roles in managing fluid status, fluid compartments, and osmotic gradients within the body. It details common crystalloid solutions, their clinical uses and risks, and introduces advanced volume expansion methods l
In clinical practice, managing a patient's fluid status is a fundamental aspect of maintaining physiological stability. Volume expanders are a diverse group of substances used to manage total body water distribution and fluid compartments. This group includes crystalloids, medications (such as vasopressin), and blood products. Understanding how these substances interact with the body's internal compartments is essential for effective treatment of dehydration, shock, and electrolyte imbalances.
Understanding Fluid Compartments
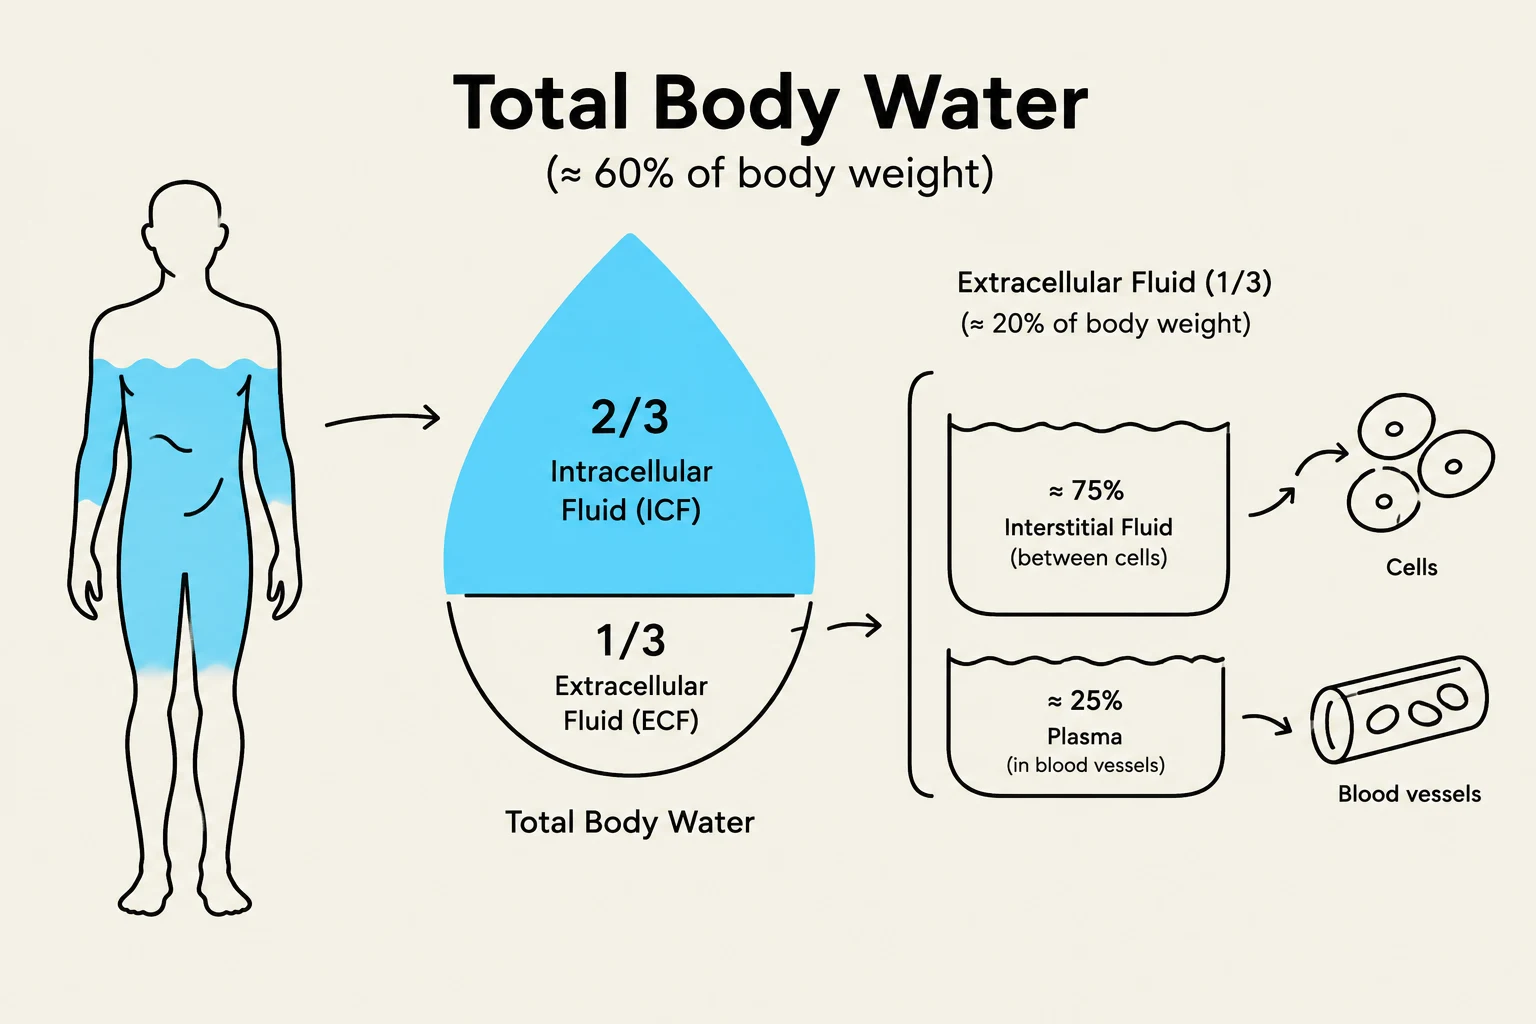
To understand how volume expanders work, one must first understand how water is distributed throughout the human body. In a healthy adult, water makes up approximately 60% of total body weight (TBW). This water is not just floating loosely; it is organized into specific compartments.
The body's water is divided into two primary domains:
Intracellular Fluid (ICF): This is the fluid contained within the cells, making up about 2/3 of the total body water.
Extracellular Fluid (ECF): This is the fluid outside the cells, making up about 1/3 of the total body water.
The Extracellular Fluid is further subdivided into two critical areas:
Interstitial Fluid (ISF): The fluid that surrounds the cells.
Intravascular Volume (IVF): The fluid contained within the blood vessels (plasma).
This diagram illustrates the distribution of total body water, showing that approximately 60% of body weight is water. This water is divided into intracellular fluid (ICF), making up 2/3 of the total, and extracellular fluid (ECF), making up 1/3. The extracellular fluid is further broken down into interstitial fluid (75%) and plasma (25% in blood vessels).
Osmolarity and Fluid Movement
The movement of water between these compartments is governed by the osmotic gradient. Water moves from areas of low solute concentration to areas of high solute concentration to achieve equilibrium. This movement is heavily influenced by the tonicity of the solution being administered.
There are three main types of solutions based on their tonicity relative to the cells:
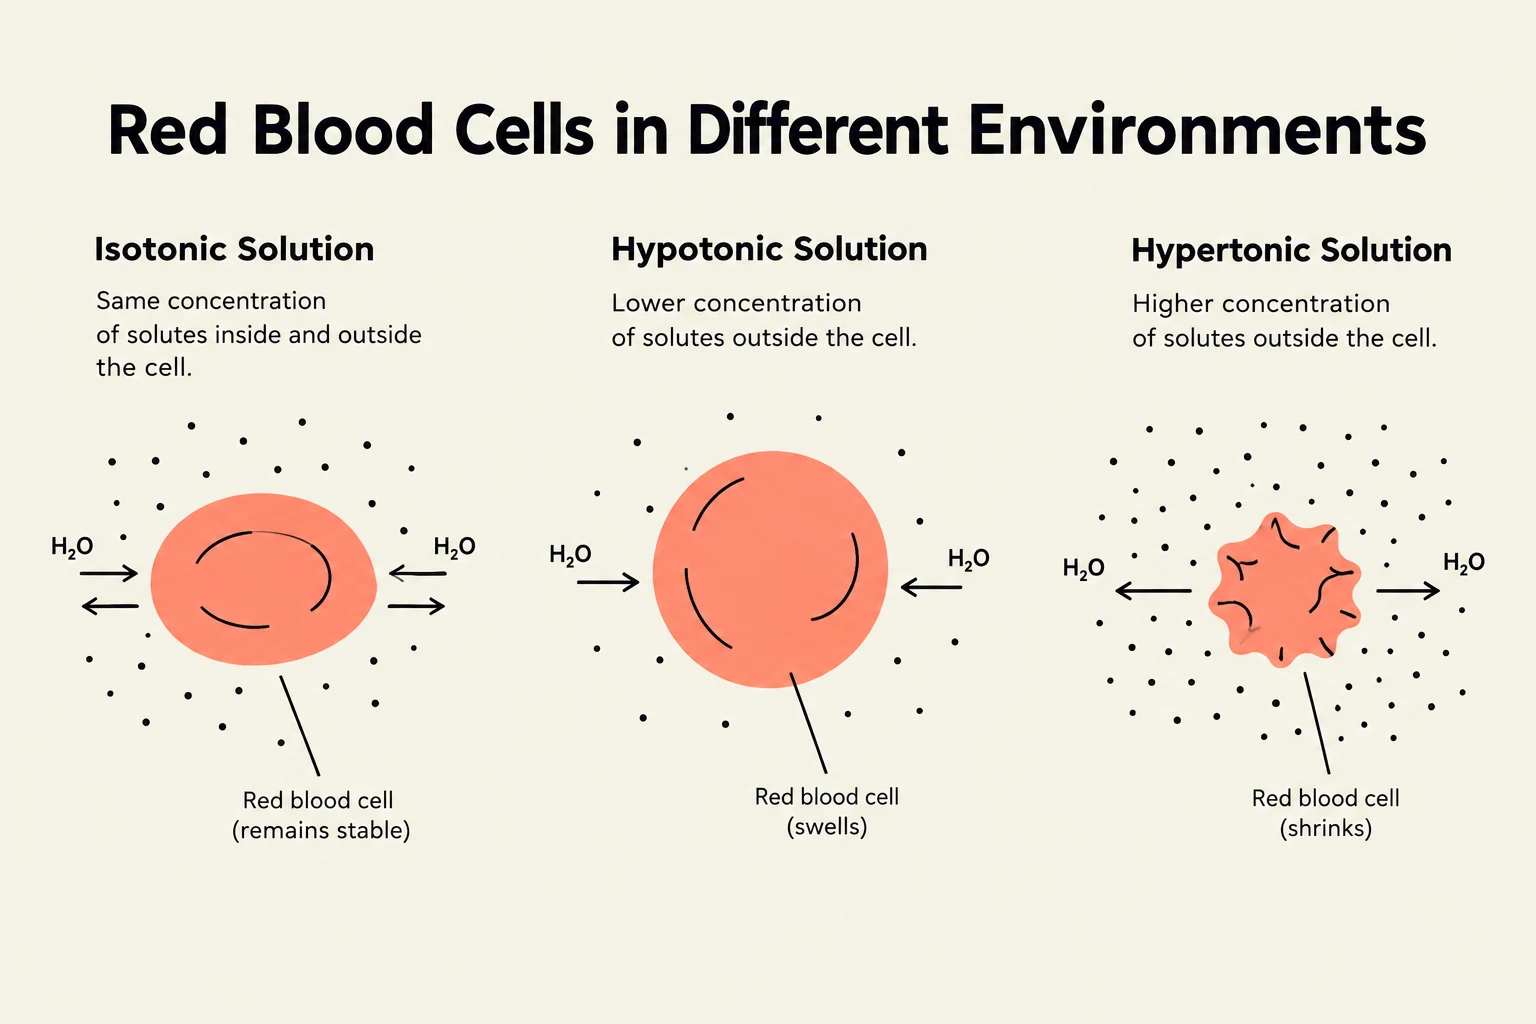
Isotonic Solutions: These have the same concentration of solutes as the intracellular fluid. Because there is no osmotic gradient, there is no net movement of water into or out of the cells.
Hypertonic Solutions: These have a higher concentration of solutes than the cells. This creates an osmotic gradient that pulls water out of the cells, causing them to shrink.
Hypotonic Solutions: These have a lower concentration of solutes than the cells. This causes water to move into the cells, which can lead to cell swelling or even bursting.
Diagram illustrating the effect of isotonic, hypotonic, and hypertonic solutions on red blood cells, showing how water movement affects cell shape and volume.
Crystalloids: The Foundation of Fluid Therapy
Crystalloids are solutions containing fluids and electrolytes that are normally found in the body. They are widely used because they maintain the osmotic gradient between the extravascular and intravascular compartments.
One of the primary advantages of crystalloids is that they do not contain proteins (colloids), which means there is no risk of viral transmission, anaphylaxis, or alterations in the patient's coagulation profile. Because of this, they are often better suited for treating dehydration rather than rapidly expanding plasma volume.
Common Types of Crystalloids
Crystalloids are categorized by their sodium chloride concentration:
Normal Saline (NS): A 0.9% sodium chloride solution. This is considered a physiologically normal concentration and is isotonic.
Half Normal Saline: A 0.45% sodium chloride solution.
Hypertonic Saline: Solutions with higher concentrations, such as 3% sodium chloride.
Lactated Ringer’s (LR) Solution: An isotonic solution that contains sodium chloride, sodium lactate, potassium chloride, and calcium chloride in water.
Dextrose 5% in Water (D5W): Often used for maintenance, though it behaves differently in the body due to the metabolism of dextrose.
Clinical Use and Risks
Crystalloids are commonly used as maintenance fluids to compensate for insensible losses, manage specific electrolyte disturbances, or promote urinary flow. They are also indicated in cases of acute liver failure, burns, renal dialysis, and shock.
However, clinicians must be wary of fluid overload. Because crystalloids can dilute plasma proteins, they may reduce the colloid osmotic pressure (COP). Furthermore, it takes a significant amount of fluid to expand the intravascular space; for example, it may take 5–6L of crystalloid to increase the plasma volume by only 1L. This can lead to side effects like peripheral or pulmonary edema.
Clinical Note: When administering large volumes of crystalloids, always monitor for signs of edema and respiratory distress, as these are indicators of fluid overload and potential pulmonary edema.
Advanced Volume Expansion: Colloids and Blood Products
When crystalloids are insufficient—particularly when a patient requires rapid plasma volume expansion or has low protein levels—clinicians turn to colloids or blood products.
Colloids
Colloids contain large protein substances that increase the colloid osmotic pressure (COP). This pressure helps pull fluid from the interstitial compartment back into the plasma compartment.
Albumin: A natural protein produced by the liver that is responsible for approximately 70% of the body's COP. It is prepared from healthy human donors and is used to treat shock and burns.
Dextran 40: A glucose-based solution used for volume expansion.
While effective, colloids can sometimes cause altered coagulation (increasing bleeding risk) or, in the case of dextran, rare instances of anaphylaxis or renal failure.
Blood Products
Blood products are the only class of fluids capable of carrying oxygen. They are used to increase tissue oxygenation and peripheral volume. Because they require human donors, they are the most expensive and least available fluid type.
Packed Red Blood Cells (PRBCs): Used to increase oxygen-carrying capacity in patients with anemia or significant blood loss.
Fresh-Frozen Plasma (FFP): Used to increase clotting factor levels in patients with deficiencies.
Whole Blood: Used in extreme cases (greater than 25% blood volume loss) because it contains both cells and plasma proteins, which help draw fluid back into the vessels.
Safety Alert: Blood transfusions carry significant risks, including incompatibility with the recipient's immune system, transfusion reactions, anaphylaxis, and the transmission of pathogens like HIV or Hepatitis. Always ensure proper crossmatch testing is performed.
Pharmacological Volume Management: Vasopressin
Beyond fluids and proteins, certain medications can influence fluid distribution by mimicking natural hormones. Vasopressin and Desmopressin are drugs that mimic the action of antidiuretic hormone (ADH).
These drugs act on the distal tubules and collecting ducts of the nephrons to increase water resorption, which concentrates the urine and can reduce water excretion by up to 90%.
Vasopressin: A potent vasoconstrictor used in hypotensive emergencies (like septic shock), pulseless cardiac arrest, and to stop bleeding from esophageal varices.
Desmopressin: Primarily used for the treatment of diabetes insipidus, Hemophilia A, and Type 1 von Willebrand disease.
Nursing Implications
When managing volume expanders, nurses play a critical role in patient safety. Key responsibilities include:
Comprehensive Assessment: Obtain thorough medication histories and document baseline height, weight, and vital signs.